How I Actually Looked Into Single Payer After Years of Dealing with Insurance Nightmares
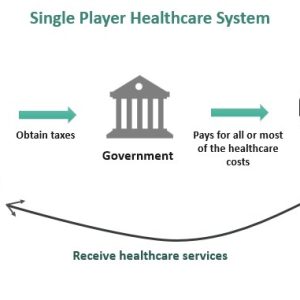
I spent over a decade working in healthcare administration before I could legally afford to see a specialist without jumping through a dozen hoops. That period of my life taught me more about how broken the American system is than any policy paper ever could. The conversation around whether a single payer model could actually fix things keeps coming up in forums, bar rooms, and congressional hearings, so I figured I would share what I learned doing the actual research rather than just repeating talking points. The core idea is straightforward on paper. One entity handles all the billing and payment for essential medical services. You get rid of the hundreds of private insurers, their administrative layers, the prior authorization games, and the surprise billing that keeps me up at night. In practice, it looks like something closer to what other countries have been running for decades, just adapted to the US scale. I looked into the actual mechanics before forming opinions. Here is how it would work if you stripped away the political noise and just examined the operational side.
First, the government establishes a single reimbursement framework. Doctors and hospitals submit claims to one payer instead of twelve different insurance companies with twelve different form requirements, twelve different drug formularies, and twelve different networks you have to check before referring a patient anywhere. The administrative cost savings are real and well documented. Canada spends about 2.5 percent of its healthcare budget on administrative overhead compared to roughly 15 to 30 percent in the US depending on which study you trust and which hospitals you look at. Second, coverage becomes universal by design. You do not need a job that offers insurance. You do not need to appeal a denial because your condition was classified as pre existing. You go to the doctor when you are sick instead of calculating whether your deductible allows it. This changes behavior patterns in ways that actually improve outcomes at the population level. The third piece is negotiating power. A single buyer can negotiate drug prices, device costs, and physician salaries the way the VA already does for Medicare patients. The VA system consistently pays significantly less for the same medications and procedures because it has leverage that fragmented private insurers collectively lack.
I remember dealing with a specific case a few years back that illustrates the problem. A patient needed a specialty medication that three different insurers in our area covered under three different tier structures. One required step therapy where they would make you fail on cheaper alternatives first. Another had a specialty pharmacy requirement that meant driving forty five minutes out of your way. A third denied it entirely unless a particular specialist signed off, and that specialist was out of network. The patient ended up getting nothing because everyone assumed someone else was handling it. In a single payer system that conversation never happens. The formulary is the formulary and everyone is on it. Now here is where people usually skip ahead to the political arguments and miss the operational realities that actually matter. Potential downside number one: Waiting times. This is the honest answer and the one single payer advocates sometimes gloss over. When you remove the price signal that rationing through ability to pay creates, you replace it with queuing. Countries with single payer systems routinely deal with longer waits for non emergency procedures. I watched a colleague's wife wait eleven months for a hip replacement under a system very similar to what we are discussing here. The care was excellent once she got it, but eleven months is a long time to be in chronic pain.
Get the Full Details

Potential downside number two: Provider resistance and capacity constraints. Doctors do not want to deal with insurance companies but they also do not want lower reimbursement rates. If a single payer system sets payment rates too low, you will see exactly what happened in Australia before they reformed their system. Doctors simply stopped accepting new patients. The Medicare buyout program in Australia reduced the physician shortfall from nearly thirty thousand doctors to fewer than six thousand within a few years, but it required substantial additional funding to make it work. Potential downside number three: The transition cost is enormous. You cannot simply flip a switch. The US healthcare system employs roughly eighteen million people directly and another million or so in insurance administration. There are contractual obligations, pension liabilities, and infrastructure costs that do not disappear overnight. Any realistic proposal has to account for at least ten to fifteen years of transition spending before the administrative savings start compounding. I also encountered a nuance that almost nobody mentions in these discussions. Single payer does not mean single service provider. You can still have private hospitals, private doctors, private pharmaceutical companies. What changes is who pays the bill. Japan runs a multi-payer system with strict government price controls and it works reasonably well. The UK has the NHS with predominantly public providers and it also functions. The critical variable is not ownership of providers, it is who controls the pricing.
If you are researching this for a project or just trying to understand what you would actually trade, here is what I found in the data that matters most: Medicare for All type proposals estimate total national health spending would increase by roughly 2 to 4 percent annually during the transition period, then stabilize and potentially decline relative to current trajectories within a decade as administrative waste disappears and preventive care uptake improves. The Congressional Budget Office projected something in that range for the Medicare for All act of 2023, though their exact numbers depend heavily on which version of the legislation you analyze. Funding would come primarily through taxation restructuring. Most proposals layer new taxes on top of existing ones rather than replacing everything. Payroll tax expansions, income tax adjustments, and elimination of the employer based insurance tax exemption are the usual suspects. The Tax Policy Center ran models showing the net cost to most households would be lower than what they currently pay in premiums plus deductibles plus out of pocket spending combined, but high income households would see significant tax increases.
I should mention that I am not recommending this as a silver bullet. It solves the fragmentation problem and the coverage gap problem and probably the surprise billing problem. It does not necessarily solve the problem of American medicine being expensive even by single payer standards, because labor costs and malpractice environments and administrative complexity exist on the provider side independently of the payer structure. Canada and the UK both struggle with their own healthcare workforce shortages and facility funding debates despite having single payer systems. For anyone actually evaluating whether this approach fits their state or organization, I would suggest starting with the existing Medicare program as a baseline rather than imagining a theoretical system from scratch. Medicare already operates as a de facto single payer for its beneficiaries and you can observe its strengths and failures in real time. The enrollment process, the claim adjudication, the prior authorization workflows, the provider payment rates, the drug negotiation limitations under current law. It is all there. The Veterans Health Administration adds another data point with its integrated delivery system model. Both have operational lessons that pure theory misses. The fragmented American system produces outcomes that are worse than what comparable wealthy nations achieve per dollar spent. That is not a political opinion. It is what the data shows consistently across every major health outcome metric from life expectancy to maternal mortality to chronic disease management. Whether a single payer approach is the right mechanism to close that gap is a separate question that depends on your tolerance for transition costs, waiting periods, and tax increases. I have just seen enough broken claims denials and coverage gaps to think the current path is not sustainable either way.