What A Dialysis Tech Actually Does Day to Day
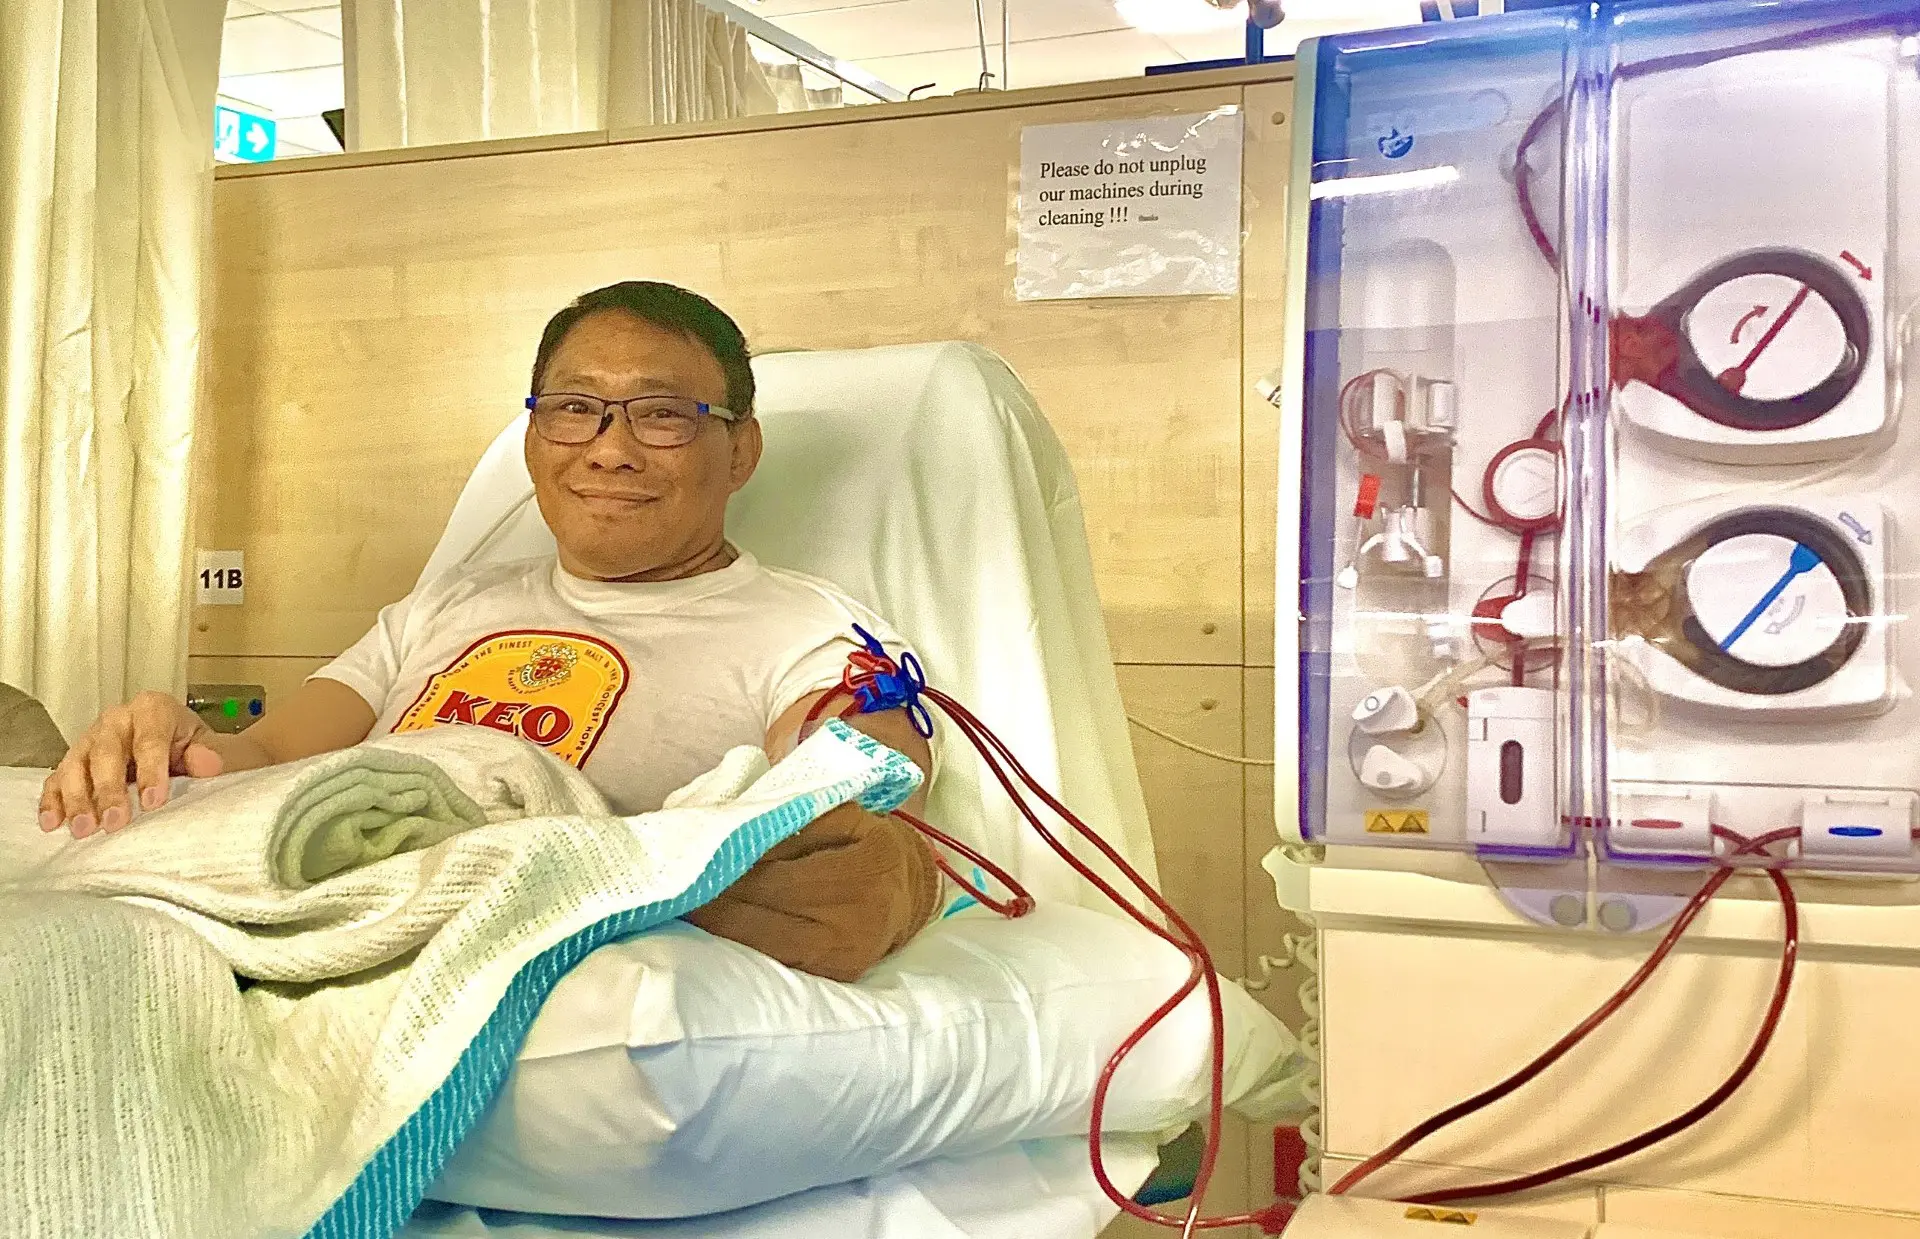
A dialysis technician runs machines that filter blood when kidneys fail. That is the headline version. The real job involves far more monitoring, troubleshooting, and patient management than most people expect. Most sessions last three to four hours, and the tech is the person in the room the entire time, watching pressures, blood volumes, and patient vitals without taking a break from it. The core responsibilities break down into setup, treatment, and shutdown. Before the patient arrives, you prime the dialyzer, check all connections, run the machine self-test, and verify the dialysate concentration. Then you access the patient — usually through a fistula, graft, or central line — and get the circuit running. During the session, you document vital signs every thirty to sixty minutes depending on facility policy, watch for hypotension, cramping, or air embolism signs, and adjust ultrafiltration rates as needed. After treatment, you flush the lines, disconnect, and run the disinfection cycle on the machine. I have seen new techs treat the machine as the patient and forget the person attached to it. That mistake shows up fast when a patient goes hypotensive and nobody notices until they are already dizzy and nauseous. The machine beeps at the end of its warning window. You are supposed to be catching problems before that beep.
Beyond the routine, you handle vascular access assessments, which means palpating fistulas for a thrill and listening with a Doppler for a bruit. A declining thrill usually means stenosis is developing, and the patient needs a referral before the access clots off completely. I once caught a graft with a progressive bruit on a Tuesday afternoon. We flagged it, got an intervention cardiology appointment scheduled by Thursday, and that same graft would have thrombosed over a long weekend if we had just written it off as a bad stick that one morning. You also manage medications during treatment. Heparin or citrate anticoagulation, labetalol for blood pressure spikes, dextrose for hypoglycemia, saline boluses for drops in pressure. You are not prescribing, but you are implementing protocols that your nurse or medical director has on file. Knowing which drug does what and recognizing the right moment to administer it separates a tech who rides out complications from one who creates them through hesitation. Documentation is a massive part of the role. Each treatment generates a record of pre- and post-weight, ultrafiltration goals versus actual removed, anticoagulant dosing, any adverse events, and machine parameters. These records feed into CMS reporting and Medicare audits. Incomplete or inaccurate documentation gets facilities cited. It also leaves you exposed legally if something goes wrong and there is no clear chart trail showing you followed protocol.
One thing nobody warns you about is the physical demand. You are on your feet for eight-hour shifts, often lifting or repositioning patients who cannot transfer themselves. I worked a unit where two of our regulars were bariatric and required a Hoyer lift for every session. Without the lift properly positioned and the sling secured before you even touch the needle, you are risking injury to both the patient and yourself. We lost a tech to a lower back strain in our first year because the facility was slow on ordering the right equipment. That is a fixable problem, but it only gets fixed when someone reports it instead of just working around it until they are done. There are also the interpersonal layers. Dialysis patients come in three times a week for years. You learn their routines, their moods, their families, their fears. Some become hostile when access is difficult. Others depend on you emotionally in ways that are hard to articulate. Setting boundaries matters. You are not their therapist, but you are often the most consistent adult interaction they have all week. Handling that without burning out takes deliberate practice. The certification pathway varies by state. In many places you need a high school diploma or GED, completion of a certified dialysis technician program, and then you can sit for the CHT or CCHT exam through BONENT or NHA. Some states require additional licensure. Check your specific board because the requirements shift and a facility hiring you will verify compliance before they hand you a badge.
Get the Full Details

Salaries sit somewhere between $40,000 and $60,000 annually depending on location, experience, and whether you work nights or weekends. It is not glamorous money, but the job has steady demand and relatively low barriers to entry compared to other healthcare roles. Turnover is high though, partly because of the emotional weight and partly because the work is repetitive enough that it becomes draining if you do not find ways to stay engaged. If you are considering this career, go into a clinic and watch a full treatment cycle before you commit. Sit in on a shift. Ask the tech what they wish they knew before starting. Most will tell you the same thing: the technical skills are learnable, but the judgment part — knowing when to push a bolus versus when to hold off, when to call the nurse versus when to manage it yourself — comes from doing it repeatedly and paying attention to what happens when you get it wrong. The field is not perfect. Staffing shortages are chronic in many regions. Regulatory burden keeps growing. Machine failures happen, usually at inconvenient moments, and you are the one expected to troubleshoot while keeping a patient stable. But the work matters in a direct, measurable way. Every session you run keeps someone alive who would otherwise be facing a transplant list or decline. That is not a motivational poster. It is just the math of the job.