Understanding Kyphosis: Beyond the Hunchback Stereotype
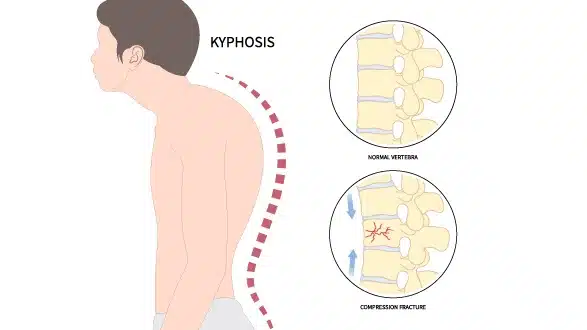
Kyphosis is simply an excessive outward curvature of the thoracic spine that creates a rounded upper back. The normal thoracic curve measures between 20 and 45 degrees. Anything exceeding 50 degrees is classified as abnormal kyphosis. This is straightforward biomechanics, not mysticism. I encounter this condition constantly in clinical practice, and most people who present with it are worried unnecessarily about dramatic deformity when their actual problem is far less severe. The way I approach any kyphosis case starts with identifying the type before discussing treatment. There are several distinct categories and they respond very differently to intervention. Postural kyphosis is by far the most common, particularly in adolescents and young adults. It develops from prolonged sitting, poor ergonomics, and weak core musculature. The curvature corrects when the person lies flat or actively extends their spine. Structural kyphosis does not correct with positioning. That distinction alone determines whether conservative management will work or whether surgical evaluation becomes necessary.
Unveiling The Mysterious World Of Kyphosis Causes Symptoms And Treatment Options
Causes Breakdown by Type
Postural kyphosis stems from muscular imbalance. The thoracic extensors become lengthened and weak while the pectoral muscles tighten and shorten. Rounded shoulders and forward head posture accompany this pattern. Screen time exacerbates the condition significantly. Most office workers and students develop some degree of this posture pattern by their mid-twenties. Scheuermann's kyphosis is the second most common structural cause. It affects adolescents during growth spurts, typically between ages 10 and 15. The vertebral bodies fail to develop properly during formation. Instead of maintaining a rectangular shape, the anterior portion of the vertebra grows less than the posterior portion. This deformity accumulates across multiple vertebrae, creating the characteristic sharp angular kyphosis. About 5 percent of adolescents develop this condition. Girls and boys are affected roughly equally, though girls tend to present with more severe curves. Congenital kyphosis results from vertebral malformation during fetal development. The spine fails to form correctly in utero. This type is rare but clinically significant because it often progresses rapidly as the child grows. Congenital kyphosis requires surgical consultation regardless of curve magnitude because the deformity will worsen with skeletal maturation. I once evaluated a seven-year-old with a congenital K-type hemivertebra at T8. The curve measured 42 degrees at presentation and had progressed 18 degrees in just eight months. Observation was not an option.
Osteoporotic kyphosis affects elderly patients, predominantly women. Vertebral compression fractures from weakened bone alter spinal alignment. Each fractured vertebra loses height anteriorly, increasing thoracic kyphosis incrementally. This is a cumulative process. Multiple compression fractures over years produce progressive worsening. Weight-bearing exercise and adequate calcium and vitamin D intake matter more for prevention than most patients realize. Neuromuscular kyphosis occurs secondary to conditions like cerebral palsy, muscular dystrophy, and spinal cord injury. Muscle weakness and spasticity create asymmetric forces on the spine. Scoliosis frequently accompanies neuromuscular kyphosis. These cases are complex because the underlying neurological condition limits treatment options. bracing provides minimal benefit and surgery carries substantial risk in this population.
Get the Full Details

Symptoms and Clinical Presentation
Mild kyphosis often produces no symptoms at all. The curvature is visible but painless. This is important because many patients discover their kyphosis incidentally through photographs or casual observation rather than medical complaints. Severe kyphosis creates visible postural changes. A pronounced hump on the upper back is the classic sign. Shoulder blades may protrude noticeably. The head positions forward relative to the shoulders. Clothing fits differently across the upper back. Pain is not a universal feature of kyphosis. When it does occur, it typically presents as mechanical back pain in the thoracic region. The pain worsens with prolonged standing or sitting and improves with lying down. Some patients report muscle fatigue and stiffness. Nerve-related symptoms appear in more severe cases. Radiculopathy, numbness, or weakness in the extremities suggests spinal cord or nerve root compression. This is a red flag that warrants immediate imaging and specialist referral. I encountered a 68-year-old male with progressive gait disturbance and bilateral leg weakness who was initially dismissed as having lumbar spinal stenosis. His thoracic kyphosis measured 78 degrees. The real problem was thoracic myelopathy from cord compression at the apex of the kyphotic curve. He required decompression surgery to prevent permanent neurological damage. Never assume leg symptoms originate from the lumbar spine without evaluating the entire spinal column.
Diagnostic Approach
Diagnosis begins with a physical examination. The Adam's forward bend test remains the standard screening method. The patient bends forward at the waist while the examiner observes the back from behind. Asymmetry in the rib cage becomes apparent with kyphosis. A kyphometer or inclinometer measures the degree of curvature directly on the skin surface. This simple tool provides a reasonable estimate without radiation exposure. Standing full-spine X-rays confirm the diagnosis and quantify the curve. The Cobb angle measurement is the gold standard for determining severity. Measurements below 50 degrees in the thoracic spine generally indicate mild kyphosis. Curves between 50 and 75 degrees are moderate. Curves exceeding 75 degrees are severe and more likely to cause functional impairment. CT scans and MRI studies become necessary when congenital abnormalities or neurological symptoms are suspected. Bone density testing through DEXA scan is essential for older patients with kyphosis. Osteoporosis may be the underlying cause or a contributing factor. Identifying and treating bone loss prevents further vertebral compression and curve progression.
Treatment Options by Severity
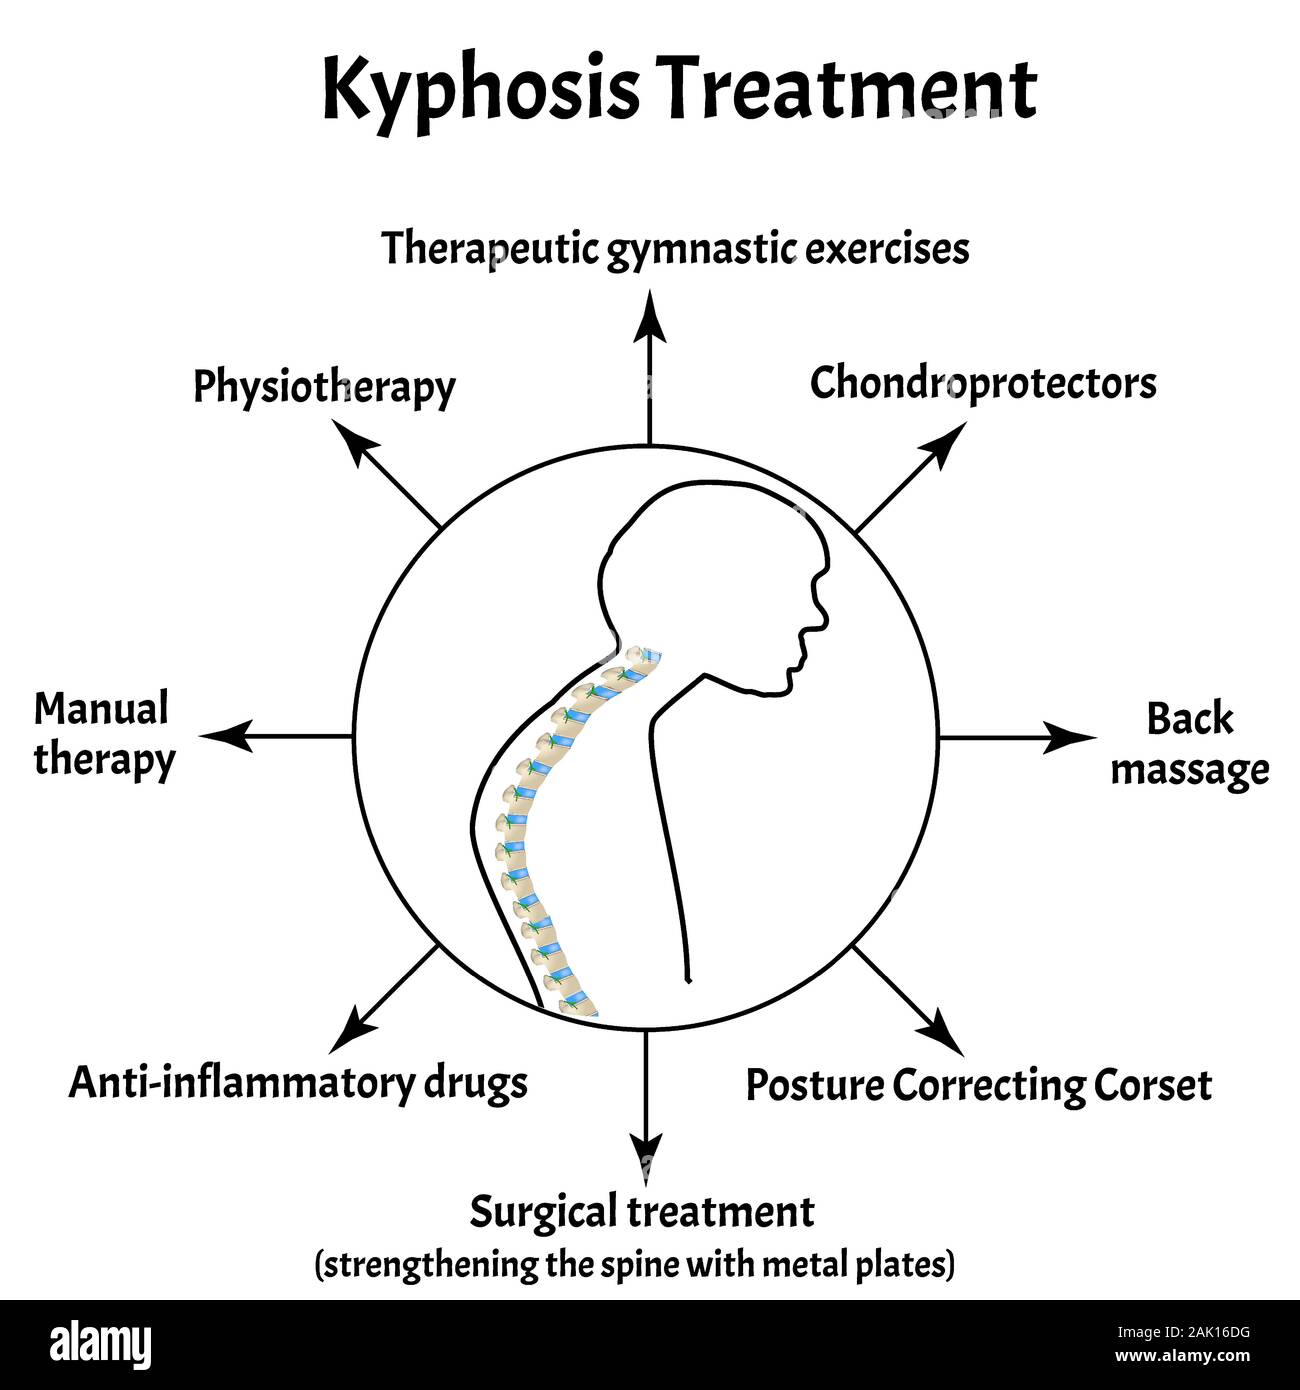
Mild postural kyphosis under 50 degrees responds well to physical therapy and postural retraining. Specific exercises target the weakened thoracic extensors and scapular stabilizers while stretching the shortened pectoral muscles. McKenzie extension exercises, rows, and prone Y raises form the foundation of treatment. A structured program typically requires three to four months of consistent exercise before meaningful postural changes become apparent. Patient compliance determines outcomes more than the specific exercise selection. Moderate kyphosis between 50 and 75 degrees in growing adolescents may benefit from bracing. Thoracolumbosacral orthoses limit spinal flexion and provide external support. Bracing is most effective during growth spurts when the spine is still developing. The average treatment duration ranges from one to three years until skeletal maturity is reached. Compliance with brace wear is critical. Patients who wear their brace fewer than 16 hours per day achieve significantly worse outcomes. I have seen teenagers remove their braces at night and sneak them into backpacks during school. This is unfortunately common and undermines the entire treatment plan. Surgical intervention becomes necessary for severe kyphosis exceeding 75 degrees, progressive curves, or cases with neurological compromise. Posterior spinal fusion with pedicle screw fixation is the standard surgical approach. Osteotomies may be required to correct rigid deformities. Vertebral body resection and reconstruction address congenital cases. Surgical correction typically achieves 40 to 60 percent reduction in the kyphotic angle. Recovery involves six to twelve months of restricted activity and gradual return to normal function.
For osteoporotic compression fractures causing kyphosis, vertebroplasty and kyphoplasty can restore vertebral height and reduce pain. These minimally invasive procedures involve injecting bone cement into the fractured vertebra. Pain relief is usually immediate. The long-term benefit for curve correction is modest. These procedures address the acute fracture but do not reverse established kyphosis. They work best when performed within weeks of the fracture event.
What Most People Miss
Not all kyphosis requires treatment. Mild postural kyphosis in adults who are asymptomatic does not progress. The fear-mongering around "hunchback" imagery inflates anxiety far beyond the actual medical risk. Many people live their entire lives with mildly increased thoracic kyphosis and never develop complications. The goal is functional improvement and pain reduction, not perfect radiographic alignment. Another overlooked point: bracing in adults with mature skeletons is essentially useless. Once growth plates close, the spine does not respond to external orthotic forces. Adults with structural kyphosis should focus on strengthening and pain management rather than wasting money on braces that cannot change their spinal alignment. Surgical discussion is appropriate only for severe, symptomatic, or progressive cases. The most effective prevention strategy is simple but rarely followed. Maintain neutral spine posture during daily activities. Set up workstations so monitors sit at eye level. Take movement breaks every 30 minutes during prolonged sitting. Strengthen the upper back and core regularly. These habits prevent postural kyphosis from developing in the first place and are far cheaper than any treatment.
Kyphosis management comes down to accurate classification and matching treatment intensity to the actual severity. Most cases are postural and respond to targeted exercise. Structural and congenital cases require specialist care. Surgery remains a last resort for the most severe presentations. The information available online about kyphosis tends to oscillate between alarm and oversimplification. Neither extreme serves patients well. Getting an accurate diagnosis and appropriate treatment plan from a qualified healthcare provider is the only reliable path forward.