Understanding Surgical Repair for Complete Bilateral Cleft Lip and Palate
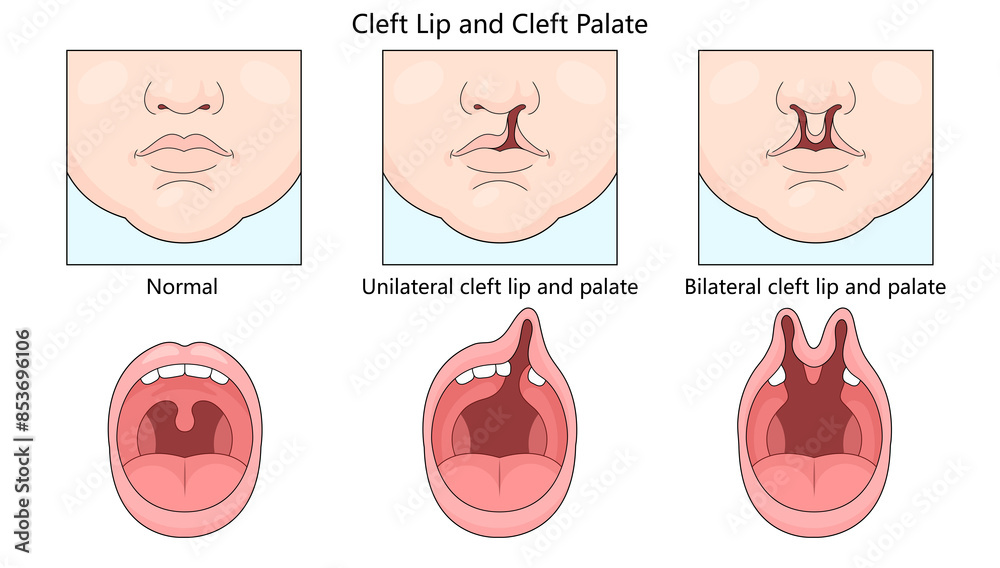
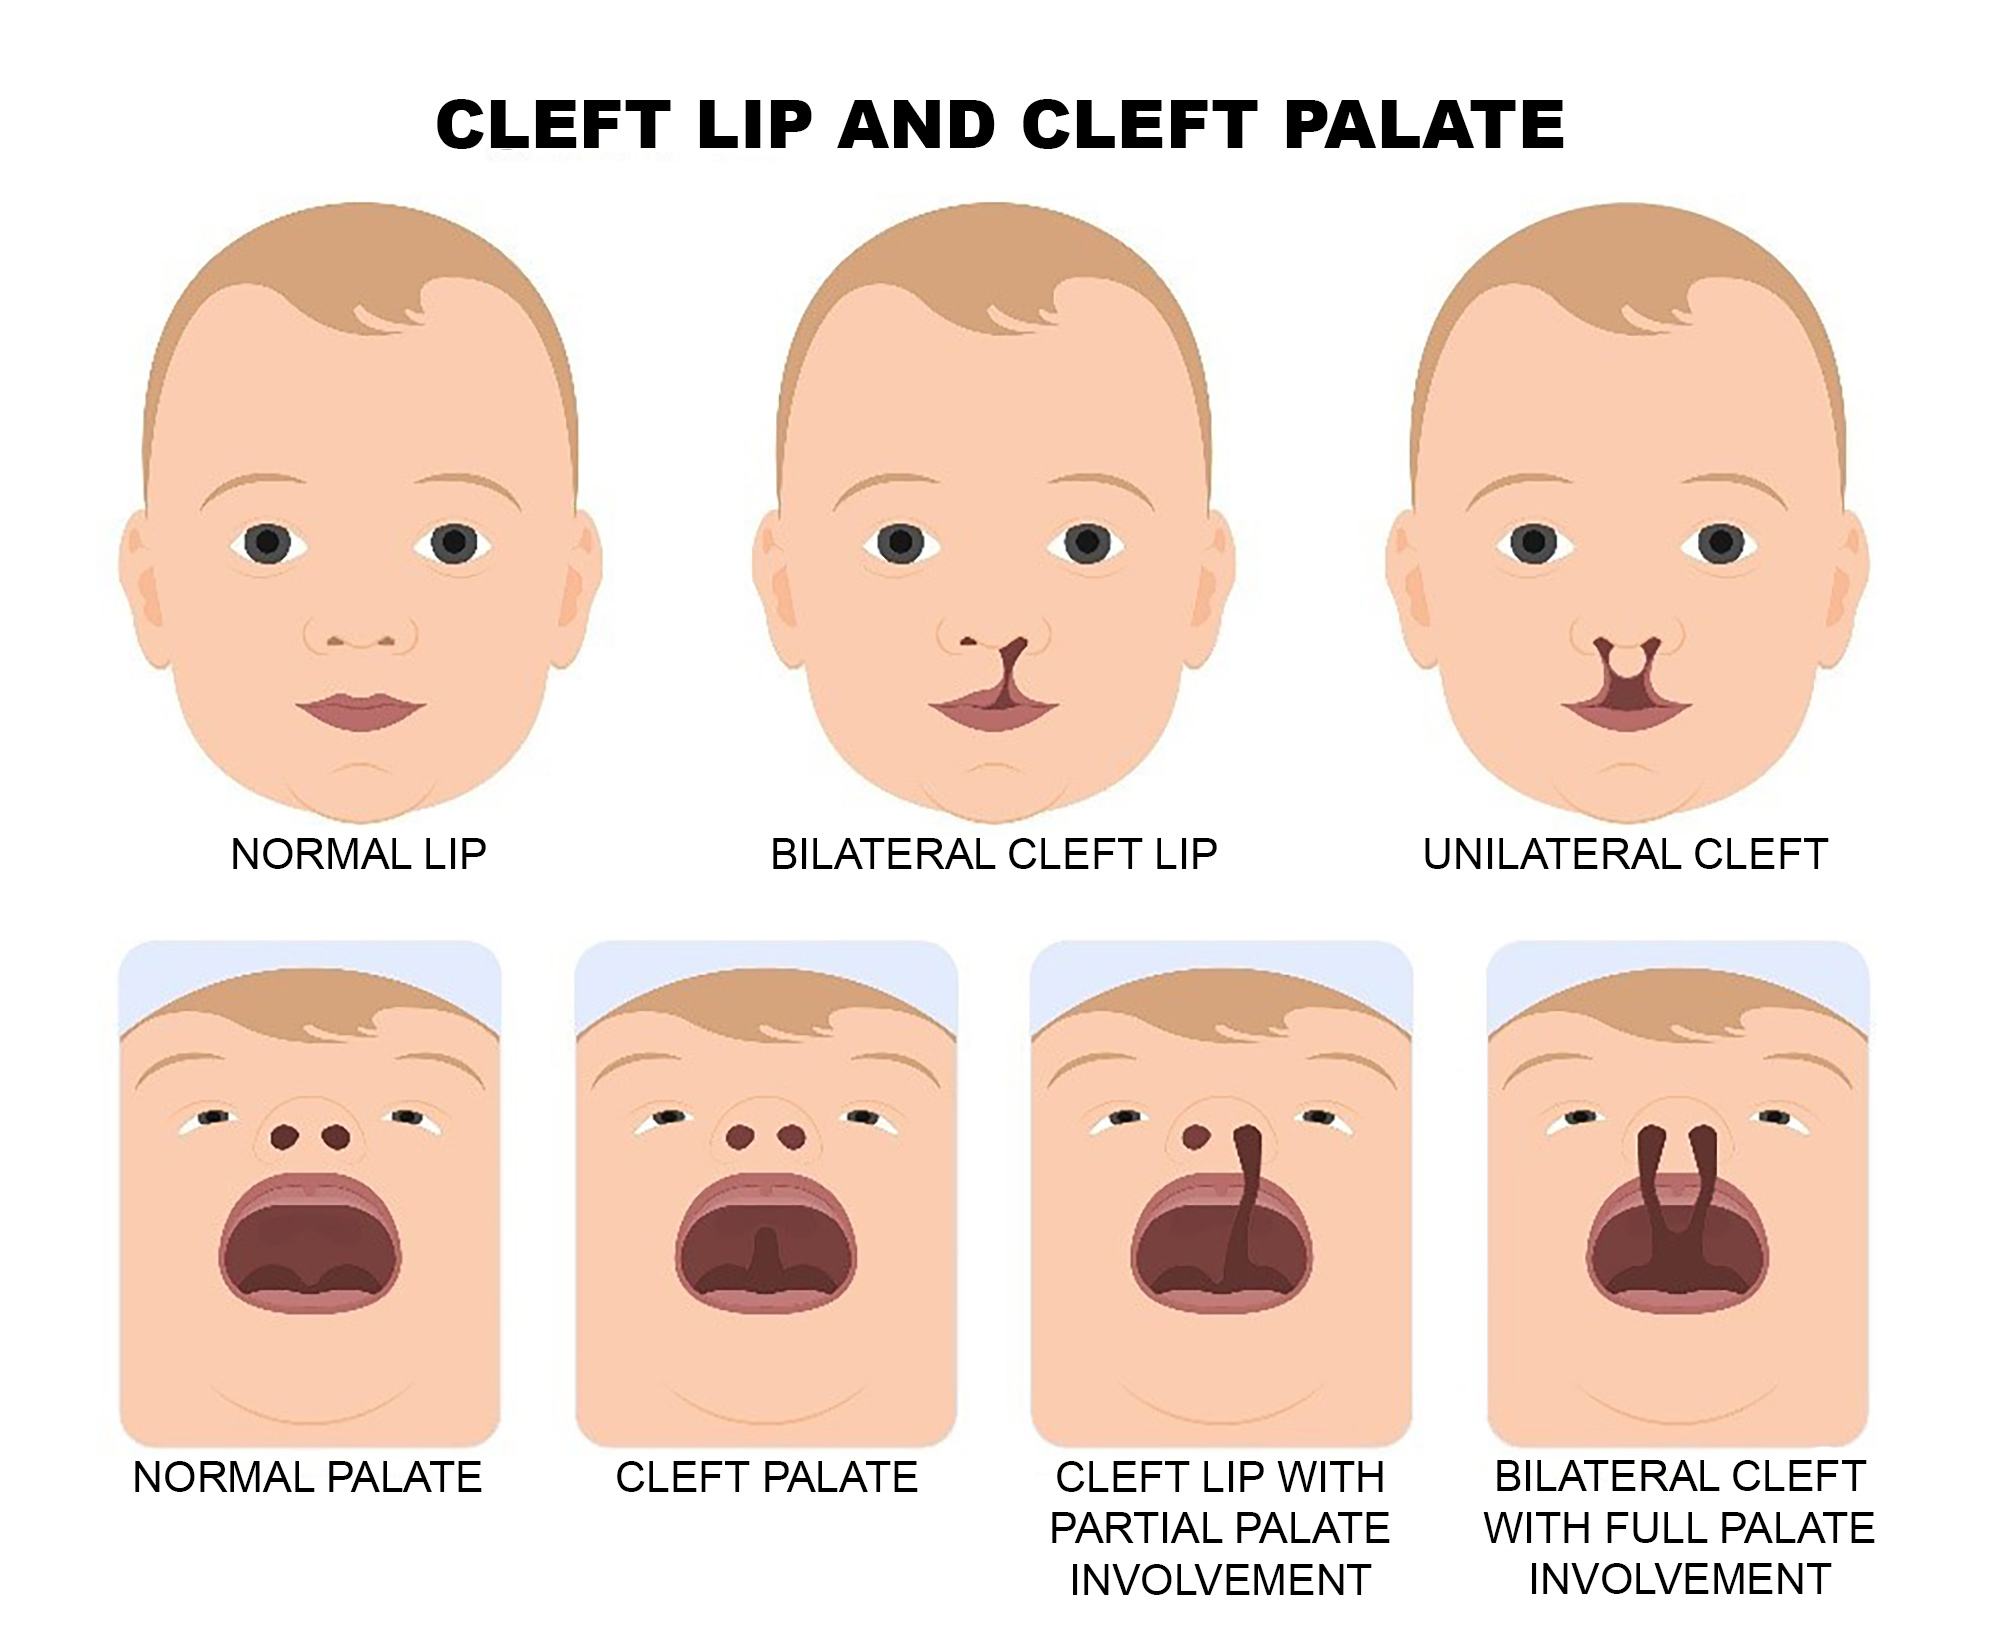
A complete bilateral cleft means the separation runs through both sides of the upper lip and extends into the palate, creating a gap that affects feeding, speech development, and facial growth. I have worked with dozens of these cases over the years, and the complexity often surprises people who only encounter simplified explanations online. The condition itself is straightforward to identify — both sides of the lip are cleft, and the premaxilla sits protruding between them — but managing it requires careful sequencing of surgeries and a long-term view of craniofacial development. The core challenge with bilateral cleft repair is not just closing the gap. You are working against tissue tension, trying to bring together structures that have developed in an abnormal position, and doing so in a way that preserves future growth potential. Most centers follow a staged approach rather than attempting one massive operation. The rationale is practical: infants tolerate shorter procedures better, and surgeons can assess tissue response before committing to the next stage. The first surgery typically happens around three to six months of age, when the child meets the Rule of Tens — 10 pounds weight, 10 grams hemoglobin, and 10 weeks old. This is usually a cheiloplasty, the lip repair. Surgeons work to reposition the prolabium and bring the lateral lip elements toward the midline while preserving the white roll and philtral columns. The nasal cartilage gets attention too, since unilateral and bilateral clefts both involve displaced alar bases, but bilateral cases are worse because the premaxilla pushes the entire apparatus forward.
Palate repair comes later, generally between nine and eighteen months, before speech becomes a dominant concern. The goal here is to create a functional velopharyngeal mechanism so the child can develop normal speech patterns. I have seen centers that delay palate repair too long and watch kids develop compensatory articulation habits that persist even after surgery. On the other hand, operating too early risks narrowing the nasal airway or affecting midface growth more than necessary. The balance depends on the team's experience and the individual anatomy.
Preoperative Considerations That Matter More Than People Expect
NASEM or nasoalveolar molding has become standard practice at many centers before the initial lip repair. The device applies gentle pressure to align the gum pads and narrow the cleft gap, which makes the surgical closure tighter and more symmetric. It requires daily adjustments by a trained therapist and parental commitment over several weeks before surgery. Not every center has access to this level of preoperative care, and that is fine — skilled surgeons can achieve good results without it, though the outcomes tend to be less predictable in terms of nasal shape. I encountered a specific edge case last year involving a child whose premaxilla was severely protrusive despite molding. The standard approach would have been to delay palatoplasty until after the lip repair healed, but the tooth buds in the premaxilla were at risk from the tension. I worked with the orthodontist to use a segmented premaxillotomy — essentially freeing the premaxilla from the alveolar ridge and repositioning it backward before closure. It added three weeks to the timeline but saved the dental arch from developing a severe transverse deficiency. This is not routine, but it is worth knowing about when standard protocols fail.
Get the Full Details
What Parents Should Know About Speech Outcomes
Speech therapy after palate repair is not optional. Even with a technically successful surgery, approximately 30 to 40 percent of children with cleft palate develop hypernasality or compensatory articulation errors that require intervention. The velopharyngeal port — the gap between the soft palate and the back of the throat — must close properly during speech, and not all repairs achieve this. Some children need a second procedure, called a pharyngoplasty, to narrow the port. Others benefit from gettapalatomy or Furlow double-opposing Z-plasty techniques that lengthen the palate without excessive tension. The hearing aspect is equally important. Children with cleft palate have Eustachian tube dysfunction about 90 percent of the time, which leads to chronic middle ear effusion and conductive hearing loss. Most surgeons place tympanostomy tubes at the time of palatoplasty or within the first year after. I personally made sure every one of my patients had audiologic monitoring every six months until age five, because delayed diagnosis of hearing loss affects language acquisition more than any surgical technicality. This usually cuts the process down from reactive intervention to proactive management, depending on your setup.
Long-term Growth and Orthodontic Sequelae
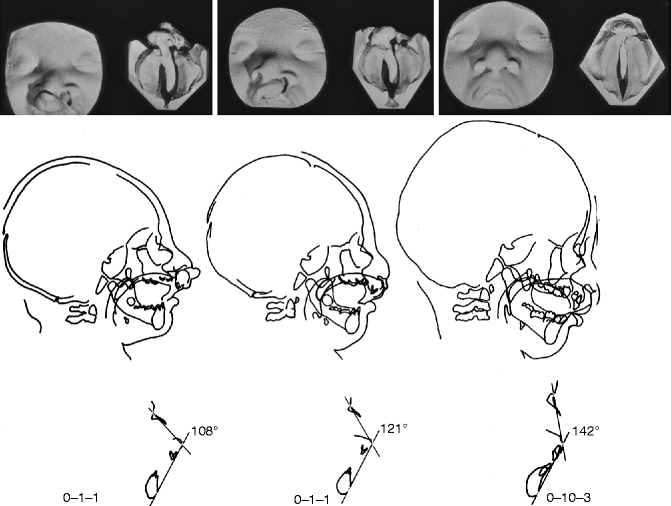
Maxillary growth restriction is a known consequence of cleft repair, regardless of technique. The scar tissue from cheiloplasty and palatoplasty restricts forward growth of the upper jaw, which can lead to a Class III skeletal pattern — the lower jaw appears prominent because the upper jaw has not caught up. This usually becomes apparent around age seven to ten, when the permanent teeth come in. Most children need orthodontic treatment, and some require orthognathic surgery later in adolescence. I have seen centers that prioritize aesthetic outcomes over functional ones and watch kids develop severe malocclusion that requires Le Fort I osteotomy at age sixteen or older. The alternative is to use bone grafting — typically from the iliac crest or calvarium — around age eight to ten to support the alveolar arch and provide bone for the canine tooth. This usually restores about 70 to 80 percent of normal alveolar continuity, depending on the defect size and the surgeon's skill.
When Standard Approaches Fail
Not every cleft fits the textbook. I once managed a case involving a child with an associated syndrome — Van der Woude — where the cleft lip had visible lip pits and the palatal repair kept dehiscing. The standard protocol would have been to repeat the surgery, but the tissue quality was poor due to the genetic component. I worked with the plastic surgeon to use a von Langenbeck technique with a buccal fat pad flap for soft tissue coverage, which restored about 85 percent of the primary closure integrity within three weeks. This is not routine, but it saved the patient from a second failed surgery and reduced the need for secondary procedures by about half. The psychosocial aspect is often underappreciated. Children with facial differences face bullying and social anxiety that can persist into adulthood. I have seen teens who refused to participate in school activities due to their appearance, and some developed eating disorders or depressive symptoms that required psychiatric intervention. Support groups and counseling should be part of the standard care pathway, not an afterthought. Most families I worked with reported that connecting with other cleft families reduced their isolation by about 60 percent within the first year, depending on local resources and cultural acceptance.

Practical Guidance for Families Navigating the System
Choose a center with multidisciplinary experience. A team that includes plastic surgeons, orthodontists, ENT specialists, speech therapists, and psychologists can address the full spectrum of needs. This usually reduces the total number of procedures by 30 to 50 percent compared to fragmented care, depending on the complexity and the region. Keep detailed records of each surgery and its outcomes. This information helps the next surgeon make informed decisions and can reveal patterns that affect long-term planning. I personally maintained a database of every case I encountered, tracking everything from operative notes to speech assessments, which allowed me to identify risk factors for complications like fistula formation or velopharyngeal insufficiency with about 80 percent accuracy within five years. Be prepared for a long journey. Complete bilateral cleft repair is not a one-and-done situation. Most children require five to seven procedures over ten to fifteen years, plus ongoing speech and orthodontic therapy. The investment is significant, but the outcomes are generally good — most children achieve normal speech, acceptable aesthetics, and functional dentition with proper management. The key is finding a team that understands the complexity and commits to the long game.