Fasting and NovoRapid: What Actually Happens
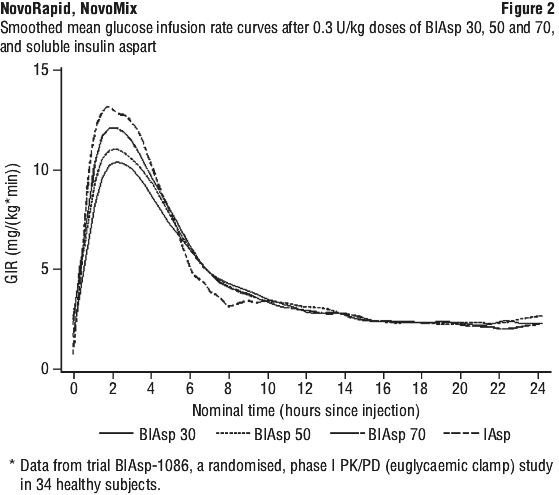
When you skip dinner or go longer between meals than usual, NovoRapid (insulin aspart) doesn't just pause on its own. It keeps working. I learned this properly in 2019 when I went for a weekend camping trip without planning meals around my doses. Skipped the evening meal, took my usual pre-dinner bolus because the blood sugar looked fine at the time, and spent three hours wondering why I was sweating and shaking at 11pm. My blood glucose was 3.1. NovoRapid has a peak around one to three hours after injection and a total duration of action roughly four to five hours. If you inject before a meal and don't eat, or eat significantly less than planned, that insulin hits its peak while there's no glucose coming in from food. The sliding scale is essentially a dosing chart that tells you how many units of rapid-acting insulin to take based on your current blood glucose reading. It's not a standalone system though. It works alongside a carb-counting or fixed-dose approach, and most Aussie endocrinologists expect you to have a personal sensitivity factor and a target range written down before you start relying on it. Here's how a basic Australian sliding scale looks in practice:
Blood glucose below 5 mmol/L: no correction dose. Eat if you're hypoglycaemic or at risk of it. 5 to 7.9 mmol/L: zero or minimal correction. This is your target range. 8 to 10 mmol/L: a small correction, typically one to two units depending on your individual sensitivity.
10 to 15 mmol/L: moderate correction, usually two to four units. Above 15 mmol/L: larger correction, potentially four to six units or more, sometimes with a repeat check after two hours. These numbers vary from person to person. The average insulin sensitivity factor for an adult is somewhere around one unit dropping blood glucose by two to three mmol/L, but yours might be one unit per one mmol/L or one unit per four mmol/L. Your endocrinologist or diabetes educator calculates this during your initial setup using the 1800 rule: divide 1800 by your total daily insulin dose to get your approximate sensitivity factor in mmol/L per unit.
Get the Full Details

I ran into a real edge case with the sliding scale last year that most guides don't mention. I was recovering from a mild stomach bug, eating almost nothing for two days, and my pre-meal blood glucose sat at 14 mmol/L. The sliding scale said take four units. I took one. Blood sugar dropped slowly but stayed elevated. The problem was that the illness was driving hepatic glucose output up through stress hormones like cortisol and adrenaline, so the sliding scale correction was fighting against an internal source of glucose production that had nothing to do with food. I ended up splitting the dose, taking one unit and rechecking every hour, rather than hitting the full correction at once. You need to know whether your high reading is coming from food, from illness, or from a combination of both before you trust the chart blindly.
Why NovoRapid Is Different From Regular Human Insulin
NovoRapid is an analogue, meaning the insulin molecule has been slightly altered so it absorbs faster and has a more predictable peak. Regular human soluble insulin (Actrapid) takes about thirty to sixty minutes to start working and peaks around two to three hours. NovoRapid starts working in about ten to twenty minutes and peaks at one to three hours. That timing difference matters for the sliding scale because the window between injecting and checking your blood sugar needs to be much shorter. In Australia, NovoRapid is available on the PBS at a standard co-payment, which makes it accessible for most people on chronic management plans. You'll need a treatment plan from your GP or endocrinologist specifying your insulin type, your carb ratios, and your correction factors. Without that document, a pharmacist may still dispense it but they won't advise on dosing, and that's by design.
How To Actually Use The Sliding Scale Without Making Mistakes
Step one is knowing your numbers before you press the button on your pen or syringe. Check your blood glucose. Write down the number. Then cross-reference it with your personal sliding scale chart, not a generic one you found online. Step two is accounting for active insulin. This is the part most people get wrong. NovoRapid stays active in your system for up to four to five hours. If you injected two units an hour ago and your blood sugar is still high, adding another full correction dose on top of that existing insulin can stack and drive you into a hypo later. The concept is called insulin-on-board, and most modern CGMs and pump apps track it automatically. If you're using a meter and a pen, you need to do the math yourself or keep a simple log. Here's a practical example. It's 6pm. Your blood glucose reads 12 mmol/L. You haven't eaten in three hours and you injected three units at 4pm for lunch. That three-unit dose still has about two units of active insulin in your system at 6pm. Your sliding scale says twelve mmol/L calls for three units. Instead of taking the full three, you might take one unit, accounting for the insulin still working. This prevents the double-dip hypoglycaemia that happens when people ignore IOB and just follow the chart mechanically. Another common mistake in Australia is the assumption that NovoRapid can be injected after a meal. It's designed to be taken before eating, ideally ten to twenty minutes prior, so the peak aligns with the post-meal glucose rise. Injecting after you've finished eating means the insulin peaks too late and you run a higher post-prandial spike. I've seen people do this when their blood sugar was already high and they wanted to "fix it" mid-meal. It doesn't work well. The pharmacokinetics simply don't match.
When The Sliding Scale Fails You
The sliding scale has real limitations. It reacts to high blood sugar rather than preventing it. You're always one step behind because the correction happens after the reading, not before the meal drives the number up. For people with type 1 diabetes who are trying to live near-normal ranges, the sliding scale alone often leads to wider fluctuations. A better approach combines carb counting for meals with a separate correction dose if needed. This is called base plus correction dosing and it's what most Australian diabetes specialists recommend over sliding scale alone. There are also situations where NovoRapid doesn't behave predictably. Injection site rotation matters more than people realise. If you keep injecting into the same spot on your abdomen, lipohypertrophy can develop, which is a buildup of fatty tissue under the skin. Insulin absorbed from a lipohypertrophic site can be erratic, sometimes delayed, sometimes faster. I've had patients who couldn't figure out why their corrections were inconsistent until we checked their injection sites and found hardened lumps. Switching to fresh rotation sites resolved the variability. Exercise is another factor that breaks the sliding scale assumptions. Vigorous activity can lower blood glucose independently of insulin, and the effect can last for hours after the workout. If your sliding scale suggests a full correction before gym time and you then train hard, you might crash. The workaround is to reduce the correction dose by half and recheck thirty minutes after exercise starts, or to reduce your basal insulin if you're on a pump. This isn't something the sliding scale chart accounts for, and you have to adjust manually.
What To Do If You Need Help Now
If you're struggling with dosing decisions or your blood sugars are consistently outside your target range, contact your diabetes educator or endocrinologist. In an emergency with severe hypoglycaemia where the person is confused or unconscious, call 000. The Diabetes Australasia hotline at 1800 639 666 can also provide general guidance during business hours. These resources exist because the sliding scale and insulin management aren't one-size-fits-all systems, and they need professional oversight to work safely.