Getting Into the Optum Provider Portal Without Losing Your Mind
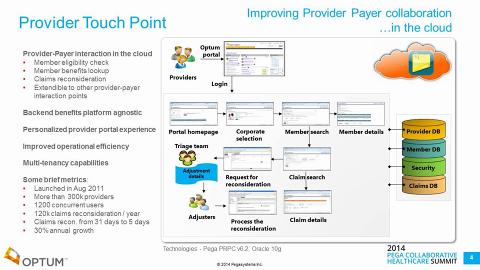
I spent about six months untangling the Optum virtual access and credentialing portal before it stopped fighting me every time I tried to pull a provider roster. The system is functional once you understand the workflow, but the onboarding experience is not intuitive. This guide covers the portal features most people miss, how to get access in the first place, and the practical habits that keep your account from getting locked. First, a heads-up on terminology that trips people up. CCN stands for Certificate of Compliance Number, which is tied to your organization's CMS enrollment record, not your NPI. When Optum asks for a CCN during portal registration, they are verifying your facility-level enrollment status. Putting your NPI in that field will cause the verification to fail silently, and then you will spend two hours wondering why the account creation step won't advance. I learned this the hard way when I submitted the same form four times across three days. The error message was vague enough that I almost submitted a support ticket before I caught it. Provider access follows a deliberate chain. You cannot simply sign up and start pulling data. The system requires organizational verification before individual logins are activated. Here is how the process actually unfolds.
Step one: Obtain your CMS Certification Number. This is available through the CMS provider lookup tool or your state Medicaid portal. Keep a screenshot or PDF of the record because Optum support will ask for it if your enrollment profile doesn't map cleanly. Step two: Start the provider registration through the main Optum portal landing page. Look for the provider self-service or provider access request option. The link is not always obvious because the public-facing site emphasizes patient resources. Use your browser's search function if the navigation buries it. Step three: Enter your organizational identifiers. This includes your federal EIN, taxonomy codes, and the CCN. The system cross-references these against CMS enrollment files. If any identifier is mismatched, the application stalls at the verification stage. I had a case where a taxonomy code had lapsed during a specialty update, which caused the portal to reject the application even though the provider was actively seeing patients. Fixing the taxonomy code in PECOS cleared the block within forty-eight hours.
Step four: Individual login creation. Once organizational verification completes, you receive an activation email. The login credentials are separate from any legacy system accounts your organization may have held. Do not assume old username/password combinations carry over. Create a new credential set that meets the current complexity requirements, and store it in your organization's secure credential manager immediately. Account lockouts due to repeated password failures are the most common support call I see.
Get the Full Details

Core Portal Features You Should Know About
The portal organizes its functionality around a few key areas, but the labels are not always descriptive. Provider directory management. This is where you update contact information, practice locations, and specialty designations. Changes here directly affect how patients find you and how claims route. If your practice moves locations or adds a second site, update the directory within five business days. Delayed updates cause referral routing errors that can cost your practice patient volume before anyone notices the root cause. Credentialing status tracking. The portal shows your current credentialing stage. It does not give detailed reasons for delays, but monitoring the status weekly prevents surprises. I recommend setting a calendar reminder every Monday to check the dashboard. The status field updates on a different schedule than the internal review process, so there is often a lag of several business days between action and visible change.
Claims and remittance inquiries. You can pull claim status reports, view ERA data, and access remittance advice. The download feature supports CSV export, which is useful for building your own reconciliations. Be aware that historical data is not always complete for claims filed before you enrolled with Optum. I once tried to pull six months of remittance history and only received data going back ninety days. The system retained older records internally, but the provider-facing interface only surfaces recent transactions. For older disputes, you need to submit a formal data request through the support channel. Communication and messaging. The portal includes a secure messaging feature for submitting document requests, reporting errors, and escalating issues. This is slower than phone support but creates a paper trail that matters when billing disputes drag on. I use it primarily for credentialing document submissions because the confirmation receipt provides proof of timely filing.
Common Pitfalls and How to Avoid Them
The portal has several friction points that deserve attention before they become problems. Session timeouts. The system logs you out after approximately fifteen minutes of inactivity. If you are filling out a long form, save frequently and keep a draft copy in a separate document. I lost an entire provider update session once because I did not realize the timeout was so aggressive. The system preserved partial data in a draft state, but recovering it required navigating back through four screens to match everything correctly. Multi-factor authentication setup. Optum requires MFA for portal access. During my initial setup, the SMS-based verification failed repeatedly because my organization uses a VoIP number that the system flagged. Switching to an authenticator app resolved the issue immediately. If you encounter MFA problems, do not keep retrying the same method. Try the alternative option within the first two attempts.

Role-based access limitations. Not every portal function is available to every user type. Administrative roles can modify provider data, while clinical roles may only have view access. If your staff member reports that a feature is unavailable, the issue is likely a role assignment rather than a system error. Contact your organization's portal administrator to review and adjust role permissions.
Best Practices for Ongoing Management
After the initial setup wears off, maintaining clean portal hygiene matters more than most practices realize. Keep your directory information current. Update changes within ten business days of any event. Late updates cause claim rejections, referral mismatches, and compliance issues that compound over time. One practice I worked with delayed updating a physician's termination date by three weeks, which resulted in that physician appearing as active in the directory and receiving routed referrals they were no longer handling. The correction required manual intervention and an apology to the referring offices. Use the portal messaging system for all documentation submissions. Phone calls are faster for urgent issues, but they leave no record. Messaging creates timestamps and attachment confirmations that are valuable during audits or disputes.
Back up your exports. Download provider roster reports and remittance summaries quarterly. The portal does not alert you to data retention policies, and relying solely on the live system is risky. I maintain a local archive of quarterly exports for exactly this reason. Monitor your credentialing expiration dates. Set reminders sixty days before any license or certification renewal is due. The portal sends notifications, but they occasionally land in spam folders or get buried under other messages. Manual calendar entries are the only reliable fallback. When the portal fails you, document everything. Take screenshots of error messages, note the timestamp, and record the steps that led to the problem. Support teams resolve issues faster when they receive specific error details rather than a general complaint. I keep a running log file for each portal issue, which has saved me considerable time when following up on unresolved tickets.