How Oxygen Gets From Air to Blood
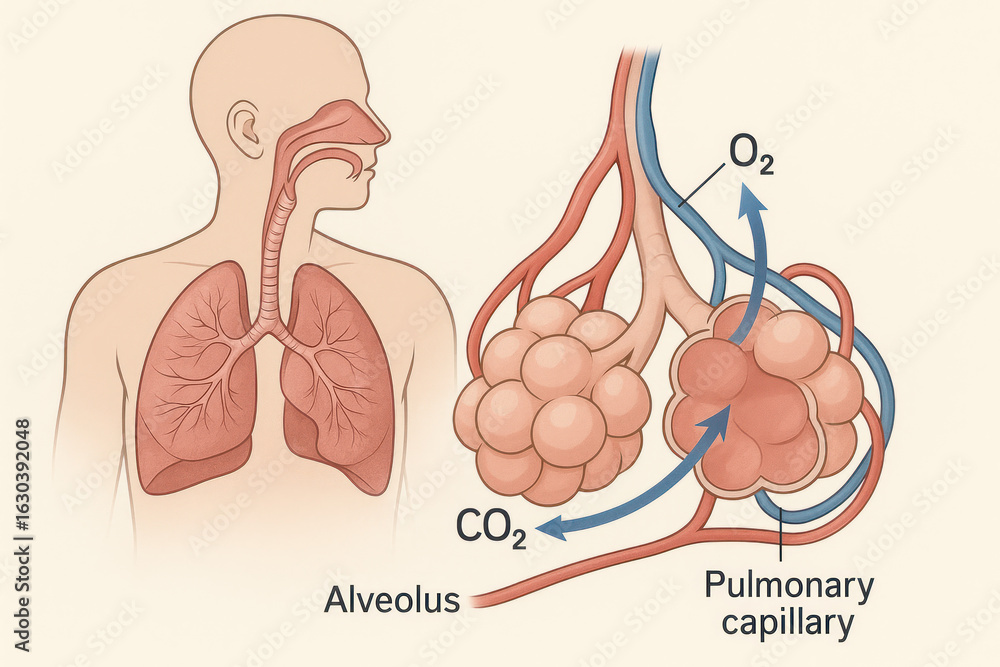
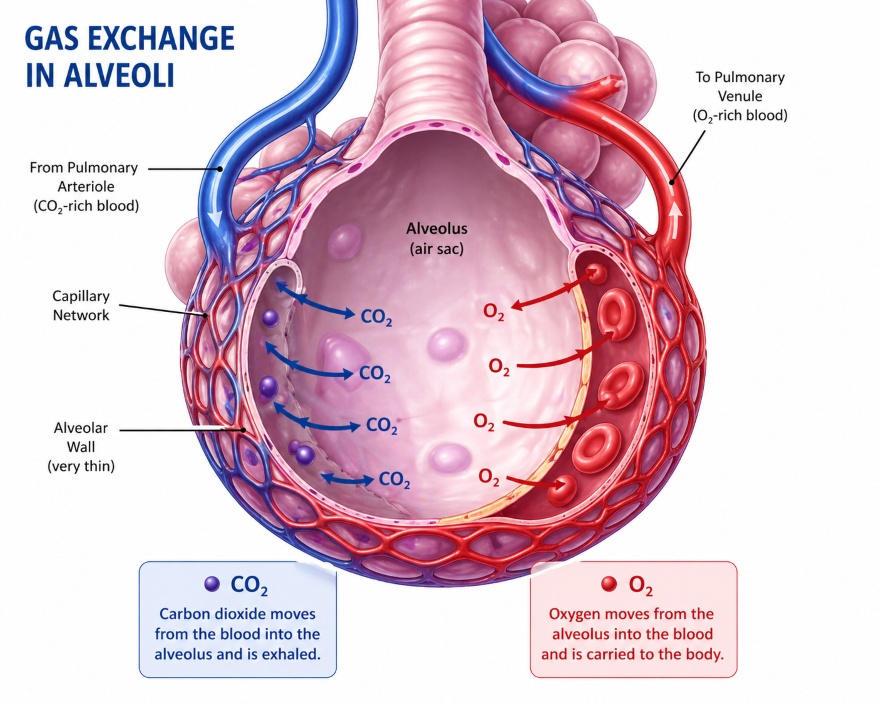
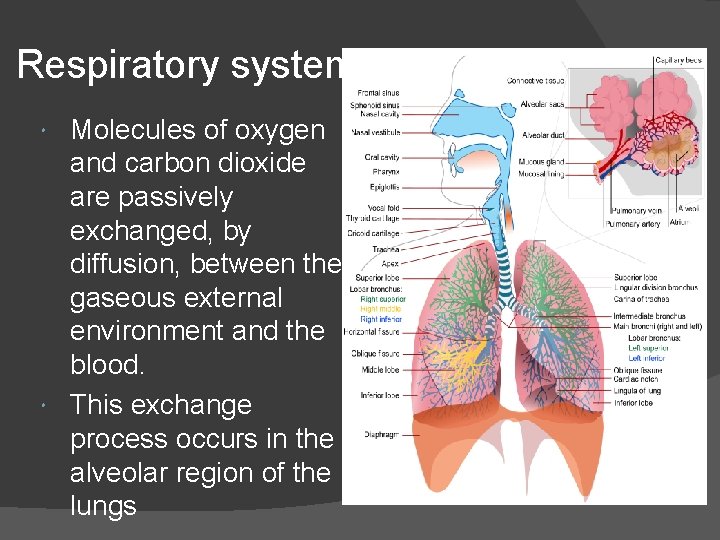
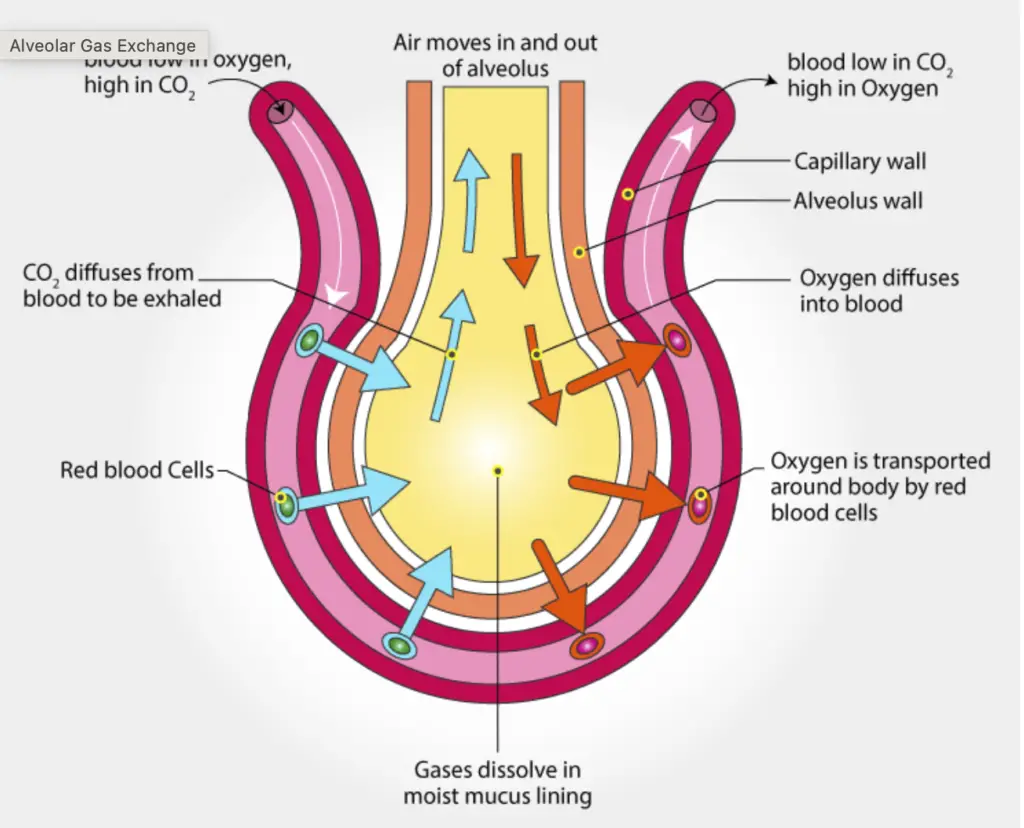
I spent three years teaching physiology lab at a community college before I got tired of watching students mix up partial pressure gradients with concentration gradients. You would think that is a basic distinction. It is not always obvious to beginners. The respiratory system does something incredibly efficient under the hood. You breathe about twelve to eighteen times per minute without thinking about it, and every single breath is moving gas across a barrier thinner than a sheet of plastic wrap. The actual mechanism comes down to diffusion. Oxygen moves from an area of higher partial pressure in the alveoli to an area of lower partial pressure in the pulmonary capillaries. That is it. There is no pump involved. The driving force is the difference between roughly 104 mmHg in the alveoli and about 40 mmHg in the deoxygenated blood arriving from the pulmonary artery. The gradient does all the work. Carbon dioxide moves in the opposite direction, from about 46 mmHg in the blood down to roughly 40 mmHg in the alveolar space. The total surface area of both lungs combined sits somewhere around 70 square meters in a healthy adult. That is roughly the size of a tennis court packed into your chest cavity. Most of that surface is made up of type I pneumocytes, these extremely thin squamous cells that form the alveolar-capillary membrane. The membrane itself is about 0.5 to 1.0 micrometers thick at its thinnest point.
I once had a patient with early interstitial lung disease who presented with exercise-induced hypoxemia but normal oxygen saturation at rest. His resting PaO2 was fine, around 95 mmHg. The moment he walked up a flight of stairs his saturation dropped to 88 percent. The problem was not his airways. It was thickening of the alveolar membrane from fibrosis. The diffusion distance increased enough to matter at high cardiac output but not at rest. I measured his diffusing capacity for carbon monoxide, the DLCO test, and it came back at about 55 percent of predicted. That confirmed the membrane pathology. Standard spirometry would have missed it entirely.
What Actually Limits Gas Exchange
There are four main determinants. Surface area matters because more alveoli means more membrane available for diffusion. Membrane thickness matters because diffusion rate is inversely proportional to distance. Partial pressure gradient matters because that is the driving force. Contact time matters because red blood cells spend only about 0.75 seconds traversing the pulmonary capillary at rest. Under normal conditions oxygen equilibrates within the first third of that transit time. The remaining two thirds is reserve capacity. That reserve is what makes exercise possible. When cardiac output triples during heavy exertion, transit time drops to roughly 0.25 seconds. A person with healthy lungs still equilibrates fully because the gradient is steeper and the alveolar surface area recruits additional capillaries that are normally closed at rest. A person with diffusion impairment does not have that buffer. Their oxygen saturation crashes during exercise even if resting numbers look normal. This is why the DLCO test and the 6-minute walk test are useful together. Hemoglobin binding is where most people get confused. Oxygen does not simply dissolve in plasma. About 98.5 percent of oxygen in arterial blood is bound to hemoglobin. The remaining 1.5 percent is dissolved oxygen, and that dissolved fraction is what determines PaO2 on an arterial blood gas. The oxygen-hemoglobin dissociation curve is sigmoidal, not linear. That shape matters because it means hemoglobin stays nearly saturated over a wide range of partial pressures. You can drop your PaO2 from 100 mmHg down to about 60 mmHg before saturation falls below 90 percent. The curve then steepens dramatically below that point.
Get the Full Details
Several factors shift the curve. Increased temperature shifts it to the right, meaning hemoglobin releases oxygen more readily. That happens in active muscle where metabolism is high. Increased 2,3-DPG in red blood cells also shifts the curve rightward. This occurs in chronic hypoxia such as high altitude adaptation or severe anemia. Carbon dioxide and hydrogen ions (the Bohr effect) shift the curve rightward as well. Acidosis promotes oxygen unloading at the tissues. The opposite is true in the lungs where CO2 is offloaded and pH rises slightly.
Common Misunderstandings About Breathing
People often assume that breathing is driven by the need for oxygen. It is not. Breathing is driven primarily by carbon dioxide levels detected by central chemoreceptors in the medulla. The chemoreceptors respond to changes in pH of the cerebrospinal fluid, which reflects arterial PCO2. Your body tolerates a much wider range of low oxygen than it does of high carbon dioxide. A PaO2 of 60 mmHg is concerning. A PaCO2 of 60 mmHg is dangerous and causes confusion, somnolence, and eventually respiratory arrest if untreated. Another misconception is that deep breathing always improves oxygenation. It does not, if your ventilation-perfusion ratio is abnormal. In conditions like pulmonary embolism or COPD with air trapping, taking deeper breaths can actually worsen gas exchange by overdistending alveoli and compressing nearby capillaries. The V/Q mismatch gets worse. Pursed-lip breathing is often more effective because it creates positive end-expiratory pressure, keeping small airways open and improving perfusion to poorly ventilated regions. The shunt concept is important here. A true intrapulmonary shunt means blood passes through the lungs without contacting ventilated alveoli at all. This occurs in pneumonia, pulmonary edema, or atelectasis. Shunt blood maintains a low oxygen content because it never participates in gas exchange. IncreasingFiO2does not fully correct shunt hypoxemia because the non-perfused alveoli simply cannot help that blood. The alveolar-arterial oxygen gradient widens significantly. This is different from V/Q mismatch, where some ventilation exists but is inadequate relative to perfusion. That pattern responds better to supplemental oxygen.
Practical Implications You Should Know
If you work in a clinical setting or study respiratory physiology, understanding the difference between diffusion limitation and perfusion limitation is essential. Most gases are perfusion-limited, meaning equilibration happens so quickly that blood flow is the rate-limiting step. Oxygen is normally perfusion-limited. Carbon monoxide is the classic diffusion-limited gas because it binds hemoglobin so avidly that it never reaches equilibrium along the capillary. That property is exactly why we use CO in the DLCO test. At high altitude the partial pressure of inspired oxygen drops because barometric pressure drops. At 3000 meters the atmospheric pressure is roughly 523 mmHg compared to 760 mmHg at sea level. The alveolar gas equation shows that PAO2 falls proportionally. Your ventilation increases reflexively, blowing off CO2 and creating respiratory alkalosis. Over days the kidneys compensate by excreting bicarbonate. This acclimatization takes time and is incomplete in many people. Supplemental oxygen restores PAO2 immediately but does not accelerate acclimatization itself. One edge case that trips people up is the diffusion barrier in restrictive lung disease versus obstructive lung disease. In pulmonary fibrosis the membrane thickens and surface area decreases. Diffusion is impaired. In emphysema the alveolar walls are destroyed, reducing surface area dramatically. Both conditions lower DLCO. Both cause exercise desaturation. The mechanisms are different but the functional consequence overlaps. Treatment strategies diverge significantly, which is why distinguishing them matters clinically.
High-information-density takeaways: resting PaO2 should be 80 to 100 mmHg on room air. PaCO2 should be 35 to 45 mmHg. The A-a gradient increases with age, roughly adding 1 mmHg per decade after age 30. An A-a gradient above 20 mmHg at rest on room air warrants investigation. Oxygen saturation below 92 percent at rest is clinically significant. Below 88 percent meets criteria for long-term oxygen therapy in COPD patients based on the NOTT and MRC trials. The respiratory system works reliably until it does not. Understanding the physics behind gas exchange helps you recognize when something is wrong before symptoms become obvious. Exercise testing, DLCO measurement, and arterial blood gas interpretation together give you a complete picture. Relying on pulse oximetry alone misses diffusion impairment, V/Q mismatch patterns, and carbon dioxide retention. Those are the scenarios where the full physiological framework saves you from a misleading number.