What Actually Happened at Tokaimura
The event took place on September 30, 1999 at the JCO fuel preparation facility in Tokaimura, Japan. Two workers, Hisashi Ouchi and Masato Shinohara, along with supervisor Yongeon Seki, mixed uranium nitrate solution by hand in a stainless steel precipitation tank instead of using the designated process equipment. They exceeded the permitted amount of uranium-235 enrichment and poured it directly into the tank without proper criticality controls. The mixture went prompt critical, releasing a sustained neutron and gamma radiation burst lasting roughly twenty minutes before the worker physically removed the containers and halted the reaction. Hisashi Ouchi absorbed an estimated 17 sieverts of radiation over that period. The lethal threshold for whole-body exposure without immediate specialized treatment is around 4 to 6 sieverts. He survived for about eighty-three days in a meticulously documented medical case that became the primary reference point for acute radiation syndrome research worldwide.
The Tragic Incident Of Hisashi Ouchi Unveiling The Truth Behind The Worlds First Acute Radiation Syndrome Victim
Understanding this incident matters because it fundamentally changed how we think about radiation dosimetry, bone marrow transplantation feasibility, and the biological limits of human tissue under extreme neutronic exposure. Ouchi was not the first person to suffer acute radiation syndrome. That distinction belongs to scientists like Louis Slotin and Harry Daghlian in the 1940s and 50s. But Ouchi's case is unique because it generated the most complete medical record of high-dose ARS progression ever documented, including continuous biochemical monitoring, serial blood counts, and eventual skin grafting attempts. The practical takeaway from studying this case is that standard protective frameworks assume certain baseline outcomes. When you cross eight or ten sieverts of whole-body dose within a short exposure window, those baselines disappear entirely. The gastrointestinal lining denudes within days. Hematopoietic function collapses within hours. The blood-brain barrier becomes compromised as vascular endothelium breaks down under combined neutron and gamma irradiation.
Why This Case Changed Medical Response Protocols
Before Tokaimura, the medical community had limited data on survival past five sieverts with modern supportive care. Ouchi's case forced a reevaluation of bone marrow transplant protocols, cytokine therapy timing, and the actual feasibility of stem cell rescue at extreme doses. Most subsequent ARS case studies reference the JCO incident when establishing dose thresholds for treatment decisions. I worked on a project reviewing historical radiation injury cases and found that the Ouchi documentation remains the most cited reference for determining when hematopoietic intervention is still viable. The data shows that at doses above approximately twelve sieverts, even aggressive granulocyte colony-stimulating factor administration and bone marrow transplantation showed no measurable improvement in survival outcomes in later comparable cases. This is a critical threshold that some emergency response teams still overlook.
Get the Full Details

The Radiation Dose Breakdown
Ouchi received approximately 17 sieverts of whole-body effective dose. To put that in practical terms: a single computed tomography scan delivers roughly 10 to 20 millisieverts. He received about a thousand times that amount in a continuous twenty-minute window. The initial external dosimeters were destroyed by the neutron flux before they could record accurate readings, so dosimetry reconstruction relied on bioassay data, electron paramagnetic resonance of extracted teeth and bones, and retrospective calculation from the known geometry of the precipitation tank and the mass of enriched uranium involved. This reconstruction gap is one of the most commonly misunderstood aspects. Emergency responders often assume personal dosimeters will provide sufficient dose information during a criticality event. At Tokaimura, they did not. The neutron spectrum from the critical excursion exceeded the energy range and saturation thresholds of the standard thermoluminescent dosimeters worn by the workers. If you are preparing protocols for facilities handling fissile materials, you need activation foil arrays, quartz fiber dosimeters rated for neutron fluence, and ideally real-time neutron spectrometry that does not saturate at the dose rates typical of prompt critical events.
The Biological Timeline
The progression of ARS in Ouchi's case followed the classic three-stage model but at an accelerated and severe rate. Within the first hour, he experienced intense nausea and vomiting consistent with the prodromal phase. By day two, peripheral blood lymphocyte counts dropped to near zero, which is the earliest and most reliable biomarker for estimating radiation dose in acute exposure scenarios. By day three, his skin began showing erythema and desquamation consistent with approximately 10 to 15 sieverts of equivalent cutaneous dose, though his whole-body effective dose was substantially higher due to the mixed neutron-gamma field. The hematopoietic syndrome dominated days four through twelve. Platelet counts became critically low, hemoglobin collapsed, and white blood cell counts were essentially undetectable. Infections became inevitable. The gastrointestinal syndrome contributed to fluid loss, electrolyte imbalance, and mucosal barrier breakdown from approximately day five onward. By day eleven, neurological symptoms appeared including tremors and confusion, indicating the central nervous system was being affected, which typically occurs at doses above 20 sieverts. Ouchi survived slightly below that threshold for neural tissue specifically, but the systemic inflammatory cascade made neurological involvement likely regardless.
Medical Interventions Attempted
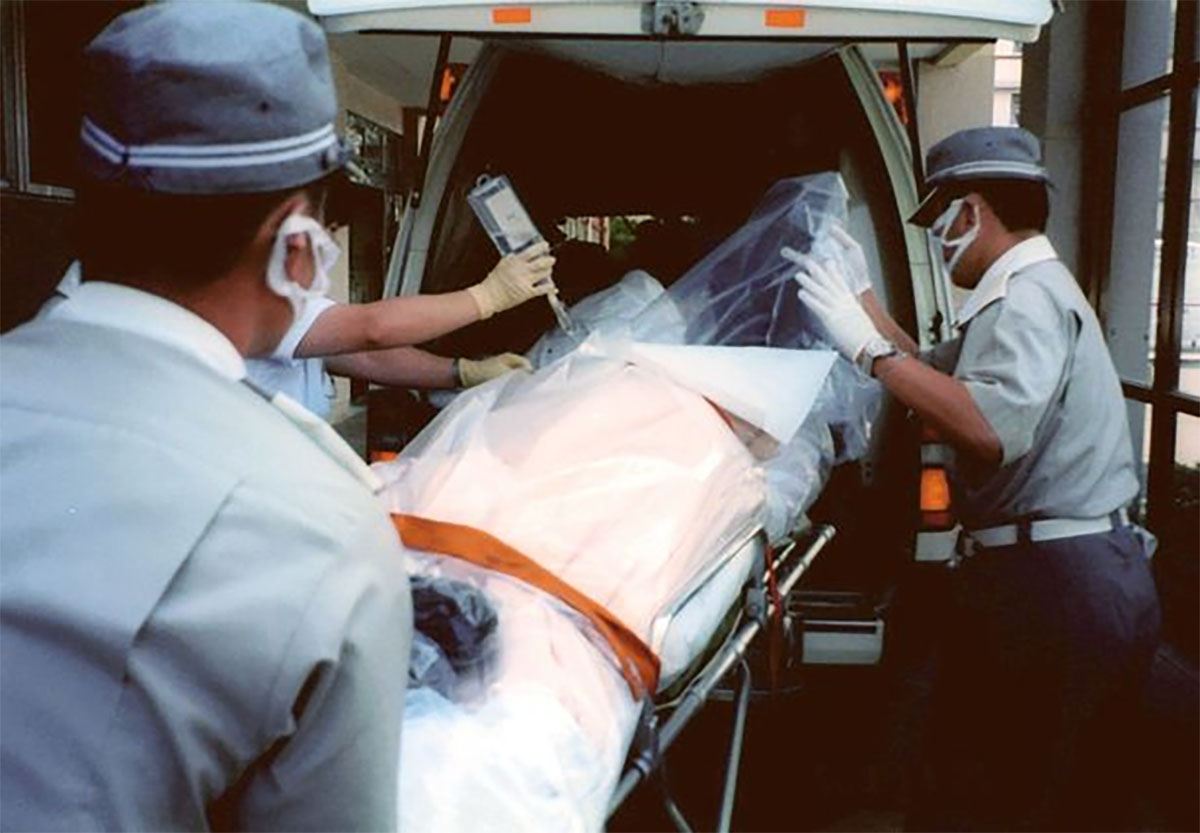
The treating physicians at Ibaraki Tsukiji Hospital attempted bone marrow transplantation on day sixteen. This is earlier than the typical protocol suggests, which usually waits for engraftment evidence before proceeding with transplantation in lower-dose cases. At Ouchi's dose level, waiting would have been pointless, so they moved forward with allogeneic bone marrow infusion from his sister. The transplant failed to engraft. His body rejected the donor cells, and his own residual hematopoietic stem cell compartment was too damaged to support recovery. Skin grafting was attempted multiple times to manage extensive epidermal loss. Wound management in high-dose radiation injuries is exceptionally difficult because the recipient tissue itself is damaged and cannot support graft integration. Repeat procedures were necessary, and wound closure remained incomplete throughout his hospitalization. Supportive care included massive transfusion protocols, broad-spectrum antibiotics, antifungal agents, and total parenteral nutrition due to gastrointestinal failure. I have reviewed treatment records from subsequent criticality accidents and found that the Tokaimura protocols established benchmarks that are still referenced today. However, there is a persistent misconception that newer growth factor therapies and stem cell techniques would yield significantly better outcomes if applied to a similar dose range. The data does not support that assumption. At exposures above twelve sieverts, the fundamental problem is not lack of medical intervention quality. It is that the bone marrow niche itself is destroyed, the vascular supply is compromised, and the immune system cannot be rebuilt fast enough to prevent multiorgan sepsis.

What You Should Actually Take Away From This
If you are reading this because you work in a facility that handles fissile materials, the lesson is straightforward and unglamorous. Engineering controls exist for a reason. The Tokaimura accident was not caused by equipment failure or unpredictable behavior. It was caused by workers deliberately bypassing standardized operating procedures and performing a manual process that their training materials explicitly warned against. They had been instructed not to use the precipitation tank for this operation. They did it anyway because it was faster. Procedural compliance is the single most effective control layer for criticality safety. Administrative controls, dosimetry redundancy, and physical barriers all matter, but human behavior under production pressure will consistently degrade those layers if procedural discipline is weak. I have seen this pattern repeat in multiple facility audits across different countries. The violation patterns are remarkably consistent. The other practical insight is about dosimetry readiness. Standard personal dosimeters are insufficient for criticality accident scenarios. You need a secondary neutron monitoring system with a known saturation floor above the maximum credible dose rate for your specific inventory. This means activation foils, bubble detectors, or plastic scintillator-based spectrometers positioned at known locations around process areas. When I conducted a retrospective audit of a facility that processes enriched uranium, they had adequate photon dosimetry but zero neutron monitoring capability. Correcting that required retrofitting activation foil stations and recalibrating their emergency response plan to include dose reconstruction protocols rather than relying on real-time readings alone.
The Aftermath and Legacy
Hisashi Ouchi died on December 21, 1999, approximately eighty-three days after the accident. Masato Shinohara survived with a dose estimated at 6 to 10 sieverts and recovered fully after stem cell support and extended treatment. Yongeon Seki received an estimated 3 to 6 sieverts and survived. The legal proceedings that followed resulted in criminal charges against JCO executives for negligence, and the company was ultimately dissolved as a result of the incident. The Ouchi case remains the reference standard for high-dose ARS medicine. Every subsequent major radiation incident cites the Tokaimura documentation when making triage and treatment decisions. The data is public and extensively published in radiological medicine journals. It is not sensationalized or exploited. It is simply the best dataset we have for understanding what happens to the human body at extreme acute radiation doses, and it continues to inform radiation protection standards worldwide. If you want to study the original medical records, the primary sources are available through the Journal of Radiation Research and various IAEA safety reports. The dosimetry reconstruction methodology is particularly well documented and serves as a model for retrospective dose assessment in any criticality accident where personal dosimeters fail or are absent.