A Practical Guide To Recognizing And Understanding Simple Columnar Epithelium
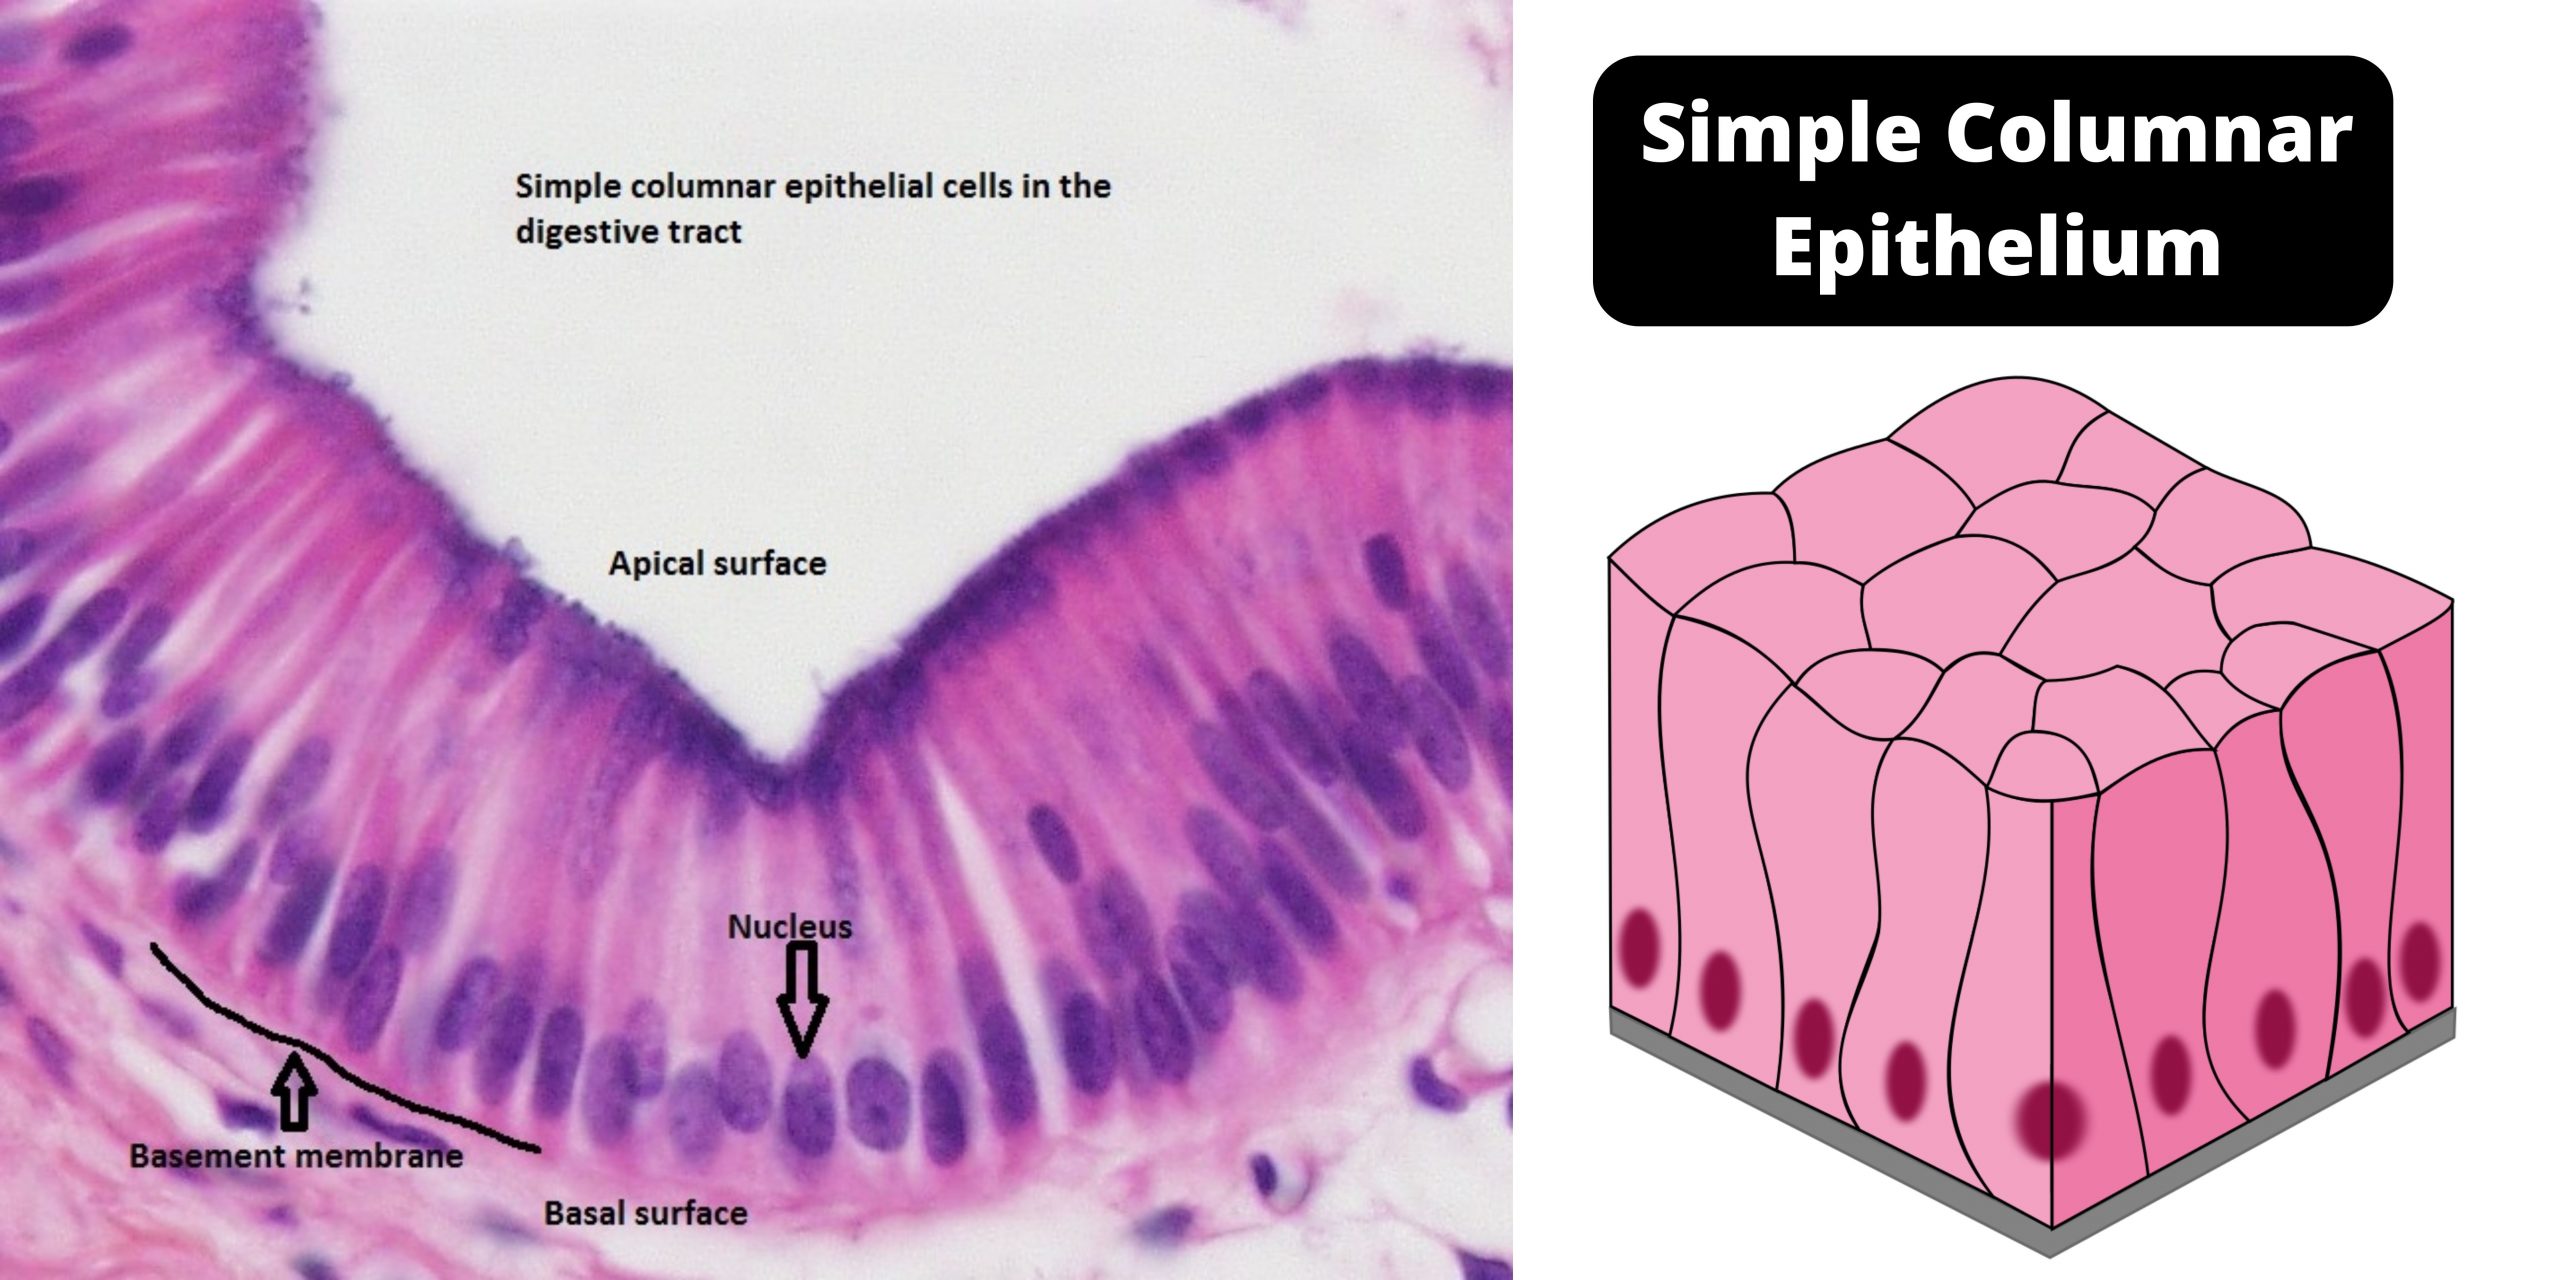
Simple columnar epithelium is exactly what the name implies: a single layer of tall, rectangular cells stacked side by side like bricks in a wall. If you have ever tried to identify this under a microscope, you already know the frustration of squinting at blurry slides and second-guessing yourself. I spent an entire semester in undergrad fighting with my histology practical grade because I kept confusing simple columnar with pseudostratified ciliated columnar. The difference matters, and here is how you actually tell them apart in practice rather than from some textbook diagram that looks nothing like a real slide. The most important thing to understand about simple columnar epithelium is that it is not just a structural lining. It is an active barrier and a selective filter, and its architecture is built around two competing needs: absorption on one hand and protection on the other. That tension is what shapes everything about the tissue. Basic structure
Each cell is roughly three to five times taller than it is wide. The nucleus is oval and positioned near the base of the cell, which means the apical surface is packed with functional machinery. That apical surface is where things get interesting. In the small intestine, the microvilli form a brush border that dramatically increases surface area for nutrient absorption. Without those microvilli, your small intestine would need to be roughly six times longer to absorb the same amount of nutrients. That is not trivia. That is the reason simple columnar epithelium evolved the way it did in the gut. Goblet cells are scattered throughout the epithelium. They secrete mucus, and they look like a wine glass or a champagne flute cut in cross section because the mucin granules pile up at the apical end and push the nucleus flat against the base. When you are looking at a slide and you see those goblet cells mixed in with the columnar absorptive cells, you are almost certainly looking at intestinal epithelium. Not the trachea. Not the uterus. The intestine. I learned this the hard way during a lab practical where I labeled a section of trachea as simple columnar epithelium because I focused only on the tall cell shapes and completely missed the pseudostratified nuclei and the cilia. I lost points, but that moment taught me something no amount of memorization could. You have to train your eye to look at the whole picture before you commit to an identification.
Where you find it The stomach lining uses simple columnar epithelium with a heavy mucous secretion to protect itself from gastric acid. The non-ciliated variety lines most of the digestive tract from the stomach through the colon. Ciliated simple columnar epithelium appears in smaller regions like the uterine (fallopian) tubes and parts of the male reproductive tract. The cilia here do not move mucus like they do in the respiratory tract. They move the ovum. Different function, same basic cellular architecture. The gallbladder and the bile ducts also carry simple columnar epithelium, and this is where many students get tripped up. The gallbladder epithelium has a very prominent brush border, and the cells appear even taller than intestinal cells. But unlike the intestine, there are no villi and no goblet cells. If you see simple columnar epithelium with massive microvilli but no goblet cells, think gallbladder, not jejunum.
Get the Full Details

The barrier function is more nuanced than it looks Simple columnar epithelium relies on tight junctions between adjacent cells to control what passes through the paracellular space. The tightness of those junctions varies dramatically by location. In the small intestine, the tight junctions are relatively leaky to allow ions and water to follow absorbed nutrients through osmosis. In the colon, the junctions are much tighter because the priority shifts from absorption to water conservation and pathogen exclusion. This is a detail most introductory courses gloss over, but it matters enormously if you are trying to understand conditions like leaky gut syndrome or inflammatory bowel disease. Here is a counter-intuitive point that is rarely emphasized: the barrier is not just mechanical. The epithelial cells actively secrete antimicrobial peptides and IgA antibodies into the lumen. Mucus itself is not just a lubricant. It traps bacteria and particles and keeps them away from the cell surface. The combination of mucus, tight junctions, antimicrobial secretions, and rapid cell turnover creates a barrier that is dynamic and self-repairing. When epithelial cells are damaged, neighboring cells divide to replace them, and stem cells in the crypts continuously regenerate the entire layer. The turnover rate in the small intestine is approximately every three to five days. That is fast. Your skin replaces itself in about two to four weeks. The gut epithelium turns over significantly faster.
I encountered a real edge case once while reviewing colonic biopsy specimens from a patient with chronic ulcerative colitis. The histology showed crypt abscesses, goblet cell depletion, and crypt architectural distortion. What struck me was how quickly the epithelium attempted to rebuild itself even in the face of ongoing inflammation. New crypts formed at abnormal angles, some branched, and the regenerated epithelium sometimes looked deceptively normal at low magnification. If you are just scanning at low power, you might miss the dysplasia that can develop years later. This is why pathologists always recommend examining multiple levels and being suspicious when the architecture looks slightly wrong even if the individual cells look relatively bland. A quick scan at low magnification in that case would have missed early dysplastic changes entirely. Common pitfalls when studying this tissue First, do not confuse simple columnar with stratified squamous epithelium. The latter is found in the esophagus and has multiple cell layers. Simple columnar is one layer. If you count more than one layer of nuclei, you are not looking at simple columnar. Period. Some slides can appear deceptively layered due to folding or tangential cutting, so rotate the field of view and check whether the nuclei actually occupy different vertical levels or just happen to overlap because of the plane of section.
Second, do not assume all columnar cells have microvilli. The uterine tube epithelium is simple columnar but relies on cilia for movement, not microvilli. The gastric pits are lined with simple columnar cells that mostly secrete mucus and lack both prominent cilia and brush borders. The presence or absence of apical specializations is your first clue to the tissue's function. Third, and this is the one most beginners ignore, the staining matters. Hematoxylin and eosin is standard, but mucicarmine or PAS stains reveal goblet cell mucin and brush border carbohydrates that H&E simply does not show well. If you are studying this tissue seriously and you only ever look at H&E, you are working blind about half the relevant features. What happens when this barrier fails

When the tight junctions break down, whether from infection, autoimmune attack, or chronic inflammation, the consequences are immediate. Bacteria and undigested food particles cross into the lamina propria, triggering an immune response that further damages the epithelium. This is the basic mechanism behind food sensitivities, bacterial overgrowth, and the systemic inflammation seen in advanced IBD. The epithelium cannot compensate indefinitely. Once the crypt stem cells are depleted or damaged, you get ulceration, and ulcers do not heal properly without resolving the underlying cause. There is no shortcut around this. Understanding simple columnar epithelium is not about memorizing cell shapes. It is about understanding the relationship between structure, location, and function, and recognizing when that relationship is disrupted. The tissue is remarkably efficient at its job, but it is not indestructible. Learn the variations. Learn the exceptions. And when you are looking at a slide, look at everything before you commit to an answer.


