Getting Better at Walking Isn't as Simple as Just Walking More
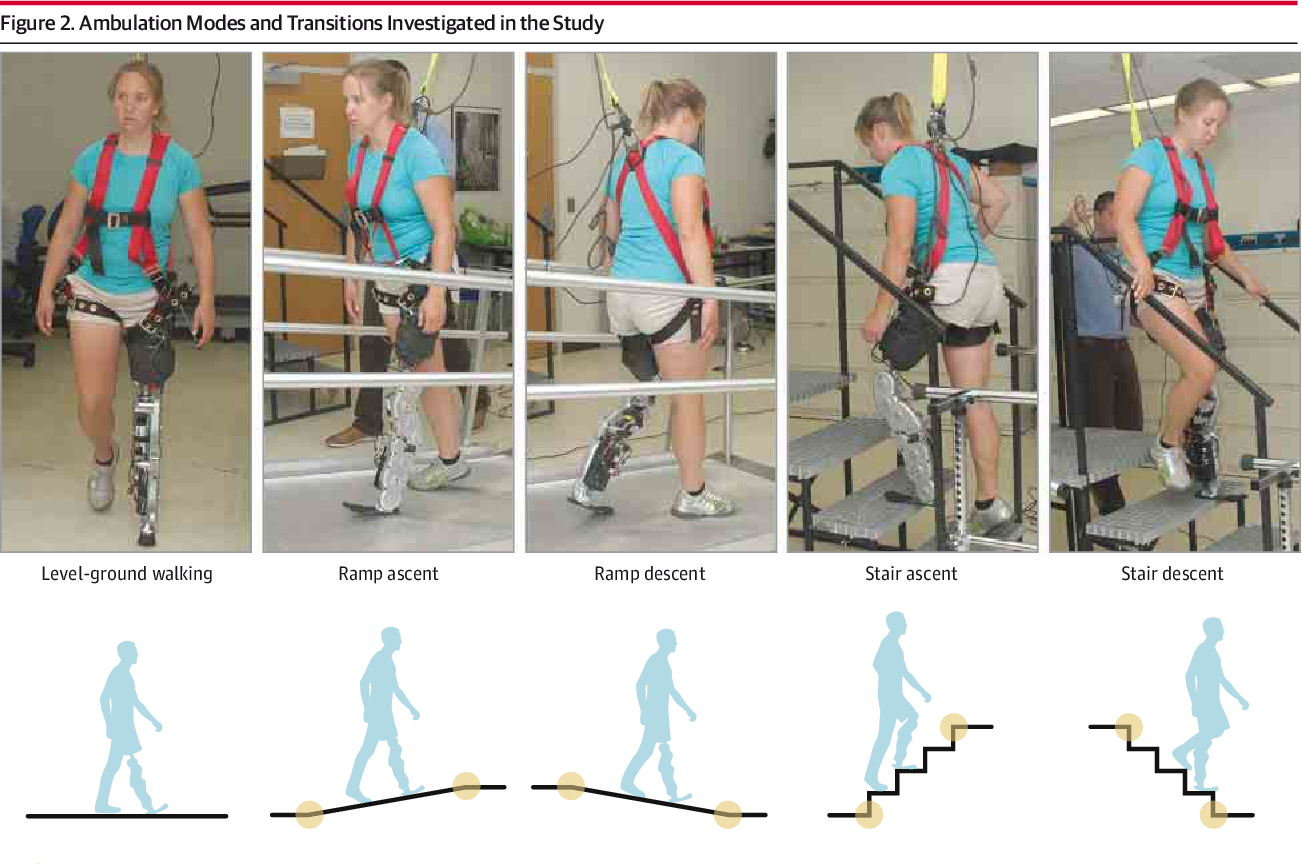
Ambulation sounds like a medical term because clinicians love it, but it just means movement from one place to another on your own two legs. That's it. The problem is most people treat walking like a background process that requires zero attention, then wonder why their knees click, their lower back seizes up after a grocery run, or they get exhausted climbing a single flight of stairs. I spent years working with physical therapists and biomechanics labs, and the consistent thread was the same: people have no idea how badly they're actually moving until something breaks. One patient came in with chronic hip flexor tightness that wouldn't resolve. Standard stretches, foam rolling, the whole routine. Nothing stuck. I had him film himself walking up stairs on his phone. Thirty seconds of video revealed he was leading with his heel on every step, locking his knee, and not loading through the midfoot at all. He wasn't walking wrong out of laziness. He'd been compensating for a minor ankle sprain from twelve years prior and never corrected the pattern. Three weeks of focused barefoot balance work and gait retraining fixed what months of stretching couldn't.
The Power Of Ambulation Unlocking The Secrets Of Human Movement
Human locomotion is deceptively complex. You're balancing two rigid levers on soft tissue pivots while your center of mass traces a figure-eight path that should theoretically topple you over at any moment. Your nervous system handles this through a mix of spinal reflexes, cerebellar feedback loops, and cortical planning. It works so well you don't notice it until it doesn't. The mechanics break down into phases, and each phase has failure points: Stance phase is when your foot is on the ground. Ideally, you load through the heel, roll through the midfoot, push off through the big toe. The arch acts as a shock absorber and a rigid lever at different moments depending on how much load you're under. If your arch collapses inward excessively — pronation — you lose that rigid lever effect and your knee rotates internally. This is where a lot of shin splints and patellar tendon issues originate.
Swing phase is when the leg is moving forward. Hip flexion, knee extension, ankle dorsiflexion. The foot needs to clear the ground. If your hip flexors are tight from sitting all day, your body compensates by hiking the pelvis or swinging the leg outward in a circumducted gait. You've probably seen this. It looks awkward because it is. The stride cycle repeats roughly once per second at a comfortable walking pace, which means your body completes about ten thousand of these cycles in a single hour of walking. When the mechanics are slightly off, those errors compound dramatically. Here's what most guides won't tell you: ankle mobility matters more than people think. I had a client who couldn't improve her walking endurance despite doing cardio daily. She couldn't dorsiflex her ankle past ten degrees with the knee straight. That's severely limited. Every time her foot hit the ground, her tibia couldn't travel forward over the foot, so her body shifted the compensation downstream to the knee and hip. Ten minutes of calf stretching and ankle mobilization before walks changed everything. Not a metaphor. Ten minutes.
Get the Full Details

Pelvic control is another hidden factor. Your pelvis should rotate slightly with each step, about four to five degrees total. If it stays rigid, your femur has to compensate with more internal or external rotation. This often shows up as groin pain or IT band syndrome in people who walk with a stiff trunk, usually from core weakness or fear of movement after an injury.
Practical Steps That Actually Work
Don't start by analyzing your gait on video unless you know what you're looking for. You'll spot obvious compensations but miss subtle ones. Start with simple awareness drills. Barefoot walking on uneven surfaces — grass, sand, a balance pad — forces your foot intrinsic muscles to activate. These are the small muscles inside the foot that keep the arch stable. Most people wear supportive shoes from age five and these muscles atrophy. Barefoot work rebuilds them. Start with five minutes a day. Don't do more until your feet stop hurting the next day. Single-leg balance is the next step. Stand on one leg while brushing your teeth. Thirty seconds per side to start. This trains proprioception and forces your hip abductors — gluteus medius — to fire. Weak gluteus medius causes pelvic drop on the swing leg, which cascades into knee valgus and foot pronation. The chain is real.
Heel-to-toe walking on a straight line, like a sobriety test line, forces a more controlled gait pattern. Ten meters forward, ten meters back. Do this daily. It feels ridiculous. It works because it removes the automatic pilot your nervous system has settled into. For people dealing with existing pain, the priority changes. If you have knee pain that worsens with walking, don't push through it. Check whether the pain is anterior (front of knee — usually patellar tracking), lateral (outside — usually IT band or lateral meniscus), or medial (inside — usually adductor or medial compartment). The location tells you where to look. Anterior knee pain often responds to hip strengthening. Lateral pain sometimes needs shoe rotation analysis. Medial pain may require arch support evaluation.

When Ambulation Training Fails
Sometimes gait retraining doesn't help, and that's important to know upfront. If you have structural issues — significant leg length discrepancy over two centimeters, advanced osteoarthritis, neuropathy from diabetes — no amount of walking drills will fix the underlying problem. You need orthotics, cane assistance, or surgical consultation depending on severity. Neurological conditions like Parkinson's disease create freezing of gait that requires cueing strategies, not biomechanical correction. Visual or auditory cues — tapping a rhythm, stepping over a laser line — bypass the damaged basal ganglia pathways and restore forward movement. This isn't alternative medicine. It's standard neurological rehabilitation. Older adults often experience fear of falling, which changes gait fundamentally. The response is to shorten steps, widen base of support, and reduce arm swing. This is protective but increases energy expenditure by up to thirty percent and accelerates deconditioning. Progressive balance training with fall prevention education addresses both the physical and psychological components.
The biggest limitation of ambulation-focused interventions is time. Gait patterns formed over decades don't change in weeks. Most people see noticeable improvement in three to six months of consistent practice. Beyond that, maintenance requires ongoing attention. Walking is a skill, not an automatic function you can neglect forever. For serious performance or rehab goals, a single session with a certified gait analyst or physical therapist specializing in movement can save months of wrong-headed self-correction. They'll film you, measure joint angles, and identify the primary compensation driving your symptoms. One session costs what three months of incorrect stretching adds up to in time wasted. Start simple. Walk barefoot on grass. Balance on one leg. Notice what changes. Your body knows how to move well. It just forgot in some places.