How the NIH Stroke Scale Actually Works in the ED
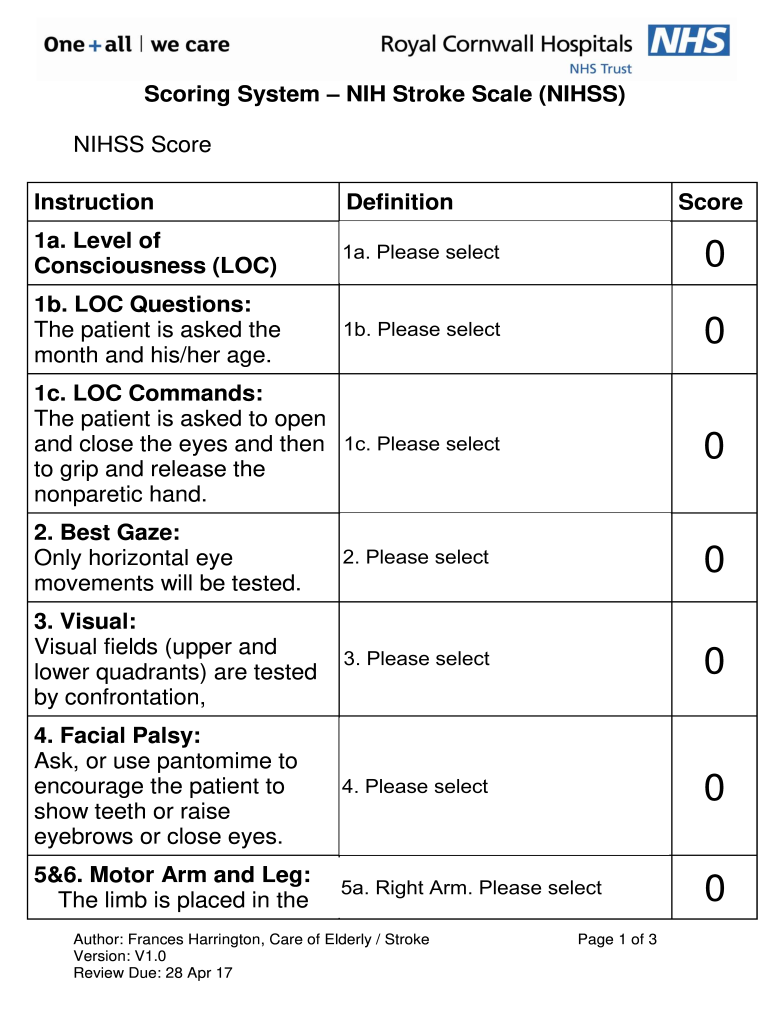
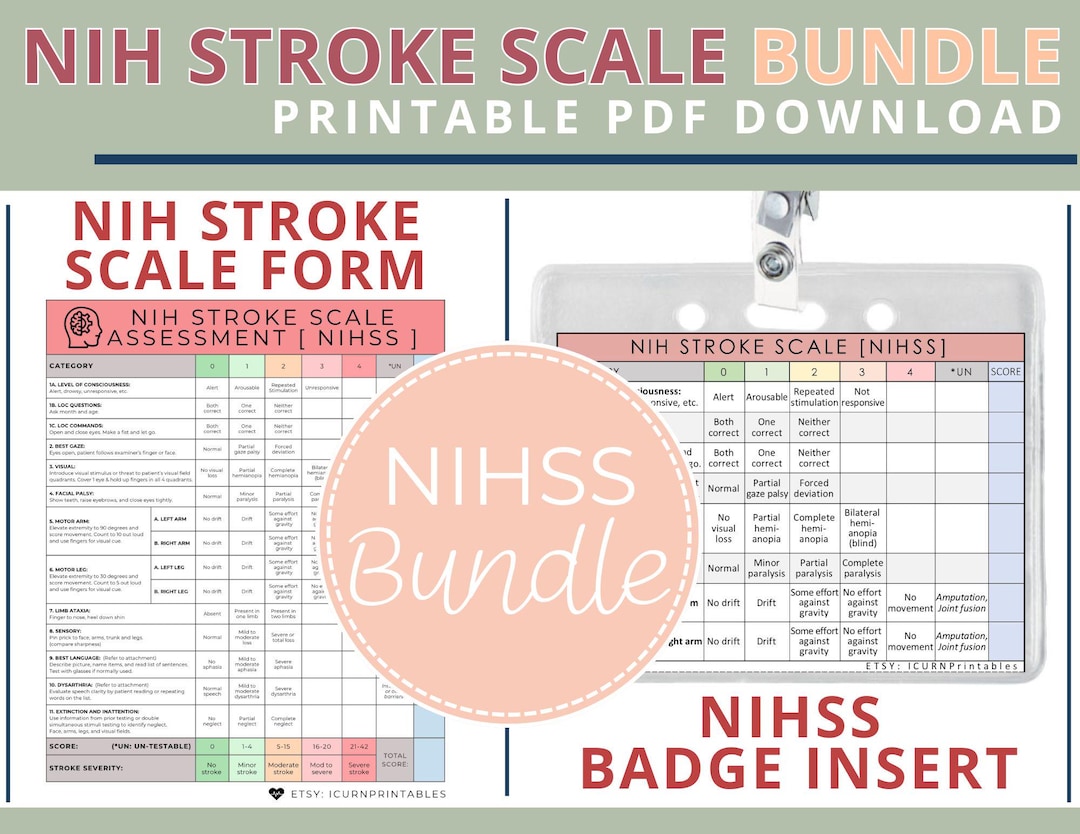
The NIH Stroke Scale is 11 items. Each item gets scored from zero to either two, three, or four depending on what you're looking at. The total possible score sits at 42. When I started doing stroke activations years ago, people treated the score like it was gospel. It isn't. It's a tool, and like any tool it has teeth if you don't know which way to hold it.The scoring goes like this. Item one asks two orientation questions — month and age. Zero is correct on both. One is wrong on one. Two is wrong on both. Item two is a command, usually squeeze and release hands or open and close eyes. Same zero-to-two range. Item three tests gaze. You look for any persistent deviation away from midline that the patient can't override. A normal response that is zero. Deviation that is fixable by verbal command is one. A forced deviation that you can't overcome is two. Item four is visual fields. You do the finger wiggle test in all four quadrants or the confrontation technique. Zero is no deficit. One is partial hemianopia. Two is complete hemianopia. Three is bilateral blindness. That last one is rare unless the patient already has known ophthalmologic disease, and you should note that on the form because it changes how you read the total.
The Nihss Stroke Scale Answers Decoding The Numbers That Define Stroke Severity And Care
Item five is facial palsy. This is where most people lose a point without meaning to. You ask the patient to show teeth or close their eyes tight. Asymmetry counts as one. Total paralysis counts as two. I once scored a patient a zero on facial droop when they clearly had one, because the side I was standing near looked symmetric. I repositioned and caught the droop on the far side. The patient got a two instead. It matters for the total. Items six and seven are arm and leg drift. Each follows a four-point scale. Zero is no drift. One drifts down after ten seconds. Two drifts down before ten seconds but hits the bed. Three cannot sustain against gravity at all. Four is no movement. The timing detail matters because the ten second window is built into the scale itself, not something you make up. Item eight is ataxia. You test finger-to-nose and heel-to-shin. Zero is normal. One is present in one limb. Two is present in two limbs. You only score this if the patient can actually cooperate with the movements, which brings me to a real problem I ran into.
Edge Cases That Break the Scale
Early in my workflow I kept getting stuck on Item 11, the extinction and inattention domain. This is where they check for hemineglect. I had a patient with a right MCA stroke who scored zero across the board except for one suspicious item, and the total was sitting at a deceptively low number. The issue was that the standard NIHSS battery doesn't reliably catch mild neglect. I started adding a simple line bisection test and a double simultaneous stimulation check using cotton swabs on both hands at once. A normal response is equal sensation on both sides. Asymmetry is a positive for neglect, which bumps the Item 11 score from zero to one. This patient ended up with a score that reflected the true extent of the deficit instead of underestimating it. The NIHSS manual acknowledges that Item 11 is the weakest item on the scale for detecting subtle neglect, but it doesn't give you a lot of guidance beyond that. The workaround is to supplement with bedside screening tools if you have time, which you usually do in a monitored setting. Another edge case is the intubated or aphasic patient. You can't score the language item if they can't produce language, and you can't score the speech item if they can't produce speech. The correct move is to mark the item as not assessable and note why. Don't guess a number just to keep the score clean. A padded total score is worse than a broken one.
Get the Full Details
Score Ranges That Actually Mean Something
A score between zero and four is minor stroke or TIA territory. Five to fifteen is moderate. Sixteen to twenty is moderate to severe. Twenty-one to forty-two is severe. These brackets exist so clinicians can talk to each other without running through the entire exam every time. They are not predictive guarantees. A score of four can still be a basilar occlusion hiding in the posterior circulation. The NIHSS was never designed for posterior strokes, and it shows it. Vertigo, diplopia, bilateral weakness, and ataxia from a brainstem event can produce a painfully low total despite a large and dangerous lesion. I learned this the hard way with a patient who came in complaining of dizziness and had a total NIHSS of three. Face was symmetric, arms were strong, legs were strong, speech was clear. The one point came from a subtle gaze abnormality I caught on re-exam. CT angiography showed a near-complete basilar artery occlusion. They went to endovascular therapy and came out relatively well because we moved fast. The scale had almost lied to us. That is the single biggest limitation you need to carry with you: the NIHSS measures anterior circulation dysfunction far better than posterior circulation dysfunction.
What the Scores Translate To in Practice
When the scale is administered correctly and consistently between two raters, the inter-rater reliability is respectable but not perfect. Training matters more than anything else. A nurse who has done fifty NIHSS evaluations will score more consistently than a physician who has done five. This is not an insult to physicians. It is a statement about repetition and pattern recognition. The items seem obvious until you try to standardize them across different patients and different environments. For the visual field item, some raters count a quadrantanopia as a one while others count it as a two. The manual says partial hemianopia is one and complete hemianopia is two, but quadrantanopia is technically partial. You need to decide what your institution standardizes on and stick with it. The variation does not change triage decisions in most cases, but it does change research data and quality metrics. For the language item, the scoring hinges on severity of aphasia, not presence or absence. A patient who can answer basic questions with paraphasic errors scores a one. A patient who can communicate only through fragmented speech scores a two. A patient who is mute or globally aphasic scores a three. Mild to moderate aphasia scores higher than severe aphasia on this item, which sounds backwards until you remember the item is measuring communication breakdown, not neurological damage magnitude.
Recording and Communication
The total score gets entered into the electronic health record and triggers thrombectomy pathways at certain thresholds. A score above six often qualifies for advanced imaging and vascular intervention evaluation. A score above ten with a confirmed large vessel occlusion is usually the threshold for direct cath lab transfer at most comprehensive stroke centers. The numbers guide workflow, not destiny. They are decision support tools. If you are looking for the official form and scoring guide, the National Institute of Neurological Disorders and Stroke maintains the NIHSS at their website. They also provide training modules and certification materials that are free to access. Many hospital systems require competency validation before allowing staff to administer the scale independently. That process usually involves watching recorded cases and then scoring them against established benchmarks until your agreement rate is acceptable.

The Bottom Line
The NIH Stroke Scale is straightforward in design and fiddly in execution. The eleven items cover consciousness, eye movement, vision, facial muscle control, limb strength, coordination, sensation, language, speech, and attention. The total score maps to severity categories that help with triage and treatment decisions. The main things to watch for are posterior circulation strokes that fly under the radar, neglect that hides behind a normal language score, and rater inconsistency that creeps in during busy shifts. Supplement the scale when you can, document limitations when they exist, and remember that a low number does not rule out a bad stroke.