Urine Formation and the Mechanics Behind It
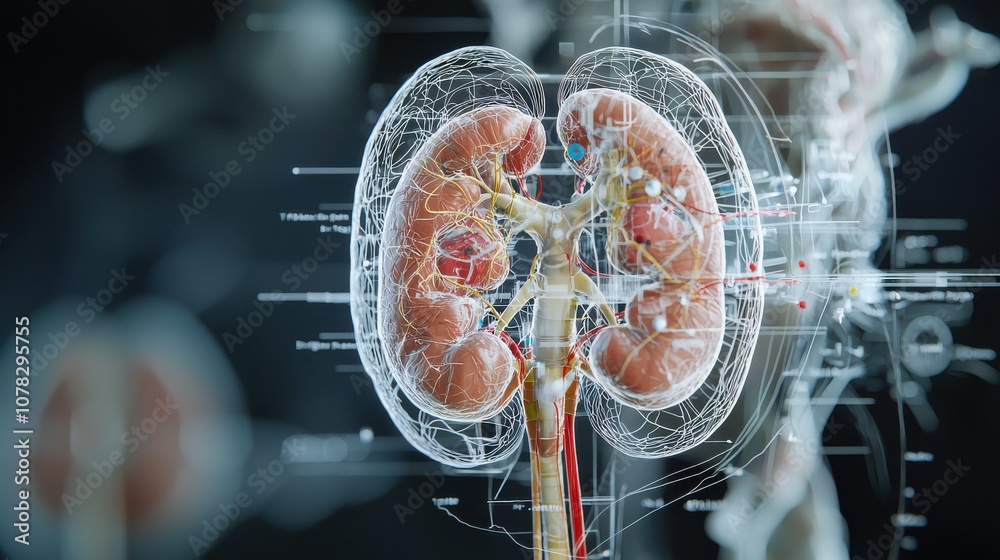
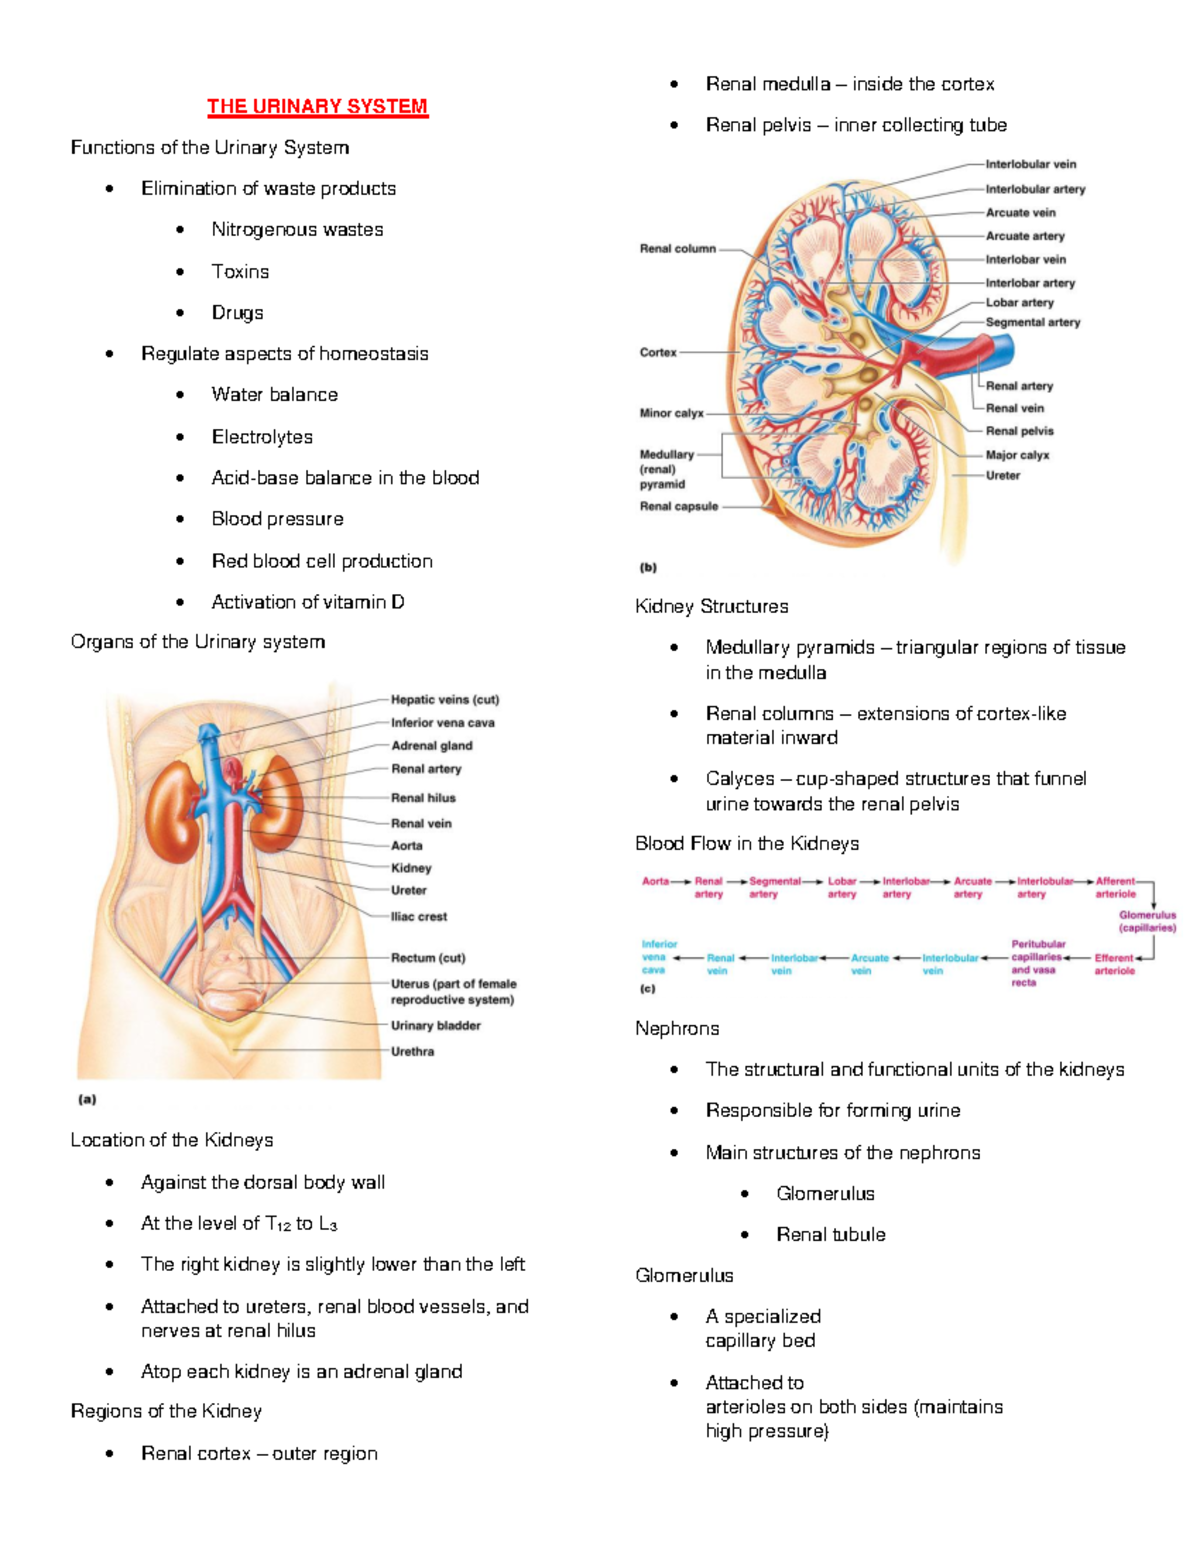
Most people think the kidneys are simple filters, like a coffee filter in a Keurig. They aren't. They are sophisticated chemical processing plants that run 24 hours a day without a break. A single human kidney contains about one million nephrons, and each nephron is responsible for filtering blood, reabsorbing what the body needs, and excreting what it doesn't. The entire blood volume in your body gets filtered roughly 60 times per day. That is not a dramatic statement, that is just the baseline physiology. When blood enters the glomerulus, it is pushed through a semipermeable membrane by blood pressure alone. No hormones are involved at this stage. The resulting filtrate contains water, salts, glucose, amino acids, and waste products like urea and creatinine. Everything small enough to pass through those pores goes into the Bowman's capsule. Large molecules like proteins and red blood cells stay behind. If they don't stay behind, you have a problem that usually shows up as protein in the urine, which is one of the first clinical signs of kidney damage.The Intricate Urinary System Understanding The Miraculous Process Of Waste Removal
The real work happens after the initial filtration. The filtrate travels through the proximal convoluted tubule, where approximately 65 percent of the filtered sodium and water is reabsorbed, along with nearly all of the glucose and amino acids. This is not passive diffusion. It is active transport driven by sodium-potassium ATPase pumps on the basolateral membrane. The energy cost of this process is significant. The kidneys account for roughly 10 percent of the body's total oxygen consumption despite making up less than 1 percent of body mass. From there, the fluid moves into the loop of Henle, which creates a concentration gradient in the medulla. The descending limb is permeable to water but not salts. The ascending limb does the opposite. This counter-current multiplier system is what allows the kidney to produce urine that is either very dilute or very concentrated, depending on hydration status. Without this mechanism, humans could not survive in environments where water is scarce. Desert-adapted animals like kangaroo rats take this further, producing urine that is nearly four times more concentrated than human maximum. The distal convoluted tubule and collecting duct are where hormonal control kicks in. Aldosterone regulates sodium reabsorption and potassium secretion here. Antidiuretic hormone, also known as vasopressin, controls water permeability in the collecting duct by inserting aquaporin-2 channels into the apical membrane. When you are dehydrated, vasopressin levels rise, the collecting ducts become permeable to water, and you produce a small volume of dark, concentrated urine. When you are overhydrated, vasopressin drops, the ducts become impermeable, and you produce a large volume of pale dilute urine.
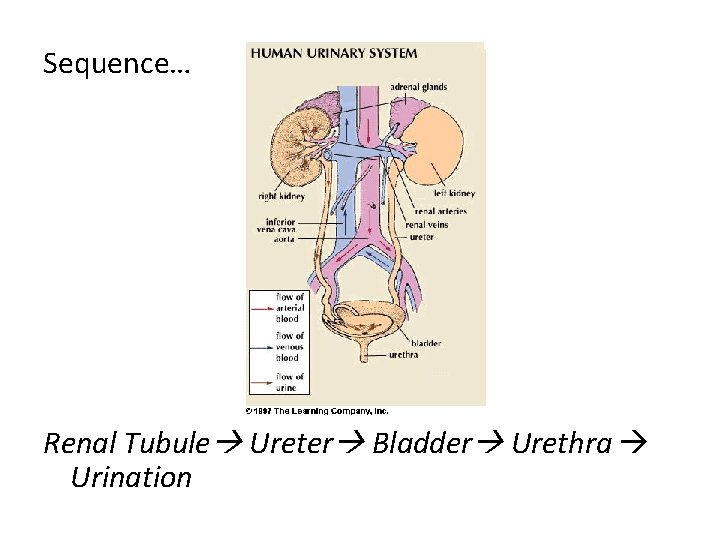
I spent a few years working in a clinical lab setting, and one thing that consistently caught people off guard was how easily the renin-angiotensin-aldosterone system can be thrown off by common medications. I recall a case where a patient on an ACE inhibitor presented with hyperkalemia because their distal tubule could no longer secrete potassium efficiently. The drug blocks angiotensin II production, which directly reduces aldosterone secretion. Aldosterone is the primary driver of potassium excretion in the distal nephron. Without it, potassium accumulates. This is not a rare side effect. It affects a meaningful percentage of patients, especially those with pre-existing renal impairment or those taking potassium-sparing diuretics concurrently. The workaround in practice was monitoring serum potassium within the first two weeks of starting therapy and adjusting the diet accordingly. Many patients were not aware that foods like spinach, potatoes, and bananas are loaded with potassium, and combining those with ACE inhibitors without medical supervision is a straightforward path to cardiac arrhythmia. The ureters are muscular tubes that move urine from the kidneys to the bladder through peristaltic contractions, not gravity. Even if you were hanging upside down, your kidneys would still drain into your bladder. The smooth muscle in the ureteral wall contracts rhythmically, and these contractions are myogenic in origin, meaning they start from pacemaker cells within the ureter itself rather than from neural input. The autonomic nervous system can modulate the frequency and strength of these contractions, but it does not initiate them. The bladder is a hollow muscular organ called the detrusor muscle. It can hold anywhere from 200 to 600 milliliters of urine in a typical adult before the urge to void becomes uncomfortable. The sensing mechanism involves stretch receptors in the bladder wall that send signals through pelvic nerves to the sacral spinal cord. From there, the brain processes the signal and can either permit or inhibit voiding. Voluntary control is established during childhood through maturation of the corticospinal pathways that suppress the reflex. This is why potty training takes time and why neurological conditions that affect these pathways, such as spinal cord injuries or multiple sclerosis, often result in urinary dysfunction. The internal urethral sphincter is smooth muscle and operates involuntarily. The external urethral sphincter is skeletal muscle and is under voluntary control. Micturition occurs when the detrusor muscle contracts, the internal sphincter relaxes, and the external sphincter is voluntarily released. In men, the urethra is approximately 20 centimeters long and passes through the prostate gland, which means prostate enlargement can obstruct urine flow and cause significant downstream problems. In women, the urethra is only about 4 centimeters long, which is one reason why urinary tract infections are significantly more common in females. Bacteria from the perineal area have a much shorter distance to travel to reach the bladder. Several things about the urinary system are poorly understood by the general public. One is that the kidney does not stop functioning when you feel the urge to urinate. The kidneys are constantly producing urine regardless of bladder fullness. The sensation of urgency is purely about bladder storage capacity, not about filtration rate. Another misconception is that drinking excessive amounts of water flushes out the kidneys in a beneficial way. It does not. The kidneys regulate their own filtration rate through autoregulation. Drinking gallons of water will not improve kidney function in a healthy person. It will simply increase urine output and potentially lead to hyponatremia if the sodium in your blood becomes diluted enough. The idea that "flushing" is inherently good comes from a fundamental misunderstanding of how renal physiology works. The countercurrent exchange system in the vasa recta is another detail that deserves more attention. These capillaries run parallel to the loop of Henle and preserve the medullary concentration gradient by allowing blood to pick up solutes as it descends and lose them as it ascends. If this system were disrupted, the gradient would wash out and the kidney would lose its ability to concentrate urine. Certain drugs, notably lithium, can damage the collecting duct cells and impair their response to vasopressin, leading to a condition called nephrogenic diabetes insipidus. Patients with this condition produce massive volumes of dilute urine and experience relentless thirst. It is a chronic, lifelong condition with no cure, only management through low-solute diets and sometimes thiazide diuretics, which seem counterintuitive but actually reduce urine volume by causing mild volume depletion that increases proximal tubule reabsorption. Kidney stones remain one of the most painful conditions in medicine, and they form through a combination of supersaturation, nucleation, and crystal growth. The most common type is calcium oxalate, and they form when the urine contains too much calcium or oxalate and too little citrate, which normally binds calcium and prevents crystallization. Low citrate in the urine, known as hypocitraturia, is a frequent underlying cause that many people never get tested for. The standard advice of "drink more water" is correct but incomplete. For recurrent stone formers, checking 24-hour urine chemistry for calcium, oxalate, citrate, uric acid, and volume is essential. Without that data, treatment is Guesswork. Thiazide diuretics reduce urinary calcium excretion. Potassium citrate raises urinary citrate. Allopurinol reduces uric acid production. Each intervention targets a specific abnormality identified through testing. The elderly present a particularly challenging subset of urinary system cases. Renal function declines with age, and not in a uniform way. Glomerular filtration rate drops approximately 1 milliliter per minute per 1.73 square meters of body surface area per year after age 40. By age 80, a typical person may have half the kidney function they had at age 30. Yet many elderly patients show few overt symptoms because the remaining nephrons compensate. Drug dosing based on serum creatinine alone is notoriously unreliable in this population because creatinine production decreases with muscle mass loss. Estimated glomerular filtration rate equations like CKD-EPI or MDRD account for age and sex, but even these have limitations in very old or very thin patients. I have seen cases where a patient's creatinine appeared "normal" at 1.0 mg/dL, but their actual GFR was well below 30 due to low muscle mass, leading to dangerous accumulation of renally cleared medications. The urinary system also interacts with nearly every other system in the body. It regulates blood pressure through renin release and fluid balance. It controls electrolyte concentrations including sodium, potassium, calcium, and phosphate. It produces erythropoietin, which stimulates red blood cell production in the bone marrow. It activates vitamin D through the enzyme 1-alpha-hydroxylase, which is critical for calcium absorption in the gut. When the kidneys fail, these functions collapse, and dialysis can replace filtration but not hormone production. This is a key distinction that is rarely emphasized. Hemodialysis clears waste products and excess fluid, but it does not produce erythropoietin or activate vitamin D. Patients on dialysis require synthetic erythropoietin injections and active vitamin D supplements because their kidneys can no longer perform those endocrine functions. Understanding how this system operates requires moving past the simple filter analogy and recognizing it as a dynamic, hormonally regulated organ that balances chemistry at a level of precision that engineering systems still struggle to match. The complexity is the reason why kidney disease is often called a silent condition. Symptoms do not appear until a substantial portion of function is lost, and by that point, the damage is usually irreversible.