The Hidden Cost Of Healing Unpacking The Nuanced Reality Of Xray Technician Hourly Pay
Samantha
2025-06-12
What the Numbers Actually Look Like on a Paycheck
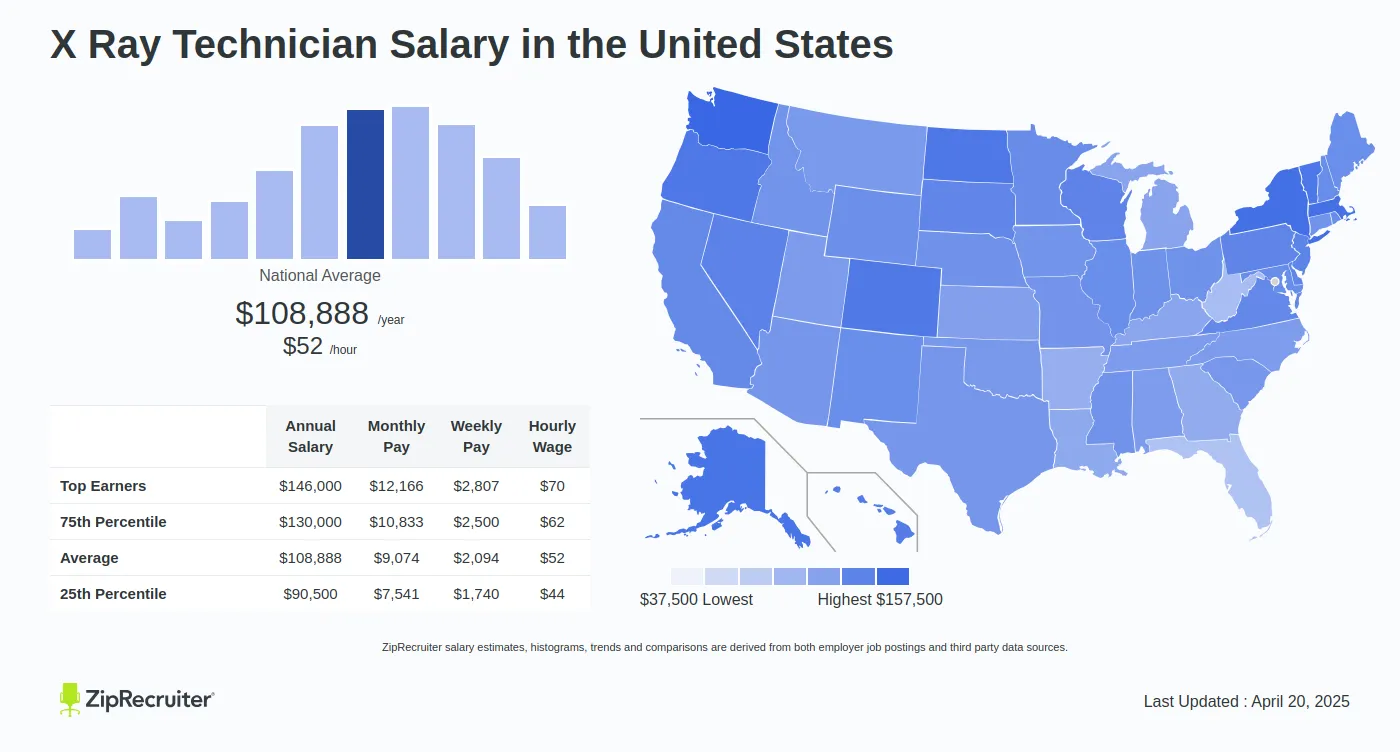
The base hourly rate for an X-ray tech in the United States typically sits somewhere between $28 and $45 for a standard W-2 position. That range is fairly consistent across major salary aggregators, but it means almost nothing in isolation. What actually determines whether you clear $60,000 or $95,000 annually has very little to do with your base rate and everything to do with the shift premiums, overtime structure, and benefit deductions that get layered on top or subtracted underneath.
Shift differentials are the first thing to understand. Nights usually add $2 to $5 per hour. Weekends can add another $1 to $3. Many hospitals stack these. A Saturday night shift might net you $6 to $8 above your base rate. This is how techs realistically push their effective hourly up into the mid-$50s without working extra days. The catch is that most of these premium rates stop at 40 hours. Once you cross into overtime territory, you are generally back to 1.5x your base rate, not 1.5x your premium-inclusive rate. That distinction matters more than people realize when you are calculating actual annual earnings.
The Hidden Cost Of Healing Unpacking The Nuanced Reality Of Xray Technician Hourly Pay
The Parts Nobody Puts in Job Descriptions
Your hourly wage does not cover a few recurring costs that eat directly into take-home pay. ARRT certification renewal runs about $170 every two years. BLS certification is roughly $80 to $100 through the American Heart Association, and you need it for most hospital positions. state licenses vary wildly by location but typically run $50 to $200 annually. If you work per diem or travel contracts, you are often responsible for your own malpractice insurance, which runs $300 to $800 per year depending on coverage limits and your employment setting.
Then there is the unpaid prep time issue. Most facilities expect you to arrive 15 to 30 minutes before your scheduled shift to change into scrubs, review the order queue, and position equipment. Unless your employer has a policy that explicitly pays for this window, you are working that time for free. A 20-minute daily buffer across a 5-day week adds up to roughly 17 hours of uncompensated labor per year. At a $35 hourly rate, that is about $600 you never see. Some larger hospital systems have started paying for this window after union pressure, but most smaller clinics and imaging centers have not.
Travel costs are another silent deduction. If you work at a hospital system with multiple locations, you may be required to float. Gas, wear on your vehicle, or public transit costs between sites are yours. I tracked this for one full quarter at a facility where I rotated between three campuses. The floating schedule added an average of $47 per week in commuting costs that were never reimbursed. Over a year, that was nearly $2,500 out of pocket.
Certifications, Credentials, and What Actually Moves the Needle
ARRT registration is the baseline credential. It is not legally required in every state, but it is functionally required because most employers will not hire you without it. Some states have their own licensing exam on top of ARRT, which adds another testing fee and paperwork cycle. Then there are the optional credentials that either help or do nothing depending on where you live.
Mammography certification from ARRT can add $2 to $6 per hour in certain markets, but not everywhere. In rural areas with limited mammography demand, employers rarely pay a premium for it. In metropolitan areas with high-volume breast imaging centers, it is worth pursuing. CT certification follows a similar pattern but tends to command a slightly higher premium, often $3 to $8 per hour more, because the skill ceiling is higher and turnover is lower. Contrast administration authorization is usually a short course, sometimes paid for by your employer, and can unlock a wider range of procedures within your current position.
The counter-intuitive part is that additional certifications do not always translate to proportionate pay increases. Many hospital pay scales are locked to a step system based on years of service and basic credential level, not individual skill add-ons. You can have ARRT in radiography, CT, and mammography and still land on the same pay step as a tech with only radiography. The higher pay comes from shift differentials and overtime, not from the credentials themselves, unless you move into a supervisory role or a specialized imaging position.
A Specific Case That Changed How I Calculate Offers
I worked with a tech who took a position at a small independent imaging center that advertised $42 per hour, which looked strong compared to the $36 per hour she was making at a hospital. The math seemed clear until she actually sat down with her first pay stub. The hospital position included a $2.50 night differential and a $1.50 weekend premium that pushed her effective rate to roughly $40 on those shifts, plus fully paid break time and a pension contribution that matched 4% of her salary. The imaging center had no shift premium, no pension, required her to clock in 20 minutes early without pay, and charged her $150 annually for her own liability insurance because they did not provide a master policy. When you factor in the missed break pay, the uncompensated prep time, the insurance cost, and the missing retirement match, her actual annual compensation at the imaging center was about $4,200 less than the hospital role, despite the higher advertised hourly rate. She switched back within eight months.
The workaround I use now when evaluating any offer is simple. I calculate the fully loaded hourly rate by adding every differential I expect to work, subtracting any unpaid time expectations, and then applying the benefits value. A 401k match of 4% is worth roughly $1.92 per hour on a $40 base rate. Health insurance premiums that the employer subsidizes at $300 per month equal about $1.73 per hour. Pension contributions are harder to quantify but typically add another $1 to $3 per hour depending on the plan. Once you put it all together, the $42 offer at the imaging center drops to something closer to $37.50 in real terms.
Where the Pay Variance Actually Comes From
Geography explains the largest chunk. Urban metro areas with high cost-of-living adjustments and unionized hospital systems consistently pay above the national median. Rural positions often lag by $4 to $8 per hour but sometimes compensate with sign-on bonuses or student loan repayment assistance. Employment setting matters almost as much. Hospitals generally pay more than freestanding imaging centers, which generally pay more than mobile or outpatient clinics. The exception is travel staffing, where agencies can pay significantly above market rate, but those positions come with instability and frequent reassignment.
Government facilities and VA hospitals tend to sit at the higher end of the scale due to structured pay bands and strong benefits packages. Private practice groups vary enormously depending on ownership structure and patient volume. If a facility is under financial pressure, your hours may get cut before your rate is reduced, which is a detail worth paying attention to during the interview process.
Overtime and the Real Ceiling
Overtime is where most techs see the biggest variance in annual income. At 1.5x your base rate, working just two overtime hours per week adds roughly $3,100 to $5,200 annually depending on your base. But overtime availability is not guaranteed. Many facilities rely on a core staff model and treat overtime as a last resort. Some explicitly discourage it. Others build it into the schedule during peak seasons or staffing shortages.
The structure of your overtime classification also matters. If you are non-exempt, you are entitled to 1.5x after 40 hours in a workweek. Some facilities use a 4/10 schedule, where you work four 10-hour days, which means you do not hit overtime until day five. This is common in hospital radiology departments. Understanding which schedule your employer uses affects your ability to pick up extra shifts strategically. A 36-hour week at a facility with no overtime threshold until 40 hours leaves you with an open slot that another facility might fill with a mandatory overtime call.
The Limitations of This Model
This approach to calculating effective hourly pay assumes you have visibility into the full compensation package, which is not always true. Some employers do not disclose benefit values upfront. Shift differential policies can change with minimal notice, especially in non-unionized settings. Travel reimbursement policies are often vague or nonexistent. There is also the issue of schedule volatility, where your expected premium shifts get reassigned without prior communication, making your projected annual income less reliable than it appears on paper.
If an employer is reluctant to provide a written summary of shift differentials, overtime policy, and benefit values before you accept an offer, that is a signal to be cautious. A straightforward employer will provide this information or direct you to an employee handbook. The ambiguity itself is a cost, because it forces you to estimate rather than calculate.
What to Do Before You Sign
Request the full compensation breakdown in writing before accepting any offer. Ask specifically about shift differentials, overtime eligibility, prepaid time policies, and benefit contribution amounts. Compare the fully loaded rate, not the base hourly. Factor in the certification and insurance costs that will come out of your pay. Run the numbers for a full year including typical shift patterns, not just a standard Monday-through-Friday day shift scenario. If the employer cannot provide clarity on these points, treat the advertised rate as a best-case floor, not a reliable number.
Gallery The Hidden Cost Of Healing Unpacking The Nuanced Reality Of Xray Technician Hourly Pay
X-Ray Technician Salary in the U.S. - 2025 Insights
Interventional Radiology Salary Breakdown: The Shocking Pay Gaps You ...
X-Ray Technician: Salary, Education & Career Guide 2026 - Sonographer ...
X-ray Technician Salary (Actual 2026 | Projected 2027) | VelvetJobs
Much Do Radiology Techs Make : How to Become an X-Ray Technician (With ...