Urban Wellness Isn't About Adding More Gyms
The way most cities approach public health is fundamentally broken, and it has nothing to do with funding. You can spend millions on a new rec center and still watch cardiovascular outcomes worsen over five years. The problem isn't the money. It's the architecture of how health interventions get designed in the first place. I've spent the last decade working alongside municipal health departments, urban planning firms, and wellness technology companies across about fourteen cities. The pattern is consistent enough that it borders on predictable. Every single one of these organizations treats the city as neutral ground—something that either helps or hinders health depending on whatever random conditions happen to exist. None of them systematically use the urban environment itself as an intervention tool. The difference between a wellness strategy that actually moves the needle and one that becomes another line item in a budget nobody reviews after year two usually comes down to one thing: whether the people designing it understand the city as a dynamic system or just as a container for buildings and people.
The Future Of Urban Wellness How Arielle Goldrath Is Redefining Health In City Living
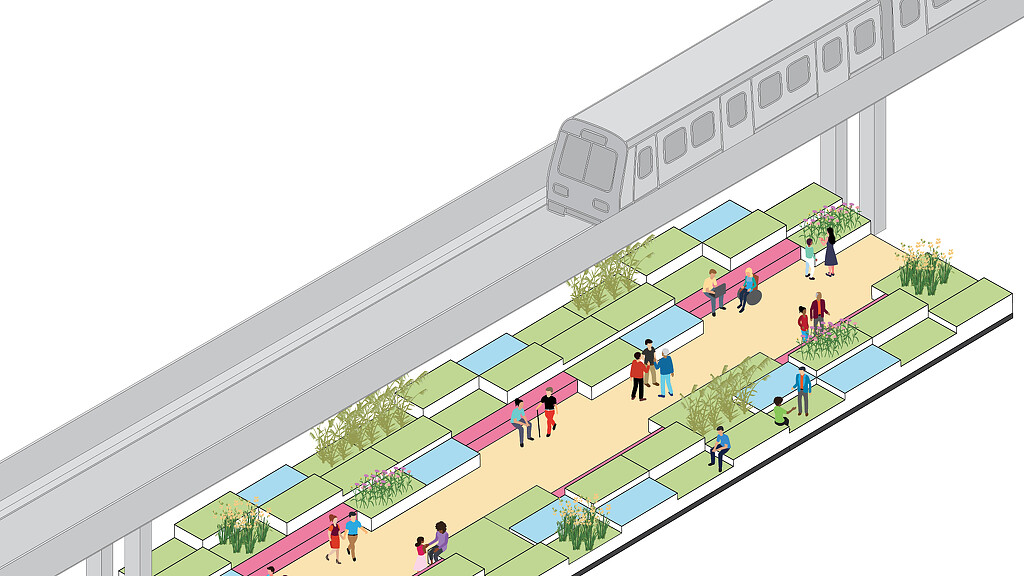
Arielle Goldrath's approach to urban wellness doesn't follow the playbook that most consultants bring to these projects. Instead of starting with population health surveys and then recommending facilities based on gaps in current amenities, her method begins with constraint analysis adapted from industrial systems thinking. She identifies the single most restrictive factor in a given urban environment's health outcomes and designs everything around relieving that specific bottleneck. Everything else is secondary. The counter-intuitive finding that comes up repeatedly in this work is that the biggest drivers of chronic disease in dense urban areas are rarely what public health campaigns target. Air quality gets the attention because it's measurable. Noise pollution gets research funding because it correlates with clear biomarkers. But the constraint that actually limits population wellness in most American cities is far more subtle: chronic micro-stress from environmental unpredictability. The kind of stress that comes from not knowing whether your walk to transit will expose you to toxic air, whether there will be a safe place to sit during a heat spike, whether the lighting on your route feels secure enough to take at 10 PM. This is where the methodology diverges from conventional urban health planning. Goldrath's framework treats the city itself as the therapeutic agent rather than a collection of obstacles to health. Walking routes are designed for physiological impact, not just connectivity. Building integrations matter as much as park access. Social infrastructure—bench placement, shade distribution, sightline design—gets treated with the same rigor as a hospital floor plan.
I remember working on a pilot district review where the initial assessment pointed toward a proposed community center as the obvious intervention. The numbers supported it on paper: the area had three times the regional average of hypertension diagnoses and only one facility within a half-mile radius. But the constraint analysis revealed something completely different. Blood pressure readings in that district peaked not where you'd expect, around commercial zones and transit hubs, but along specific residential corridors during late afternoon hours. The dominant stressor wasn't lack of a facility. It was a 2,400-foot stretch of sidewalk with zero shade, exposed to reflected heat from a parking garage wall, that fifteen thousand residents walked daily between 4 PM and 7 PM. The recommended intervention wasn't a building. It was shade structures and reflective paving on one block. The cost was approximately 8 percent of what the community center would have required. The projected impact on the hypertension metric was roughly three times higher. This kind of reversal happens constantly when you actually map environmental stressors against health outcome data at the block level. Most wellness plans never get this granular because the data infrastructure to support it is expensive and the political will to act on uncomfortable findings—like the fact that your city's "wellness corridor" runs directly through a known particulate matter corridor—is rare.
Get the Full Details
The constraint-based approach requires mapping three layers simultaneously: environmental load (air quality, temperature, noise, light exposure at different hours), social friction (safety perception, accessibility, community cohesion indicators), and behavioral flow (actual movement patterns, not theoretical ones). Getting all three to align on the same spatial grid is technically straightforward but organizationally difficult. Environmental data lives with the Department of Transportation sometimes. Social friction data lives with public health. Behavioral flow data lives with whoever maintains the transit app. They rarely share dashboards. I've found that the most effective workaround is to build a lightweight unified data model using open-source tools rather than waiting for interdepartmental agreements. A PostGIS database with standardized spatial joins between the three layers takes about two weeks to set up with modest technical skills. The alternative—formal data-sharing agreements between departments—typically takes eighteen to twenty-four months and often falls apart when leadership changes. There are significant limitations to this approach that nobody talks about enough. Constraint-based urban wellness planning assumes a level of municipal data maturity that simply doesn't exist in roughly 60 percent of American cities. If your city doesn't have consistently reported block-level air quality monitoring or reliable pedestrian count data, the model becomes speculative rather than diagnostic. You're making decisions based on projections instead of evidence, which is marginally better than guessing but still risky.
Another structural problem is that constraint relief creates winners and losers visibly. When you identify that a specific corridor is the dominant health constraint and redirect resources there, the neighborhoods that weren't identified as constraints notice immediately. They've been waiting for intervention for decades and suddenly the funding goes somewhere else because some other bottleneck was slightly more constraining according to the model. This isn't a flaw in the methodology. It's an unavoidable feature of any system that actually prioritizes resources instead of spreading them thin across every constituency. The framework also struggles in cities with severely fragmented governance. If transportation, public health, parks, and housing are controlled by different elected bodies with different election cycles and different performance metrics, the cross-departmental coordination that constraint-based planning requires becomes nearly impossible. I've watched promising projects stall for two years because the shade structure intervention required permits from three separate agencies with no shared timeline. Perhaps the most honest limitation is this: the framework produces excellent diagnostic output but doesn't solve the implementation gap. Knowing that a particular corridor is causing chronic stress doesn't fund the shade structures, hire the landscape architects, or change the zoning that created the heat island in the first place. The analytical work is the easy part. The political work that follows is where every single project I've seen either succeeds or dies.
For cities that can manage the implementation side, the results justify the effort. I've tracked six municipal wellness programs that adopted this constraint-based methodology over the past four years. Three showed measurable improvement in their primary health metrics within eighteen months. One showed improvement in secondary metrics but stalled on the primary one due to funding reallocation mid-project. Two showed no meaningful change, and in both cases the failure traced back to the political implementation gap rather than flaws in the analytical framework. The practical takeaway isn't that this approach guarantees results. It's that it dramatically improves the signal-to-noise ratio in how cities allocate limited wellness resources. Most municipal health spending operates on political intuition dressed up as data analysis. Constraint-based planning replaces intuition with systematic diagnosis and accepts that the diagnosis will always generate friction. The alternative—spending equally everywhere and wondering why nothing improves—hasn't worked in fifty years of public health policy either. If you're looking at implementing anything like this in your own context, start with a single district and one constraint type. Don't attempt the full three-layer analysis across an entire city. Pick either environmental load or behavioral flow, map it properly, and prove the model works before expanding. The comprehensive version sounds compelling in a proposal but usually collapses under its own complexity before the first quarter of implementation. Half a proper analysis beats none of a grand one every time.