What Nobody Tells You About High Uric Acid Before You Develop Gout
I spent about three years working with patients who showed up with swollen ankles and were convinced they had twisted a ligament. Turns out half of them were just sitting on a uric acid level of 8.5 mg/dL. That is the number where crystals start precipitating in your joint fluid. You do not feel it happening. The first time you notice anything is when your big toe looks like it lost a fight with a clamp. Uric acid itself is a normal waste product. Your body breaks down purines from food and cellular turnover into it, and your kidneys filter it out through urine. When the balance tips and your blood contains more uric acid than can stay dissolved, you get hyperuricemia. The threshold is roughly 6.8 mg/dL at body temperature. Below that, everything stays in solution. Above it, monosodium urate crystals form. They are sharp. They sit in your joints and around your tendons and your body mounts an inflammatory response to something it cannot phagocytose fast enough.
The Dark Side Of Uric Acid High Spot The Symptoms Before Its Too Late
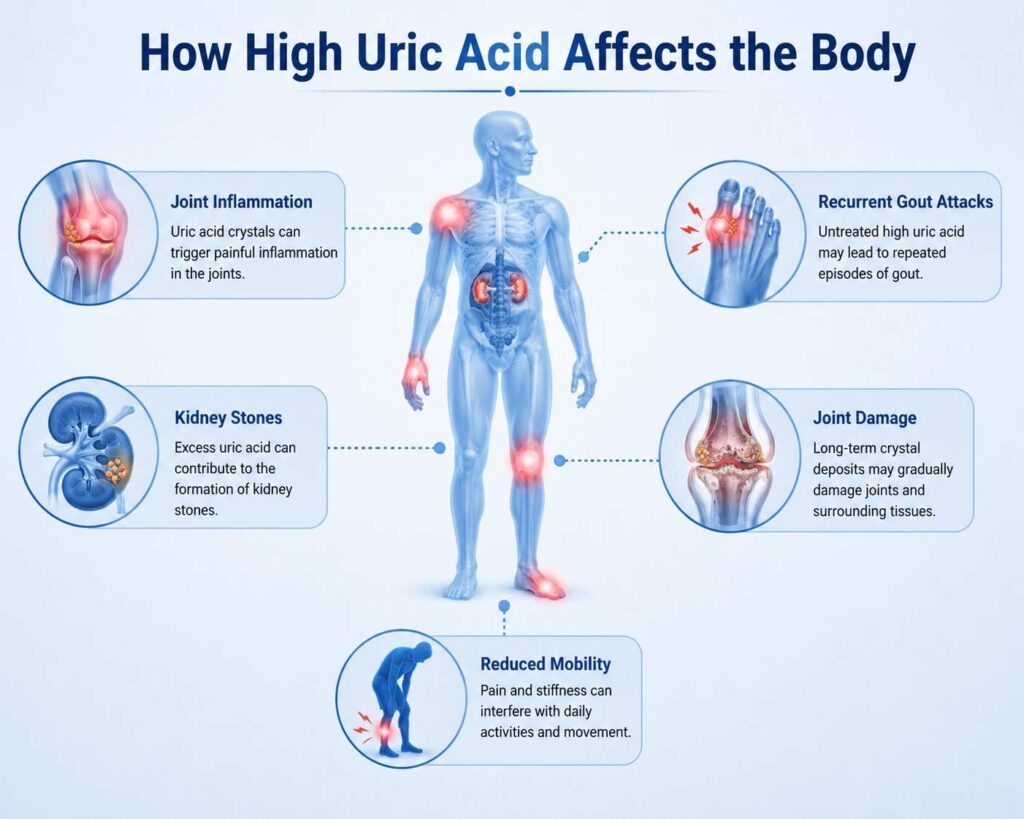
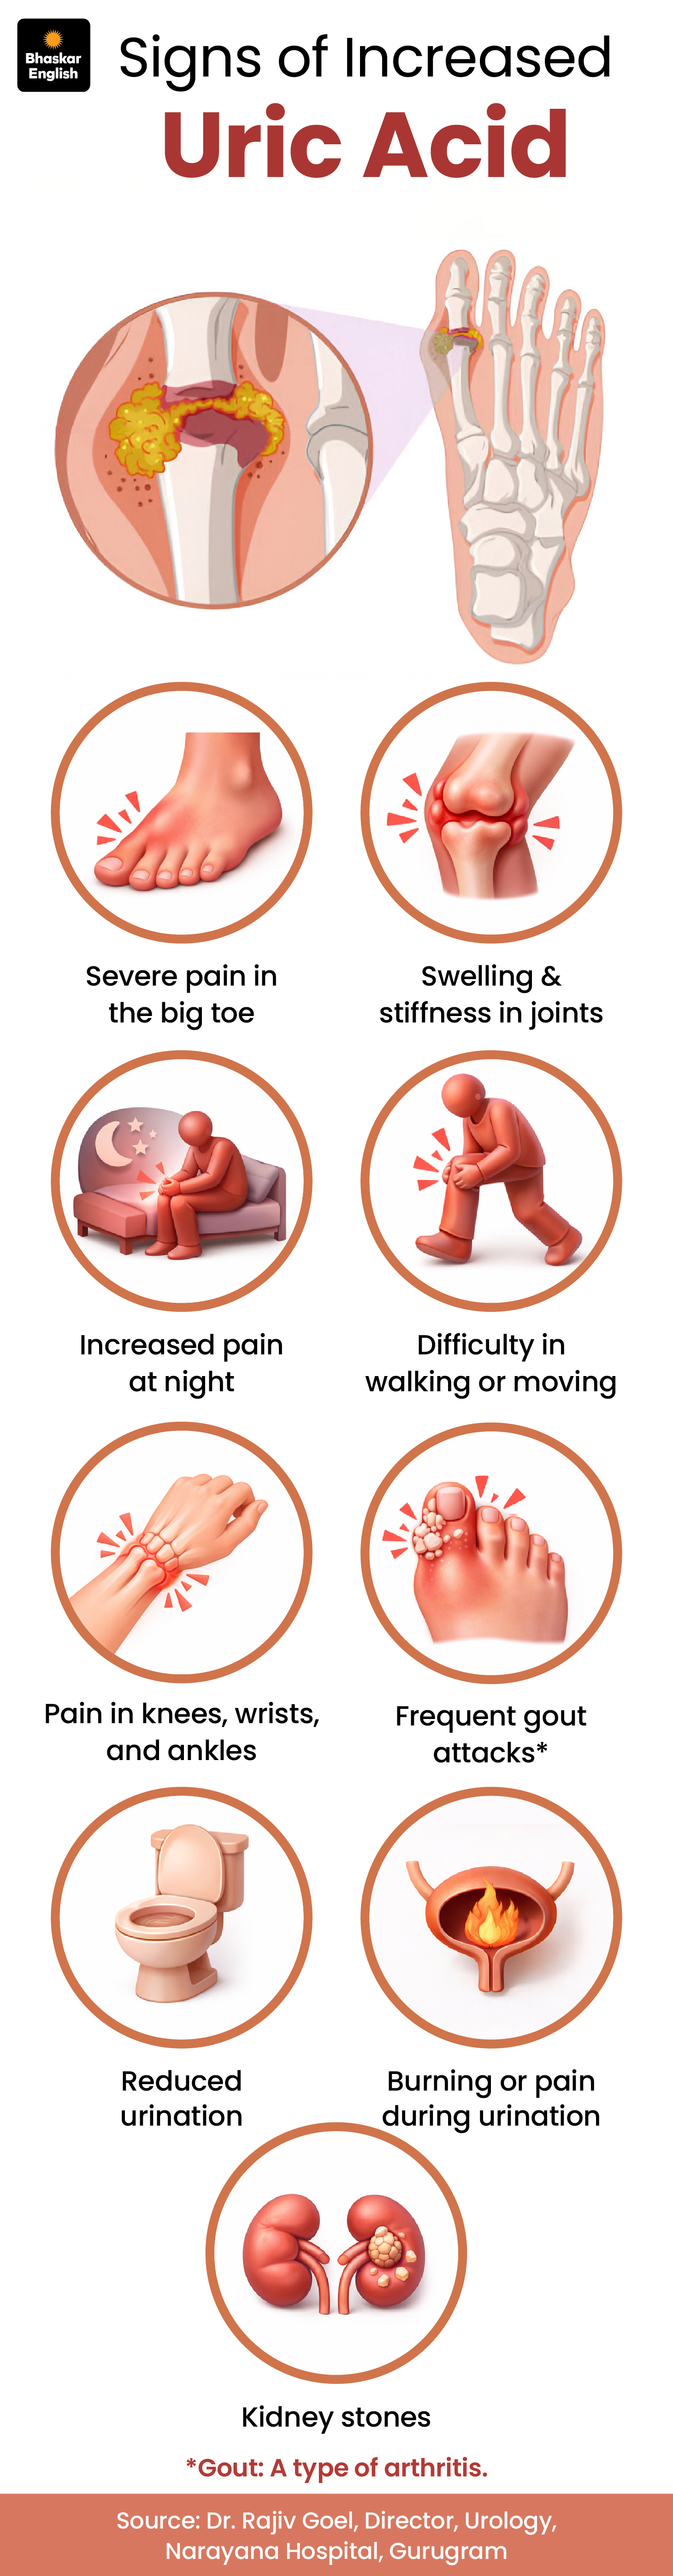
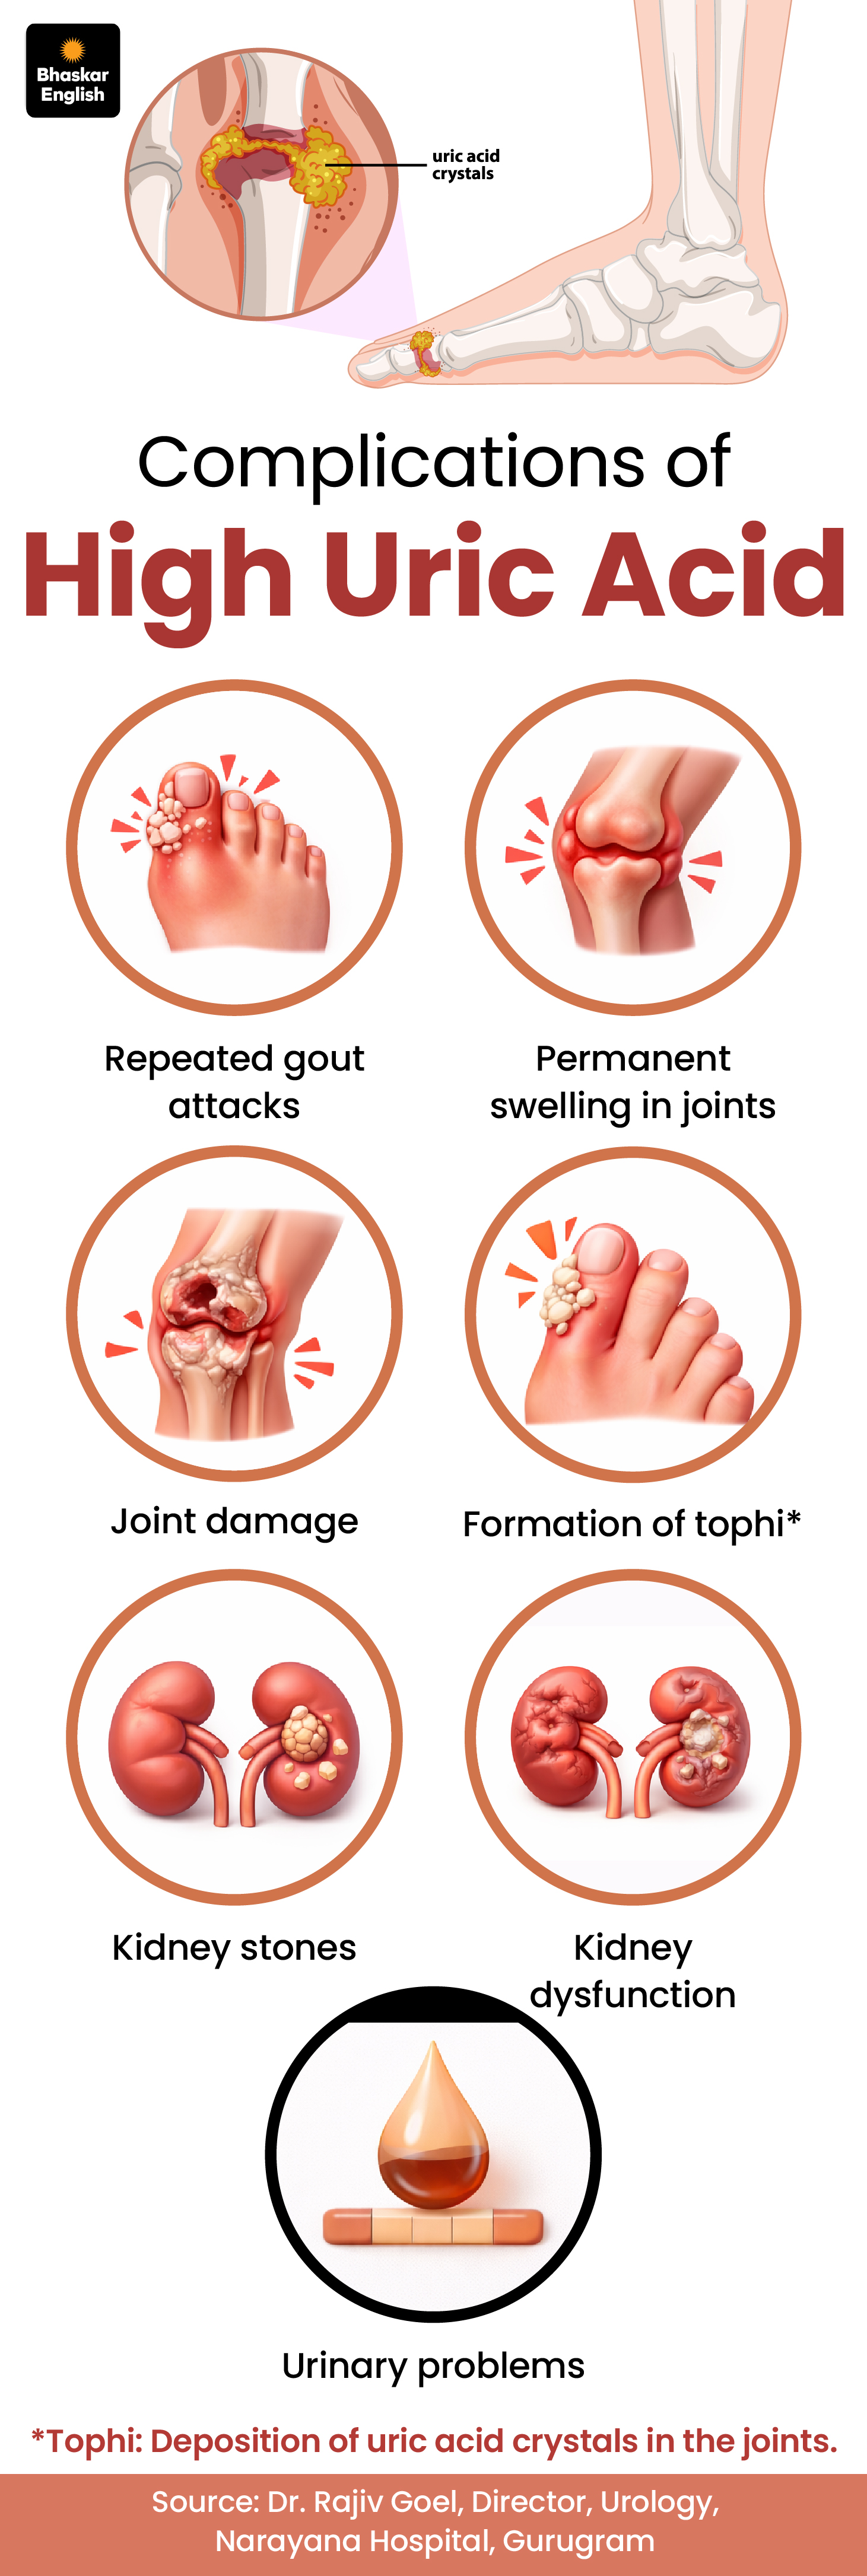
The thing about uric acid is that most people ignore it until the acute phase hits. There is no pain signal at the hyperuricemia stage. Your lab draw comes back with a number that says 9.2, you nod, and you go home. Two months later you wake up at 2 AM with your foot so sensitive that even the sheet touching it feels like sandpaper on bone. That is an acute gout flare, and it usually peaks within twelve hours. The joint gets red, hot, and visibly swollen. Some patients get a low grade fever during a severe episode because the inflammatory cascade releases cytokines into the systemic circulation. Before the flare, there are subtle signs that most people write off. A dull ache in the metatarsophalangeal joint after a heavy meal. A feeling of fullness around the ankle that does not quite match a sprain. Tophi can develop years before any painful attack. These are chalky deposits of urate crystals under the skin, most commonly on the fingers, the helix of the ear, or the Achilles tendon. I had a patient who had a tophus the size of a walnut on his elbow. He had never had a gout flare in his life. The mass was just there, hard, non tender, and slowly growing for about four years. We confirmed it with dual energy CT and the crystal composition was 100 percent monosodium urate. Here is what most general practitioners miss when they first see an elevated uric acid reading. They check the number and then wait for symptoms. But recent data suggests that asymptomatic hyperuricemia can cause renal damage independently of gout attacks. Urate crystals deposit in the interstitium of the kidney, causing chronic tubulointerstitial nephritis. It is a slow process. You will not feel it. Your eGFR drifts downward over five to ten years and you end up with stage 3 chronic kidney disease without ever having a single painful flare. I started tracking renal function in my patients with urate levels above 9 mg/dL even when they were asymptomatic, and about thirty percent of them showed early tubular dysfunction on urinalysis within eighteen months.
Another thing people do not expect is that dietary purine restriction alone rarely brings uric acid down by more than one mg/dL. Your body produces about two thirds of its uric acid endogenously. The liver makes it from scratch. Only about a third comes from what you eat. So cutting out shellfish and red meat is helpful, but if your kidneys are not excreting uric acid efficiently, which is the case in roughly ninety percent of American adults with hyperuricemia, diet alone will not solve the problem. You need to address the excretion side. That usually means medications like febuxostat or allopurinol, and in some cases probenecid to boost renal clearance. Allopurinol works by inhibiting xanthine oxidase, the enzyme that converts hypoxanthine to xanthine and then to uric acid. It is effective but you have to start low and titrate slowly. Starting at the full dose in someone who has never taken it can actually trigger a flare because rapid shifts in urate levels mobilize crystals from tissue deposits back into the bloodstream. The counter intuitive part is that during an acute flare, starting urate lowering therapy is sometimes the right move if the patient is already on it, but if they are not yet on any medication, most guidelines recommend treating the inflammation first with NSAIDs, colchicine, or steroids, and only introducing the allopurinol or febuxostat after the flare resolves. The reasoning is that introducing a new urate lowerer during an active flare can prolong the attack by shifting the equilibrium and dissolving some surface crystals while deeper deposits remain irritating. I learned this the hard way with a patient in my practice. She had severe bilateral gout in her knees and we started her on allopurinol at two hundred milligrams on the same day we prescribed indomethacin for the pain. The flare lasted eleven days instead of the usual five to seven. We switched to prednisone taper and added colchicine prophylaxis for three months before the next dose adjustment, and that time the response was clean. Kidney stones are another consequence that flies under the radar. Uric acid stones account for about ten to fifteen percent of all kidney stones in developed countries. They form when your urine pH drops below five point five. At that acidity, uric acid precipitates out of solution much more readily than at neutral pH. If you have a history of stones, checking your urinary pH with dipstick at home is cheap and useful. If it reads below five point five consistently, your clinician may recommend potassium citrate to alkalinize the urine, which can prevent stone formation without necessarily requiring aggressive urate lowering drugs. I keep a box of pH strips on my desk now because asking every patient with gout to check their urine pH once a week takes five seconds and catches a lot of people who are silently forming stones.
Get the Full Details

Metabolic syndrome is tightly linked to hyperuricemia. Insulin resistance reduces renal urate excretion by about twenty percent. So if you are overweight, have hypertension, or carry central adiposity, your uric acid level is likely elevated even if your diet is reasonable. In these cases, losing ten percent of your body weight can drop uric acid by roughly one to one point five mg/dL. That is not dramatic but it moves the needle enough to push some people below the crystal precipitation threshold. Combined with reducing fructose intake, which directly stimulates purine synthesis in the liver, the effect is additive. Fructose metabolism consumes ATP and generates urate as a byproduct almost immediately. A single sugary drink can raise your serum uric acid within an hour. This is why high fructose corn syrup in sodas is considered one of the strongest dietary drivers of gout prevalence in the last thirty years. The limitations of self monitoring are worth stating bluntly. Home uric acid test kits exist but they measure capillary blood from a finger prick, and the variance between those and a venous lab draw can be anywhere from zero point five to over one mg/dL. If you are trying to track whether a lifestyle change is working, a single home test is not reliable. You need at least three readings over two weeks to get a sense of the baseline. And if your level is consistently above eight, you should not be relying on home tests to decide whether to see a doctor. The threshold where we typically consider pharmacological intervention in symptomatic patients is a sustained level above six mg/dL, and above seven in anyone with tophi or recurrent flares. For asymptomatic patients with comorbidities like hypertension or CKD, many clinicians treat earlier, sometimes starting medication when the level exceeds nine regardless of symptoms. There is also a genetic component that no amount of diet modification will fix. Some people carry variants in the ABCG2 transporter gene, which is responsible for about fifty percent of renal uric acid excretion. If you have two copies of the loss of function variant, your kidneys simply cannot clear uric acid efficiently no matter how clean your diet is. I had a patient, lean, never drank alcohol, ate mostly vegetables, and his uric acid was stuck at ten point two for eight years. We tried everything conservatively for six months before confirming the ABCG2 mutation. Once we knew the mechanism, we went straight to febuxostat and his level dropped to four point eight within three weeks. The diet was never the problem. The excretion pathway was broken.
If you have been noticing any of the earlier signals, a joint that feels oddly warm without redness, swelling that comes and goes over weeks, or unexplained fatigue after meals high in purines, getting a basic metabolic panel with a uric acid number drawn is the most efficient next step. It costs about thirty dollars at a direct lab and the result takes twenty four hours. Waiting for a full flare to appear before doing anything means you have already crossed the crystal precipitation threshold, and the tissue damage from repeated flares is cumulative. Each attack erodes a little more cartilage. By the time you have chronic tophaceous gout, the joint destruction is often irreversible. The goal is to catch it at the hyperuricemia stage, before the crystals have time to organize into any significant deposit. That is where the window is widest and the interventions are simplest.