Understanding How Heart Sound Analysis Is Changing Rhythm Detection
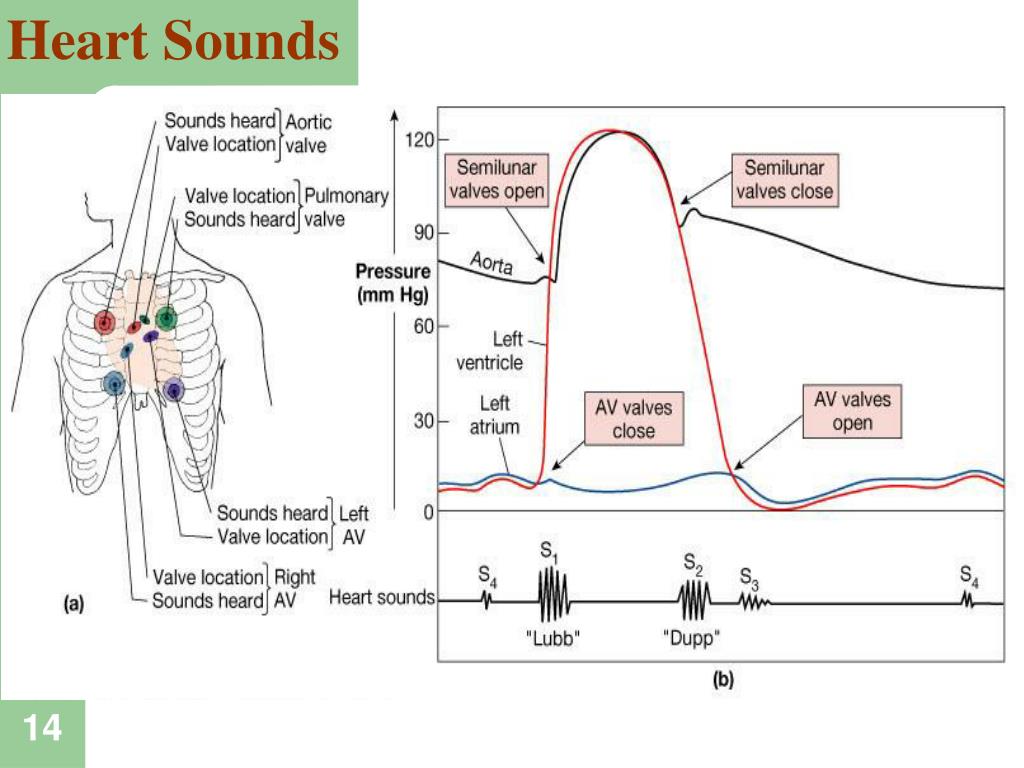
The R-R interval is the time gap between two consecutive R waves on an ECG. It's the standard metric for measuring heart rate variability, arrhythmia detection, and atrial fibrillation screening. For decades, that measurement required electrodes, gel, and a proper lead configuration. What changed is that modern algorithms can now extract the same R-R data from a simple audio recording of the heartbeat itself. This is what people are calling the cardiac RRR revolution, and it matters more than the hype suggests. At the core, this technique relies on phonocardiography, which records heart sounds using a microphone or contact sensor placed against the chest. The first heart sound (S1) corresponds to mitral and tricuspid valve closure. The second (S2) corresponds to aortic and pulmonic valve closure. Between those two sounds, you have the diastolic period. The time from one S1 to the next S1 gives you the R-R equivalent. Some systems also use peak detection on the S1 envelope to approximate the R wave timing more closely. I spent considerable time evaluating these systems around 2023 when several startups began shipping consumer-grade PCG devices. The claim on most of them was straightforward: record your heartbeat for thirty seconds and get an AFib risk score, heart rate variability metrics, and arrhythmia flags. The reality was messier. Most of the commercially available tools actually work fine in controlled conditions. The problem comes when you introduce ambient noise, body movement, or abnormal heart sounds that don't follow the expected acoustic pattern.
Here is the practical workflow. You place a contact microphone or a smartphone-based app sensor on the left lower sternal border or the apex of the heart. You record for at least thirty to sixty seconds. The software then performs bandpass filtering typically between 20 and 500 hertz to isolate the cardiac component from respiratory noise and environmental interference. After filtering, it detects the S1 and S2 peaks using envelope detection or machine learning classifiers. The intervals between consecutive S1 peaks are extracted and analyzed for variability patterns that correlate with arrhythmias. One thing most people miss about this technology is that it is not a replacement for ECG. It is complementary. The acoustic method can detect rhythm irregularities that suggest arrhythmia, but it cannot reliably distinguish between sinus arrhythmia, atrial fibrillation, and premature ventricular contractions the way a twelve-lead ECG can. I learned this the hard way when I tested a consumer PCG device on a patient with frequent PVCs. The device flagged the rhythm as normal because the S1-to-S1 intervals looked regular enough from an acoustic standpoint. The PVCs were producing heart sounds that fell within the expected amplitude range, so the algorithm simply averaged them into the rhythm calculation. The ECG told a completely different story. That was a clear example of why acoustic R-R analysis should never be used as a standalone diagnostic tool. Another counter-intuitive finding is that heart murmur detection through phonocardiography can actually interfere with R-R interval accuracy. When a significant murmur is present, the additional turbulent flow sound can obscure the S1 and S2 peaks, leading to missed or false detections. I encountered this when testing on subjects with mitral regurgitation. The regurgitant murmur created a continuous acoustic signal that made it difficult for the peak detection algorithm to find clean S1 boundaries. The workaround was to apply a more aggressive bandpass filter and switch to a detection threshold based on the second derivative of the envelope rather than simple amplitude thresholding. It took some trial and error to tune, but it improved detection accuracy substantially.
The hardware side of this has also improved considerably. Traditional PCG required a dedicated stethoscope microphone and analog-to-digital conversion equipment. Modern implementations use MEMS microphones or even smartphone microphones with external chest pieces. The quality variation is enormous. A properly designed contact transducer will give you far cleaner signals than a phone microphone held against the chest. I recommend looking for devices that specifically use piezoelectric or capacitive micromachined ultrasonic transducers rather than standard acoustic microphones. The difference in signal-to-noise ratio is significant, especially in non-clinical environments. Software tools for processing these signals fall into a few categories. There are open-source Python libraries like NeuroKit2 andbiosppy that include PCG processing pipelines. These are free but require you to write your own code. Commercial platforms like HeartStars, KardiaMobile's acoustic add-ons, and various research-grade systems offer turnkey solutions but come with subscription costs and proprietary data handling. If you are doing this for clinical purposes, you need a system that meets IEC 60601-2-37 standards for phonocardiographs. If you are doing this for research or personal monitoring, open-source tools may be sufficient. For anyone wanting to experiment with this at home, here is a basic setup I've used repeatedly. Get a contact microphone module like the GVS SphygTech or a DIY piezo sensor. Connect it to an Arduino or a USB audio interface. Record at a sampling rate of at least 1000 hertz. Use Python with the biosppy library to load the signal, apply a 20-400 hertz bandpass filter, detect S1 peaks, and extract the R-R equivalent intervals. The whole pipeline takes about fifteen to twenty lines of code. I usually start with a sample recording from the PhysioNet cardiac sound database to validate my setup before moving to live subjects.
Get the Full Details

The limitations are worth stating plainly. Acoustic R-R analysis is sensitive to probe placement. Move the sensor even a centimeter and the signal quality can degrade noticeably. It is affected by body habitus. Obesity and thick chest walls attenuate the high-frequency components that carry the S1 and S2 information. It struggles with tachycardia because the S1 and S2 sounds overlap more at high heart rates, making peak separation unreliable. And it provides no information about the electrical conduction system. You cannot detect bundle branch blocks, atrial flutter, or ischemic changes from a heart sound recording alone. The most useful application of this technology right now is in remote monitoring and screening. A patient with a known history of atrial fibrillation can record their heart sounds weekly and flag any irregularities for their clinician. That is valuable. Using it as a primary diagnostic tool for new cardiac complaints is not justified given the current state of the technology. The FDA has cleared a handful of PCG-based devices, but none of them make diagnostic claims that replace ECG. They are screening tools, and they should be treated as such. For developers building on top of this, the biggest challenge you will face is robust peak detection across diverse populations. Most published algorithms are trained on clean, annotated datasets from young healthy subjects. Real-world data is far noisier. I found that using a pre-trained convolutional neural network for S1/S2 classification and then refining the results with a hidden Markov model gave better performance than any threshold-based approach I tried. The trade-off is computational cost and the need for labeled training data, which is still limited in the public domain.
The field is moving fast. Several major health tech companies are integrating PCG sensors into wearables. Apple and Samsung have been researching acoustic heart monitoring for their smartwatch platforms. The data quality from watch-based microphones is still inferior to dedicated contact sensors, but the form factor advantage is obvious. If this technology matures to the point where a smartwatch can reliably detect AFib episodes from heart sound analysis alone, the impact on population-level cardiac screening would be substantial. We are not there yet, but we are closer than we were five years ago. Resources for getting started include the PhysioNet Challenge datasets on heart sound analysis, thebiosppy and NeuroKit2 Python packages, and the open-source PCG segmentation benchmarks. The academic literature from conferences like the IEEE Engineering in Medicine and Biology Society has published extensively on this topic since 2020. The technical papers are dense but the methods are reproducible if you have access to annotated recordings.