Understanding Post-Op Drain Output: A Practical Guide for Clinical Staff
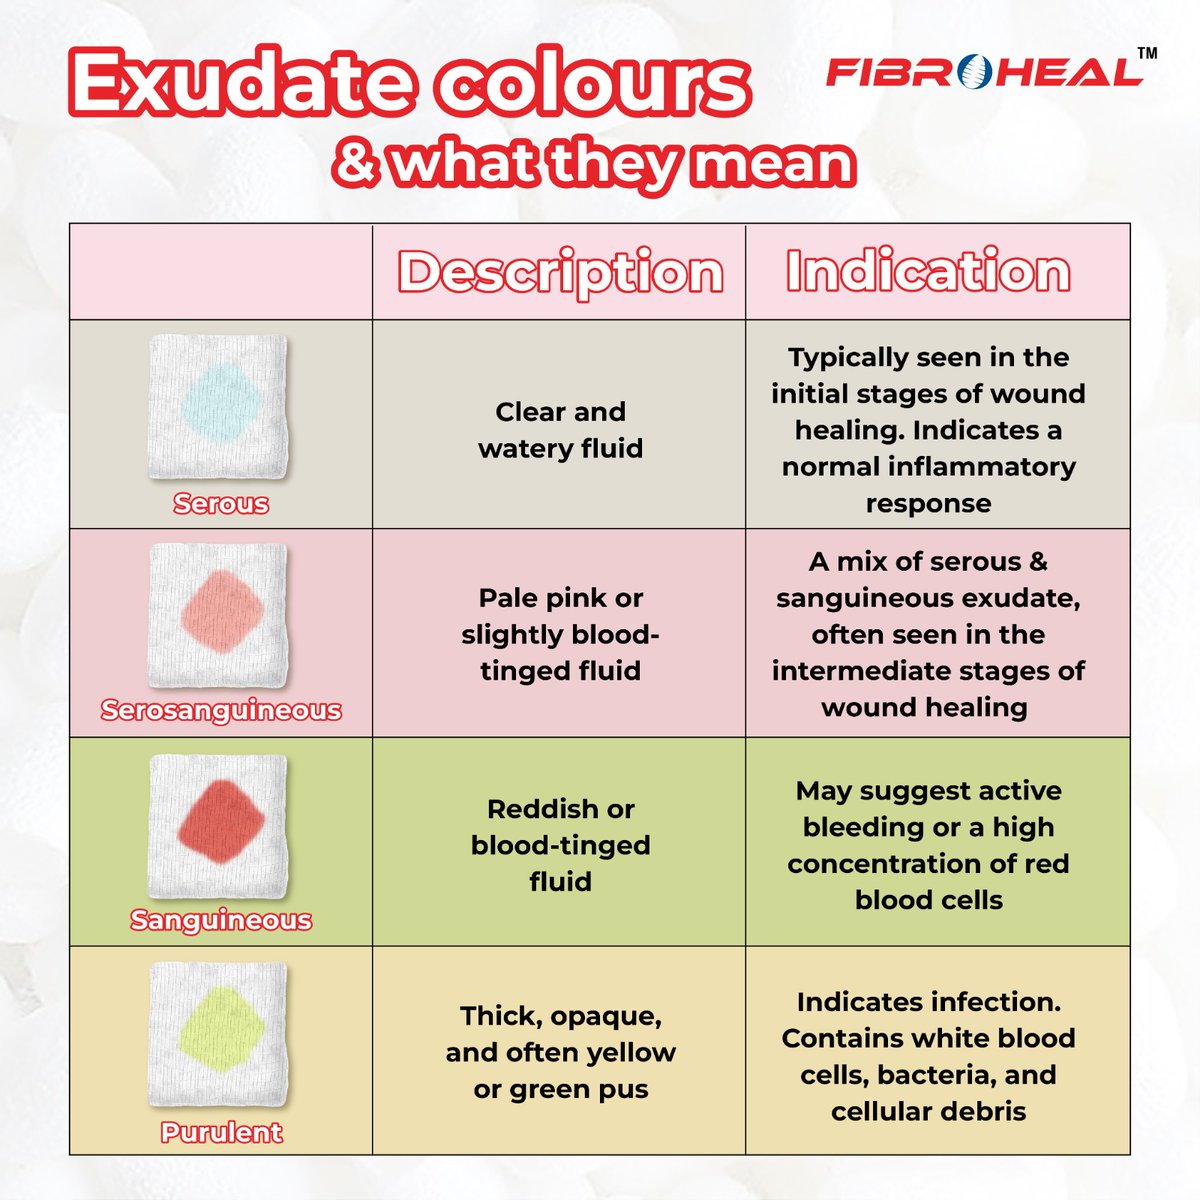
Every hospital I've worked in has had some version of a color chart posted somewhere near the nursing stations or surgical wards. They're usually laminated sheets that correlate drain fluid appearance with likely clinical conditions. The purpose is straightforward — help bedside staff quickly recognize when drainage is moving from expected to concerning, and escalate before a patient deteriorates. I'm going to walk through what the colors actually mean in practice, not just what the textbook says. Most charts cover six to eight categories, and understanding the edge cases is where things get tricky. Here is the breakdown based on what you will actually see on the floor. Serous — pale yellow to light amber. This is normal post-operative drainage. It's thin, watery, and appears in the first 24 to 48 hours after most procedures. The volume matters more than the color here. A cholecystectomy patient draining 30ml every four hours is fine. Same color draining at 150ml per hour means something else is going on.
Serosanguinous — pink to light red. Very common in the first couple of days. Blood mixes with serous fluid and you get this color. Again, volume and trajectory matter. If it lightens over time, you are watching the right pattern. If it stays this color past day three after a clean surgery, you start asking questions about possible bleeding sources. Hem sanguineous — bright red, thick. Active bleeding. Not always surgical re-bleeding, though that is the first thing you rule out. Could be a coagulopathy, could be anticoagulant reversal issues, could be a vessel that slipped its clip. When I saw this after a splenectomy, we called the surgeon immediately. Time matters. You do not wait to see if it changes. Purulent — yellow to green, opaque, often thick. Infection. This can show up anywhere from day two to week two depending on the procedure. Some patients produce purulent drain output and feel completely fine. Others look terrible and the fluid looks almost clear. Do not use appearance alone to rule infection in or out. Send cultures. Check the white count. Look at the patient.
Chylous — milky white. This is lymphatic fluid. You see it mostly after retroperitoneal surgery, thoracic procedures, or any operation near the cisterna chyli. It is often mistaken for pus because both are opaque. The key difference is the triglyceride content. Chyle tests positive for triglycerides above 110 mg/dL. Pus does not. I had a case once where a post-op pancreatic surgery patient had white drain output and the initial impression was infection. We sent it for chemistry instead and caught a chyle leak before it became a major problem. The patient avoided a second surgery by catching it early. Bilious — dark green to brownish-green. Bile leakage. Common after hepatobiliary surgery. The color is distinctive enough that experienced staff usually catch it, but it can be subtle when mixed with serous fluid. If you are unsure, send a bilirubin level on the drain fluid. A ratio of drain fluid bilirubin to serum bilirubin greater than one suggests a leak. Urine — straw yellow to clear, sometimes cloudy. Urinary leak is rare but happens after pelvic or urological surgery. You can confirm with a creatinine level on the drain fluid. Drain fluid creatinine significantly higher than serum creatinine means urine is in the mix.
Get the Full Details

Here is something the charts do not tell you, and it took me years to learn it properly: the timing and trend are almost always more important than the absolute color on any given day. A patient might have bright red output on post-op day one and everything is normal. That same color on post-op day five after a hysterectomy is a problem. Context changes everything. Another thing nobody emphasizes enough: lighting conditions matter more than people realize. I have watched nurses flag output as "slightly blood-tinged" under fluorescent ward lights, then have the same fluid look completely clear in natural daylight. The difference was partly the lighting and partly the drain tubing color. Clear tubing versus colored tubing changes how you perceive the output. Use white background trays when evaluating drain fluid. It sounds trivial but it actually changes your assessment reliably. There is also a practical limitation with these charts that nobody likes to admit — they are blunt instruments. A color chart can tell you something looks abnormal. It cannot tell you why. Two patients with identical green drain output may have completely different problems. One has a biliary leak, another has an infected hematoma, and a third has a simple resolving seroma with coincidental discoloration. The chart gets you to the question. The workup answers it.
If you need a reference sheet, most hospital supply catalogs carry printable versions. The American College of Surgeons and several surgical societies also publish standardized charts that you can adapt. The ones you build yourself in your department tend to work best because they reflect the actual drain types and procedures your unit handles. A generic chart covers everything. A unit-specific chart covers what you actually see. I would also note that digital imaging tools are starting to appear for objective color analysis, but they are not reliable enough yet to replace clinical judgment. The lighting variables, the opacity differences, and the bag material all introduce enough noise that a phone camera reading is more likely to mislead than help. Stick to what you can see with your own eyes under consistent conditions, and document everything with timestamps. The bottom line is that these charts are triage tools, not diagnostic tools. They buy you time to notice something is off so you can investigate properly. Used correctly, they prevent delays. Used blindly, they create false reassurance or unnecessary alarm. Train your staff on both the colors and the limitations, and make sure everyone understands that the chart is the starting point, not the answer.