What Syndactyly Actually Is
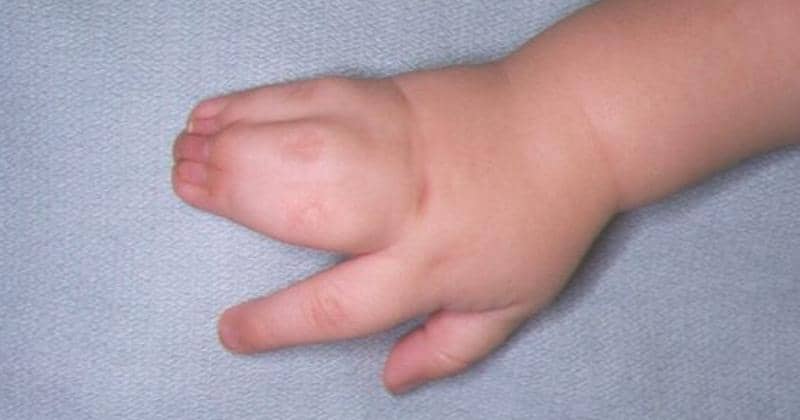
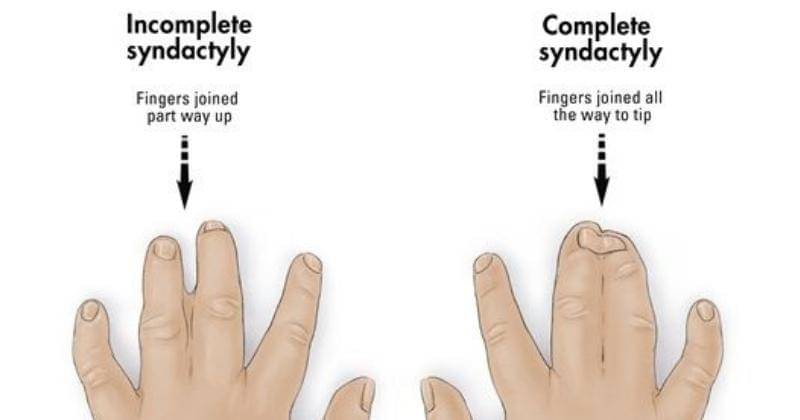
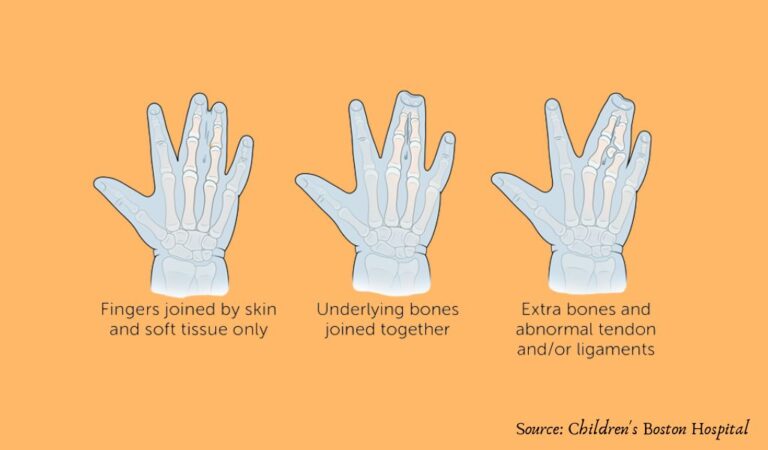
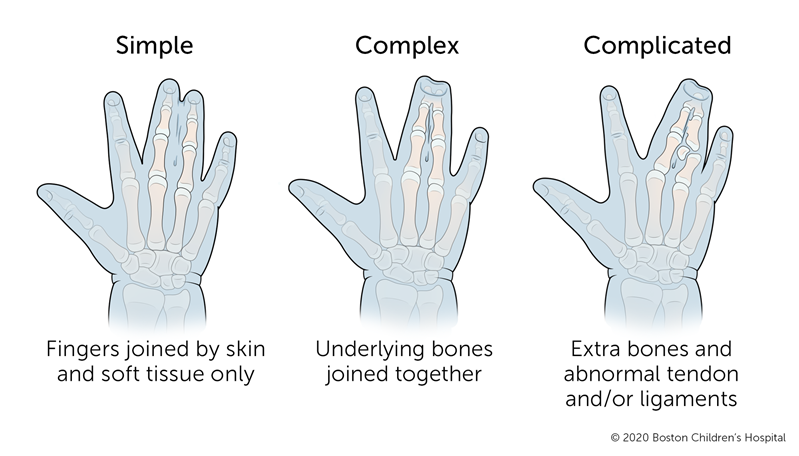
Syndactyly is a congenital condition where two or more fingers or toes remain fused together instead of separating during fetal development. It shows up in roughly 1 in every 2,000 to 4,000 live births. Sometimes it affects just one web space between two digits. Sometimes it involves multiple digits on both hands and feet. The severity ranges from a thin band of skin connecting two fingers to fully fused bone structures that look like a single paddle-shaped digit. The exact cause isn't always clear. In many cases it's an isolated genetic event with no family history. In other cases it runs in families as an autosomal dominant trait with variable expressivity. Certain genetic syndromes list syndactyly as one of their features - Apert syndrome being the most well-known, but also Poland syndrome, Ellis-van Creveld syndrome, and a handful of others. Exposure to certain teratogens during pregnancy can contribute, though most cases simply happen without any identifiable external trigger. Surgical separation is the standard approach, and timing depends heavily on which digits are involved. For simple skin-only syndactyly between the index and middle fingers, surgeons typically operate between 6 and 18 months of age. Waiting too long risks contracture and difficulty with fine motor development. Operating too early increases anesthesia risk and technical difficulty with tiny structures.
More complex cases involving the ring and little fingers, or cases where bones are fused, require a different timeline. These often get delayed until 12 to 24 months, sometimes longer if the child needs additional procedures. Bone fusion, called complex syndactyly, may need osteotomy and bone lengthening in addition to soft tissue release. The surgical technique itself involves a Z-plasty or similar flap advancement to create new web space and prevent the reconstructed web from contracting back together. Skin grafts are frequently necessary, usually taken from the groin or forearm, to cover the exposed surfaces after the digits are separated. Without a graft, the raw areas will scar down and pull the fingers back together anyway. I once worked with a case where the surgeons separated the third and fourth digits using only local flaps, no graft. The web space looked fine initially, but by six weeks post-op the scar tissue had contracted significantly. The patient needed a revision surgery with a split-thickness graft and two years of hand therapy to regain usable range of motion. That case reinforced how important it is to plan for graft coverage when the dorsal skin isn't sufficient to close primarily.
Pitfalls People Miss
One thing that surprises families is that surgery doesn't guarantee normal appearance. The separated fingers will have visible scars along the web space and potentially along the sides of each digit where grafts were placed. Sensation may be reduced in the operated digits. Stiffness is common, especially if therapy isn't consistently done. Another underestimated factor is that some syndactyly types simply aren't worth surgical correction from a functional standpoint. Cases involving the fourth and fifth fingers where the fusion is minimal sometimes respond better to observation and splinting than to surgery. The cosmetic result can be worse than the original condition, and the hand loses mobility from scarring. A skilled pediatric hand surgeon will usually recommend against intervention in straightforward cases affecting only the ulnar side digits with no functional limitation. Post-operative therapy is non-negotiable. Without it, the digits will re-adhere or develop contractures regardless of how well the surgery went. Therapy typically starts within a week of cast removal and continues for several months. Parents who skip this step often end up back at the surgeon's office within three months dealing with recurrent syndactyly.
Get the Full Details

Not all syndactyly requires treatment at all. Mild cases affecting only the skin between adjacent toes often cause no problems and never need intervention. Toe syndactyly is generally far less functionally significant than hand syndactyly. Many pediatric orthopedic specialists simply monitor these cases and only recommend surgery if the child develops pain, shoe fit issues, or functional complaints later on.