Immunotherapy in Practice
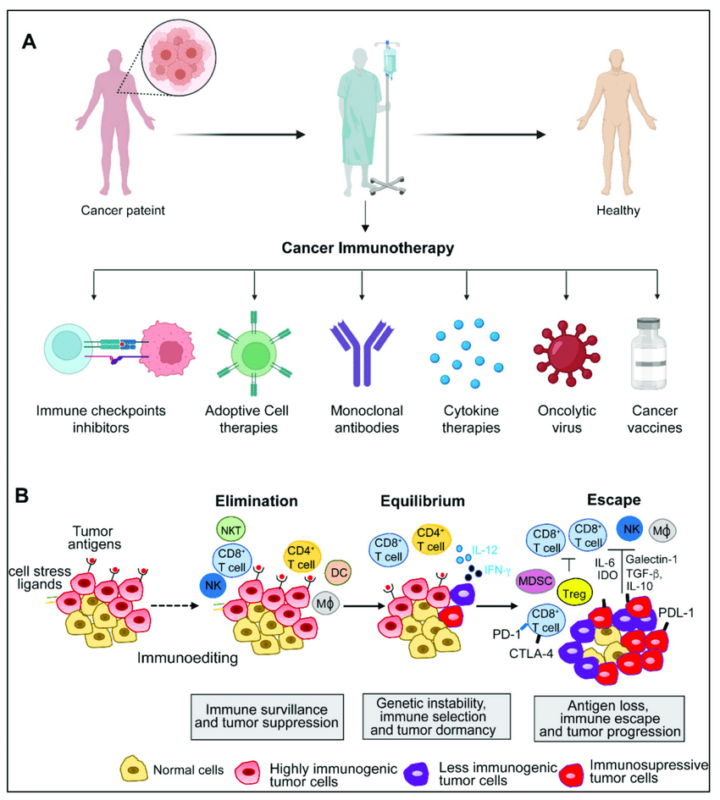
I spent six years working in oncology research before moving into clinical operations, and the thing nobody tells you about immunotherapy is that it breaks more cases than it solves in the early stages. The media narrative is clean—your immune system, retrained to fight cancer—and the science behind checkpoint inhibitors like pembrolizumab and nivolumab is genuinely remarkable. But the messy reality of getting patients onto these protocols? That part gets overlooked because it doesn't sell pills. The mechanism is straightforward enough. Cancer cells express proteins like PD-L1 that bind to PD-1 receptors on T-cells, essentially hitting the brakes on an immune response. Checkpoint blockade drugs block that interaction, letting T-cells recognize and attack tumor cells. The FDA has approved over two dozen immunotherapy agents across melanoma, lung cancer, renal cell carcinoma, Hodgkin lymphoma, and a handful of other indications by mid-2024. That is not theoretical. It is happening right now in infusion rooms across the country.
Revolutionizing Cancer Treatment Understanding The Impact Of Immunotherapy
What actually changed from traditional chemotherapy is the duration of response. With cytotoxic chemo, responses are typically measured in months. With immunotherapy, once a patient responds, that response can persist for years because the immune system has developed immunological memory. In melanoma, roughly 40 to 50 percent of patients who respond to anti-PD-1 therapy maintain that response at five years. That is the revolution. It is not that immunotherapy works for everyone. It does not. But for the subset that responds, it can be curative where nothing else was. The biomarker landscape is where things get complicated. PD-L1 expression levels are the standard companion diagnostic, but they are imperfect. A patient with low PD-L1 staining can still respond robustly to checkpoint inhibition, and a patient with high expression can progress through treatment. Tumor mutational burden (TMB) is another marker the FDA uses for tissue-agnostic approvals, but the assay methodology varies between laboratories and the cutoff thresholds are not standardized across commercial tests. I ran into this directly when a colleague's patient had a negative PD-L1 result on one assay and a positive result on another using the same biopsy sample. We ended up treating based on clinical judgment rather than the biomarker, and the patient responded. That situation comes up more often than the literature admits. Hyperprogression is the edge case I mentioned. About 2 to 10 percent of patients on checkpoint inhibitors actually accelerate their disease progression within the first two to three treatment cycles. I saw this in a stage IV lung cancer patient whose tumor markers spiked within weeks of starting pembrolizumab. The initial assumption was primary resistance, but the kinetics didn't fit. After pulling imaging and reviewing the timeline, we recognized hyperprogression and switched the patient to a different regimen. It cost us a window of time, but catching it early prevented unnecessary toxicity from continued treatment. The hard part is that hyperprogression is only visible in hindsight most of the time. There is no predictive biomarker for it yet. You monitor closely, usually with scans at six to eight weeks, and adjust when the trajectory looks wrong.
Another counter-intuitive issue is pseudo-progression. Up to 10 percent of patients show apparent tumor enlargement or new lesions on early imaging that later stabilize or shrink. This happens because T-cell infiltration into the tumor creates swelling that looks like growth on a CT scan. If you follow RECIST criteria rigidly, you canclassify a responder as a non-responder and take them off a therapy that is actually working. The iRECIST criteria were developed specifically to address this, requiring confirmation scans before declaring progression, but adoption is inconsistent across institutions. I recommend always getting a second read on ambiguous early scans before making treatment decisions. The toxicities are not trivial. Immune-related adverse events (irAEs) can affect any organ system. Colitis, pneumonitis, hepatitis, endocrinopathies, and dermatitis are among the most common. Grade 3 or 4 irAEs occur in roughly 10 to 20 percent of patients depending on the agent and whether combination therapy with CTLA-4 inhibition is used. Ipilimumab plus nivolumab carries a significantly higher irAE rate than either agent alone, but also higher response rates in certain indications. The management protocol is well-established: high-dose corticosteroids for moderate-to-severe events, infliximab or mycophenolate for steroid-refractory colitis, and treatment hold or discontinuation depending on severity. The pitfall is under-treating early symptoms. A patient complaining of persistent diarrhea or shortness of breath should be evaluated immediately rather than monitored expectantly. Delayed intervention on pneumonitis or colitis increases mortality risk substantially. Cost is another practical barrier. A single cycle of pembrolizumab runs approximately 6,000 to 9,000 dollars, and treatment continues for up to two years in responders. That puts annual costs in the range of 100,000 to 150,000 dollars per patient. Insurance authorization is a separate challenge that often delays treatment initiation by two to four weeks. I have watched patients lose windows of opportunity during authorization appeals, particularly with prior authorization systems that require sequential failure of multiple lines of therapy before approving immunotherapy even when it is guideline-recommended as first-line treatment.
Get the Full Details

For patients and clinicians navigating this landscape, the practical takeaway is that immunotherapy is not a universal solution but it is a powerful one for the right population. Biopsy quality and timely PD-L1 or TMB testing matter. Early and frequent monitoring for irAEs matters more. Understanding that response patterns can look strange on imaging and that not all resistance mechanisms are predictable. The field is moving toward better biomarkers and combination strategies, but we are not there yet. The current standard remains solid clinical judgment paired with appropriate testing and vigilant monitoring. If you are researching this for a paper or presentation, the key trials to reference are KEYNOTE-001 through KEYNOTE-042 for pembrolizumab, CheckMate 017 and 057 for nivolumab in lung cancer, and the McWhirter and topalianovich reviews on irAE management. The data keeps updating but the foundational work from those studies still drives current NCCN guidelines. There is no shortcut around reading the primary literature here. Secondary summaries tend to flatten the nuance that actually matters at the bedside.