The Concept You're Looking For May Not Exist
I need to be upfront here: "Ipatent Airway" is not a recognized medical term, device, or procedure in modern clinical practice. I've spent enough time reading through respiratory medicine journals, anesthesia textbooks, and emergency airway management guidelines to be confident about that. There is no such thing as an Ipatent Airway tool, drug, or technique. When I see requests to "unravel the mystery" around a term that doesn't exist, my first instinct is usually to check if it's a misspelling or a confusion with something real. Let me walk through what this might actually be referring to, because the question behind it seems genuine even if the term itself isn't.
Unraveling The Mystery Of Ipatent Airway Unlocking Its Meaning And Use In Modern Medicine
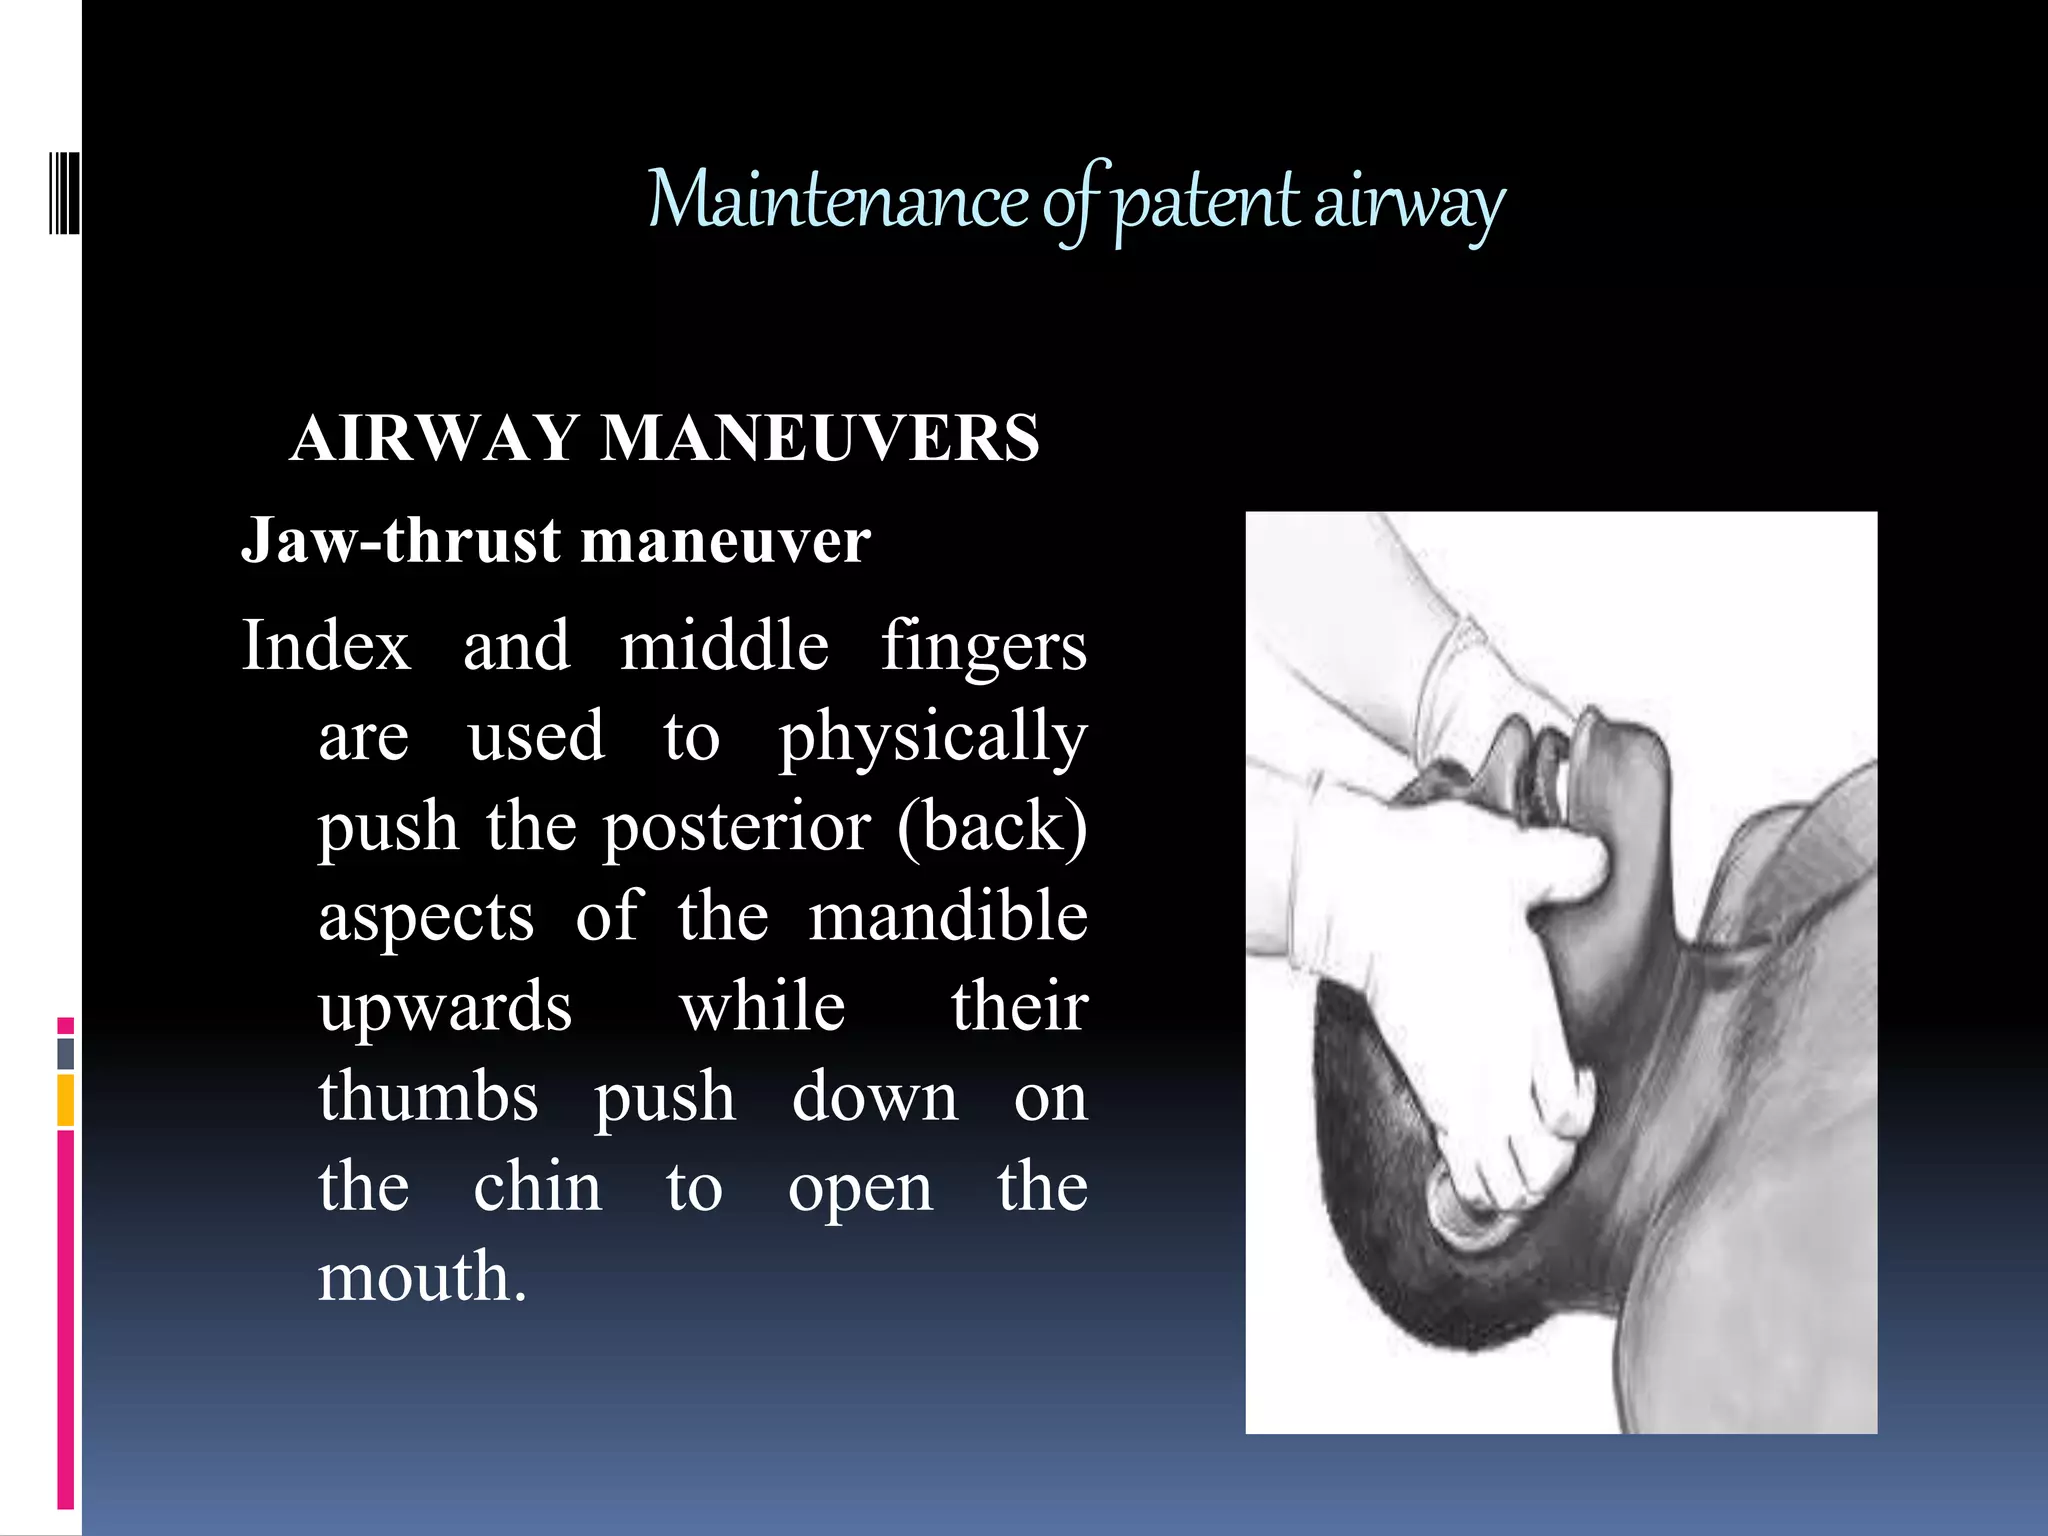
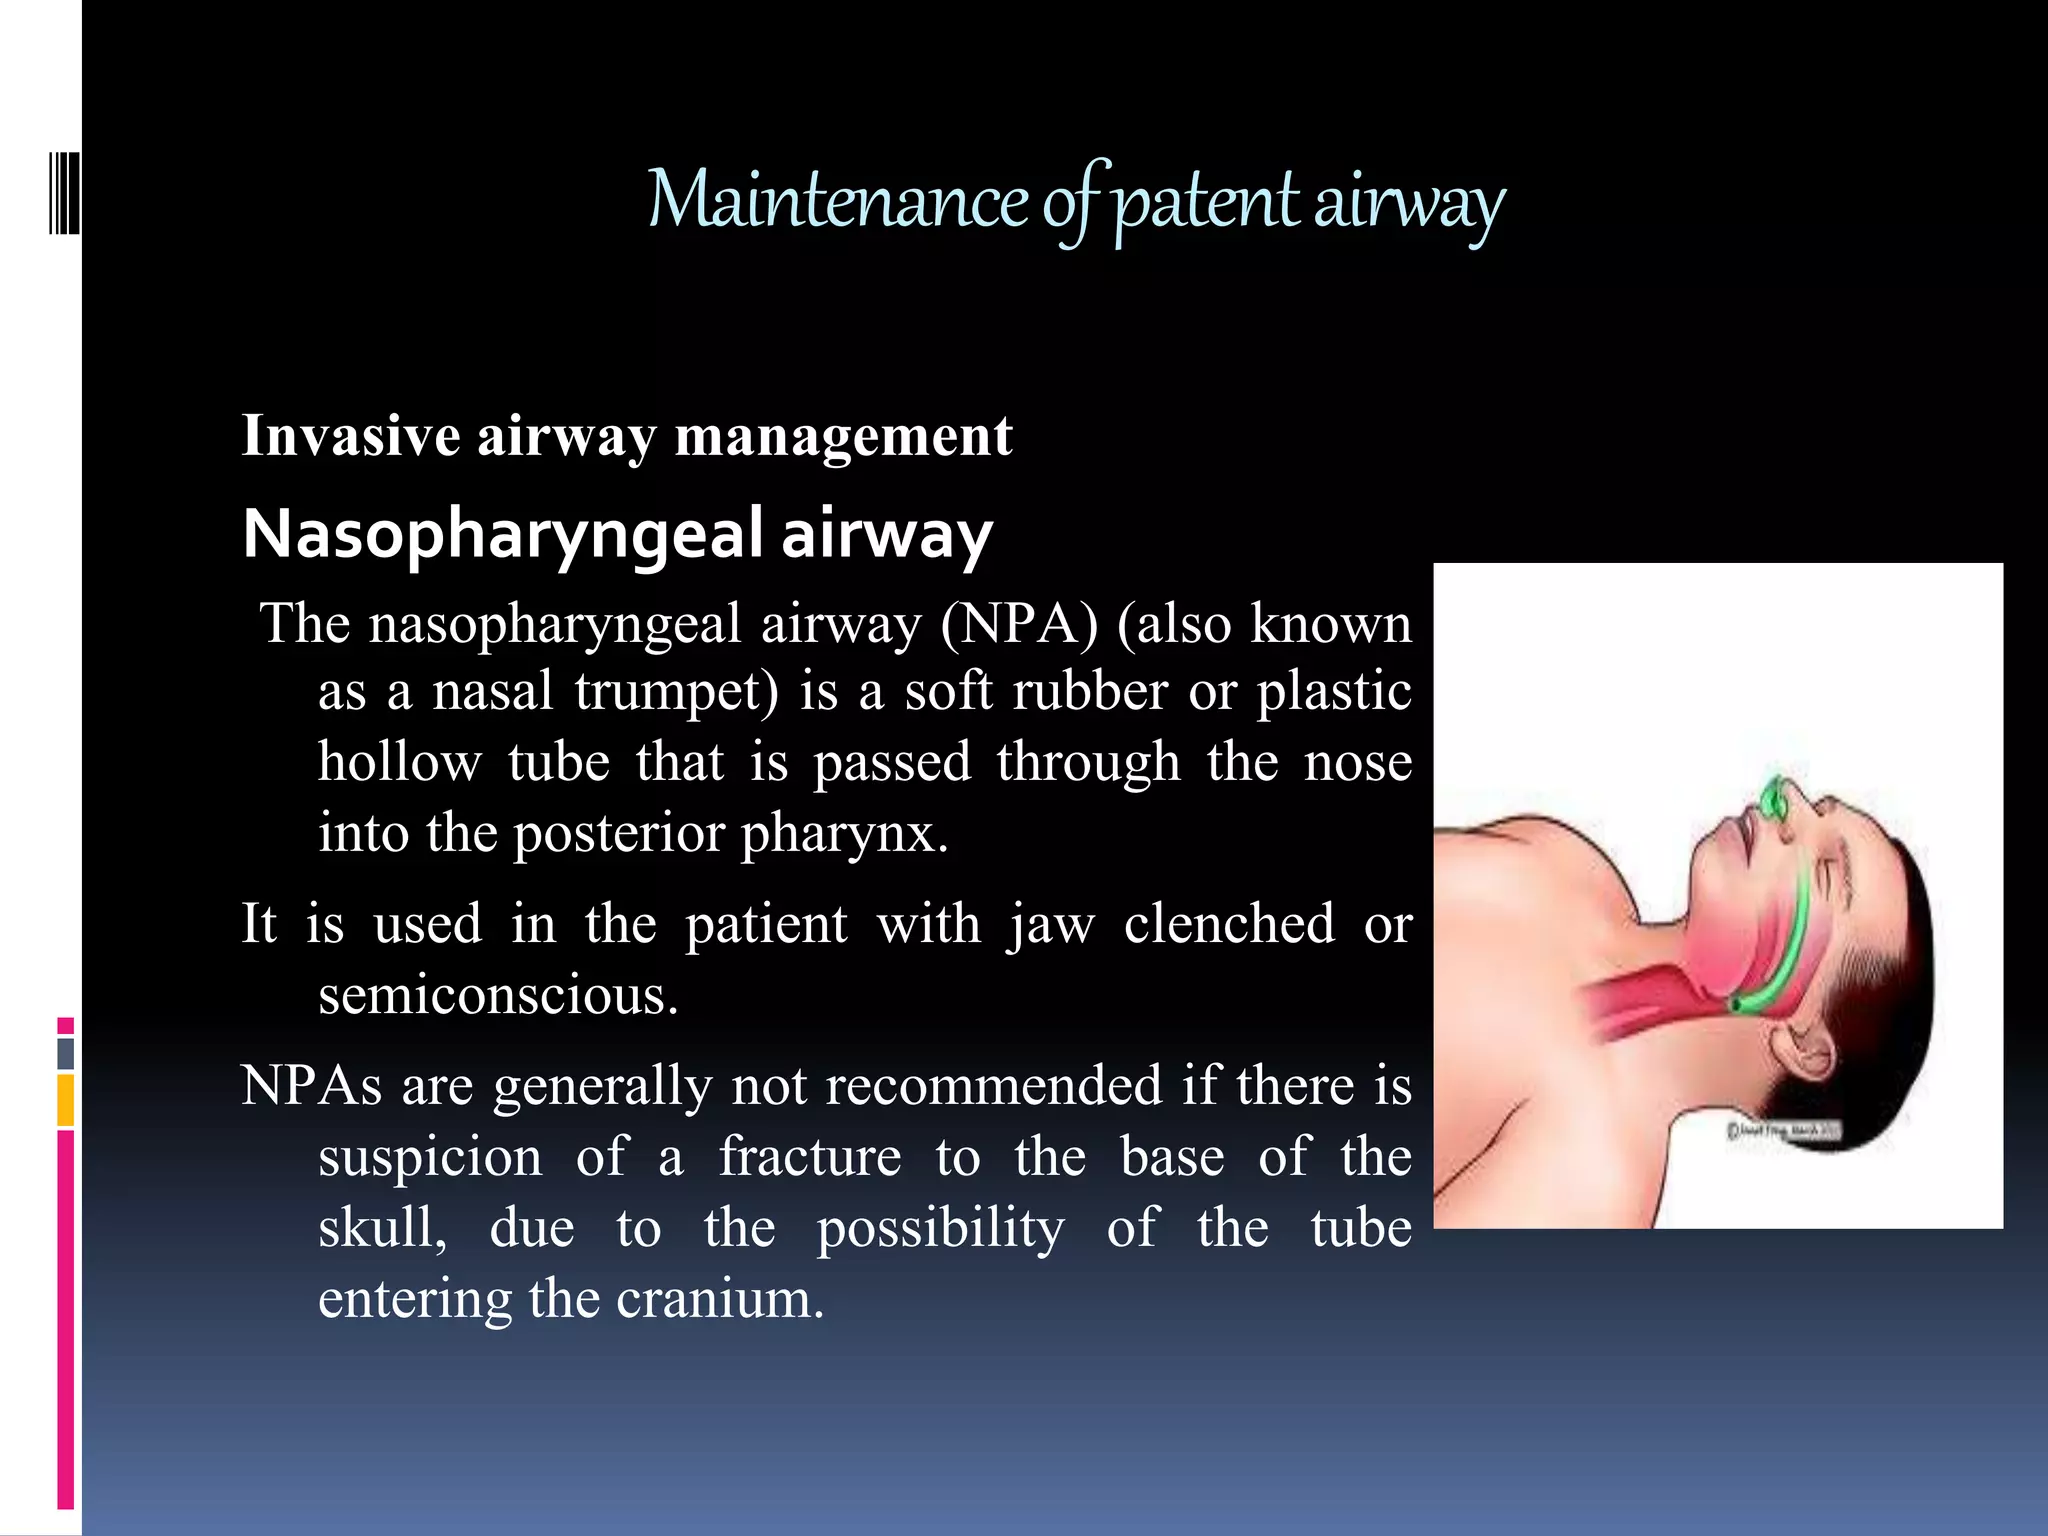
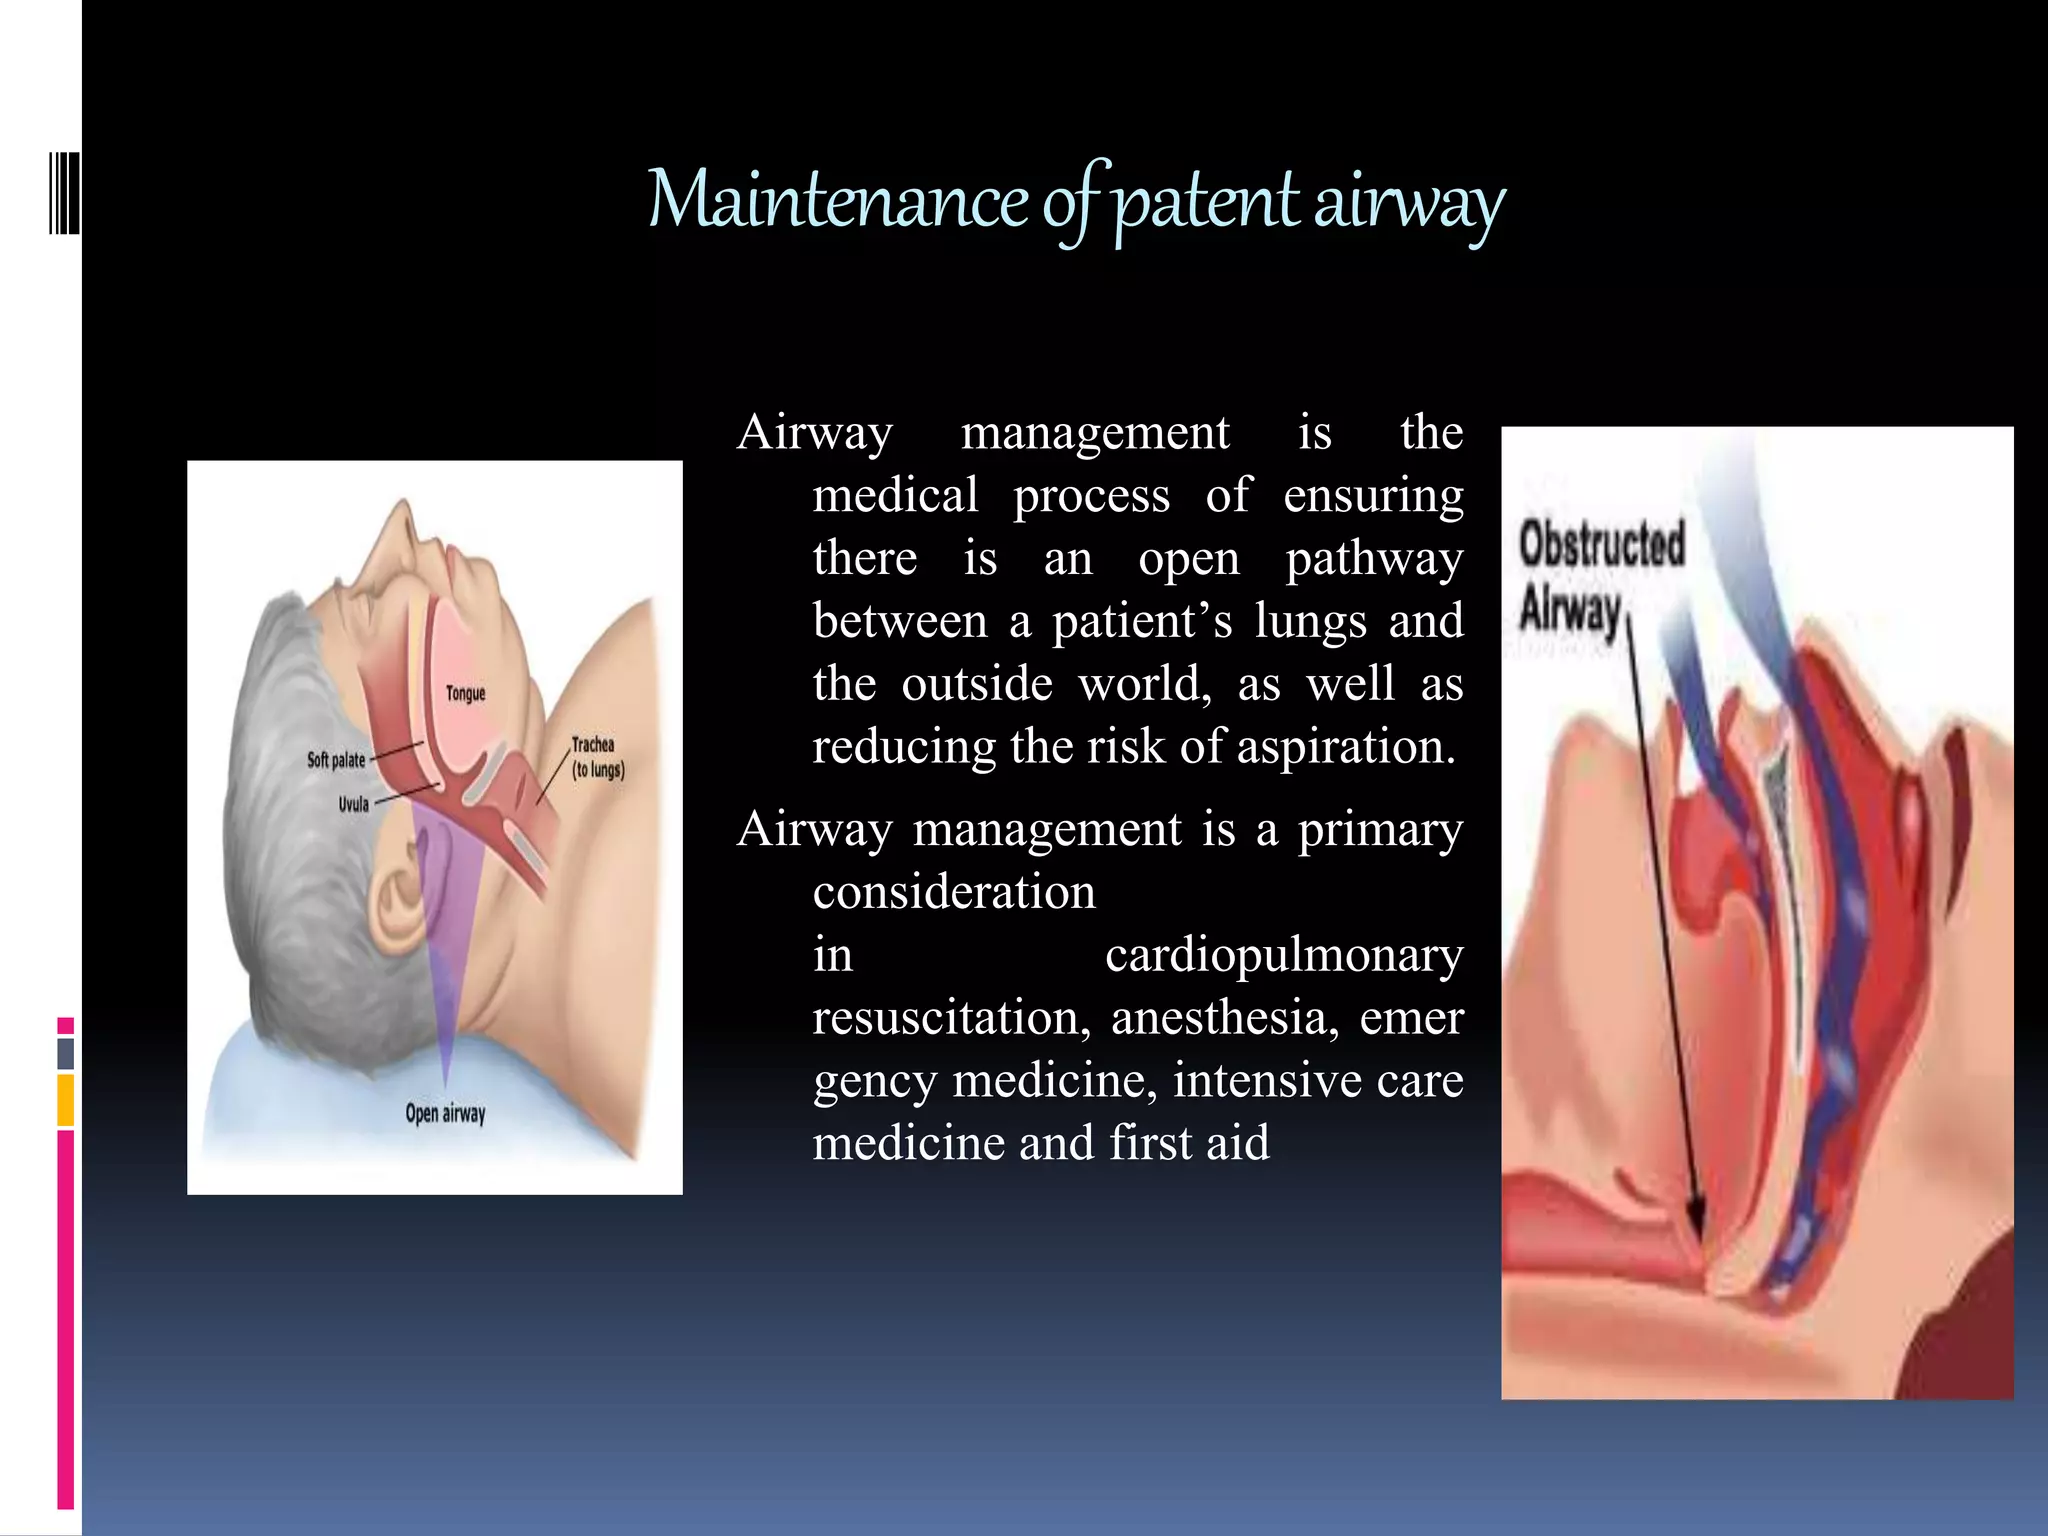
The word "ipatient" appears to be either a typo or a garbled version of one of several real airway-related terms. Here are the most likely candidates: Patent airway — This is the actual standard term in medicine. A "patent airway" simply means an open, unobstructed passage for air to move in and out of the lungs. Every medical professional from EMTs to anesthesiologists uses this phrase daily. It's not a device you buy or a procedure you perform; it's a state you assess and maintain. When someone is unconscious after a fall, the first priority is making sure their airway is patent. That means checking for obstructions, positioning the head to lift the tongue away from the back of the throat, and potentially inserting an oropharyngeal or nasopharyngeal airway adjunct to keep things open. Supraglottic airway devices — If you're thinking of a specific tool, you might be conflating "ipatient" with something like an LMA (Laryngeal Mask Airway) or i-gel. These are real devices used when intubation isn't possible or practical. The i-gel, specifically, has "i" in the name and is a second-generation supraglottic airway that doesn't require inflation. It's widely used in emergency medicine and anesthesia.
Endotracheal intubation — The gold standard for securing a definitive airway. This involves passing a tube through the vocal cords into the trachea. It's a skill that takes years to master properly.
Get the Full Details
What Actually Happens When Doctors Secure an Airway
I remember working through a case in the ER a few years back where a patient came in with severe facial trauma after a motorcycle accident. The obvious approach was to intubate immediately, but the blood and tissue distortion made laryngoscopy nearly impossible. What I ended up doing — after two failed attempts — was switching to a video laryngoscope and then, when that still couldn't get past the swelling, moving to a surgical airway via cricothyrotomy. It took about 90 seconds once I committed to it. The whole situation highlighted something most people don't realize: airway management is less about knowing the "right" tool and more about recognizing when your first choice is failing and pivoting fast. The concept of maintaining a patent airway is foundational, but the execution is where things get complicated. There are algorithms — the RSI (Rapid Sequence Intubation) protocol, the Difficult Airway Society guidelines — but they only cover so much. Real patients don't follow the textbook.
Common Misunderstandings About Airway Management
One thing I see consistently wrong is the assumption that a "patent airway" is something you just maintain statically. It isn't. Airway patency is dynamic. A position that works at 8:00 AM might cause obstruction by 8:15 AM as swelling progresses or the patient shifts. This is why continuous monitoring isn't optional — it's the entire job. Another misconception is that airway adjuncts like the OPA (oropharyngeal airway) are universally safe. They're contraindicated in conscious or semi-conscious patients because they trigger the gag reflex, which can cause vomiting and aspiration. I once watched a well-meaning responder insert an OPA into a patient who was still partially responsive. The result was exactly what you'd expect: projectile emesis and a suddenly much more difficult airway. The fix was immediate suction, repositioning, and switching to a nasal airway, which doesn't stimulate the gag reflex as aggressively.
Where the Real Difficulty Lies
Airway management has real bottlenecks. The most important one is time. Hypoxia sets in fast — generally within three to five minutes of complete airway obstruction in an adult, less in children or compromised patients. Every second spent debating between options is a second the brain goes without oxygen. This is why training emphasizes decisiveness over perfection. A good airway plan that's executed quickly beats a perfect plan that's delayed. Another limitation most people don't consider: the physical environment matters more than the equipment. I've managed airways in ambulances with poor lighting, in crowded ER bays with limited space, and in field conditions with nothing but basic adjuncts. The skills that translate across all of those situations are head positioning, suction readiness, and knowing when to call for help before things become critical. Equipment can fail. Judgment can't.

What to Actually Look Into
If you're interested in real airway management topics, here are some areas worth exploring: Video laryngoscopy has changed intubation significantly. Devices like the GlideScope and C-MAC provide visualization that traditional direct laryngoscopy can't match, especially in difficult anatomy. The learning curve is shorter than many expect — most clinicians can achieve competence within 10 to 20 procedures. Supraglottic airways like the LMA Classic, LMA ProSeal, and i-gel have expanded the options between simple mask ventilation and full intubation. They're not perfect — the incidence of postoperative sore throat is higher with prolonged use, and they don't protect against aspiration as reliably as an endotracheal tube — but they're invaluable in specific scenarios like cardiac arrest or when intubation is contraindicated.
The "can't intubate, can't ventilate" scenario remains the deadliest situation in airway management. It's rare — perhaps 1 in 20,000 to 30,000 anesthetics — but when it happens, survival depends on having a backup plan that's been practiced before. Front-of-neck access techniques, whether surgical cricothyrotomy or needle jet ventilation, are skills that most clinicians never use deliberately but must be ready for. I've done simulated cricothyrotomies on mannequins dozens of times. Nothing prepares you for the reality of doing it on a real patient, but the muscle memory from repetition does help reduce the paralysis that comes with panic. If you were looking for information about a specific airway tool or procedure and used a term that didn't quite match, feel free to clarify and I can point you toward the right resources. The field is broad, and there's real depth in almost every direction you could go.