What the Numbers Actually Look Like on the Ground
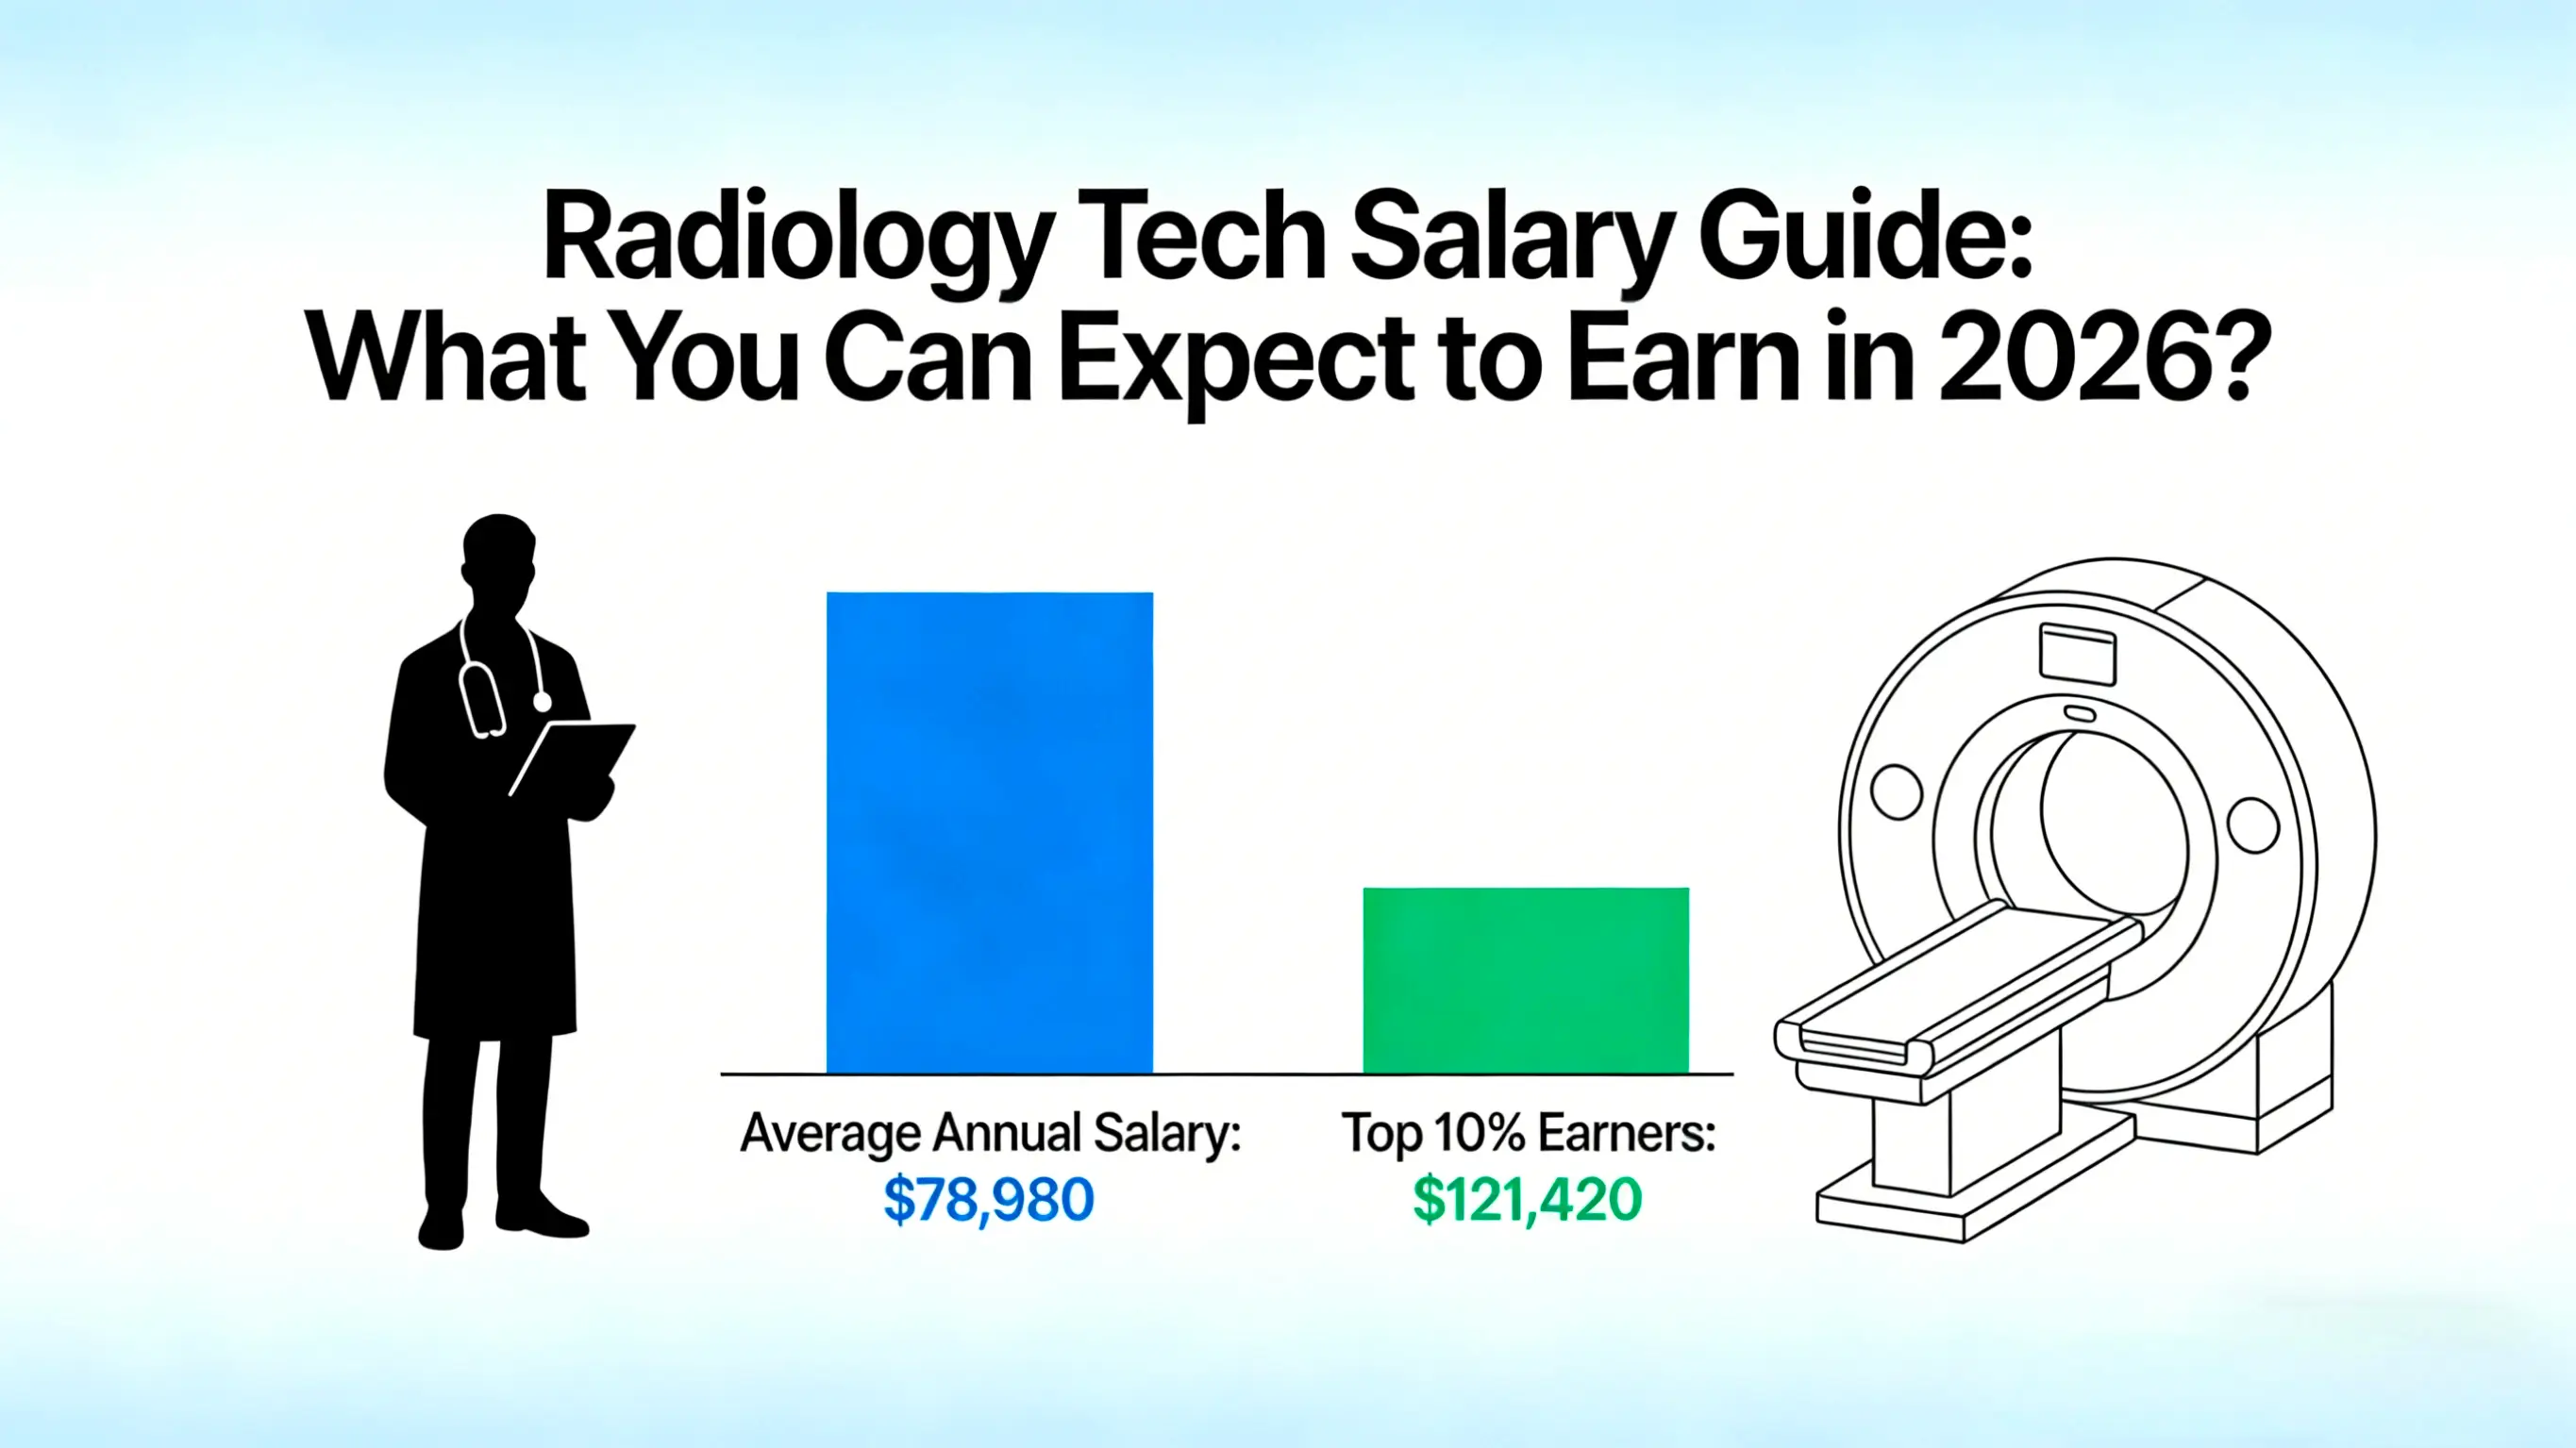
The average radiologic technologist in the United States makes somewhere between $65,000 and $85,000 a year depending on where you are and what shift you work. That range is real. Most job boards will show you a median around $76,000, but medians lie a little bit because they smooth over the people making $50,000 in rural Alabama and the people making $130,000 traveling in California. The truth sits somewhere messy in between. I have been in this field long enough to know that salary discussions rarely go the way people expect them to go. New grads walk in thinking they will make six figures within three years. They do not. What actually happens is that you start around $30 to $38 an hour, work shifts that ruin your sleep schedule, and slowly build up credentials that let you ask for more money.
Radiologic Tech Salary How Much You Can Really Earn In Medical Imaging
This heading keeps showing up in searches because people want a single number. There is not one. The number depends on geography, specialty, employment type, union status, and how many weekends you are willing to sacrifice. I will break it down the way I actually explain it to people who ask me for advice. Entry level radiologic technologists typically start in the $30 to $40 per hour range. That translates to roughly $62,000 to $83,000 annually before taxes if you work full time. Hospital positions tend to pay more than outpatient imaging centers, but hospital work is also harder on your body. You are lifting patients, standing for eight hours straight, and dealing with emergency trauma cases that keep you moving faster than you ever thought possible. Travel rad techs are a different category entirely. They can make $2,000 to $3,500 a week including housing stipends. I did a six month contract in Phoenix and took home about $95,000 that year. It was brutal. Ten hour shifts, every other weekend, back to back assignments. The money is real, but so is the exhaustion. Most people burn out within eighteen months unless they pace themselves.
Specialty certifications change the math. Mammography, CT, MRI, vascular intervention, radiation therapy — each one opens a different door. ARRT post-primary certifications add maybe $3 to $8 an hour to your base pay in most systems. It does not sound like much until you multiply it over a full year. That is an extra $6,000 to $16,000 depending on the market.
Get the Full Details
Where Geography Matters More Than You Think
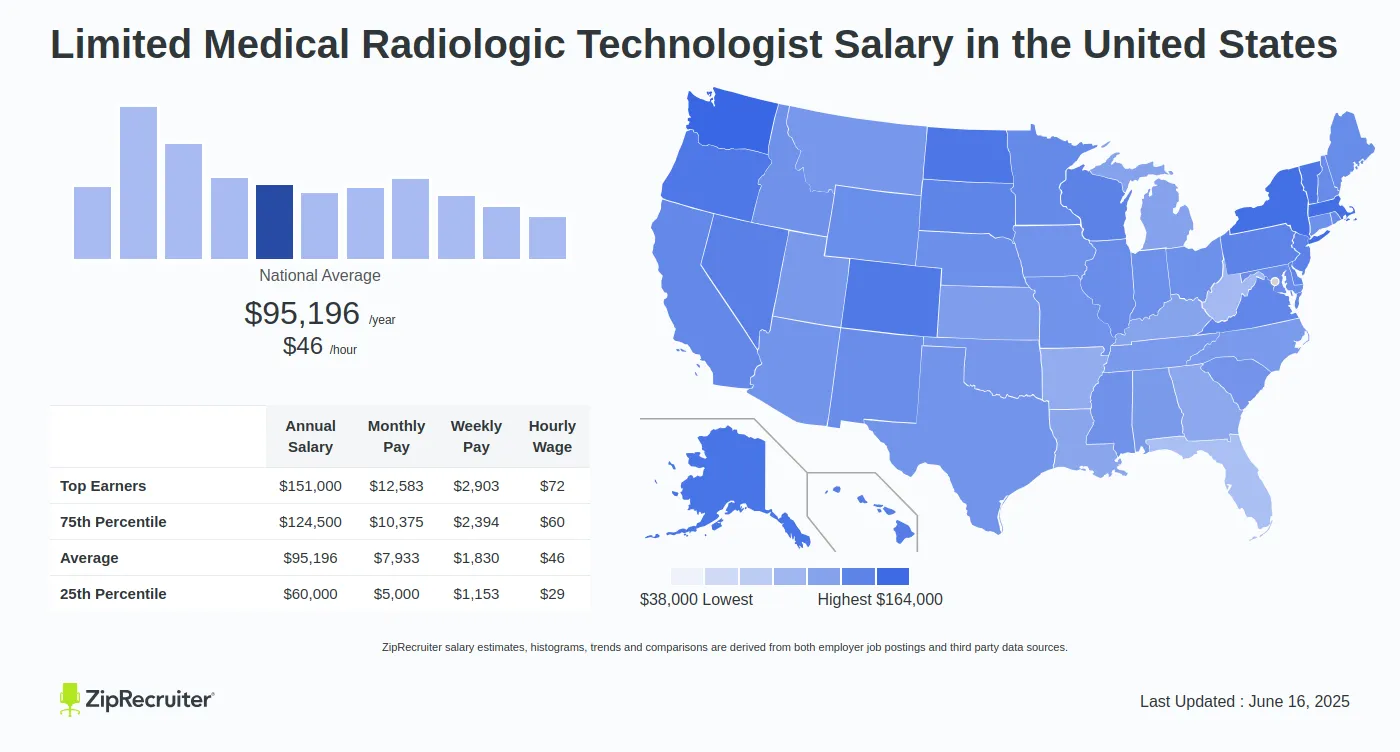
I learned this the hard way. Early in my career I took a job in a mid-sized city because it felt like a safe choice. Stable hospital, good benefits, reasonable cost of living. Two years later I realized I was making $15 an hour less than a tech in a nearby rural county that had a severe staffing shortage. Rural markets pay more sometimes. Always look at actual take home pay, not just the base rate. A $40 per hour job in San Francisco feels different than a $40 per hour job in Ohio. Cost of living adjustments matter enormously. The Bureau of Labor Statistics tracks occupational employment statistics by metropolitan statistical area. Look at those numbers before you accept an offer. Cities like San Jose, Santa Rosa, and Vallejo in California routinely push radiologic technologist salaries past $120,000. But you are also paying $3,000 a month for an apartment. Rural areas in the Midwest or South might only offer $55,000 to $65,000, but your rent is $800 and your grocery bill is twenty percent lower. Union hospitals are another factor. If you work in a union facility, your pay scale is usually published in a collective bargaining agreement. There is less negotiation but also less ambiguity. Non-union facilities give you room to negotiate, but they also give you room to get lowballed. I watched a colleague get offered $33 an hour at a non-union hospital in Texas. She countered at $38 and landed at $36. If you do not negotiate, you almost certainly leave money on the table.
The Credential Stack That Actually Moves the Needle
Most people know about the ARRT credential. That is the baseline. Everything after that is where the real earning potential lives. Here is what I have seen actually change paycheck size over a ten year span: CT certification adds approximately $2 to $5 per hour. In some systems it is bundled into a general radiography pay scale and does not change anything at all. You need to check the specific employer. MRI certification is worth more than CT in most markets. Expect $4 to $8 per hour more, sometimes more in competitive cities. The supply of MRI certified techs is lower than CT certified techs, which creates a wage premium.
Mammography is its own weird animal. It pays decently, often $3 to $6 per hour more than general rad, but the work is slower and more repetitive. Some people love it. Some people hate it. The pay bump is real but modest. Vascular Interventional Radiography is where the money gets interesting. This is not entry level work. You need multiple certifications and usually several years of experience. But angiography and IR techs in major medical centers can make $100,000 to $140,000 regularly. I know people making $160,000 in academic hospitals with night differential and call pay stacked on top. It is not easy. The cases run long, the radiation exposure is higher, and the on call expectations are real. Radiation Therapy is technically a separate credential but many rad techs cross over. It pays well, usually $75,000 to $110,000 depending on the region. The schedule is more regular than diagnostic imaging, which is a benefit. You get weekends off more often. Fewer nights. Fewer holidays.

Shift Differentials and How They Add Up
Night shift usually adds $2 to $4 per hour. Evening shift might add $1 to $2. Weekend differential varies wildly by employer. Some places pay 10 percent on weekends. Others pay flat $3 per hour. A few pay nothing extra and just mandate weekend rotation as part of the base job. I once calculated my actual hourly rate across three different contracts and the difference between day shift and night shift was sometimes only $1.50 an hour after benefits were factored in. Other contracts gave me $5 an hour premium for nights. Always read the fine print on the offer letter. The base rate is never the whole story. Call pay is another hidden income source. Some hospitals pay a flat monthly stipend just for being on call, even if you never get called in. Others pay per activation. I had a position where the on call stipend was $400 a month and activations paid $150 each. I averaged two activations per month, so that was an extra $700 a month or about $8,400 a year. Not life changing but it added up.
The Travel Contract Reality Check
Travel contracts sound glamorous. They are not. The pay is higher because the turnover is high and the burnout is real. You are constantly relocating, constantly adapting to new PACS systems and new protocols, constantly without a familiar support network. Most travel contracts are thirteen weeks. Some go to twenty six. Some convert to permanent positions if the hospital likes you, but that conversion is not guaranteed and not always desirable. I spent fourteen months traveling. I made good money. I also missed three holidays, slept in different beds every two weeks, and could not maintain any kind of routine. My tax situation was a nightmare because I was earning income in three different states. If you go the travel route, hire a CPA who understands multistate nursing and allied health income. Do not try to figure it out yourself. The travel market also fluctuates. During COVID, travel rad tech wages were insane. By 2024 they had come down significantly but remained above local hiring rates. Right now in 2026 the market is stabilizing. It is still profitable but not the golden era it was a few years ago.
Advanced Practice and Leadership Roles
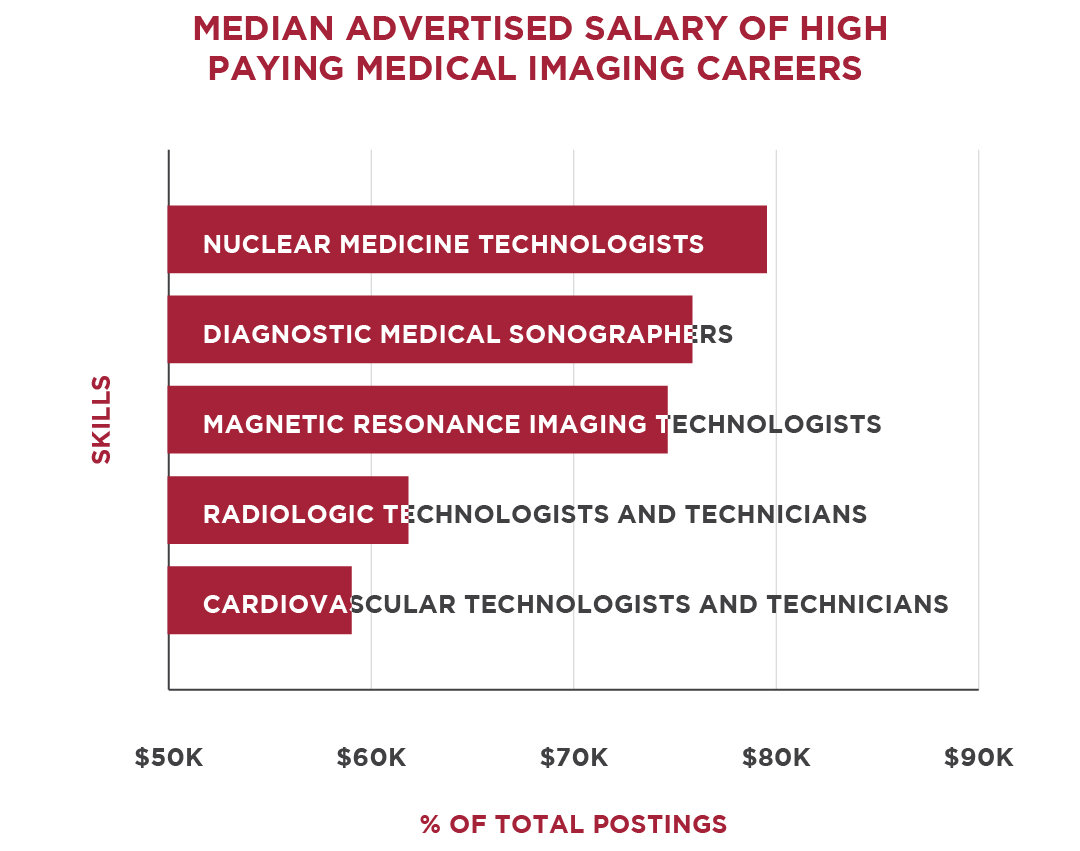
If you want to push past the $100,000 mark without becoming a travel nomad, look at advanced roles. Some hospitals hire rad techs as imaging coordinators, protocol specialists, or vendor liaison managers. These positions usually require four or more years of experience and sometimes a bachelor's degree. Pay ranges from $85,000 to $120,000 with better hours and less physical strain. Progression into radiation safety officer is another path. It usually requires additional certification through the NCRP or a state radiation control program. The work is mostly administrative and compliance based. Pay is moderate but the lifestyle is much more sustainable. Sonography is a separate career track that some rad techs transition into. It requires additional education, usually a formal ultrasound program or an associate degree. But sonographers generally make more than general rad techs. The crossover is possible if you are willing to invest the time.
A Specific Problem I Faced With Salary Negotiation
Early in my second year I interviewed with a regional hospital system for a senior rad tech position. They offered me $35 an hour based on my years of experience. I knew I had CT certification and mammography and five years in the field. The market rate in our area was closer to $40 an hour for someone with my credentials. I asked for $40. They countered at $37.50. I pushed back and mentioned that another hospital had offered me $39 with sign on bonus. They came back at $38.50 with a guarantee that I would be reconsidered for a raise at six months instead of the standard twelve. I took it. The raise came at five months because my performance reviews were strong. I ended up making $40.25 an hour by month eight. The lesson was simple. Know your market rate before you walk into the room. Have a backup offer if possible. And do not be afraid to negotiate more than once. Most hiring managers expect negotiation. What they do not expect is a candidate who walks in blind. Research the salary data. Check the BLS occupational employment stats for your metro area. Look at Glassdoor and Indeed salary reports. Use whatever data you can find. Then make your case.
The Limitations and Honest Downsides
Here is what nobody tells you about the earning potential in medical imaging. Physical wear and tear is real. I have techs in their mid thirties with chronic knee pain, shoulder impingement, and back issues from years of positioning patients. You cannot just push through it forever. Some people switch to ultrasound or Radiation Therapy to escape the physical demands. Others leave the profession entirely. Burnout is another limitation. The salary is decent but the emotional toll of working in busy emergency departments or trauma centers is underestimated. You see terrible things every day. People in pain. People dying. Families screaming. After five or six years some people just need out. That affects your career trajectory and your earning potential if you end up working part time or switching to a quieter department. The job market is not uniformly strong everywhere. Some rural areas have serious shortages and pay well to attract people. Some suburban areas have enough techs that wages stay flat. Some urban markets are oversaturated with new grads every year. The local market conditions matter more than the national averages you read online.
If you want maximum earning potential, the most reliable path is a combination of specialty certifications plus travel contracts plus geographic flexibility. That path is also the most stressful and least stable. There is no perfect option. There is only the option that fits your priorities.


