When Hiccups Won't Quit
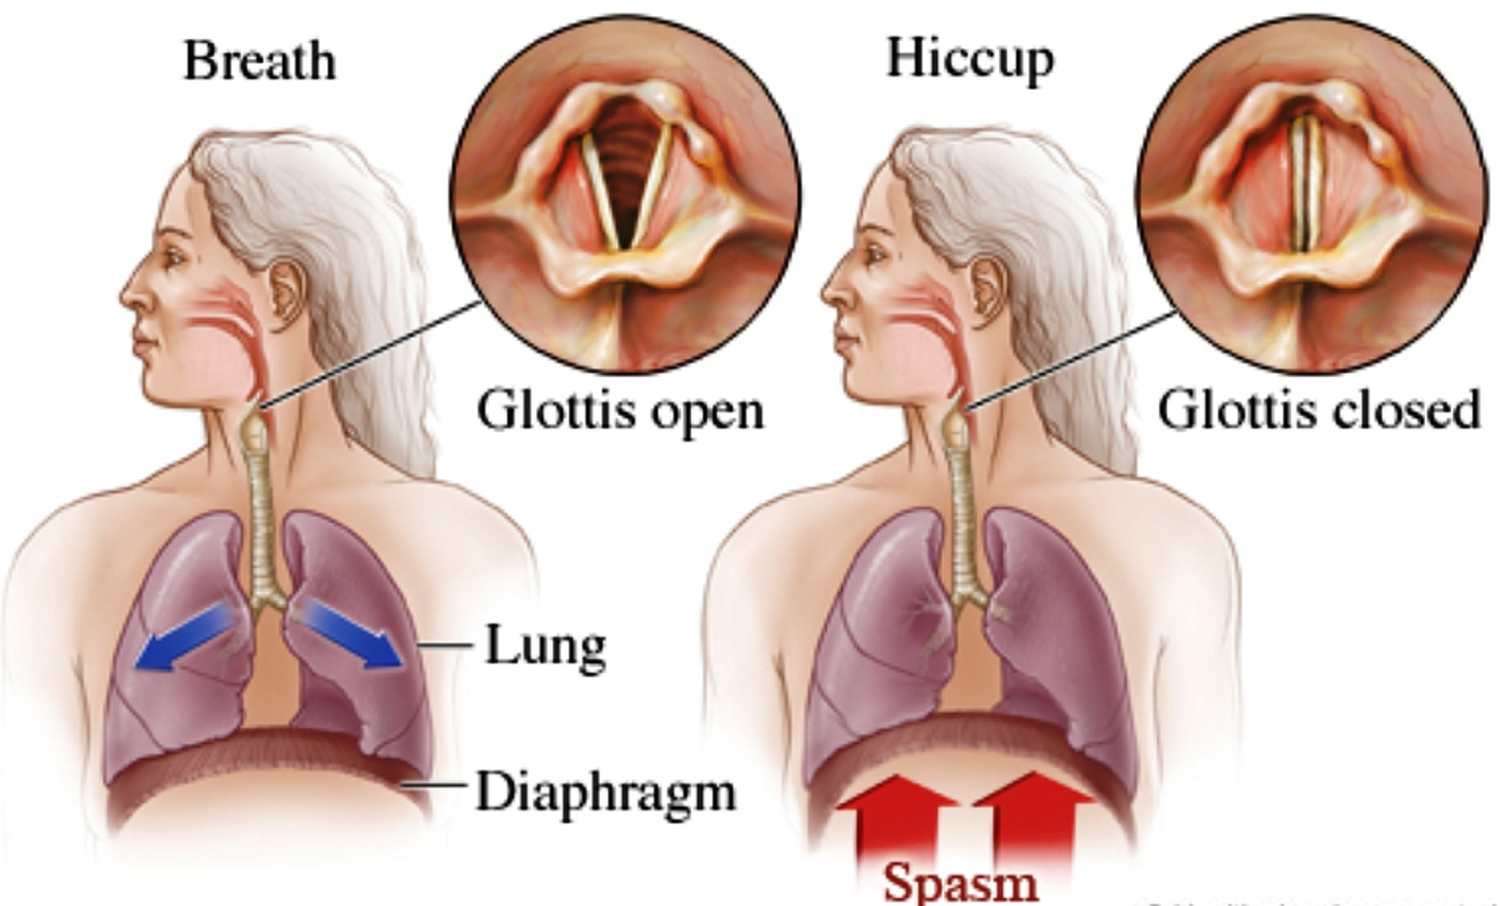
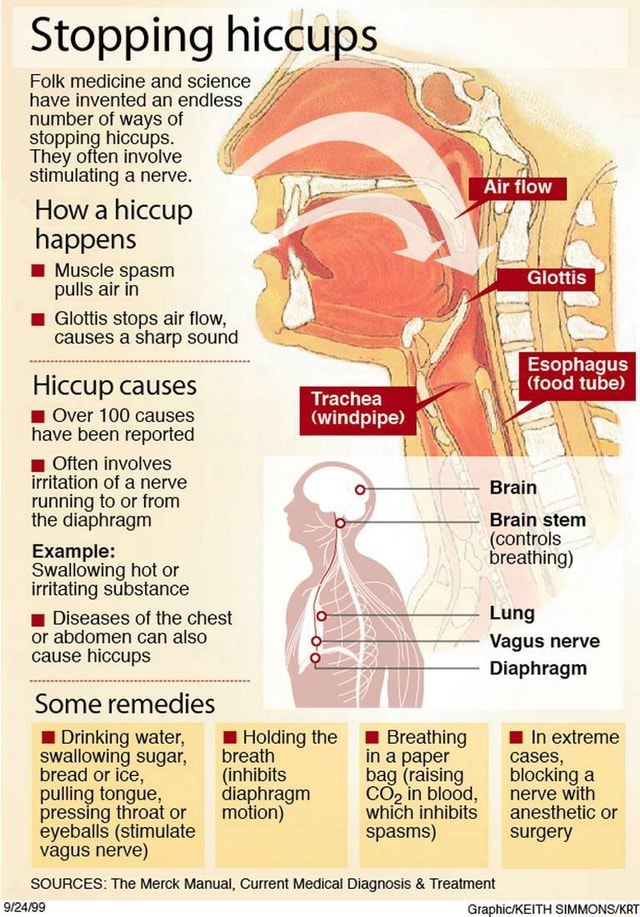
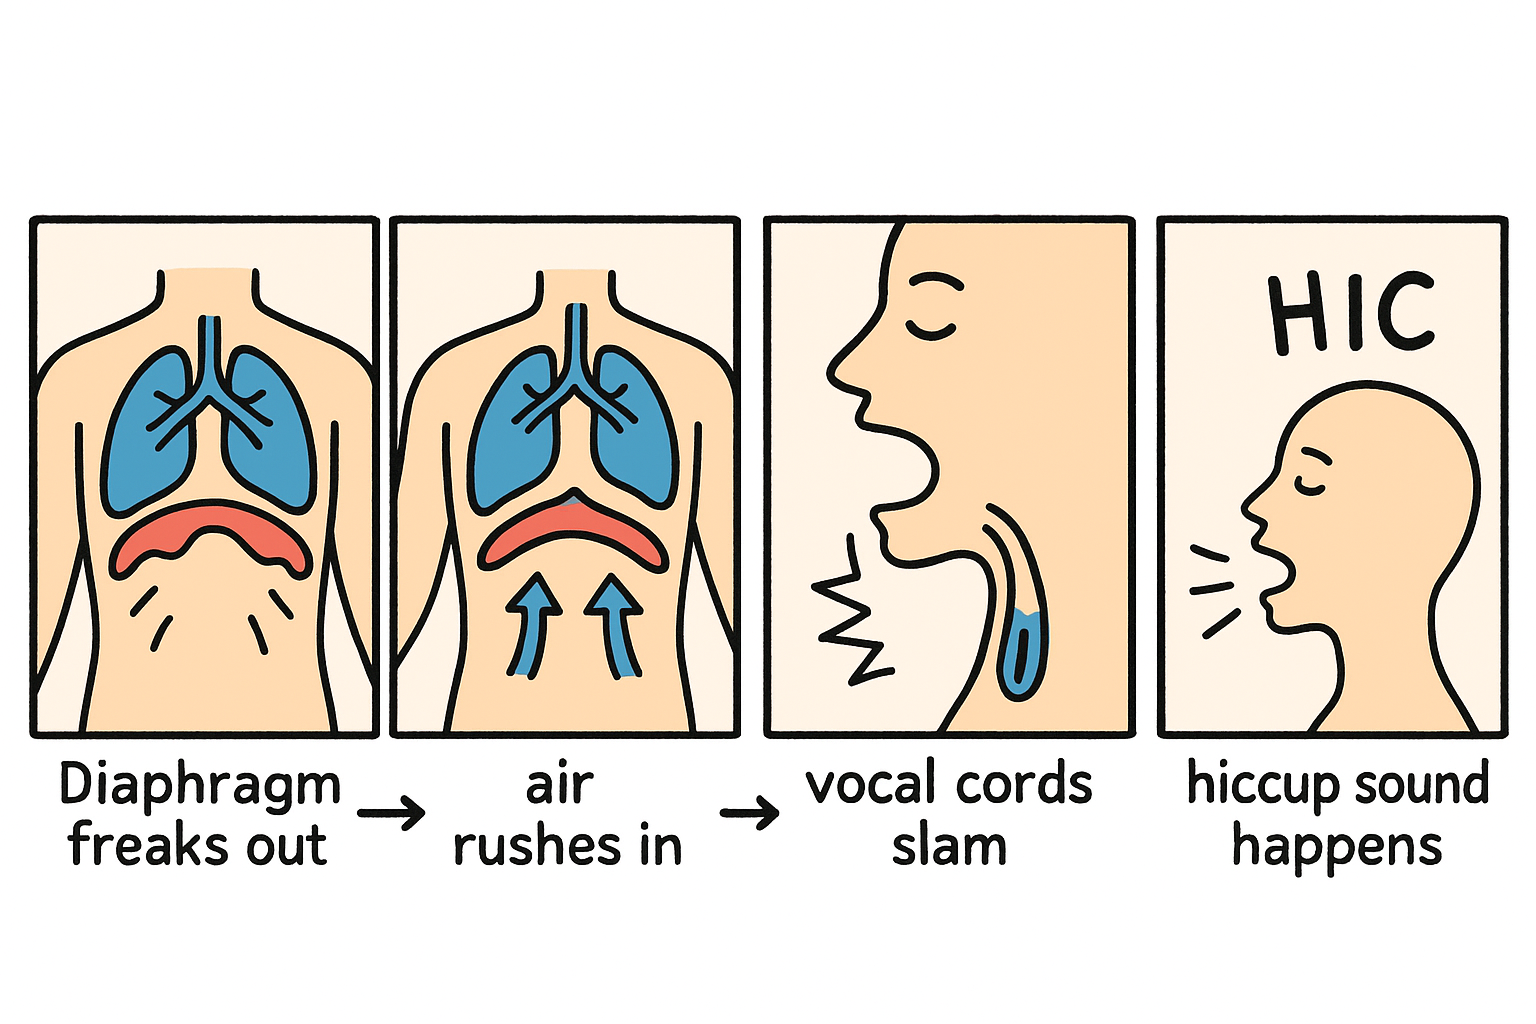
Hiccups are usually fine. They start, they annoy you, they go away within minutes. But when they cross into territory lasting more than 48 hours, something is different. That's what doctors call persistent hiccups. Beyond a month, they become intractable. The difference matters because the approach changes completely. The hiccup reflex arc involves four main players: the vagus nerve, the phrenic nerve, the sympathetic chain in your chest, and a coordination center in your brainstem. A hiccup happens when all of them misfire together. The diaphragm spasms, the glottis snaps shut, and you get that sound. Easy enough for an occasional episode. The problem with persistent cases is that the reflex loop has essentially become self-sustaining. It stops being a momentary glitch and starts behaving like a seizure in miniature. The brainstem circuit gets locked into a pattern, and nothing you do at home is going to break it. This is not guesswork. I've seen people try breathing into paper bags, holding their breath until they passed out, drinking water upside down, and getting hit in the back. None of it matters once you're past the 48-hour mark. The mechanism has shifted.
Here's what most people miss: the cause isn't always in the diaphragm or the stomach. I dealt with a case last year involving a patient whose hiccups lasted three weeks straight. Everything we checked was normal. Gastroenterology was clean. Chest imaging showed nothing. We were running out of options when someone noticed that the hiccups had started right after he began a new blood pressure medication. It wasn't a common side effect listed in the package insert. It came up in about one percent of cases, buried in an appendix. We stopped the med. The hiccups ended in roughly 36 hours. This kind of thing is the reason persistent hiccups warrant a real workup. Not because they're dangerous on their own, but because they're a signal. The list of possible underlying causes includes gastroesophageal reflux disease, which is by far the most common culprit, pneumonia or pleurisy irritating the phrenic nerve, medications like benzodiazepines and corticosteroids, alcohol abuse leading to gastritis, metabolic issues such as diabetes or kidney failure, and central nervous system conditions including tumors, strokes, or multiple sclerosis affecting the brainstem pathway. In practice, the diagnostic path usually goes like this. Your primary doctor will order basic bloodwork, check for electrolyte imbalances, and run a chest X-ray. If those are clear, gastroenterology gets involved for an endoscopy to look for silent reflux or hiatal hernia. If nothing shows up there, neurology becomes the next stop. Brain MRI. It's a long road, but it's the one that actually works for finding the source.
When it comes to treatment, the over-the-counter remedies stop working around the 12-hour mark. By then you need actual pharmacology. The first line is usually chlorpromazine, which is the only FDA-approved medication specifically for hiccups. It's an antipsychotic, so the side effect profile is not pleasant. Drowsiness, low blood pressure, restlessness. Metoclopramide is another option that works on the gastrointestinal side and tends to be better tolerated. Gabapentin has shown promise in recent case studies, particularly for hiccups with a neurological component, at doses starting around 300mg daily. Baclofen is used off-label with similar results. In refractory cases, surgeons will sometimes stimulate the phrenic nerve or perform a diaphragm block. I want to be blunt about the limitations here. There is no guaranteed fix. Some persistent hiccup cases just don't respond to anything and resolve on their own after weeks or months. The medications all carry significant side effects. Chlorpromazine can cause tardive dyskinesia with prolonged use. Metoclopramide carries a black box warning for neurological effects. Gabapentin causes cognitive fog that makes driving dangerous for some people. You're weighing relief against real risks. One more thing that isn't widely known. Acupuncture has shown unexpected effectiveness in certain persistent cases. A 2022 systematic review found that needle stimulation at specific points, particularly ST36 and CV17, could interrupt the reflex arc in patients who hadn't responded to medication. It's not a first-line treatment anywhere, and the evidence quality is modest, but it's worth discussing with a specialist if drugs aren't working for you. I saw one patient where this was the only thing that broke a six-week cycle.
Get the Full Details
The takeaway is straightforward. If your hiccups haven't stopped after two days, stop trying home remedies and see a doctor. Get the workup. The underlying cause is usually findable, and treating the cause works far better than treating the symptom. Ignoring persistent hiccups isn't dangerous in most cases, but it is inefficient. You're spending weeks miserable when the solution might be as simple as adjusting a medication or managing acid reflux you didn't know you had.