A Practical Guide To Left-Sided Abdominal And Thoracic Anatomy
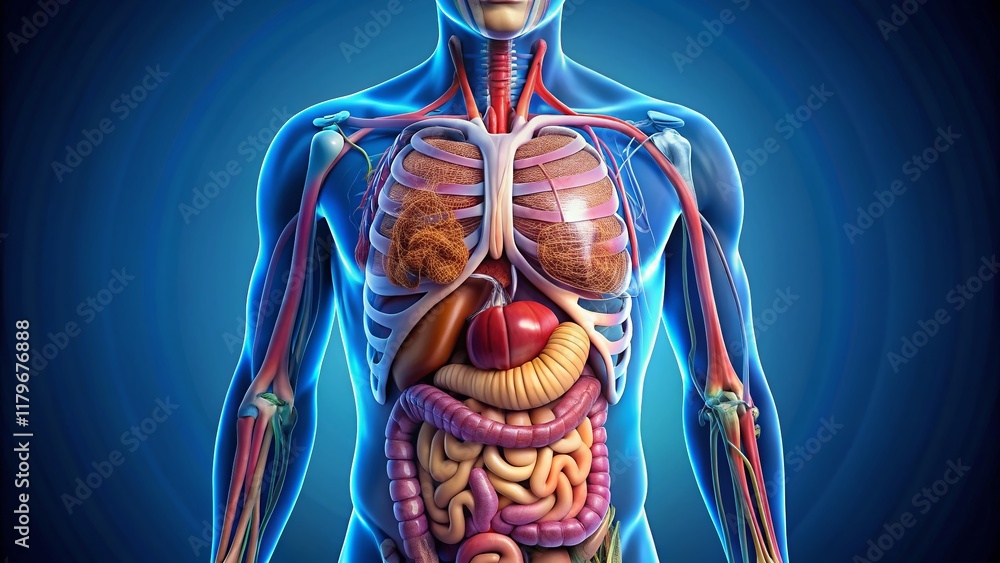
You open a textbook and see a neat diagram of organs arranged symmetrically. Real patients don't look like that. When you're trying to figure out what's causing pain, swelling, or tenderness on one side of the body, knowing which structures are actually there matters more than memorizing a list. I'm going to walk through the relevant anatomy, how it presents in practice, and where people regularly get tripped up. The left side of the body contains several organs, and their positions matter when you're trying to localize a problem. The heart sits predominantly on the left, though it's really a midline structure that extends further into the left hemithorax. About two-thirds of the heart's mass is to the left of the midline, which is why cardiac pain and referred symptoms often project to the left chest, left arm, and jaw. The apex points downward and to the left, resting against the fifth intercostal space at the midclavicular line. That's a key landmark. If you're palpating for the apical impulse and you find it at the sixth space or laterally, something's shifted — either the heart is enlarged, or an adjacent structure is pushing it. The spleen sits high in the left upper quadrant, protected by the rib cage from ribs nine through eleven. It's a vascular organ, which means it bleeds heavily when injured. A blunt trauma to the left lower chest can rupture the spleen without any obvious external signs. The organ itself is about the size of a fist in a healthy adult, roughly 12 centimeters in length. You typically can't palpate it unless it's enlarged, and when it is enlarged, the edge moves inferiorly and medially with respiration because it's tethered to the diaphragm through the gastrosplenic ligament.
The stomach occupies most of the left upper quadrant. Its fundus sits under the diaphragm, and the body extends toward the midline. The greater curvature faces left and downward, while the lesser curvature faces right and upward. This orientation matters for surgical approaches and for understanding how gas or fluid collects in different positions. A distended stomach from outlet obstruction will push against the left hemidiaphragm and can cause referred shoulder pain through the phrenic nerve. Below the stomach, the tail of the pancreas extends all the way to the splenic hilum. The body and head sit more toward the midline, but the tail is purely left-sided and sits in close proximity to the spleen, left kidney, and splenic flexure of the colon. Pancreatic pathology in the tail can mimic splenic or renal pain because the retroperitoneal location doesn't give you clean localization. Pain from the pancreatic tail tends to drill through to the back at around the T6 to T8 level. The left kidney sits retroperitoneally at roughly the T12 to L3 vertebral level. It's positioned slightly higher than the right kidney because the liver displaces the right side downward. The left kidney is about 11 to 14 centimeters long and weighs roughly 150 grams. Behind it run the twelfth rib and several nerves — the subcostal nerve, iliohypogastric nerve, and ilioinguinal nerve. Kidney stones passing through the left ureter produce pain that tracks from the flank around to the groin, and the exact path of that pain corresponds to the nerve roots being irritated as the stone descends. Stones in the upper ureter refer pain to the flank. Stones in the middle ureter refer pain to the lower abdomen. Distal ureteral stones refer pain to the genitalia and inner thigh.
The splenic flexure of the colon, where the transverse colon turns into the descending colon, sits just beneath the spleen. This is a common site for diverticula and a frequent location for fecal impaction because the colon changes direction here and the lumen narrows slightly. Constipation-related pain in the left upper quadrant is often traced back to this junction rather than to the spleen or stomach.
Get the Full Details

How Left-Sided Symptoms Actually Present
Clinical presentation on the left side doesn't follow a clean pattern. Left lower quadrant pain gets labeled as diverticulitis until proven otherwise, but ovarian pathology, ureteral stones, and even cardiac events can present there. I've seen myocardial infarctions dismissed as gas pain because the patient reported left lower abdominal discomfort without any chest symptoms. The diaphragm can refer pain to the shoulder, and the lower diaphragm specifically refers to the left shoulder through the phrenic nerve — so a splenic rupture or subphrenic abscess might present as isolated shoulder pain with no abdominal findings at all. Left upper quadrant tenderness is often assumed to be splenic, but the stomach, splenic flexure, left kidney, pancreatic tail, and even the lower left lung and pleura all occupy that space. A basilar pneumonia on the left can irritate the diaphragm and cause perceived upper abdominal pain. I had a patient who came in for "stomach pain" after a bad meal. Every sign pointed to gastritis. The stomach exam was unremarkable. A chest X-ray showed a left lower lobe consolidation. The pain was from the pneumonia irritating the diaphragm, not from anything in the abdomen. Two weeks of antibiotics resolved it completely. Flank pain on the left is overwhelmingly renal in origin, but Musculoskeletal causes are frequently overlooked. A strained quadratus lumborum or a thoracic radiculopathy at T12 can produce identical pain to a renal colic. The key differentiator is often movement — renal colic doesn't change with position or palpation of the paraspinal muscles, while muscular pain worsens with specific movements or direct pressure. But even that rule has exceptions. A large renal hematoma can irritate the adjacent musculature and produce tenderness on palpation that mimics a muscular origin.
Common Pitfalls In Left-Sided Assessment
The biggest mistake people make is assuming left-sided chest pain is cardiac without considering other structures. Costochondritis, intercostal neuralgia, and esophageal spasm all present with left-sided chest pain that can be indistinguishable from angina without proper workup. A reproducible tenderness on palpation of the costochondral junctions makes cardiac causes far less likely, but it doesn't rule them out entirely. I've had patients with confirmed left ventricular ischemia who also had simultaneous costochondritis, and the muscular tenderness made them falsely reassured that their chest pain wasn't cardiac. Another frequent error is underestimating how much the stomach can enlarge. A massively distended stomach from gastric outlet obstruction can extend well below the left costal margin and into the left lower quadrant, mimicking a pelvic mass or ovarian cyst. On physical exam, you might hear a succussion splash and feel a large, rounded mass in the lower abdomen. Without a history of early satiety, vomiting, or weight loss, it's easy to chase the wrong diagnosis. An upright abdominal X-ray or a quick bedside ultrasound resolves this instantly. Splenic enlargement is another area where assumptions lead to errors. The standard teaching says you palpate for the spleen from the right side, moving toward the left costal margin. But in massive splenomegaly, the spleen can fill the entire left hemi-abdomen and cross the midline into the right side. I once examined a patient with a spleen that extended from the left costal margin all the way to the right iliac crest. The organ was so large that the classic percussion and palpation techniques described in textbooks simply didn't apply. The diagnosis — hairy cell leukemia — was confirmed after a CBC showed pancytopenia with characteristic circulating cells. The spleen measured over 25 centimeters on imaging.
Atypical Presentations That Catch People Off Guard
Left supraventricular tachycardia can present as isolated epigastric discomfort without palpitations or dizziness. The vagus nerve mediates both cardiac and GI sensation, and tachyarrhythmias can trigger visceral referral patterns that mimic peptic ulcer disease. An ECG in the emergency department caught this in a patient who'd been treated for gastritis for three weeks without improvement. The epigastric pain resolved within minutes of electrical cardioversion. A left renal cell carcinoma can present with left testicular pain in men because the left gonadal vein drains directly into the left renal vein, unlike the right side which drains into the inferior vena cava. A tumor in the left kidney can compress or invade the renal vein, increasing pressure in the gonadal venous system and producing varicocele-like pain. This is why any left-sided testicular pain in an older man warrants renal imaging, not just a scrotal ultrasound. Hernias on the left side behave differently than on the right due to anatomical differences. The left inguinal canal is longer and passes more posteriorly, which changes the risk profile for indirect hernias. Left-sided Spigelian hernias are rare but tend to present with vague left lower quadrant pain that gets worse with standing and Valsalva maneuvers. They're easily missed on physical exam because the defect is below the arcuate line and the hernia sac pushes through the transversalis fascia without creating a visible bulge. CT imaging is usually required for diagnosis.

Practical Approach To Left-Sided Findings
When evaluating left-sided symptoms, start with the most dangerous possibilities first. Cardiac causes should be ruled out with an ECG and troponin before pursuing gastrointestinal or urological workups, especially in patients over 40 with any cardiovascular risk factors. A normal ECG and negative troponins significantly lower the probability of acute coronary syndrome, but they don't eliminate it entirely in high-risk presentations. For left upper quadrant pain, the sequence usually goes: cardiac evaluation if indicated, then abdominal ultrasound to assess the spleen and left kidney, followed by CT if the ultrasound is inconclusive. Endoscopy is reserved for cases where gastric or esophageal pathology is suspected based on history — dysphagia, odynophagia, melena, or unexplained weight loss. I've seen too many patients sent for expensive CT scans when a simple upper endoscopy would have identified a bleeding gastric ulcer or a malignancy at an earlier stage. Left lower quadrant pain follows a different algorithm. Non-contrast CT of the abdomen and pelvis is the gold standard for suspected diverticulitis or nephrolithiasis. Ultrasound is useful in younger patients and pregnant women to avoid radiation exposure, but it's operator-dependent and less sensitive for detecting small stones or early diverticulitis. In women of reproductive age, pelvic ultrasound and pregnancy testing should precede any CT scan regardless of how confident you are about the diagnosis.
Flank pain with hematuria is renal colic until proven otherwise. A non-contrast CT kidney-ureter-bladder protocol will identify stones in over 95 percent of cases and can also detect masses, hydronephrosis, and other structural abnormalities in a single study. Urine analysis showing red blood cells confirms the source but doesn't tell you where the stone is located. The CT scan does that, and the location determines whether you're dealing with a passable stone or one that needs urological intervention.
Limitations And Where This Breaks Down
Anatomical variation is more common than most clinicians admit. A retroaortic left renal vein occurs in about 2 to 3 percent of the population and can be mistaken for a lymph node or mass on imaging. An inverted spleen, where the organ rotates around its vascular pedicle, can present with acute abdominal pain and mimic a volvulus or torsion. These variants are usually discovered incidentally during imaging for unrelated complaints, but they matter when you're interpreting scans. Physical examination has limited sensitivity for many left-sided pathologies. You cannot reliably palpate the left kidney in most adults. The pancreas is generally impalpable except when significantly enlarged or inflamed. Splenic enlargement must reach approximately 3 centimeters below the costal margin before it's detectable by palpation, and even then, obesity and abdominal wall tension can obscure the finding. Imaging is necessary for accurate assessment in most clinical scenarios. Pain referral patterns are unreliable for definitive localization. The dermatomal innervation of the left abdomen spans T7 to L1, and pain from visceral structures often refers to areas distant from the actual pathology. A left ureteral stone may cause pain in the flank, the lower abdomen, and the groin simultaneously, making it difficult to determine the exact level of obstruction from symptoms alone. Imaging remains the standard for localization.

Left-sided symptoms can also be referred from the right side and vice versa. A right-sided kidney stone can sometimes cause bilateral flank discomfort through shared neural pathways. Gastric pain from a posterior ulcer can refer to the back on either side depending on the extent of retroperitoneal irritation. This is why focused imaging and laboratory testing matter more than relying on symptom location alone.