Understanding the Ostium: A Basic Guide
An ostium is simply an opening. In anatomy, it refers to any natural orifice or entrance that connects two cavities or leads from one space to another. The word comes from Latin, meaning "mouth." You encounter these structures throughout the body, and they serve as critical pathways for fluids, air, or other biological material to move between regions. The term itself doesn't specify location. It just describes a function. Any tubular connection or gap leading somewhere qualifies. Surgeons and radiologists use the word constantly, which is why understanding the basics matters if you ever read a medical report or follow clinical discussions.
What Is The Ostium A Simple Explanation For Curious Minds
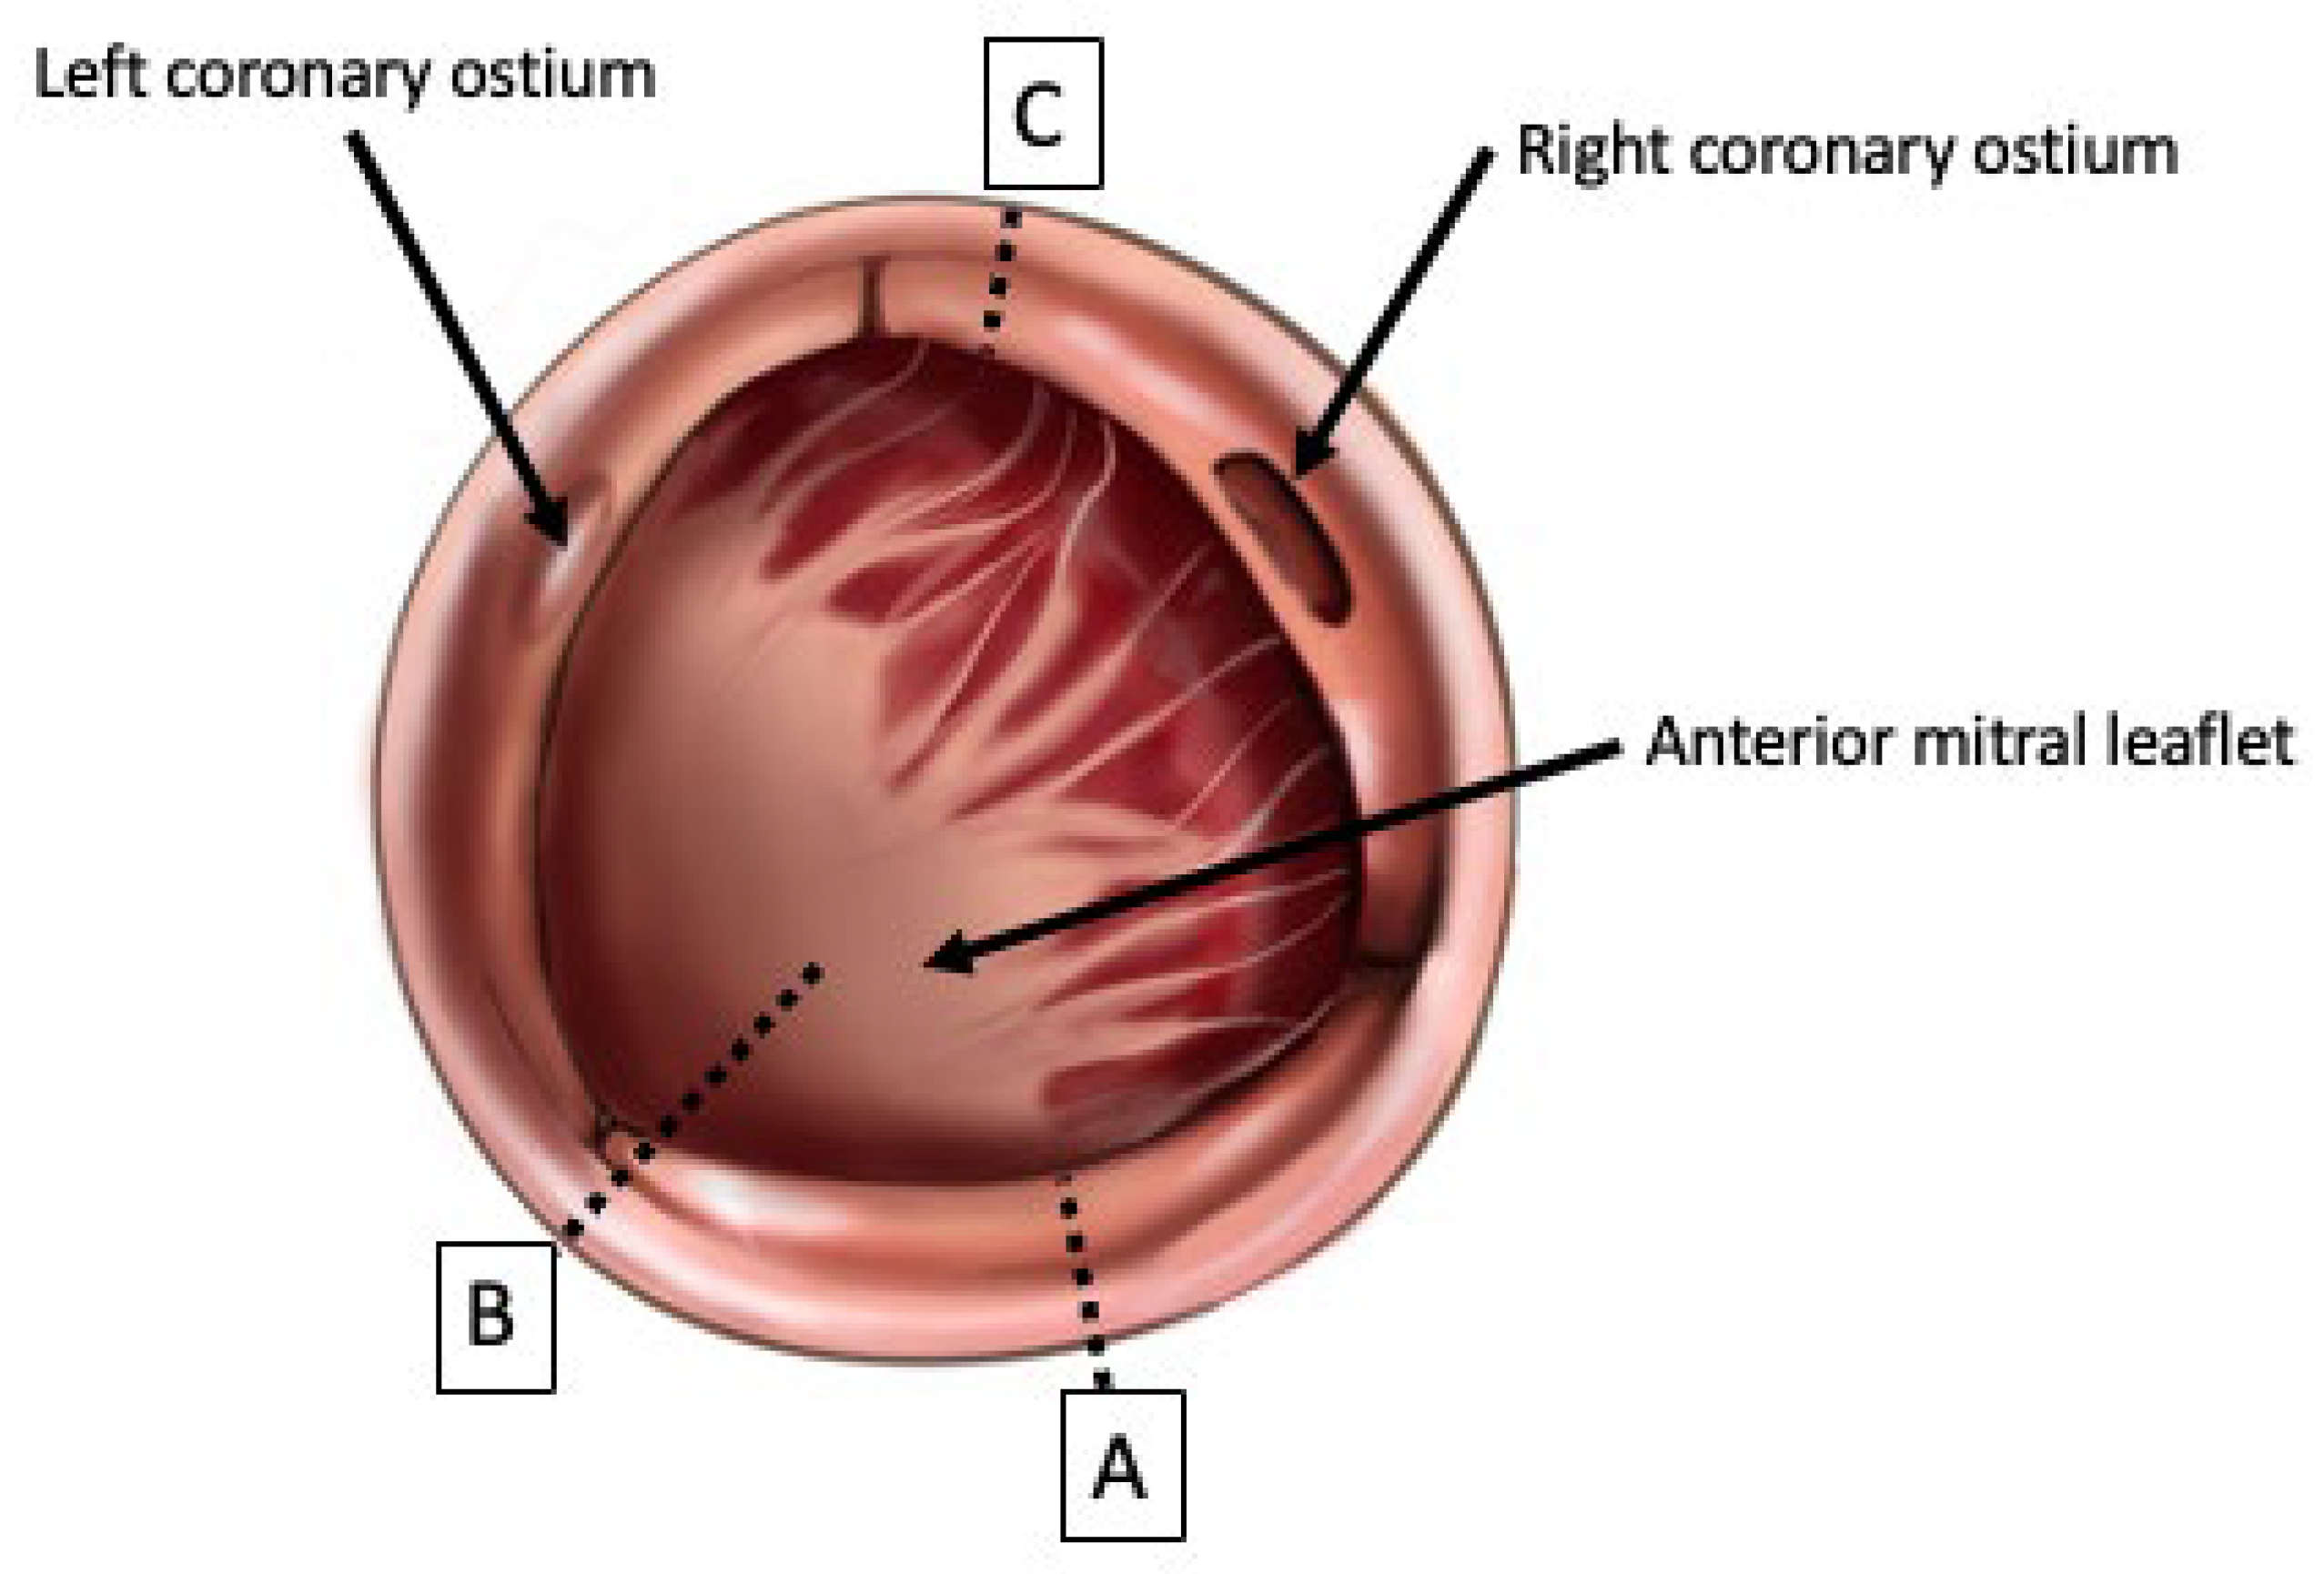
The most commonly referenced ostia appear in the cardiovascular and respiratory systems. In the heart, the coronary ostia are openings at the base of the aorta where the left and right coronary arteries emerge. These supply blood to the heart muscle itself. During a cardiac catheterization, the physician threads a catheter through these ostia to reach the coronary circulation. If the ostia are narrowed, diseased, or difficult to locate, the procedure becomes significantly harder. In the nasal cavity, the sinus ostia connect the paranasal sinuses to the nasal passages. The maxillary sinus ostium, the sphenoid sinus ostium, and the frontonasal duct are all clinically relevant. When these openings become blocked due to inflammation, infection, or structural abnormality, mucus cannot drain properly. That leads to sinus pressure, recurrent infections, and sometimes chronic rhinosinusitis. I've seen patients undergo months of medication before a simple CT scan revealed that their frontal sinus ostium was essentially sealed shut by a deviated septum and polyp tissue. They needed functional endoscopic sinus surgery, not another round of antibiotics. The uterine ostia are another example. The internal os marks the opening from the cervix into the uterine cavity, while the external os opens into the vagina. During pregnancy, the internal os remains closed until late stages or labor. Monitoring cervical os dilation is standard practice in obstetrics.
Ostia also appear in the renal system. The renal calyceal ostia connect the minor calyces to the major calyces, channeling urine from the collecting ducts toward the ureter. In the context of stone disease or upper tract urothelial carcinoma, these openings can become sites of obstruction or tumor growth.
Get the Full Details

Why Ostia Matter Clinically
The reason ostia get so much attention in medicine is that blockage or anatomical variation at any of these openings can have serious downstream consequences. A narrow coronary ostium can cause myocardial ischemia even if the rest of the coronary arteries look clean. A blocked sinus ostium creates a closed space where bacteria grow unchecked. A narrowed ureteropelvic junction ostium leads to hydronephrosis and potential kidney damage over time. I worked with a case where a patient kept presenting with unexplained chest pain. Cardiac enzymes were normal, stress tests were borderline, and everything pointed away from coronary artery disease. Eventually, a coronary angiogram revealed that the left main coronary ostium had a significant takeoff anomaly. The artery didn't originate where it should have. It passed between the aorta and the pulmonary artery, which compressed it during exertion. This isn't a textbook presentation. The patient had been misdiagnosed for two years before the anomaly was identified. Anatomical variations of ostial origin are well documented but not always anticipated on non-invasive imaging.
Common Pitfalls and Complications
One thing that catches people off guard is how variable ostial anatomy can be. Standard atlases show idealized versions, but real patients rarely conform perfectly. The coronary sinus ostium, for example, has a valve called the Thebesian valve in roughly 40 percent of people, and the size and shape of that valve varies enormously. When attempting venous pacing or certain structural heart interventions, operators can struggle to engage the coronary sinus because the ostial geometry doesn't match what they expected. Sinus ostia present different challenges. The osteomeatal complex is a crowded anatomical region, and the individual ostia within it can be pinpoint small. Radiologists sometimes miss subtle occlusions on MRI because the sequence parameters weren't optimized for small air-fluid levels. A dedicated high-resolution CT with thin cuts is far more reliable for evaluating sinus ostial patency. This is worth noting if you're comparing imaging modalities for chronic sinus disease workups. Another limitation worth mentioning is that identifying an ostium on imaging doesn't always tell you whether it's functional. A sinus ostium might appear open on a scan but still be obstructed by mucosal swelling or dysfunction. Anatomy and physiology don't always align. Clinical symptoms should drive decision-making more than imaging findings alone.
How Diagnosis Works in Practice
Detection depends on the ostium in question. Coronary ostia are visualized primarily through invasive angiography or coronary CT angiography. Functional significance is assessed with fractional flow reserve measurements during catheterization. Sinus ostia are evaluated with nasal endoscopy and sinus CT. Renal ostia fall under the domain of urography and retrograde pyelography when intervention is being considered. For the sinus ostia specifically, endoscopic visualization gives you direct information about mucosal condition, drainage patterns, and whether purulent material is actively expressing from an opening. Imaging complements this, but it doesn't replace direct inspection. I found this out early in my career when I relied too heavily on CT reports that described "patent" ostia. The scans were technically adequate, but the patient was still symptomatic. A quick endoscopic exam showed that two of those supposedly patent ostia were covered by thick fibrinous debris that the radiology protocol couldn't resolve. Debridement and steroid irrigation resolved the issue within a week. The takeaway is that ostia are small, critical junctions in the body's plumbing system. They deserve careful evaluation because problems at these points tend to cascade into larger issues. Understanding their anatomy, recognizing variation, and knowing the limitations of your diagnostic tools will serve you better than memorizing lists of every ostium in the human body.