What Radiography Actually Is
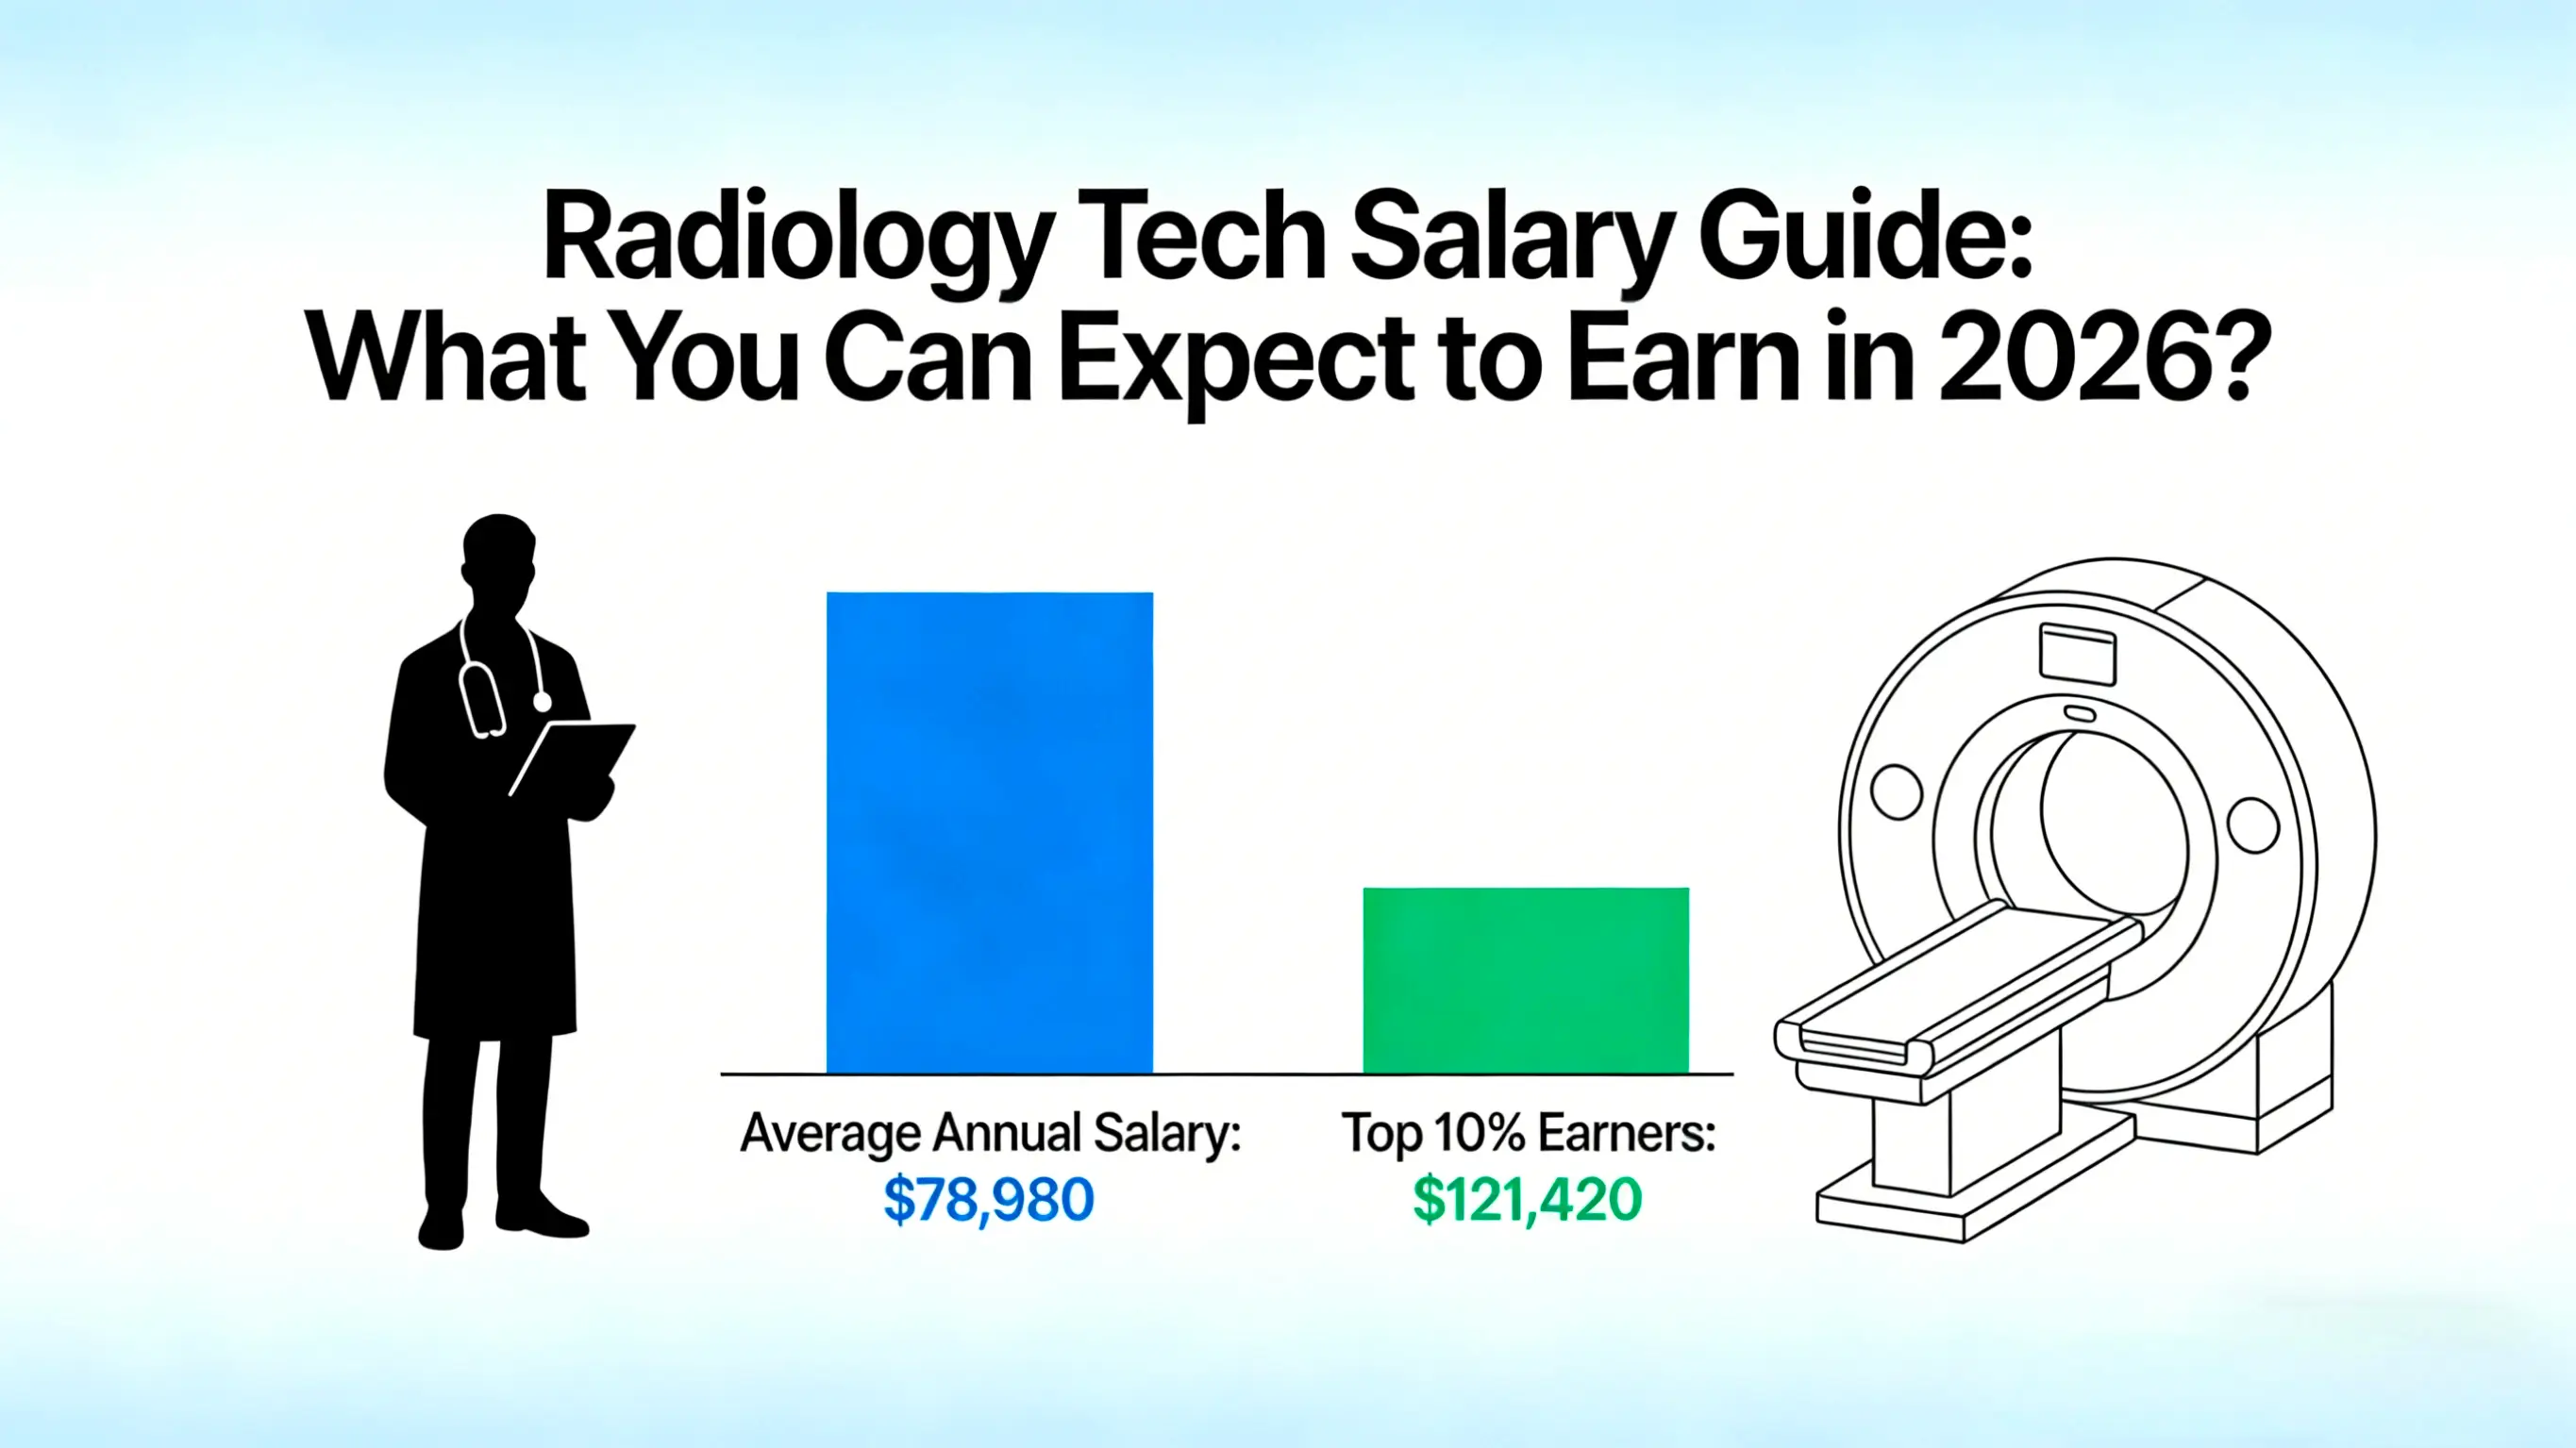
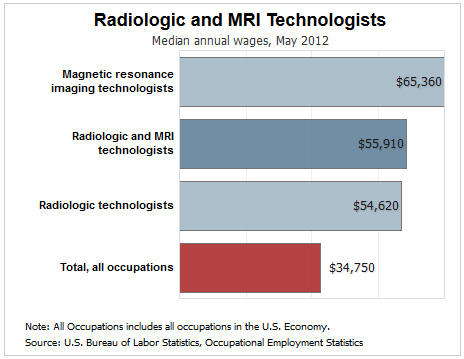
Radiography is the practice of creating images of the inside of the body using ionizing radiation, most commonly X-rays. A radiographer positions the patient, selects the technical parameters, triggers the exposure, and ensures the resulting image is diagnostically useful. That's the surface version. The reality involves a lot more nuance than textbook definitions usually capture. I've been doing this for long enough that I've seen the career trajectory change dramatically. When I started, radiographers were mostly X-ray techs in hospital basements. Now the field has branched into CT, MRI, fluoroscopy, mammos, interventional radiography, and nuclear medicine. The salary range reflects that fragmentation pretty heavily. Entry-level staff radiographers in the United States typically earn between 55,000 and 70,000 dollars annually. That's the starting number most programs advertise. It varies by region obviously. A position in rural Kansas pays differently than one in Manhattan. The Bureau of Labor Statistics puts the median around 68,000, but that's a national figure that smooths over a lot of real variation.
Specialization changes the math. CT technologists routinely make 75,000 to 95,000. MRI techs in that same range, sometimes higher depending on whether you're doing cardiac protocols or advanced neuro. Interventional radiography pushes into the 90,000 to 120,000 bracket, and that's before you factor in shift differentials for on-call work. Radiologists who have completed residency and fellowship can make well north of 400,000, but that's a completely different career path from radiography. The thing nobody tells you upfront is that the pay isn't just about your credential. It's about your schedule. Night shift differentials of 10 to 15 percent are standard at most hospitals. Weekend rotation can add another 5 to 10 percent. Travel radiography contracts regularly pay 1,800 to 2,800 dollars per week all-inclusive, which is why a lot of people burn out on the road and come back to permanent positions after a year or two.
The Actual Work
A typical day for a general radiographer involves maybe 30 to 50 projections across a mix of inpatients and outpatients. You're walking into rooms with trauma patients, post-op folks who can't reposition, elderly people with dementia who don't understand why you're asking them to hold still. You learn quickly that technique selection is only half the job. Patient communication and positioning under difficult circumstances is the other half. I remember one case that stuck with me. A trauma patient came in with a suspected pelvic fracture. Standard AP pelvis protocol wasn't going to work because the patient was on traction and couldn't be moved. The attending wanted a cross-table lateral, but the C-arm wasn't available in the trauma bay. So I ended up doing a supine AP pelvis with the cassette positioned transversely and a tight collimation to minimize scatter. The image wasn't textbook perfect, but it showed the fracture line clearly enough to get the patient to OR. That's the kind of improvisation that doesn't show up in study guides. Another practical reality: dose optimization is constantly negotiated between image quality and ALARA principles. Beginners often default to higher mAs because they're worried about repeating images. Repeating images actually delivers more dose than getting it right the first time with proper technique. Learn your exposure charts. Memorize the conversion factors for different body habits. It saves time and it keeps your repeat rate down, which matters for both patient safety and your department's quality metrics.
Get the Full Details

How to Enter the Field
The standard path is an accredited radiography program, usually two years for an associate degree, though bachelor's programs are becoming more common. Program accreditation through JRCERT is non-negotiable if you want to sit for the ARPCE exam. Graduating from a non-accredited program essentially closes most employment doors. After graduation, you pass the certification exam through the American Registry of Radiologic Technologists. Some states require additional licensing on top of that. The requirements vary, so check your state's health department website before you apply for jobs. I've seen people accepted to programs only to discover later that their state has extra requirements that their program didn't cover. There's a bottleneck that fewer people talk about. Many hospitals now require at least one to two years of experience before they'll hire for certain modalities. So you graduate, get your first job doing general X-ray, and then spend the next couple years trying to get cross-trained. It's not a dealbreaker, but it slows down your earning potential in the early years. Getting certifications in CT or MRI while you're working your general position is the most reliable way to accelerate.
Where the Career Goes Stale
I'll be straight about the downsides because nobody else will. Physical toll is real. You're lifting and positioning patients all day. Chronic lower back problems are among the most common complaints among radiographers after fifteen years. Anti-fatigue mats, lift assist devices, and learning proper body mechanics from day one matter more than you'd think. I've seen colleagues leave the profession entirely because of back issues that accumulated over decades of improper patient handling. Automation is eating into certain roles. Portable X-ray inICU settings now has plenty of AI-assisted positioning tools that reduce the technical skill required for basic exams. Some facilities are using autonomous portable imaging robots that don't need a technologist in the room at all. This isn't happening everywhere yet, but it's happening fast enough that you should watch the trend. The emotional load also gets underestimated. You're the person who delivers bad news sometimes, literally. A radiographer spots a pneumothorax on a chest film and pages the resident. Or you see a mass that turns out to be malignant. You don't get to process that the same way physicians do, and the cumulative effect of absorbing that information without the closure of treatment discussions is something you should consider before committing.
If you're looking at this career, the practical takeaway is straightforward. Get accredited, get certified, specialize early, protect your body, and don't assume the starting salary is your ceiling. The numbers work in your favor if you're willing to put in the additional training and accept the shift work that comes with it.