What Is Ihs Health Insurance Decoding The Indian Health Service For Employees And Providers
Samantha
2026-09-20
What IHS Actually Covers and How It Shows Up on Your Record
The Indian Health Service doesn't work like a typical health plan you'd find on the open market. It is a federal benefit program administered by the Department of Health and Human Services, and eligibility hinges on tribal enrollment status rather than employment or income alone. For employees of IHS or a federally recognized Tribe or Alaska Native Corporation running an IHS-funded program, benefits roll through a different administrative pipeline than standard employer-sponsored insurance. That distinction matters more than people realize.
What Is Ihs Health Insurance Decoding The Indian Health Service For Employees And Providers
Understanding the system starts with knowing what "IHS health insurance" actually refers to. Most people mean one of two things. First, they mean direct care coverage through IHS facilities and the contract health delivery system. Second, they mean the IHS-funded health insurance premium assistance program, sometimes called the Health Insurance Premium Payment (HIPP) program, which helps pay for marketplace or employer-based premiums when IHS determines it would be cheaper to cover the premium than to provide direct services. These are separate mechanisms. Don't conflate them.
For employees working within the IHS system, your benefits package is governed by federal employee regulations under 42 CFR Part 100 and related OPM guidelines. You get the standard federal benefits bundle — FERS for retirement, FEHB for health insurance, FLSA status determination — but there are unique layers on top. If you are clinically credentialed and providing care through an IHS facility, you operate under a compact arrangement where IHS pays for your direct services and then seeks reimbursement through secondary payers. That secondary billing is where most headaches originate.
Providers enrolled in the IHS network face a different reality. Contract health care relies on the Section 7(h) referral system, meaning IHS authorizes care outside its own facilities and the responsible entity becomes the payer of last resort. You bill IHS, not the patient's primary insurance first in most referral cases. The per diem rates, the inpatient payment methodology, the outpatient fee schedule — they are all distinct from Medicare and Medicaid fee schedules. I have seen providers lose thousands on improperly categorized referral claims because they submitted them using commercial insurance modifiers instead of the IHS-specific revenue codes that the contract health delivery system requires.
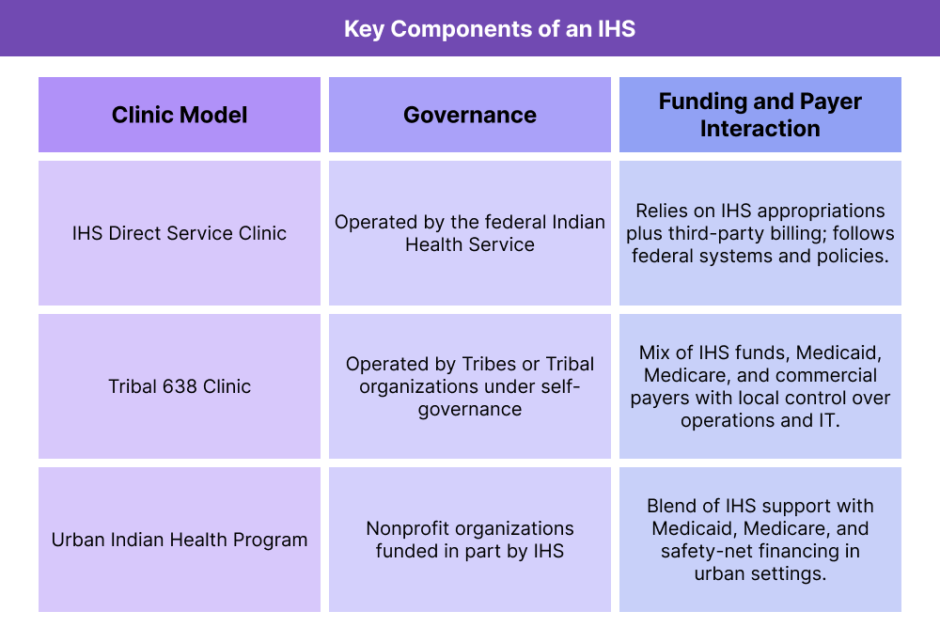
On the employee side, a practical detail that catches people off guard involves the distinction between IHS direct employees and those employed by tribal health programs under 638 contracts. Both serve the same population. Both provide clinical care. But the benefits administration, the HR channels, and sometimes the health insurance options diverge. If you are confused about which plan you are enrolled in, check your SF-50 or your tribal employment records before calling the benefits office. They will ask you to do exactly that anyway.
One edge case I ran into involved a provider who was cross-trained and worked both at an IHS hospital and a contracted community health center under a 638 agreement. Their referrals bounced between two billing systems with different authorization numbers. Claims sat in limbo for six to eight weeks because the referral number from the IHS facility didn't carry over cleanly into the tribal clinic's charge entry. The workaround was straightforward but not documented anywhere obvious. I had each site assign a single tracking number on the front end and match it to the IHS referral ID on the back end before the claim ever entered the billing cycle. That eliminated the mismatch entirely and cut average claim turnaround from about nine weeks to roughly three.
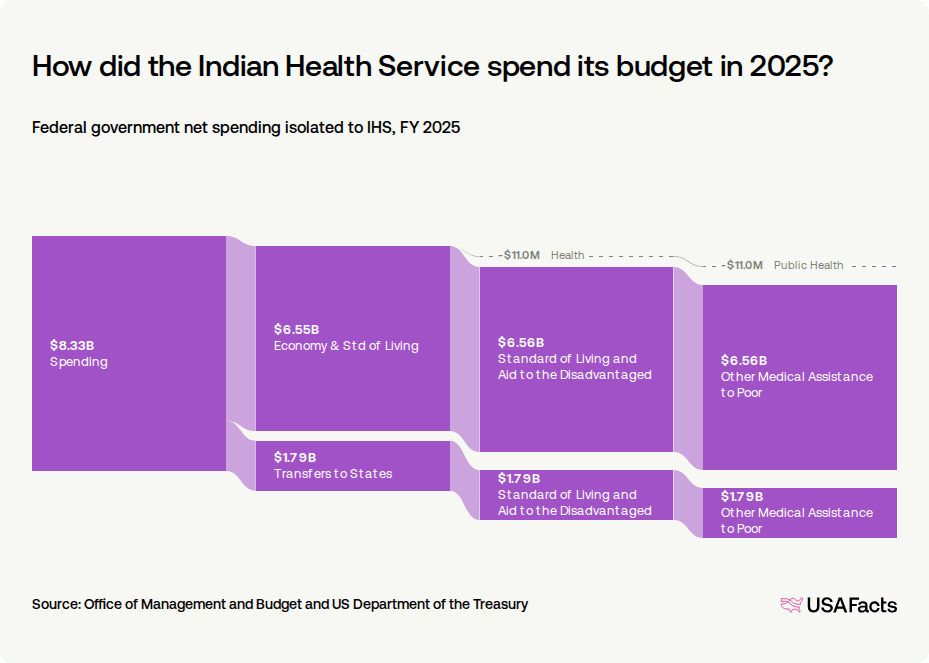
There are also some less obvious structural realities worth understanding. The IHS trust fund mechanism is not a capitation model. It is a reimbursement-based appropriation system, which means funding does not arrive as a fixed per-member-per-month amount flowing into a clinic's account. It arrives as congressionally appropriated funds distributed through a complex formula based on census data, acuity indices, and facility classifications. When appropriations get delayed — and they do, usually in Q2 or around continuing resolutions — facility budgets tighten immediately even though patient obligations do not pause. Providers feel this through scheduling delays, supply rationing, and occasional furlough days. Employees feel it through hiring freezes and delayed performance awards.
Another counter-intuitive point: being eligible for IHS services does not automatically qualify you for premium assistance. The HIPP program requires an independent determination that enrolling in another plan, such as through the marketplace or an employer, is cost-effective from the government's perspective. That determination uses actual premium data plus expected utilization costs. I have seen eligible patients denied HIPP because their expected direct care costs were calculated as lower than the annual premium, even though the patient's actual utilization would have been high. The model penalizes exactly the people who need coverage the most. Advocating for a manual review with updated clinical documentation can overturn that outcome, but it takes patience and paperwork.
For providers entering the IHS contracting world, credentialing runs through a separate process from typical payer enrollment. You will go through IHS medical review boards, site-specific privileging, and often dual credentialing if you hold privileges at both an IHS facility and a 638 clinic. Timeline ranges from sixty to one hundred twenty days depending on the region and whether your primary source verification clears on the first pass. Having your NPDB report, DEA registration, and malpractice history with tail coverage ready before you start speeds this up considerably.
The main limitations are blunt. IHS funding remains chronically under-allocationed relative to the statutory obligation. Facilities across the country operate at consistent staffing gaps. Patient wait times for specialty care through the contract system average between forty-five and ninety days in many regions. Telehealth expansion has improved access somewhat, but bandwidth constraints on reservations and rural sites remain a genuine bottleneck. If you are considering employment through IHS, understand that the mission-driven environment is real, but the resource constraints are equally real and affect daily workflows directly.
Bottom line for anyone navigating this system, whether you are an employee figuring out your benefits or a provider working out billing mechanics, is to stop treating IHS like a conventional health plan and start treating it like what it is: a parallel federal healthcare infrastructure with its own rules, its own billing codes, and its own administrative layers. The learning curve is steep, but the documentation exists. You just have to know where to look and which form numbers to cite when something does not match.
Gallery What Is Ihs Health Insurance Decoding The Indian Health Service For Employees And Providers
What does the Indian Health Service (IHS) do? | USAFacts
IHS Clinics Meaning: Indian Health Service and Tribal 638 Facilities ...
The Indian Health Service (IHS) by Mashaal Zahid on Prezi
Indian Health Service (IHS) Benefits | DenialCrusher
ihs.gov - Indian Health Service | Indian... - IHS