Calprotectin Testing in IBD: What Actually Works
Fecal calprotectin is a protein released by neutrophils when your gut is inflamed. It's become one of the standard non-invasive tools for monitoring inflammatory bowel disease, and most gastroenterologists use it regularly. The abbreviation you'll sometimes see as Cpn (calprotectin) on lab requisitions is what connects the test to routine clinical workflows. Calprotectin gets measured from a stool sample. You don't need an endoscopy to get the number. The test quantifies how much of this calcium-binding protein is present in grams per kilogram of stool, and the result gives you a rough read on whether neutrophilic inflammation is active in the intestines. That matters because flares in Crohn's disease and ulcerative colitis track closely with rising calprotectin levels, often weeks before symptoms become obvious to the patient. I've seen patients who felt fine but had calprotectin numbers in the 800 to 1,200 range. Those patients needed a change in therapy just as much as someone describing bloody diarrhea. That disconnect between how a patient feels and what the biomarker shows is exactly why the test has value in maintenance management.
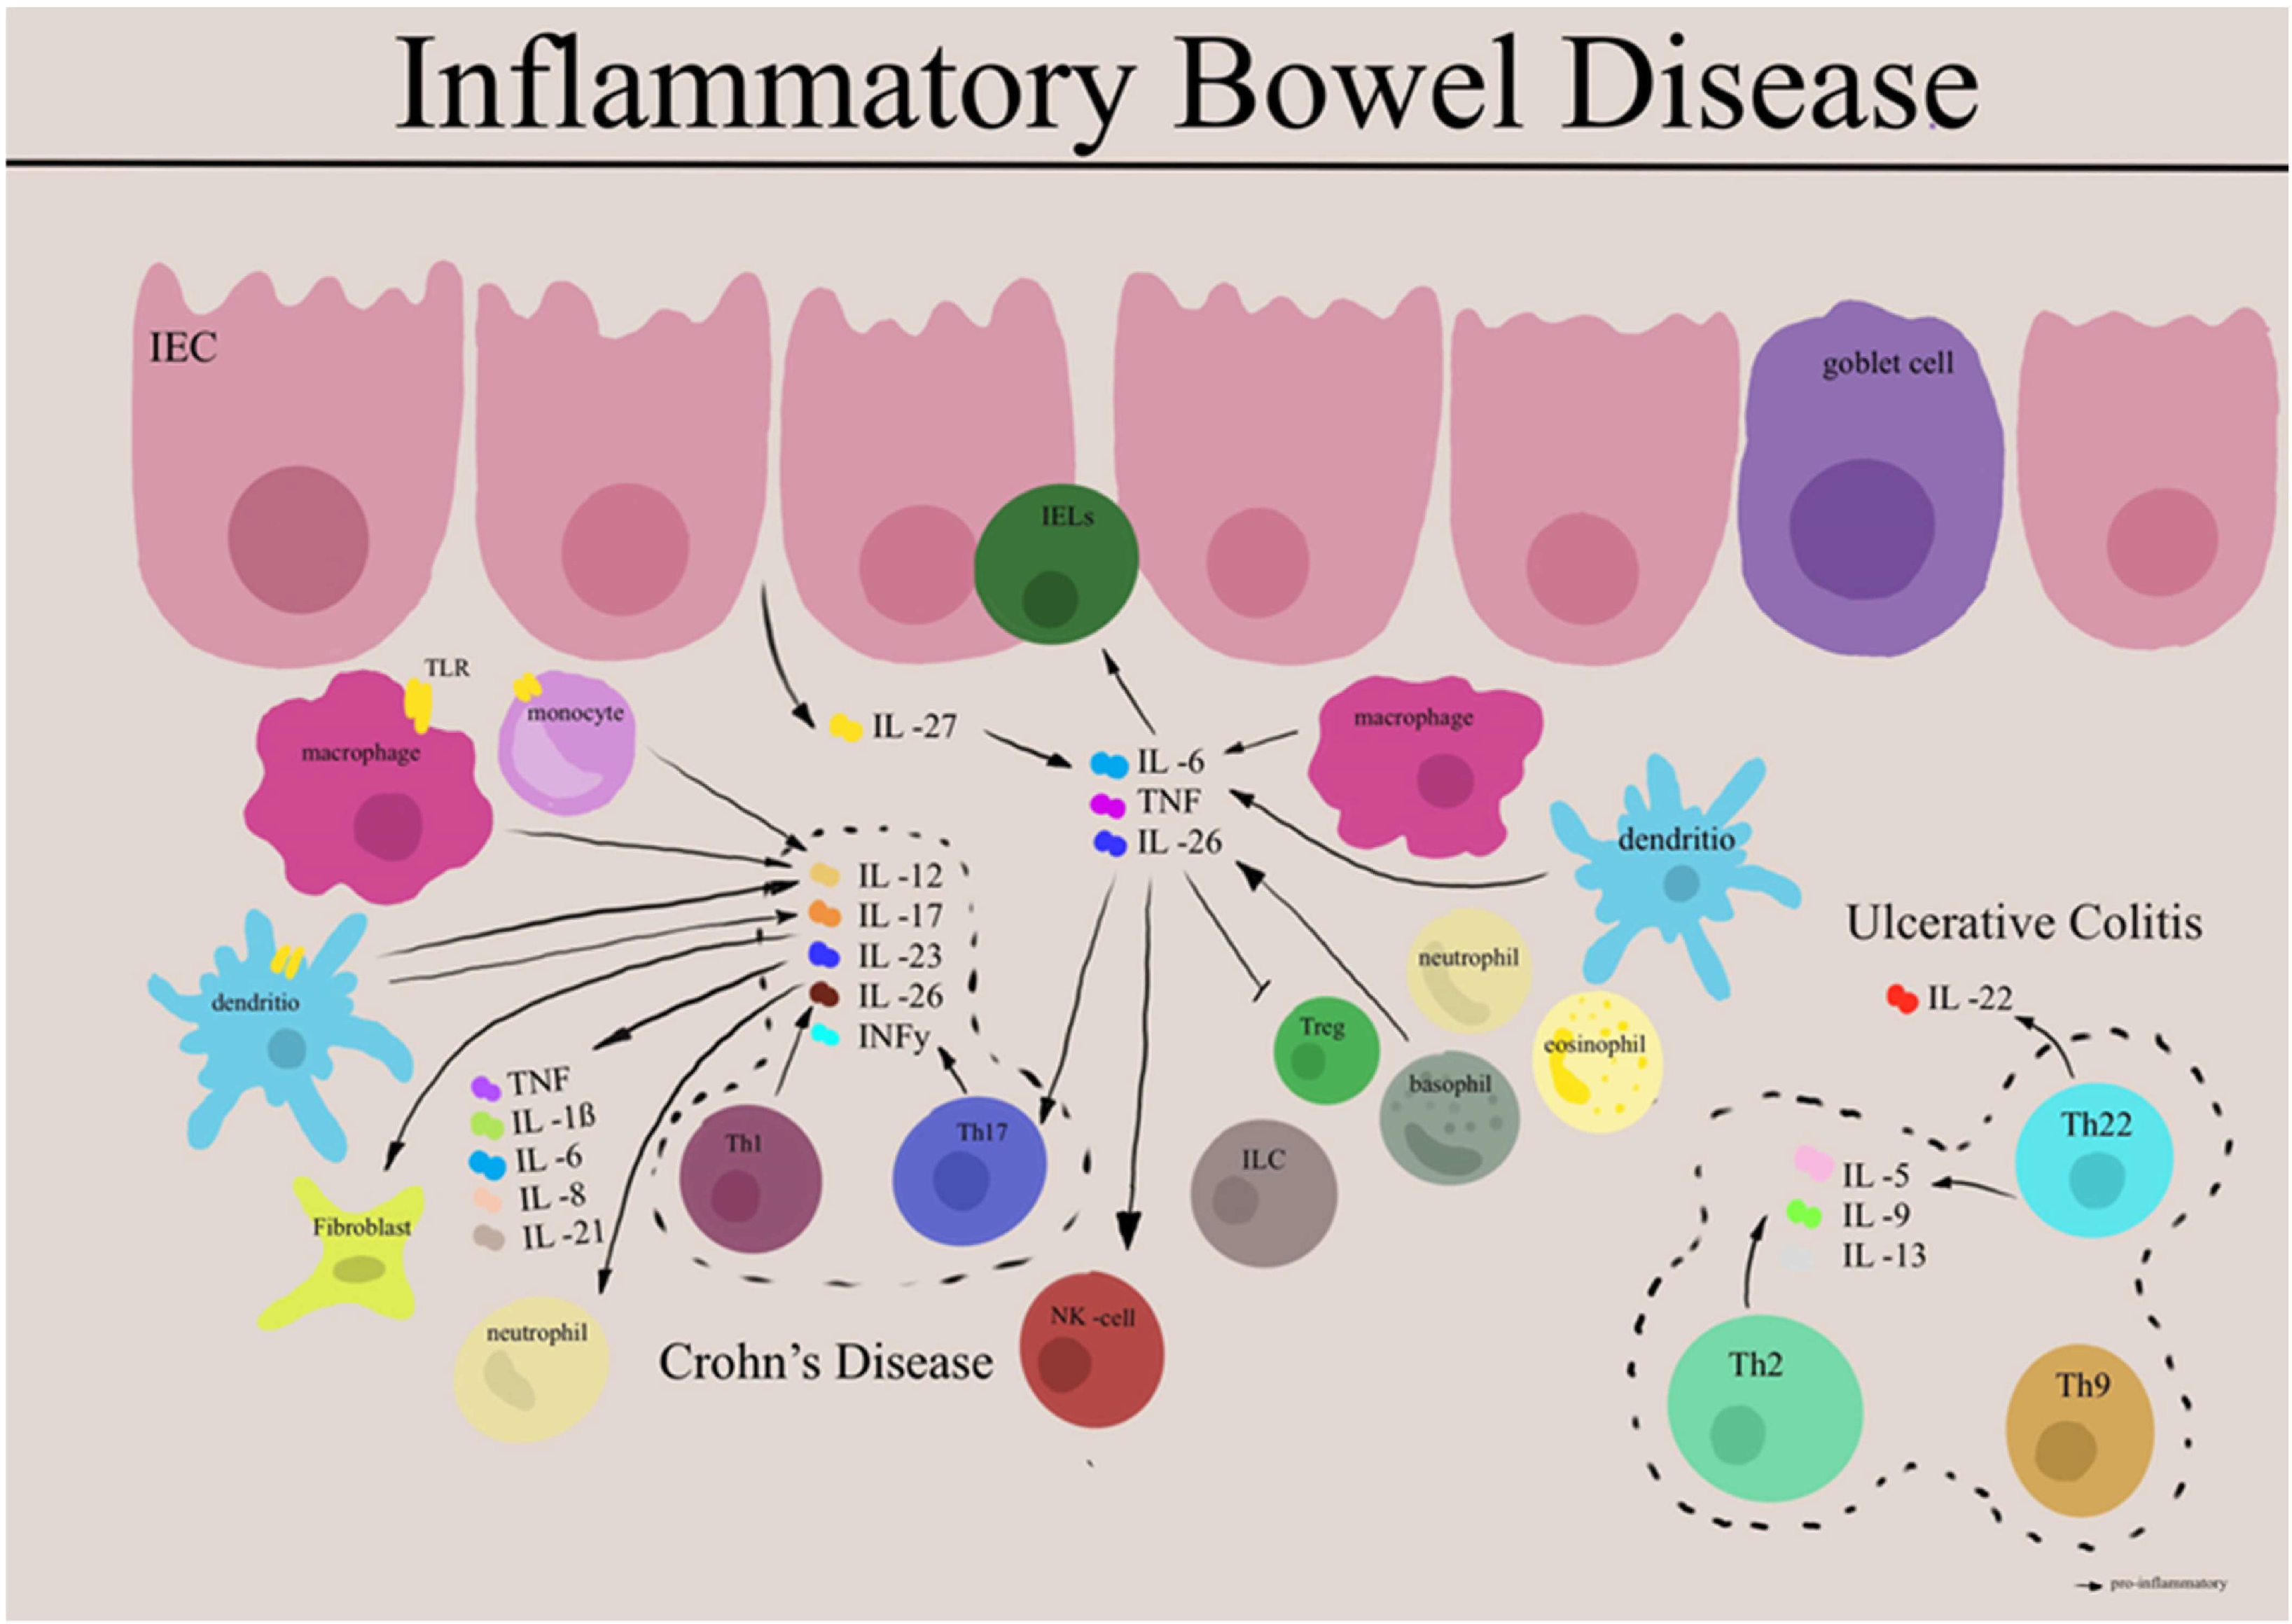
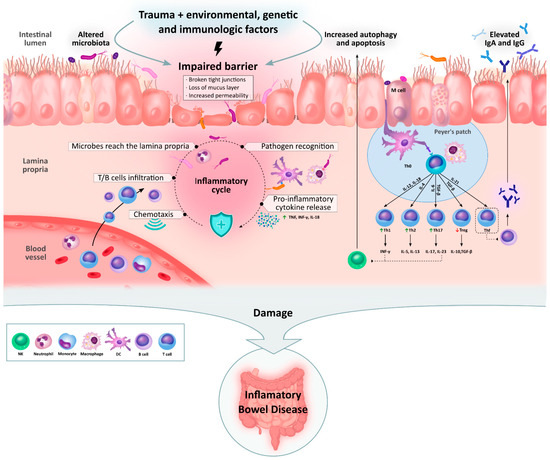
The mechanism is straightforward. When immune cells flood the intestinal lining during an IBD flare, they degranulate and release calprotectin into the gut lumen. The protein is stable in stool samples, which is why it survives the collection-to-lab pipeline better than many other markers. Commercial ELISA kits and point-of-care rapid tests both exist, and they generally correlate well with each other above the threshold levels that matter clinically.
How the Test Actually Works in Practice
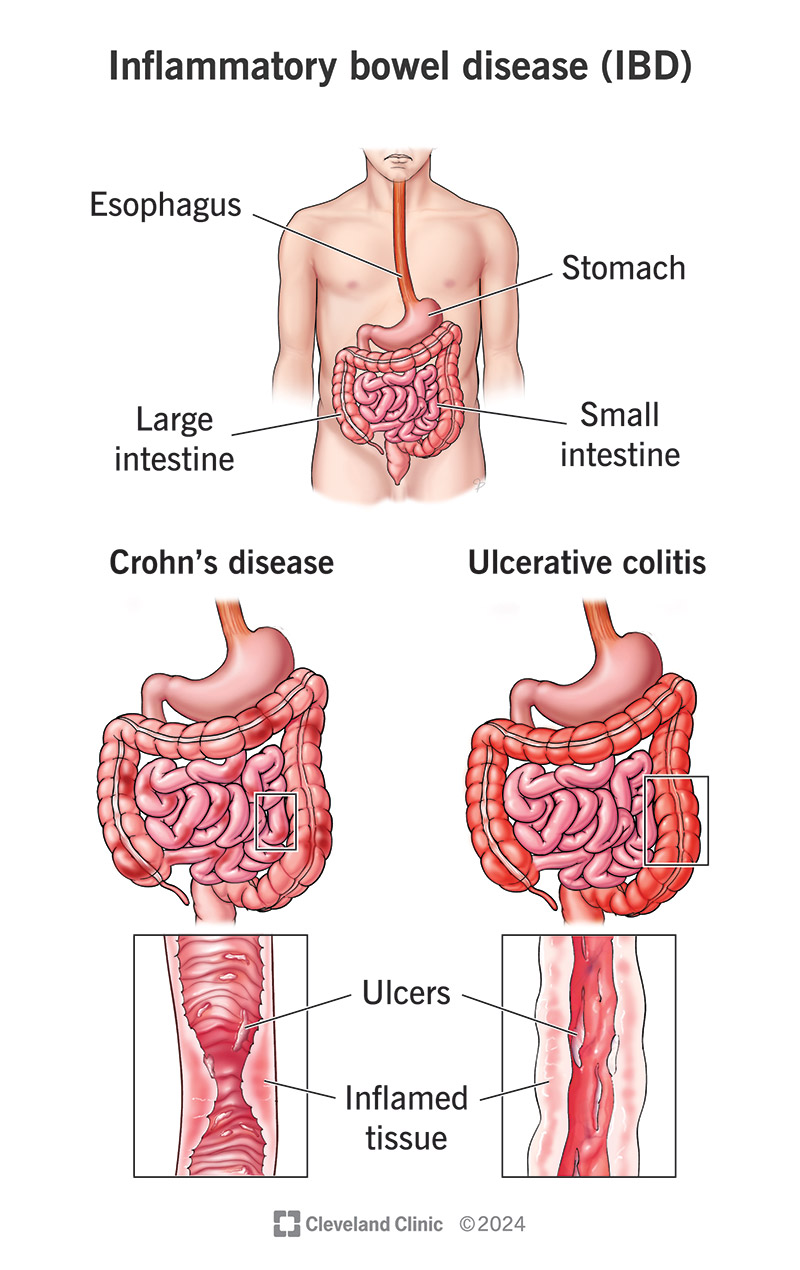
You collect a small stool sample using the provided container, mail or drop it off at the lab, and wait. Turnaround time varies by facility but typically lands between three and seven business days for a standard reference lab. Rapid point-of-care versions can give you a qualitative result in fifteen minutes, though they lack the precision of quantitative assays when you're tracking trends over time. The reference ranges most GI practices follow run roughly like this: under fifty micrograms per gram is considered normal. Between fifty and two hundred is the gray zone where you might repeat the test or correlate with clinical findings. Above two hundred strongly suggests active intestinal inflammation and usually triggers further workup or a treatment adjustment. One thing beginners miss is that calprotectin doesn't differentiate between Crohn's and ulcerative colitis. It tells you inflammation exists and roughly how active it is, but it won't point to the location or the disease subtype. You still need colonoscopy with biopsies for that. I learned that the hard way early on when a patient had elevated calprotectin but a clean scope — turned out the issue was isolated small bowel Crohn's that the standard colonoscopy couldn't reach. That patient needed MR enterography instead.
Get the Full Details
Pitfalls and When the Test Misleads You
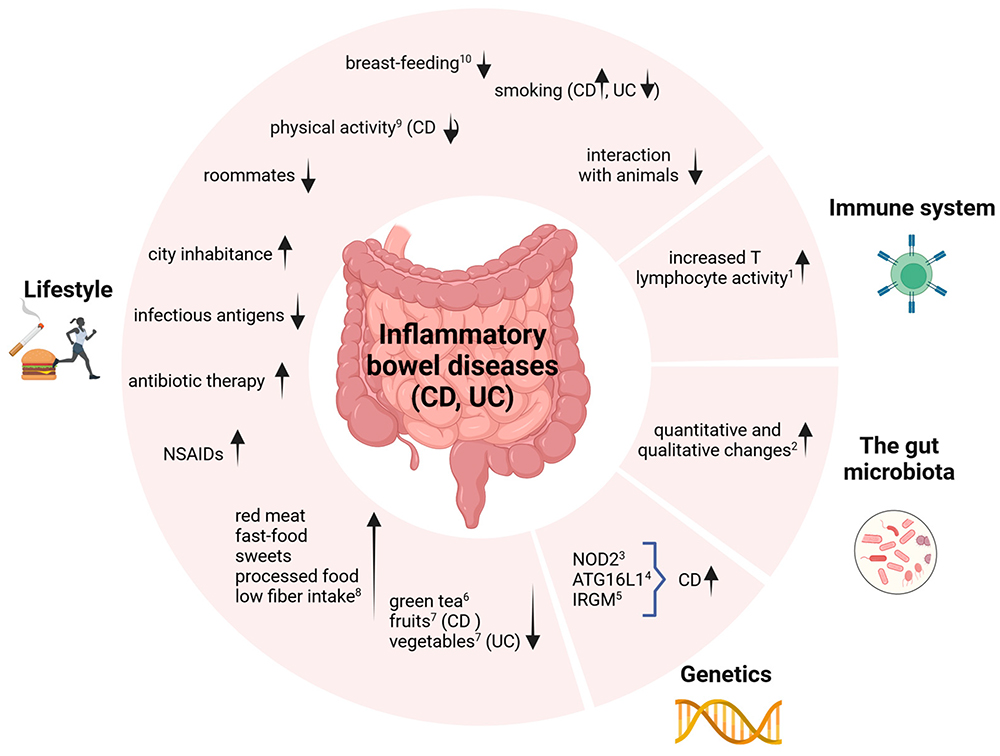
Calprotectin is useful but it's not infallible. NSAIDs can elevate the number slightly without actual IBD activity. So can infections like Campylobacter or Giardia. I've seen post-infectious calprotectin readings stay elevated for weeks after the organism itself was gone, which led to unnecessary medication changes in at least one case I recall. The workaround was to repeat the test four to six weeks after the infection cleared rather than reacting to a single elevated value. Colorectal cancer and large polyps can also raise calprotectin. If a patient has unexplained elevation with alarm features like weight loss or anemia, you can't just attribute it to IBD and move on. That's a scenario where skipping ahead to visualization is the right call regardless of the IBD history. Another limitation is that calprotectin correlates poorly with mild mucosal healing. A patient can be in clinical remission and still have a calprotectin in the two-hundred-to-three-hundred range, which some labs would flag as abnormal even though that level might represent acceptable healing for certain individuals. The trend matters more than any single cutoff. I always ask my patients to send samples at roughly the same point in their treatment cycle so the numbers are actually comparable month to month.
What the Numbers Mean for Treatment Decisions
In ulcerative colitis, calprotectin is most established as a surrogate endpoint for mucosal healing. Several trials have shown that targeting calprotectin below a certain level — usually around two hundred micrograms per gram — correlates with better long-term outcomes than treating symptoms alone. For Crohn's disease the evidence is thinner but the general principle holds: normalization or near-normalization of calprotectin tends to predict sustained remission better than symptom assessment by itself. Biologic therapy monitoring is where the test sees the most daily use. When someone starts an anti-TNF agent or an integrin inhibitor, I typically check calprotectin at baseline, then again around eight to twelve weeks after initiation. If the number hasn't dropped meaningfully, that's often a signal to check drug levels and antibodies rather than just waiting and hoping. I had a patient on adalimumab whose calprotectin plateaued at four hundred despite feeling subjectively better. We checked the trough level, saw it was subtherapeutic, added an immunomodulator, and the number came down to acceptable range within a couple of months. Adjusting based on the biomarker caught that one before a full-blown flare happened. The counter-intuitive part is that very low calprotectin doesn't always mean everything is optimal. Some patients on combination therapy hit near-zero numbers and still experience flares from non-inflammatory causes like bile acid malabsorption or small intestinal bacterial overgrowth. Calprotectin only measures neutrophilic inflammation. It won't detect those other issues, and mistaking a non-inflammatory flare for quiescent disease is a real clinical trap.
When to Skip the Test or Pair It With Something Else
If a patient has clear endoscopic evidence of active disease and obvious clinical symptoms, repeating calprotectin adds little value. The test shines brightest in surveillance intervals and in patients whose symptoms are ambiguous. It's also less useful in strictly perianal Crohn's disease where inflammation may be contained outside the lumen and not shedding calprotectin into the stool in meaningful quantities. C-reactive protein and erythrocyte sedimentation rate remain the blood-based companions to calprotectin, but they're far less sensitive for gut-specific inflammation. CRP can be normal in up to half of IBD flares. I rarely order CRP alone for IBD monitoring anymore unless I'm also checking the fecal marker. The combination gives you a more complete picture, though the fecal test should carry more weight in most maintenance scenarios. For anyone managing IBD long-term, the practical takeaway is that calprotectin testing is routine enough to not be daunting but precise enough to matter when you interpret it correctly. Know the cutoffs, watch the trend, and don't let a single number drive a major therapy change without context. That's how you use it without overreacting or underreacting.