Understanding Sp and Systolic Pressure
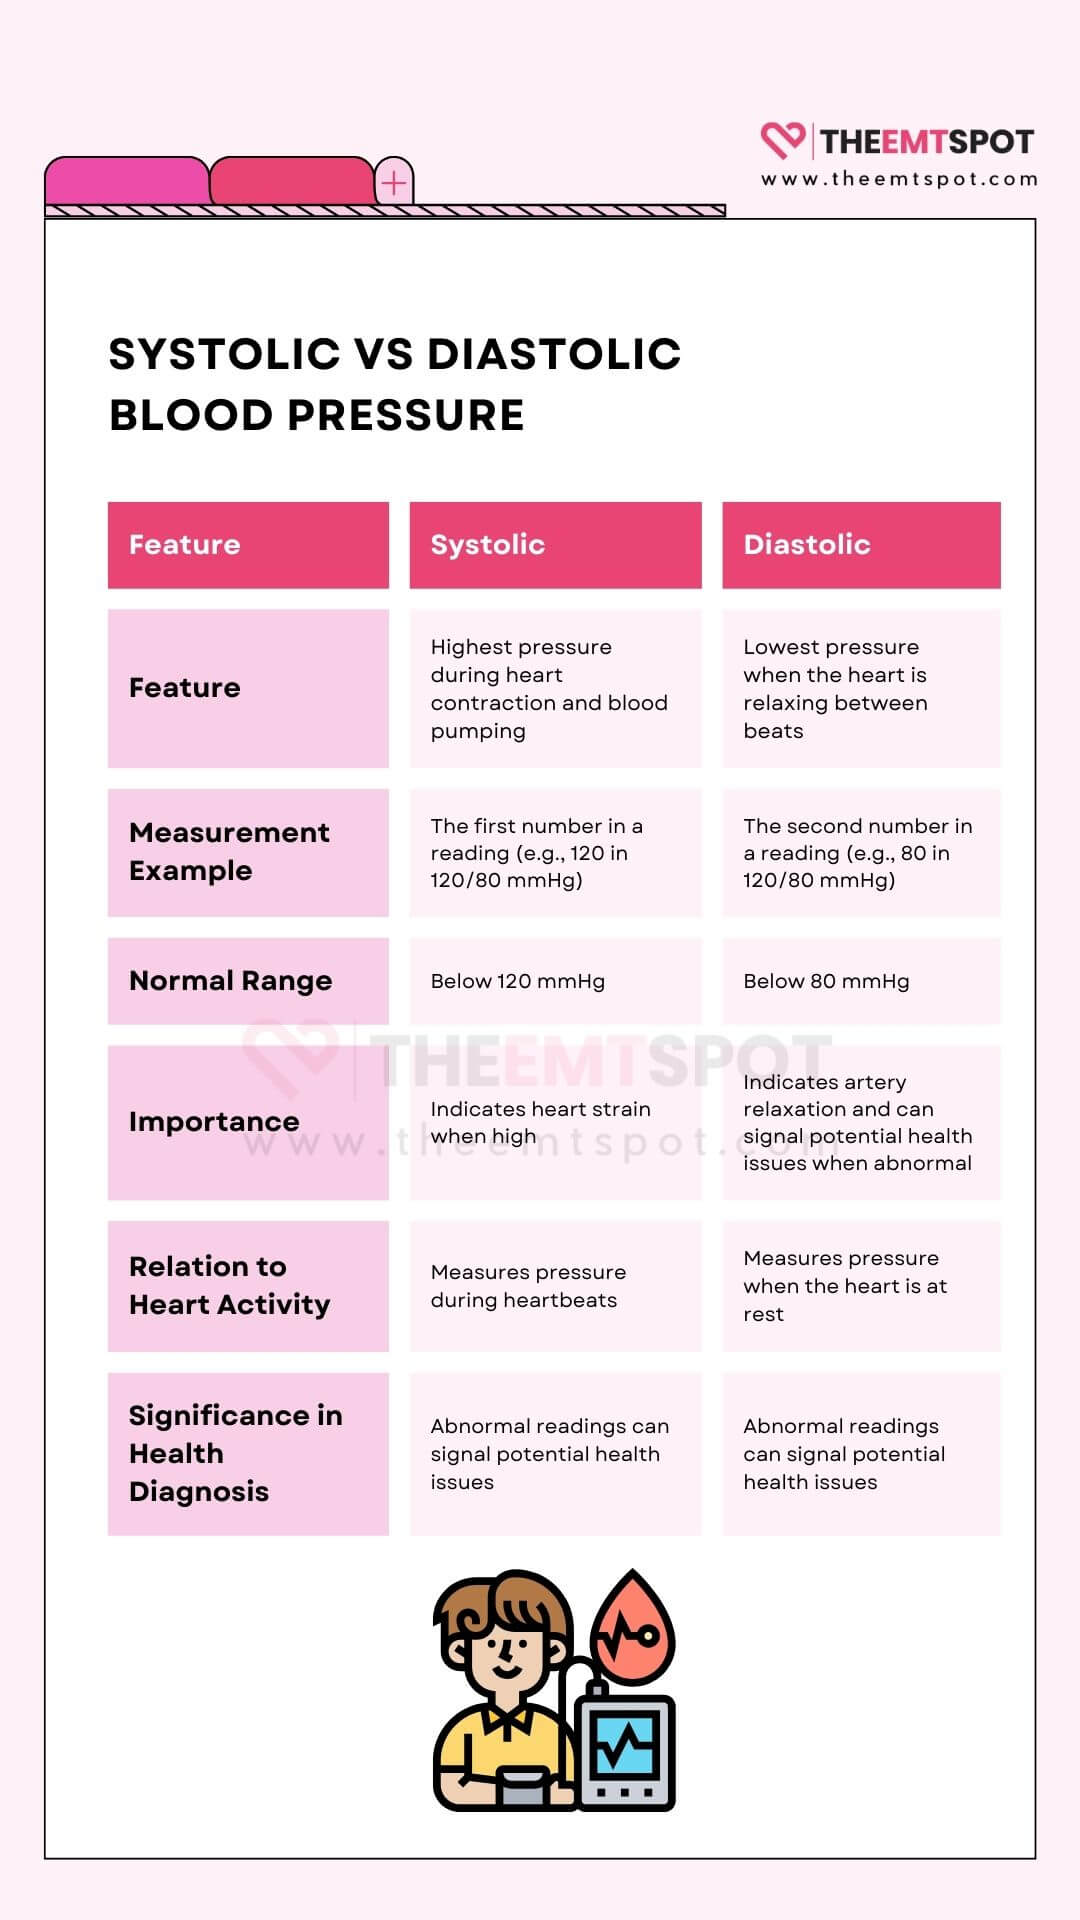
Sp is shorthand for systolic pressure, the top number on a blood pressure reading. When you see a result listed as Sp 120, it means the systolic pressure during that heartbeat cycle was 120 mmHg. This is standard notation in electronic health records, lab reports, and sometimes quick handoff notes between clinicians. The abbreviation saves time when space is tight on a chart or when documenting rapid serial measurements. I spent years managing inpatient floors where we tracked blood pressure every four hours on stable patients. Writing out "systolic pressure" repeatedly gets old fast. Sp became universal shorthand because everyone understood it. You will still see full terms in formal publications, but in clinical practice, Sp does exactly what it says.
What Does Sp Mean In Medical Terms Understanding The Systolic Pressure
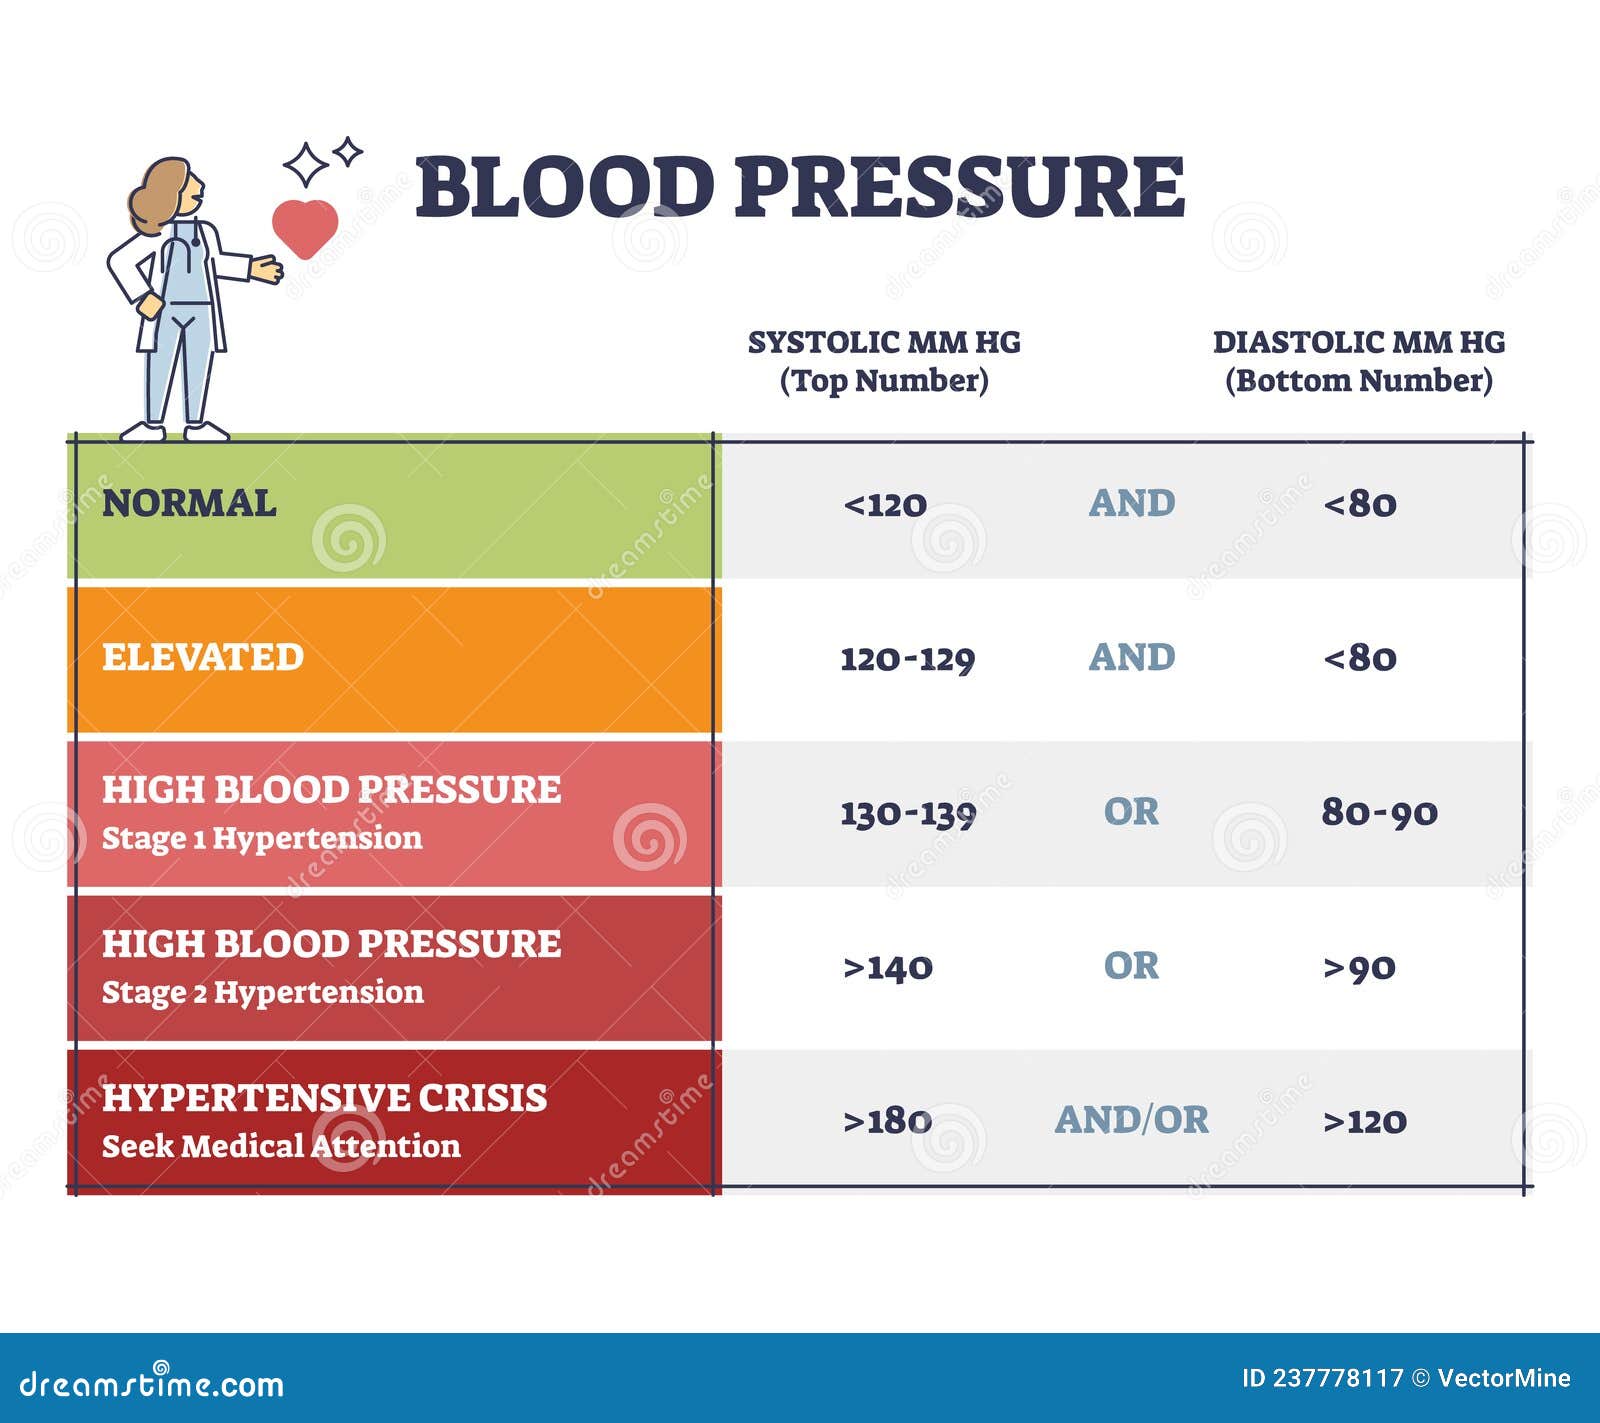
The systolic number represents the pressure in your arteries when your heart contracts. It is measured in millimeters of mercury, abbreviated as mmHg. A normal resting systolic reading falls between 90 and 120 for most adults. Anything consistently above 130 is considered elevated and typically triggers further evaluation. Below 90 can indicate hypotension, especially if the patient is symptomatic. One detail people routinely miss is that Sp alone does not tell the whole story. A patient could have a perfectly normal Sp of 120 but a dangerously high diastolic of 105. That is a sign of isolated systolic-diastolic hypertension, which carries significant cardiovascular risk. Always check the full reading. Never treat the top number in isolation. I encountered a specific edge-case early in my career that changed how I interpret these numbers. An elderly patient presented with a Sp of 105, which looked borderline low to the attending physician. I was about to call for a repeat measurement when I noticed the pulse was irregular and the Sp had actually climbed from 98 at rest to 105 with minimal ambulation. The patient was in atrial fibrillation with rapid ventricular response. A flat Sp might suggest stability, but that slight rise with activity revealed underlying compensation. The workaround was simple: I documented the trend rather than a single snapshot, and the team initiated rate control instead of holding off on treatment. Context matters more than a single digit.
When measuring Sp yourself with a home monitor, proper technique matters more than most people realize. Sit quietly for five minutes before taking a reading. Keep your arm supported at heart level. Do not talk during the measurement. Take three readings one minute apart and record the average. The first reading is almost always artificially elevated due to the white coat effect, even at home. Discard it. The average of the second and third readings is what you report to your clinician. Common pitfalls with Sp include using a cuff that is too small, crossing your legs while measuring, or taking readings immediately after caffeine or exercise. All of these inflate the number by 5 to 15 mmHg without warning. That margin is enough to shift someone from "elevated" to "hypertension stage 1" and trigger unnecessary worry or medication adjustments. Another practical issue is arrhythmia interference. Home monitors struggle with irregular heartbeats. If you have atrial fibrillation or frequent ectopic beats, the Sp reading can be wildly inaccurate. I have seen readings swing by 30 mmHg between consecutive attempts in the same patient. In those cases, manual auscultation with a sphygmomanometer and stethoscope remains the gold standard. Automatic devices simply cannot compensate for the varying stroke volumes that come with irregular rhythms.
Get the Full Details
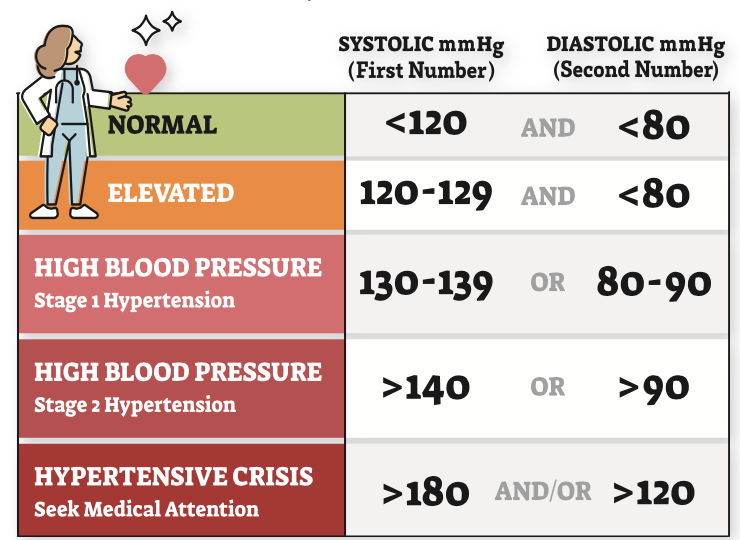
The clinical threshold for action varies by population. For healthy adults under 60, we generally treat when Sp is consistently above 130. For older adults over 75, especially those with frailty or orthostatic issues, we may accept a Sp up to 140 and prioritize avoiding falls from hypotension over aggressive lowering. Guidelines exist, but they are not one-size-fits-all. Context and comorbidities always override a single number. If you want a reliable home monitor, look for one that is validated by the FDA or approved by organizations like the British Hypertension Society. Cheap monitors from gas stations or discount stores are frequently inaccurate by 10 to 20 mmHg. The difference between a $20 unit and a properly validated device is not marketing, it is calibration. I replaced a patient's cheap monitor after their clinic readings were consistently 15 points lower, and they were being overtreated until we discovered the home device was inflating their numbers. This usually cuts diagnostic confusion down from weeks to a single office visit. Systolic pressure rises predictably with age due to arterial stiffening. A Sp of 135 in a 70-year-old is common and often accepted, while the same number in a 35-year-old warrants investigation. This is not a flaw in the system. It is physiology. The arteries lose elasticity over time, and the heart has to push harder to move blood through them. That is why age-adjusted thresholds exist in most treatment algorithms.
One advanced nuance is pulse pressure, which is the difference between Sp and the diastolic number. A wide pulse pressure, say 160 over 60 giving a pulse pressure of 100, signals potential aortic regurgitation, severe hypertension with stiff arteries, or hyperthyroidism. A narrow pulse pressure, say 100 over 85 giving a pulse pressure of 15, suggests early shock, pericardial tamponade, or severe heart failure. The gap between the two numbers often tells you more than either number alone. Track your Sp over time rather than fixating on daily fluctuations. Blood pressure varies throughout the day, across days, and with stress, illness, and sleep quality. One bad reading is noise. A trend over two weeks is data. I recommend logging morning and evening readings for fourteen days before bringing a list to your appointment. Screenshots from phone apps work fine. Write it down if your app crashes. What matters is the pattern, not the single outlier. Sp is straightforward in theory and manageable in practice if you pay attention to technique, context, and trends. It is a vital sign, not a diagnosis. Use it as one piece of a larger clinical picture, and do not let a single elevated number panic you before you have established a baseline.