Walking, but Not the Way You'd Think
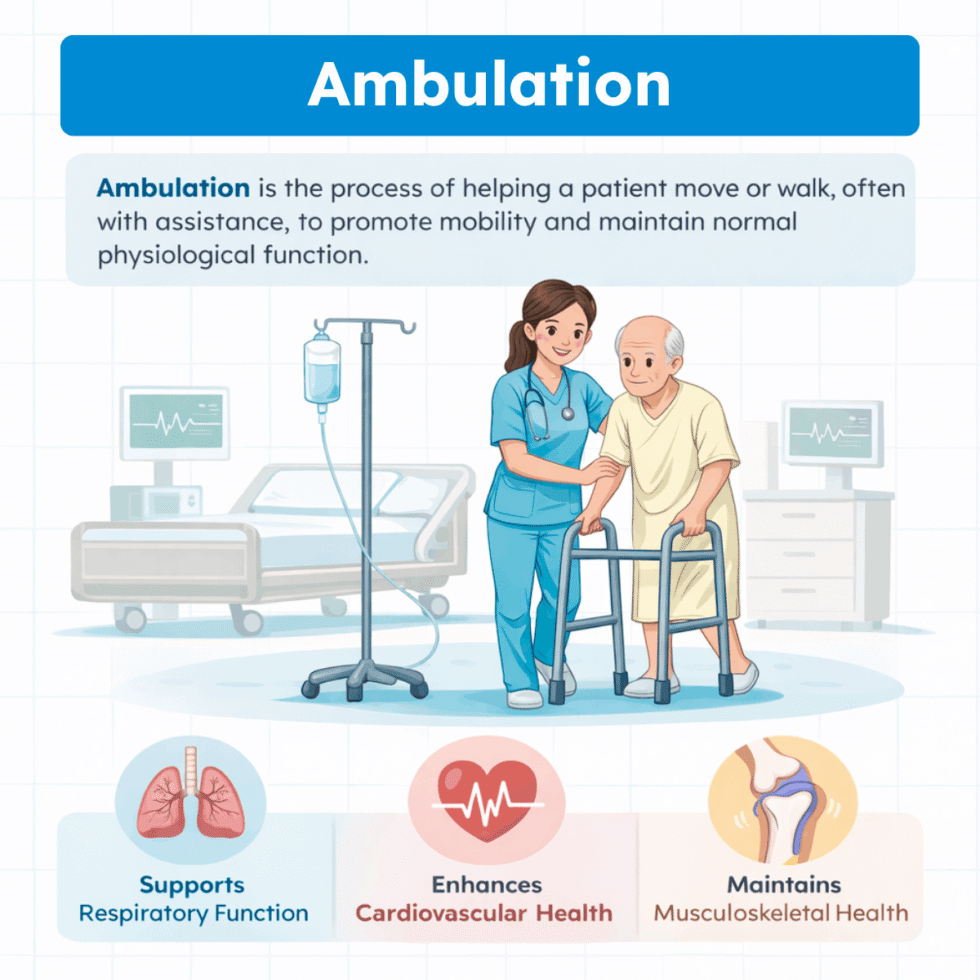
Ambulation is medical jargon for walking. That's the textbook definition, and it's not wrong. But in clinical practice, the term carries a lot more weight than a simple dictionary swap. When a nurse charts "patient ambulating," she isn't just noting that someone moved their feet in a straight line. She's documenting functional status, mobility level, independence, and often a trajectory of recovery or decline. I spent years on surgical floors watching patients progress from bedbound to bathroom visits to hallway circuits. The difference between a patient who ambulates independently and one who needs assistance isn't just a matter of physical ability. It's medication timing, pain management, fluid status, and whether the physical therapy consult ever got placed. I've seen perfectly capable patients sit for three days because nobody connected the dots between post-op orders and actual movement.
What Does Ambulation Mean In Medical Terms
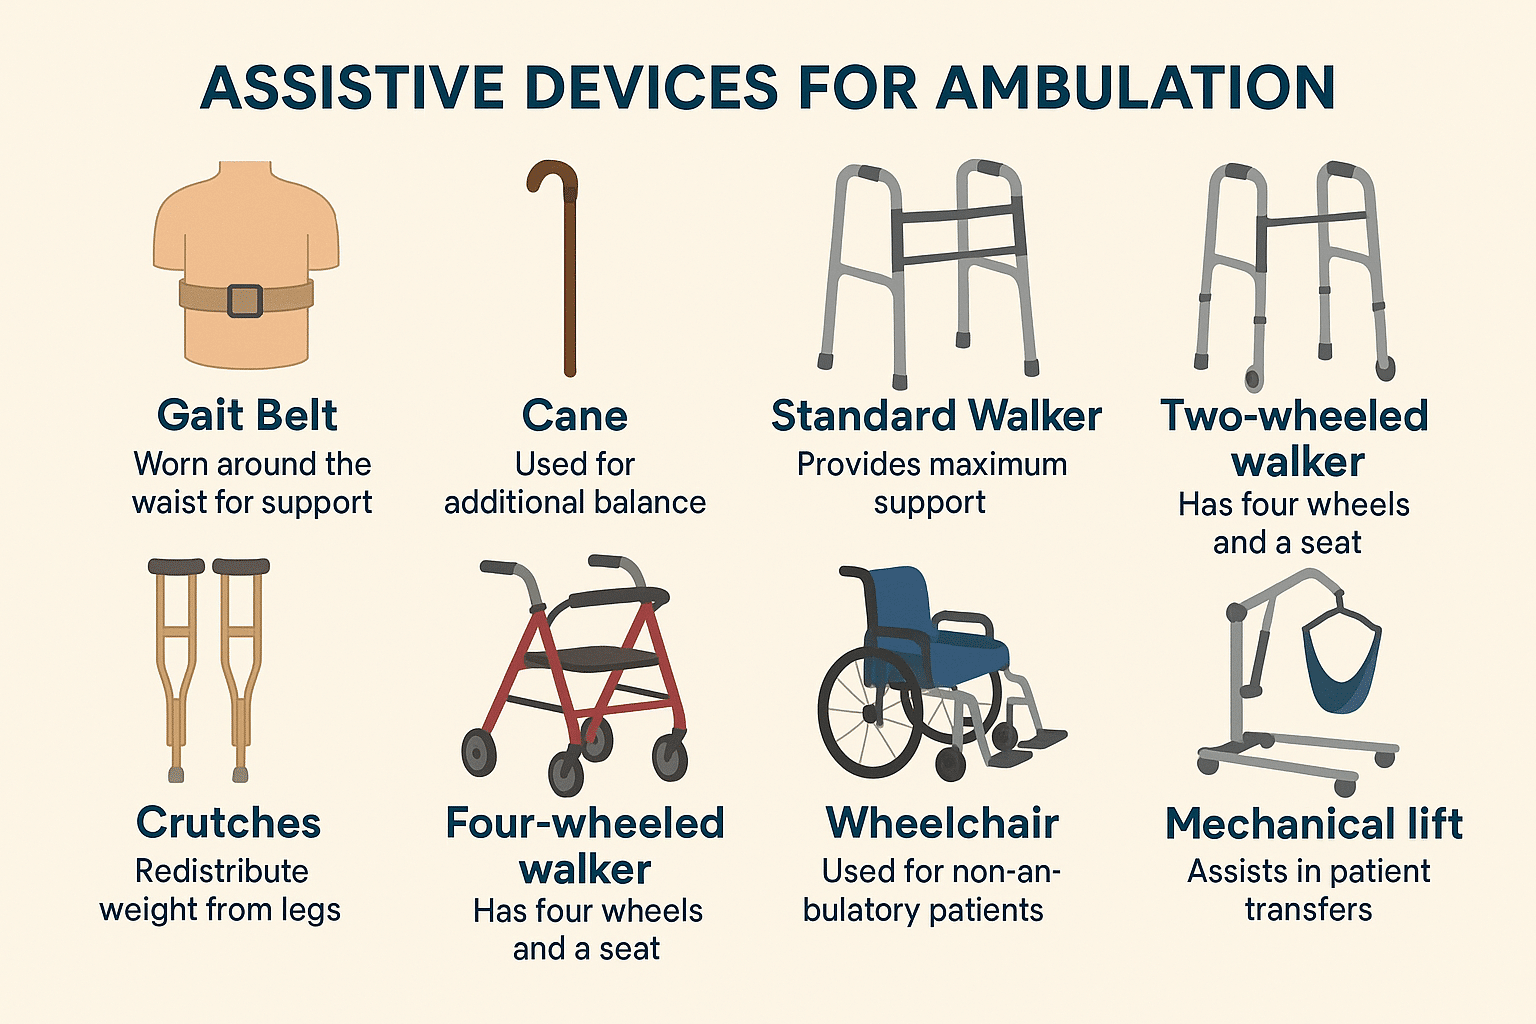
At its core, ambulation refers to the act of moving from one place to another, typically on foot. In hospital settings, it's used as a measurable milestone. You'll see it broken down into categories: independent ambulation, ambulation with assistive devices (walkers, canes, crutches), ambulation with minimal or moderate assistance, and ambulation with maximal assistance or totally dependent. Each category has specific staffing implications. Here's what most people miss. Ambulation in a medical context isn't binary. It's not just ambulating or not ambulating. There's distance, there's frequency, there's tolerance. A patient who walks fifty feet down the hall with a walker and rests afterward is ambulating. A patient who walks twenty feet before becoming dizzy and needs to sit is also ambulating, just with a significantly lower functional level. The chart needs to capture all of that. Vague documentation like "ambulated in hallway" is useless for tracking progress. I learned this the hard way when a handoff note said a patient "ambulated well" and the next shift assumed they were at baseline. They weren't. They were at half their baseline and dehydrated. We caught it when I started requiring distance and tolerance notes in our shift reports. Accuracy matters here because decisions about discharge planning, skilled nursing placement, and physical therapy intensity all hinge on how accurately that word is being used. There's a practical wrinkle that isn't in any textbook. Post-operative patients, especially after orthopedic or abdominal surgery, often resist ambulation not because they can't but because they're afraid of pain or falling. I had a patient, seventy-two-year-old male, hip replacement, day one post-op. He refused to get out of bed. Not defiant, just genuinely terrified. What worked wasn't persuasion. It was timing the ambulation session forty-five minutes after his IV pain meds peaked, having the physical therapist present before I even asked, and letting him hold onto my forearm instead of the walker for the first three steps. He walked eighty feet that day. By day three, he was doing two hundred feet independently. The intervention wasn't clinical. It was psychological. Ambulation orders mean nothing if the patient won't comply, and compliance is often the real bottleneck in these cases.
Another thing that catches people off guard. Ambulation isn't always beneficial. There are legitimate contraindications. Unstable spinal fractures, certain post-cardiac event restrictions, active deep vein thrombosis in some protocols, hemodynamic instability, and recent procedures where weight-bearing is restricted. I've seen order sets auto-generate "ambulate as tolerated" for patients who absolutely should not be up. The system didn't catch it because the order came from a attending who had written that blanket instruction months earlier and never revised it. Always verify the order against the patient's actual status before facilitating ambulation. It sounds obvious, but automated ordering systems create complacency. Staff stop double-checking because the order is already in the chart. The documentation standards around ambulation have tightened considerably over the past decade. Medicare conditions of participation and Joint Commission expectations both require clear notation of functional status. "Ambulates" alone won't satisfy an auditor. You need to note the level of assistance, distance, frequency, and any adverse events during the activity. I've had chart audits flag ambiguous ambulation notes. One reviewer marked a record as deficient because it said "assisted ambulation" without specifying whether that was one-person assist, two-person assist, or mechanical lift. The difference between those three categories determines reimbursement rates for skilled nursing facility placement. That single vague term could cost a facility thousands. If you're looking at this from a caregiving perspective rather than a clinical one, the same principles apply. Ambulation for an elderly parent at home isn't just getting them to walk. It's assessing whether they need a walker versus a cane, whether they're at fall risk, whether they're taking medications that cause orthostatic hypotension, and whether the home environment supports safe movement. I've consulted on cases where patients were prescribed walk-in showers and stair lifts because nobody considered that a four-minute walk to the bathroom with a unstable gait was the actual problem. Fix the ambulation issue first. The rest follows.
Get the Full Details

For anyone studying medical terminology or preparing for clinical rotations, understand that ambulation is one of those words that sounds simple but functions as a comprehensive assessment tool. It tells you about cardiovascular status, musculoskeletal integrity, neurological function, medication side effects, and psychological readiness all at once. The most accurate ambulation notes I ever wrote came from actually watching the patient move, not from asking them how they felt. Patients will say they're fine. Their gait speed and balance tell the truth. There's also the question of frequency. How often should a hospitalized patient ambulate? The evidence supports early and frequent ambulation for most surgical populations. Starting within twenty-four hours after many procedures reduces complication rates, shortens length of stay, and decreases the risk of deconditioning. But "frequent" doesn't mean "as much as possible." It means structured, planned, and monitored. A patient who walks three times a day for ten minutes each time typically does better than one who attempts a single long walk and then rests for two days because they're exhausted. Spacing it out matters more than the total distance in a single session. One last point that rarely gets discussed. Cultural and personal factors affect ambulation compliance in ways that standard protocols don't account for. Some patients view remaining in bed as resting properly. Others associate walking with weakness or loss of dignity. I worked with a patient who was physically capable of independent ambulation but consistently requested bed rest because she felt exposed and vulnerable in a hospital gown while moving through shared spaces. We found a workaround using a provided robe and scheduling hallway walks during lower-traffic hours. The clinical indication was clear. The barrier was entirely environmental and emotional. Ambulation orders don't address that, but competent care does.