Preterm Fetal Response To Oxygenation Interruptions: What Actually Happens
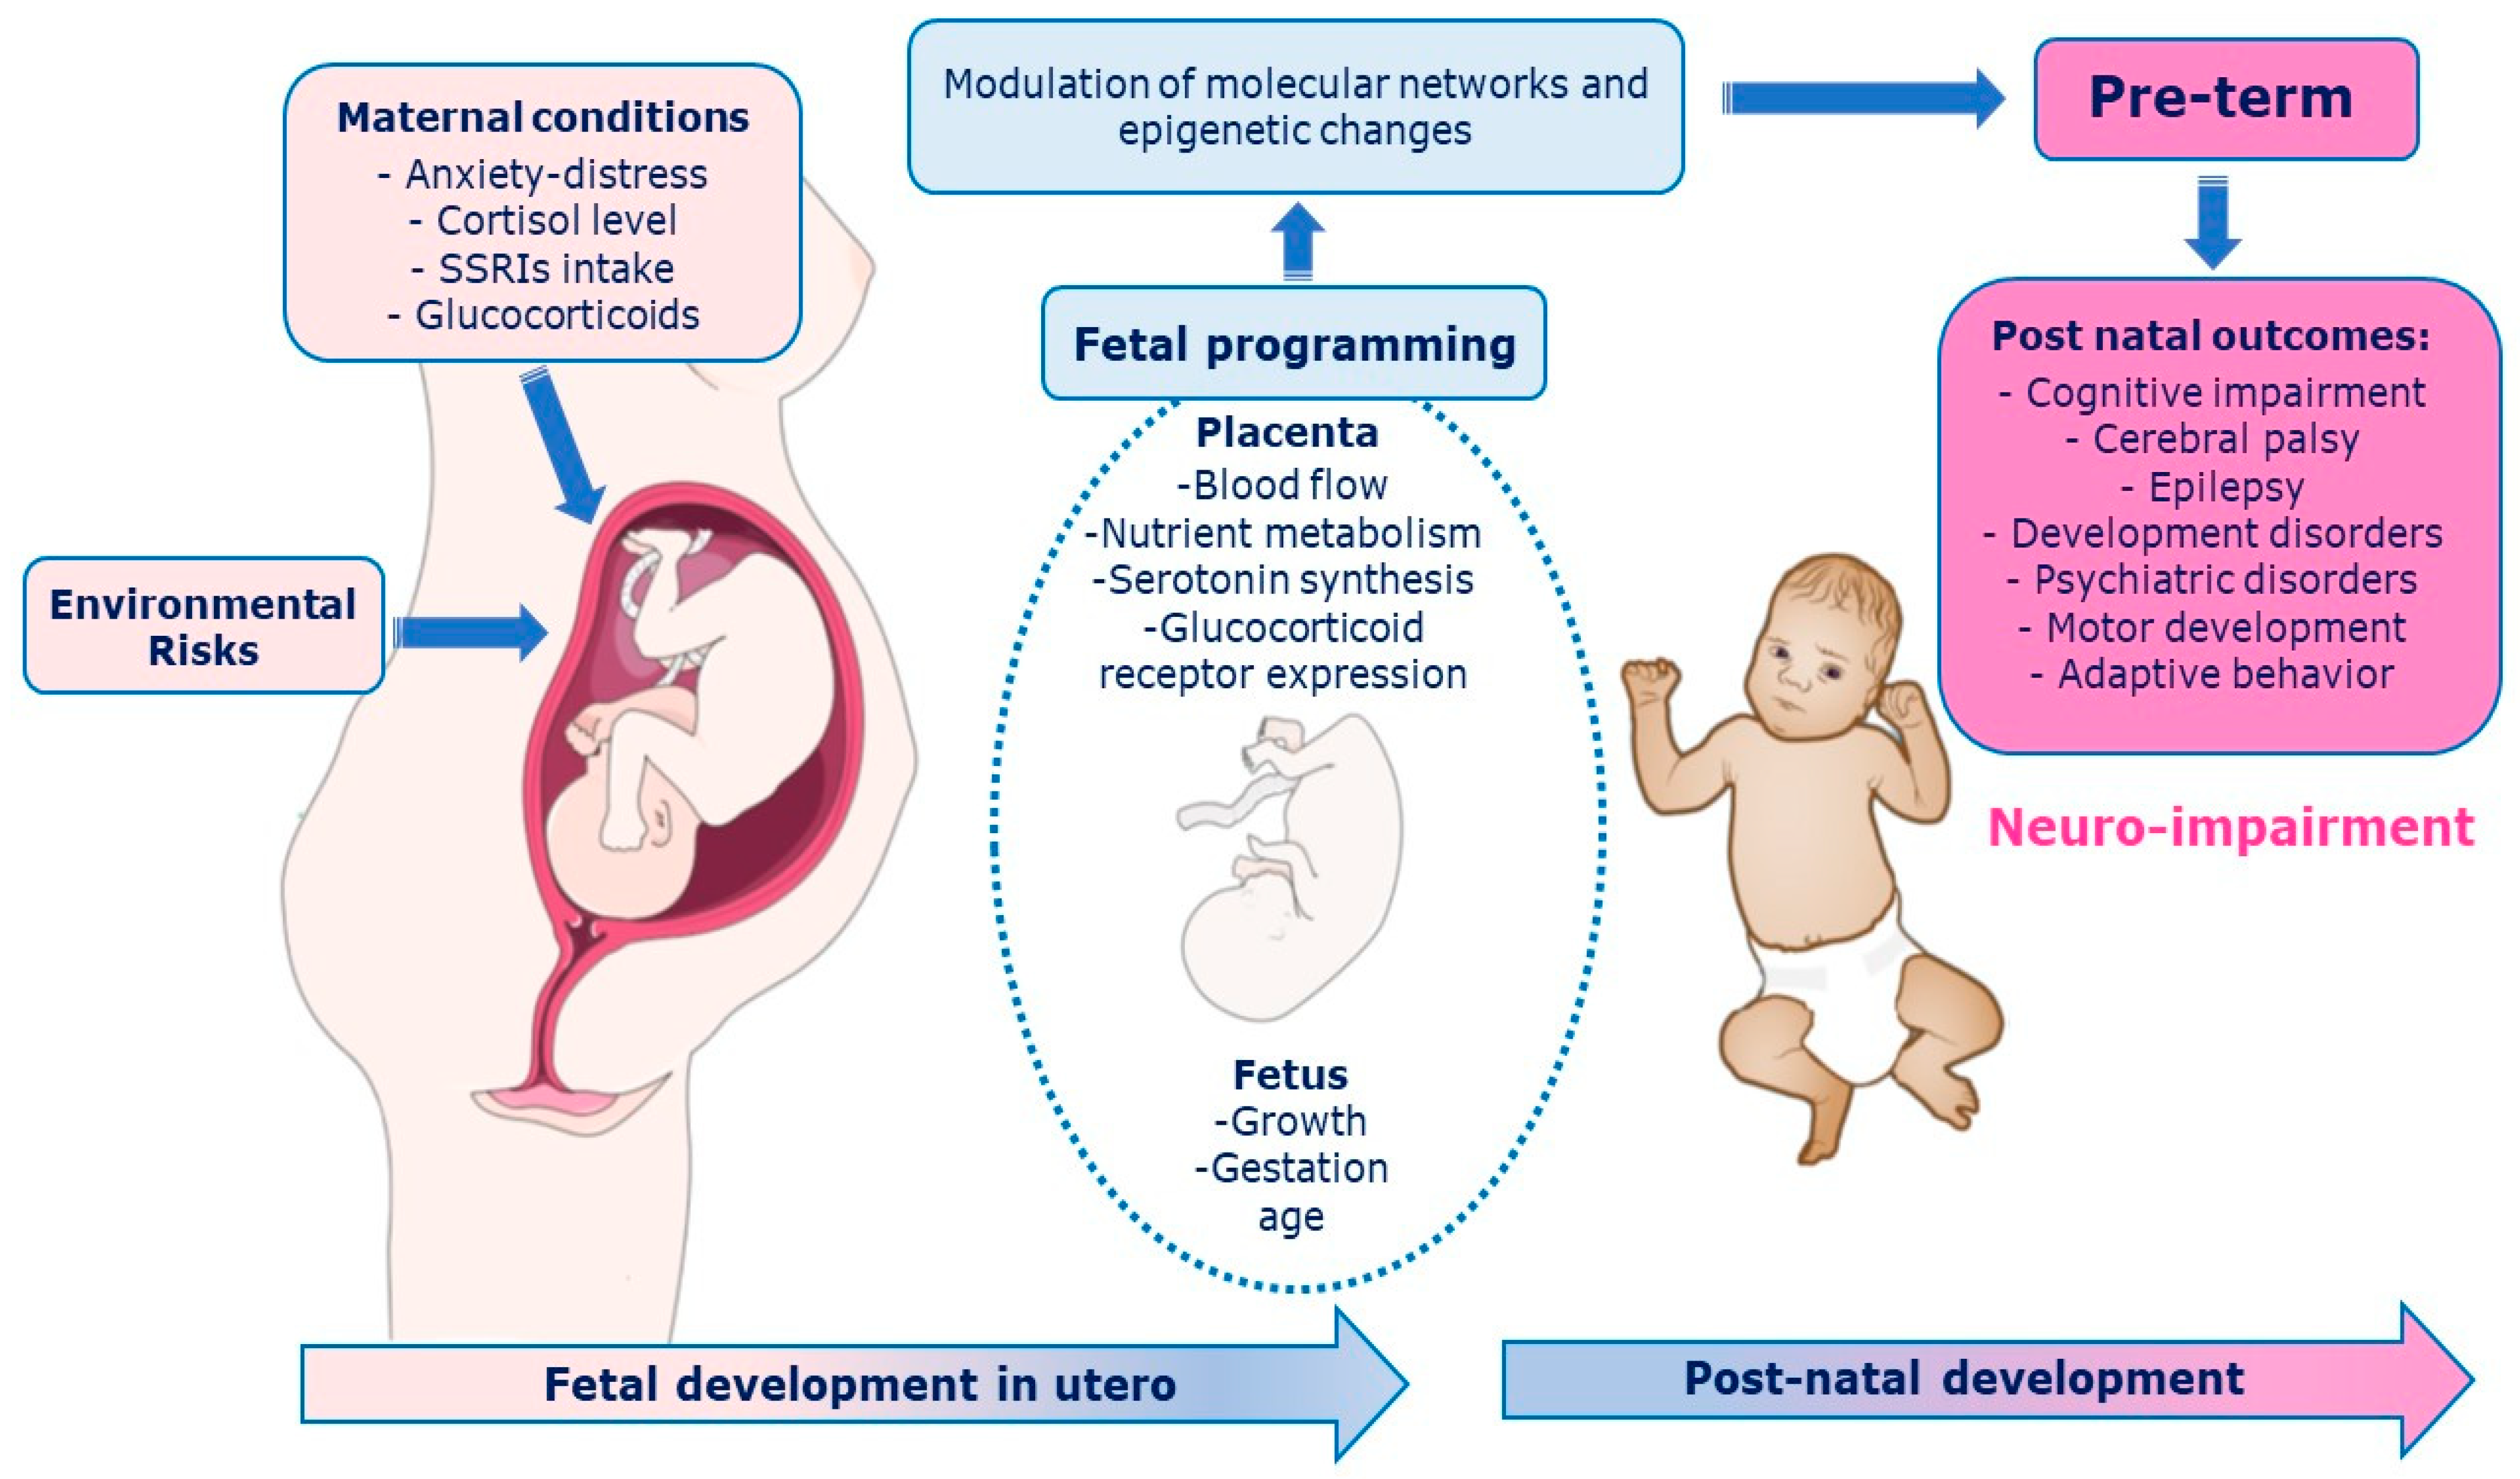
Preterm fetuses respond to oxygen interruptions differently than term fetuses, and understanding those differences matters because the clinical interpretation can be wrong if you apply term-based assumptions. I spent years reading fetal monitoring strips and learning this the hard way through a few bad calls. The core characteristic is that preterm fetuses have a blunted autonomic response. Their parasympathetic nervous system isn't fully mature, so when oxygen drops, you don't see the same protective bradycardia patterns that develop later in gestation. Instead, you might see variable decelerations that look concerning on paper but actually represent a less compromised state than they would at term. I ran into this with a 28-week patient who had recurrent variable decelerations that looked textbook severe. My first read was immediate delivery. Then I reconsidered. Those decelerations weren't descending as sharply as term equivalents, and the baseline variability remained moderate throughout. We monitored conservatively for another 48 hours, she delivered vaginally at 30 weeks, and the baby was fine. The preterm response to hypoxia is slower and less dramatic, which means the urgency is often lower than the strip appearance suggests.
There are a few mechanisms at play here. The preterm cardiovascular system has different baroreceptor sensitivity. The heart rate acceleration capabilities are limited because the neural pathways aren't myelinated yet. And the fetal hemoglobin dissociation curve is shifted left, meaning oxygen unloading to tissues works differently than it will after 36 weeks.
Reading The Strip: What Changes Before 32 Weeks
Baseline heart rate in preterms runs higher on average, around 155 to 165 beats per minute. What looks like tachycardia at term is often normal baseline at 26 weeks. When you see a deceleration, judge it against that higher baseline and don't automatically escalate the category. Acceleration criteria are different too. At term, we look for 15 beats above baseline lasting 15 seconds. Before 32 weeks, the threshold drops to 10 beats above baseline for 10 seconds. If you apply the term criteria to a preterm strip, you will miss accelerations and misclassify reactive tracings as non-reactive. Variable decelerations in preterms tend to be shallower and longer in duration rather than deep and abrupt. The cord compression physiology is the same, but the fetuses compensate more slowly. This means you should watch the recovery phase carefully. If the heart rate returns to baseline within two minutes after the contraction ends, that's reassuring even if the nadir looked ugly.
Get the Full Details

Consequences And Why They Matter Differently
The consequences of oxygen interruption in preterms are not simply scaled-down versions of term consequences. Their brains are more vulnerable to oxidative stress during periods of reoxygenation after an interruption. The oligodendrocyte precursors that myelinate the CNS are extremely sensitive to free radical damage, and each hypoxic event followed by resumption of oxygenation creates a burst of reactive oxygen species. I saw this in practice with a set of twins at 27 weeks. One twin showed prolonged deceleration during induction. We moved quickly, but the infant still had mild periventricular leukomalacia on follow-up imaging. The other twin had a shorter interruption and no imaging abnormality. The difference wasn't the severity of the initial drop, it was the total duration of compromised oxygenation and the inflammatory cascade that followed. Sometimes the consequences show up later. Children born preterm who had repeated intermittent hypoxic events in utero have higher rates of attention deficits and motor coordination issues at age five, even when neonatal courses were uncomplicated. The damage is subtle and cumulative, which is why the monitoring has to be consistent rather than reactive.
Clinical Vigilance: What Actually Works
The biggest mistake I see is applying term-based algorithms blindly. The NICE guidelines and ACOG categories were built on term populations. They work, but the thresholds need adjustment. A category II tracing at 28 weeks deserves a different management plan than a category II tracing at 39 weeks. Here is what I do in practice. First, confirm gestational age accurately. An estimated age that is off by two weeks can completely change how you interpret the strip. Second, look at the acceleration pattern before you fixate on decelerations. Absence of accelerations in a preterm fetus is far more concerning than the presence of shallow variables. Third, check the variability. Minimal or absent variability in a preterm fetus before 30 weeks is abnormal regardless of other features. When I encounter a preterm strip with concerning features, I don't jump to immediate intervention. I optimize maternal position, give IV fluids, and adjust oxygen if the mother is hypoxic. I then reassess in 20 to 30 minutes. The preterm fetus tolerates intervention better than term fetuses because their oxygen extraction is different. This window usually gives enough information to decide whether delivery is actually needed or whether continued monitoring is appropriate.
There is one scenario where this approach fails and I want to be direct about it. If the fetus shows sinusoidal pattern or prolonged bradycardia below 80, no amount of conservative management changes the outcome. Those are emergency situations regardless of gestational age. I once missed that distinction with a 26-week patient who had what I initially read as severe variables. On second look, it was a sinusoidal pattern. We delivered within 40 minutes. The baby had significant complications but survived. That call costs you sleep. The bottom line is that preterm fetal monitoring requires a different mental model. The responses are slower, the thresholds are lower, and the consequences operate on a different timeline than term monitoring. Spend time studying preterm tracings specifically. Read about the physiology before you trust your patterns. And when something feels off, slow down and reconsider rather than rushing to the OR based on a template designed for a different population.