Understanding What Sinews Communicate Through Physical Tension
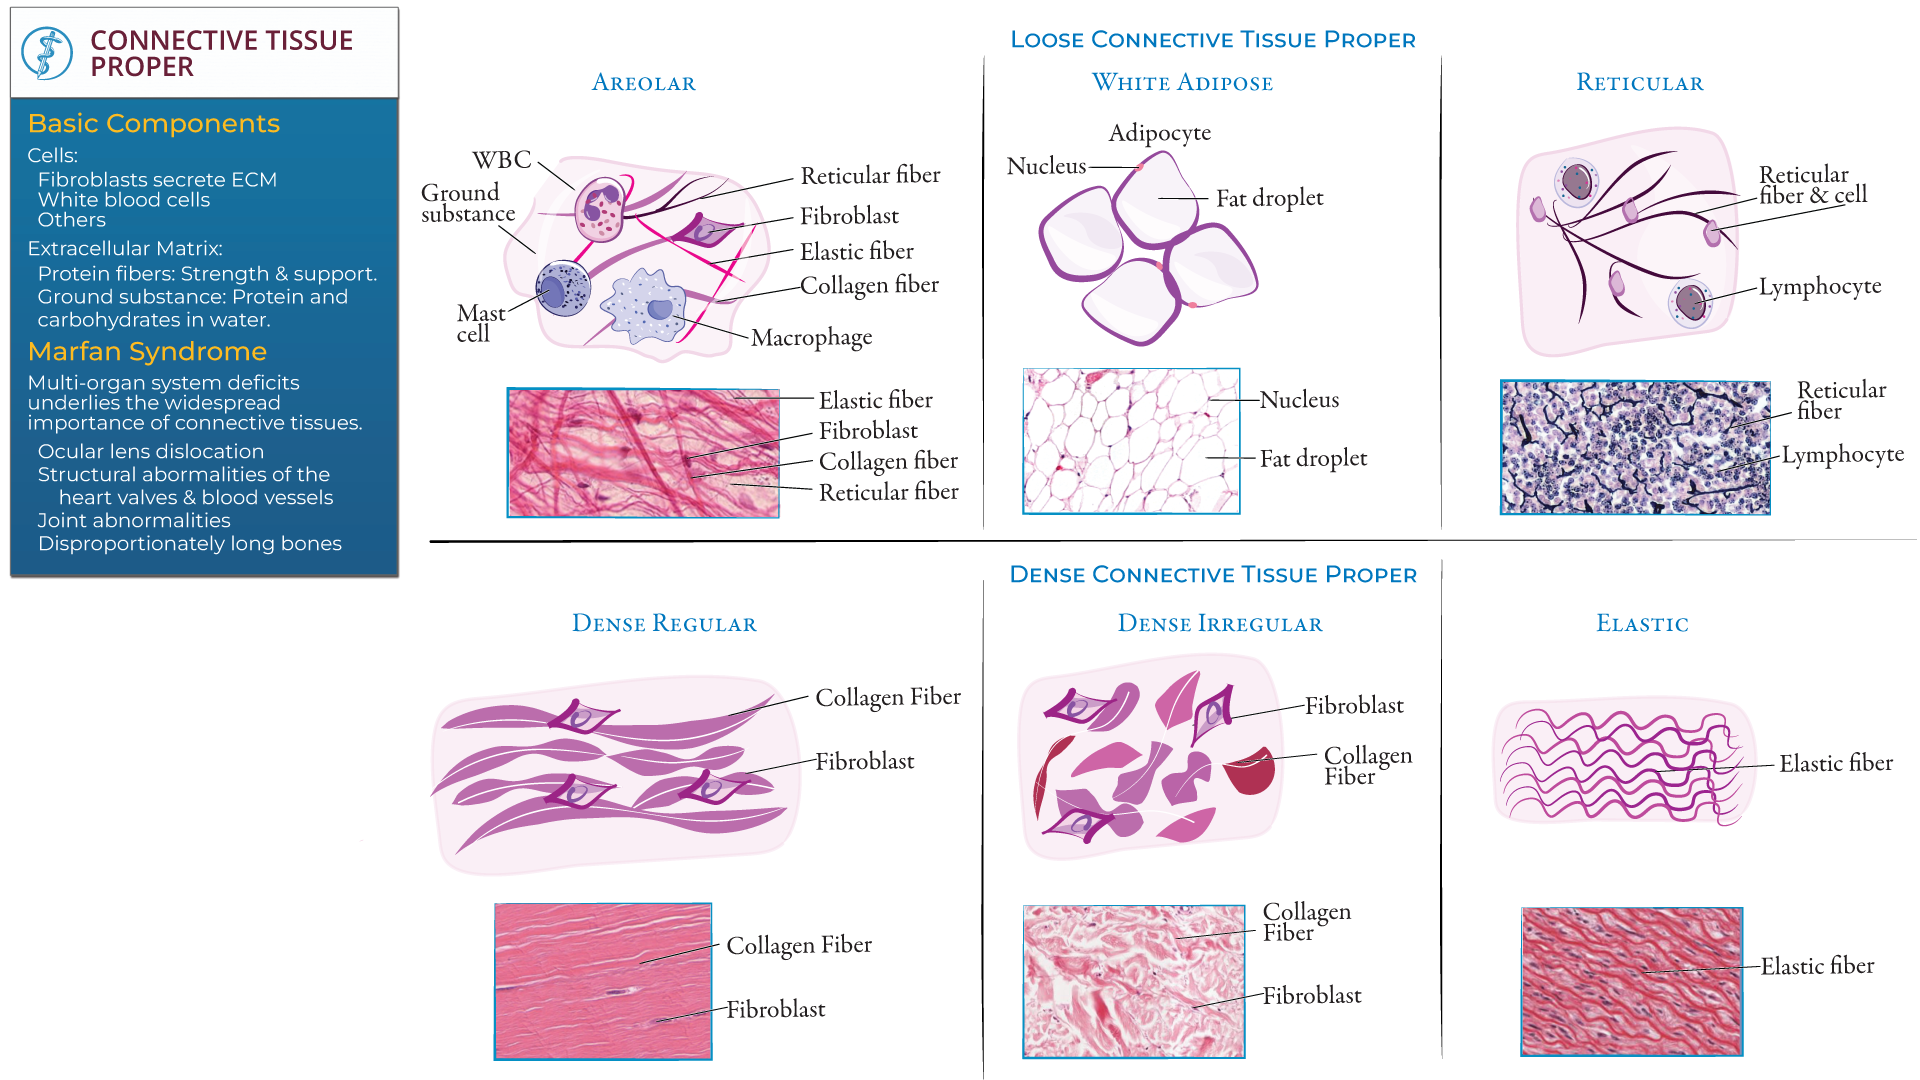
Sinews, commonly referred to as tendons, are dense fibrous connective tissues that attach muscle to bone. They transfer mechanical force generated by muscle contraction into skeletal movement. Ligaments, which are structurally similar but serve a different function, connect bone to bone and stabilize joints. Both fall under the broader category of connective tissue that includes fascia, aponeuroses, and retinacula. Understanding these structures matters because they carry mechanical loads far beyond what most people realize. A tendon can withstand tensile stress in the range of 50 to 100 megapascals before failing, which translates to several times body weight during everyday activities like walking or lifting. Translating sinew language means reading the signals that connective tissue sends through changes in texture, elasticity, and resistance. When a tendon becomes stiff or thickened, it is communicating a history of repeated mechanical stress, incomplete healing, or compensatory loading patterns. The translation process involves palpation, movement assessment, and observation of how tissue responds under load. A healthy tendon glides smoothly beneath the skin and returns to its baseline shape after deformation. A compromised tendon feels rope-like, warm, or nodular. This is not abstract terminology. It is something you learn to recognize through repeated hands-on assessment. The connective tissue network operates as a continuous tensional field. Fascia surrounds muscles, envelops individual fibers, and connects to tendons at the myotendinous junction. When one region of this network tightens, the effect propagates through the entire system. A restriction in the plantar fascia can alter Achilles tendon mechanics. A Tight hip flexor can change the loading pattern on the patellar tendon. This interconnectedness is why isolated treatment often fails. You have to understand the full chain of tension, not just the site of pain.
I spent years working with athletes who presented with what appeared to be straightforward tendonitis. The standard protocol was rest, ice, and eccentric loading exercises. It worked for some. For others, it made things worse over time. The turning point came when I stopped treating the tendon as an isolated structure and started mapping the tension pathways feeding into it. One particular case stands out. A marathon runner came in with chronic Achilles tendinopathy that had not responded to six months of conventional treatment. The tendon itself was thickened and painful at the mid-portion. Standard eccentric protocols had been applied correctly. The problem was not the tendon. It was the gastrocnemius-soleus complex and the superficial back line fascia extending up through the hamstring and into the thoracolumbar fascia. The leg was compensating for a stiff lumbar spine and restricted hip extension. Until we addressed the proximal restrictions, the distal tendon remained overloaded regardless of how many calf raises we prescribed. The workaround was straightforward once the pattern became visible. We spent three weeks working on lumbar mobilization, hip flexor release, and myofascial decompression along the posterior chain before returning to any direct tendon loading. The tendon itself required only about six weeks of gradual reloading after the upstream issues were resolved. Total treatment time was roughly ten weeks compared to the six months of failed intervention. The difference was reading the connective tissue landscape as a whole rather than focusing on the most obvious symptom.
Reading Connective Tissue Signals in Practice
Palpation is the primary tool for translating tissue language. You are assessing viscosity, temperature, mobility, and tissue layering. Healthy deep fascia has a quality. It moves independently beneath the skin. Fibrotic or dehydrated fascia adheres to underlying structures and moves as a single rigid mass. Adhesions feel like sticky or gritty resistance under the fingertip. They do not always correspond to pain. A person can have significant fascial restriction in an area that feels neutral to them until movement stretches that restriction. Creep and stress relaxation are two fundamental material properties of connective tissue that every practitioner needs to understand. Creep is the tendency of tissue to deform progressively under sustained load. If you hold a joint at end range for several minutes, the collagen fibers gradually lengthen and the tissue yields. Stress relaxation is the reduction in tension that occurs when tissue is held at a constant length. These properties are the basis for sustained stretching protocols. Holding a position for 90 to 120 seconds allows the collagen matrix to undergo viscoelastic deformation. Short bouncy stretches do not produce the same effect because the tissue remains in a predominantly elastic state. Wolff's law applies to bone, but a similar principle governs connective tissue. Tissue adapts to the mechanical demands placed upon it. Repetitive loading in a specific direction strengthens collagen fibers along that axis. Unloaded tissue degrades. Overloaded tissue thickens and becomes less compliant. This is why sedentary people often have stiffer tendons and why athletes develop region-specific adaptations. The problem arises when loading patterns change faster than tissue can adapt. Tendons have relatively poor blood supply compared to muscle. The nutrient diffusion rate limits how quickly they can remodel. A common mistake is prescribing aggressive loading too soon after injury or during a sudden increase in training volume. The tendon responds slower than the muscle. Muscle strength can improve noticeably within weeks. Tendon remodeling often requires three to six months of consistent graded loading.
Get the Full Details

Common Pitfalls in Connective Tissue Assessment
One major pitfall is confusing muscle tightness with fascial restriction. A muscle that feels short on palpation may simply be neurologically inhibited or weakened rather than genuinely shortened. Loading it aggressively will not resolve the issue and may worsen it. The correct approach is to differentiate between true structural shortening and protective co-contraction. Neurogenic tightness responds to nervous system down-regulation, gradual lengthening, and strengthening through full range of motion. Fascial restriction responds to sustained mechanical loading and manual decompression. Another frequent error is treating pain as the primary target. Pain is a reliable alarm signal, but it is not a precise map of the underlying problem. Referred pain from myofascial trigger points can localize distantly from the source. A trigger point in the upper trapezius can refer pain along the side of the neck and into the temple. A trigger point in the piriformis can refer pain down the posterior thigh, mimicking sciatica. Palpating for taut bands and nodules within muscles helps distinguish referral patterns from primary tissue pathology. Pressing on a active trigger point reproduces the patient's familiar pain pattern and often produces a local twitch response.
When Translating Connective Tissue Signals Fails
This approach has clear limitations. It does not work well for acute inflammatory conditions where the tissue is actively degenerating. Systemic conditions like rheumatoid arthritis, gout, or metabolic disorders require medical intervention that manual assessment cannot address. Structural abnormalities such as bone spurs, calcifications within the tendon, or complete ruptures are visible on imaging and should not be mistaken for soft tissue dysfunction. If a patient presents with sudden onset severe pain, swelling, bruising, or loss of function, the first step is imaging, not palpatory assessment. The method also depends heavily on the skill and experience of the assessor. Two practitioners may palpate the same area and reach different conclusions about tissue quality. There is no standardized objective measure for fascial viscosity. This subjectivity is a real weakness. Using tools like ultrasonography to visualize tendon thickness, fiber alignment, and blood flow can supplement manual assessment and reduce interpretive variability. Shear wave elastography is becoming more accessible and provides quantitative measurements of tissue stiffness.
A Practical Framework for Reading Sinew Signals
The process begins with a movement screen. Observe how the person moves before touching them. Look for asymmetries, compensations, and restricted ranges. Then move to palpation. Assess tissue temperature, hydration, and mobility in the affected region and adjacent segments. Identify areas of increased density, adhesion, or decreased glide. Next, apply controlled load and observe the tissue response. Does the tissue yield gradually under sustained pressure? Does it spring back immediately? Does it feel glassy and hard or pliable and responsive? Finally, correlate your findings with the movement screen. Do the restrictions you identified explain the movement deviations you observed? Progressive loading is the primary intervention for most connective tissue issues. The key is dose control. Start with sub-load tasks that do not provoke significant pain during or after the activity. A useful benchmark is keeping pain during and after exercise below 3 out of 10 on a standard scale. If pain exceeds that threshold, the dose is too high. Increase load gradually over weeks, not days. Isometric holds are an effective starting point because they generate force without significant joint movement or tissue strain. A 45-second isometric hold at 70 percent of maximum effort, repeated three to five times, can reduce tendon pain through neuromodulatory mechanisms while beginning the remodeling process. Hydration status significantly affects connective tissue mechanics. Dehydrated fascia becomes more adhesive and less slippery. Collagen fibers require water to maintain their triple helix structure and proper spacing. People who train intensively and do not maintain adequate hydration often report increased stiffness and slower recovery. This is not a minor factor. It is a foundational variable that interacts with every other intervention.

The deeper you go into connective tissue assessment, the more you realize that the body does not compartmentalize problems the way textbooks do. A knee issue is rarely just a knee issue. A shoulder complaint is almost never isolated to the rotator cuff. The connective tissue network distributes force across the entire body. Reading it requires patience and a willingness to follow the tension wherever it leads rather than stopping at the most obvious location. Most people stop too early. The real information is usually two or three regions away from the symptom.