What Sinews Actually Are, Without the Drama
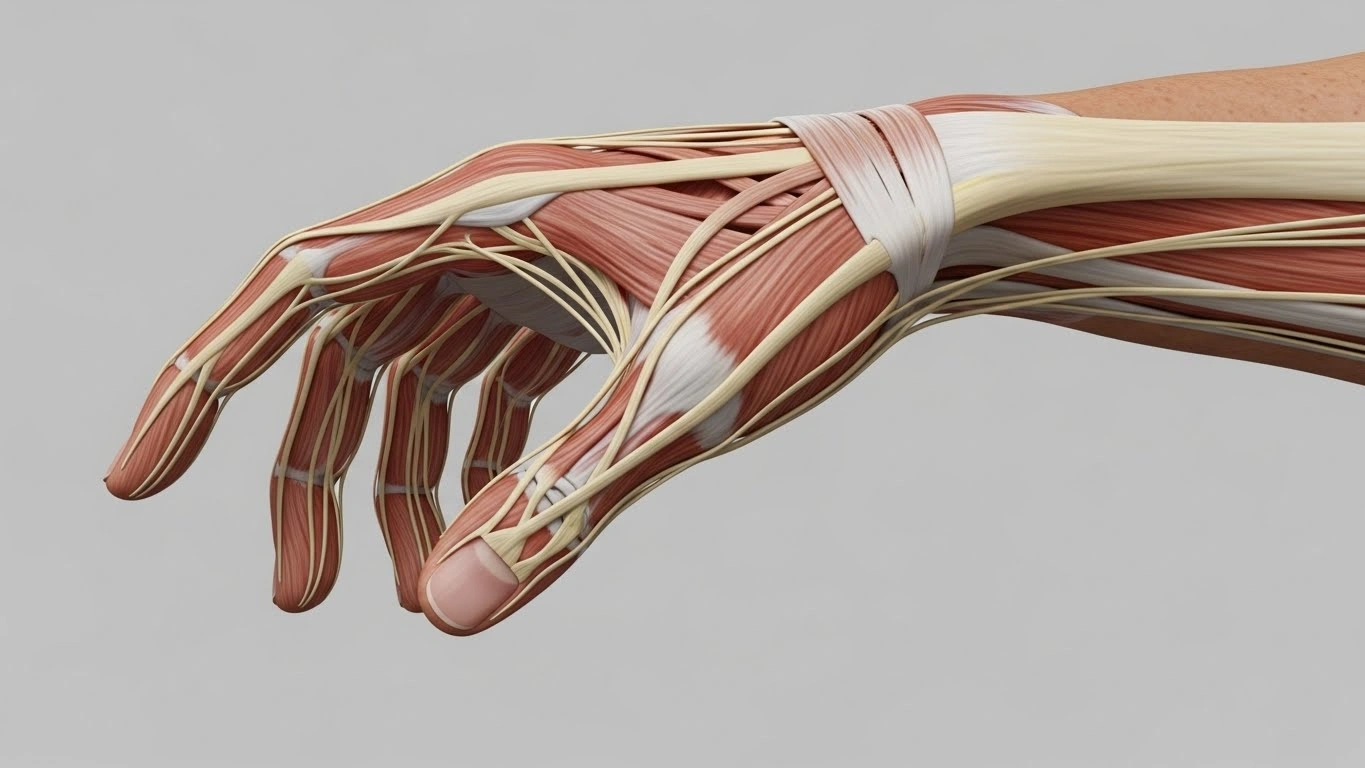
Sinews are the tough, fibrous connective tissues that attach muscle to bone, though in common usage the word gets applied loosely to the entire structural network holding your body together. The precise medical term is tendon, and the distinction matters more than you'd think if you ever deal with a real injury or read a surgical report. Ligaments connect bone to bone. Sinews or tendons connect muscle to bone. They look similar under a microscope — dense regular collagen — but they sit in different mechanical roles and fail differently. I spent years working with athletes and manual laborers who'd tear a tendon and then swear they'd "strained a sinew," which usually meant they'd confused the timing and location of the injury. The difference isn't academic. A partial tendon rupture near the insertion point on the bone heals completely differently from a mid-substance strain, and mislabeling it in a rehab context can cost you weeks. I learned that the hard way when a client came in claiming a hamstring pull after a hike. He'd actually avulsed the distal hamstring tendon off the ischial tuberosity. We ended up getting him to an orthopedist within 48 hours because the mechanism didn't match a typical strain, and that timing probably saved his hamstring from chronic weakening. A month later would have been worse.
What Are Sinews A Simple Definition You Need To Know
A tendon is a band of dense fibrous connective tissue made primarily of type I collagen fibers arranged in parallel bundles, with sparse tenocyte cells interspersed between them. It transmits force from the muscle belly to the bone, and it does so with very little stretch — healthy tendons elongate roughly 4 to 8 percent of their resting length before reaching their failure point. That low elasticity is the whole point. Muscles contract; tendons lock that contraction into skeletal movement without absorbing and dissipating energy like a ligament would. The composition is what makes tendons tricky to work with clinically. They have poor blood supply compared to muscle tissue. A tendon's vascularity sits around 5 to 10 percent of what you'd find in skeletal muscle, which means injuries heal slowly and conservatively managed tears often stall at partial thickness. I've seen people push through Achilles tendinopathy for months thinking it would resolve on its own, when really the collagen fibers were just reorganizing poorly under continued load. The workaround I found that actually moves the needle is progressive heavy slow resistance training — three sets of ten reps at about 70 percent of one-rep max, done twice weekly, held for 12 to 16 weeks. Most degenerative tendons respond to that protocol if caught early enough, but the window closes once you're past partial tearing into complete disruption. One thing beginners consistently miss is that tendons aren't uniform structures. The musculotendinous junction — where the muscle fibers taper into tendon — is actually the weakest point in the entire unit, not the mid-substance of the tendon itself. Most hamstring and biceps ruptures happen there, not in the middle of the cord. Another counterintuitive detail: tendons don't just handle tension. Under certain joint angles and loading conditions, they can experience compressive forces that cause delamination or fraying against bony prominences. Rotator cuff tendinopathy is partly a compression impingement issue, not just an overuse stretch issue. That changes the treatment approach entirely.
There's also a naming problem you run into when reading older texts or talking to non-specialists. "Sinew" historically covered both tendons and ligaments interchangeably, and in some veterinary and comparative anatomy contexts it still does. If you're reading about large animals or horse conditioning, sinew might mean the nuchal ligament or the suspensory apparatus, which has nothing to do with muscle attachment. It's sloppy terminology but it's everywhere outside clinical settings, and it creates confusion when you're trying to diagnose or explain an issue to someone who's already searching the internet. The practical takeaway is straightforward: sinews are tendons, they're made of tightly packed type I collagen, they transfer muscular force to bone, and they heal slowly because they're relatively avascular. If you're dealing with a suspected tendon issue, pay attention to where the pain localizes — near the bone attachment versus mid-cord versus the muscle junction — because each location implies a different mechanism and a different recovery timeline. Heavy slow loading works for most degenerative cases if you commit to the 12-week minimum, and ignoring the progression leads to worse outcomes than doing nothing at all.
Get the Full Details