Understanding Fluid Accumulation When Cancer Reaches The Liver
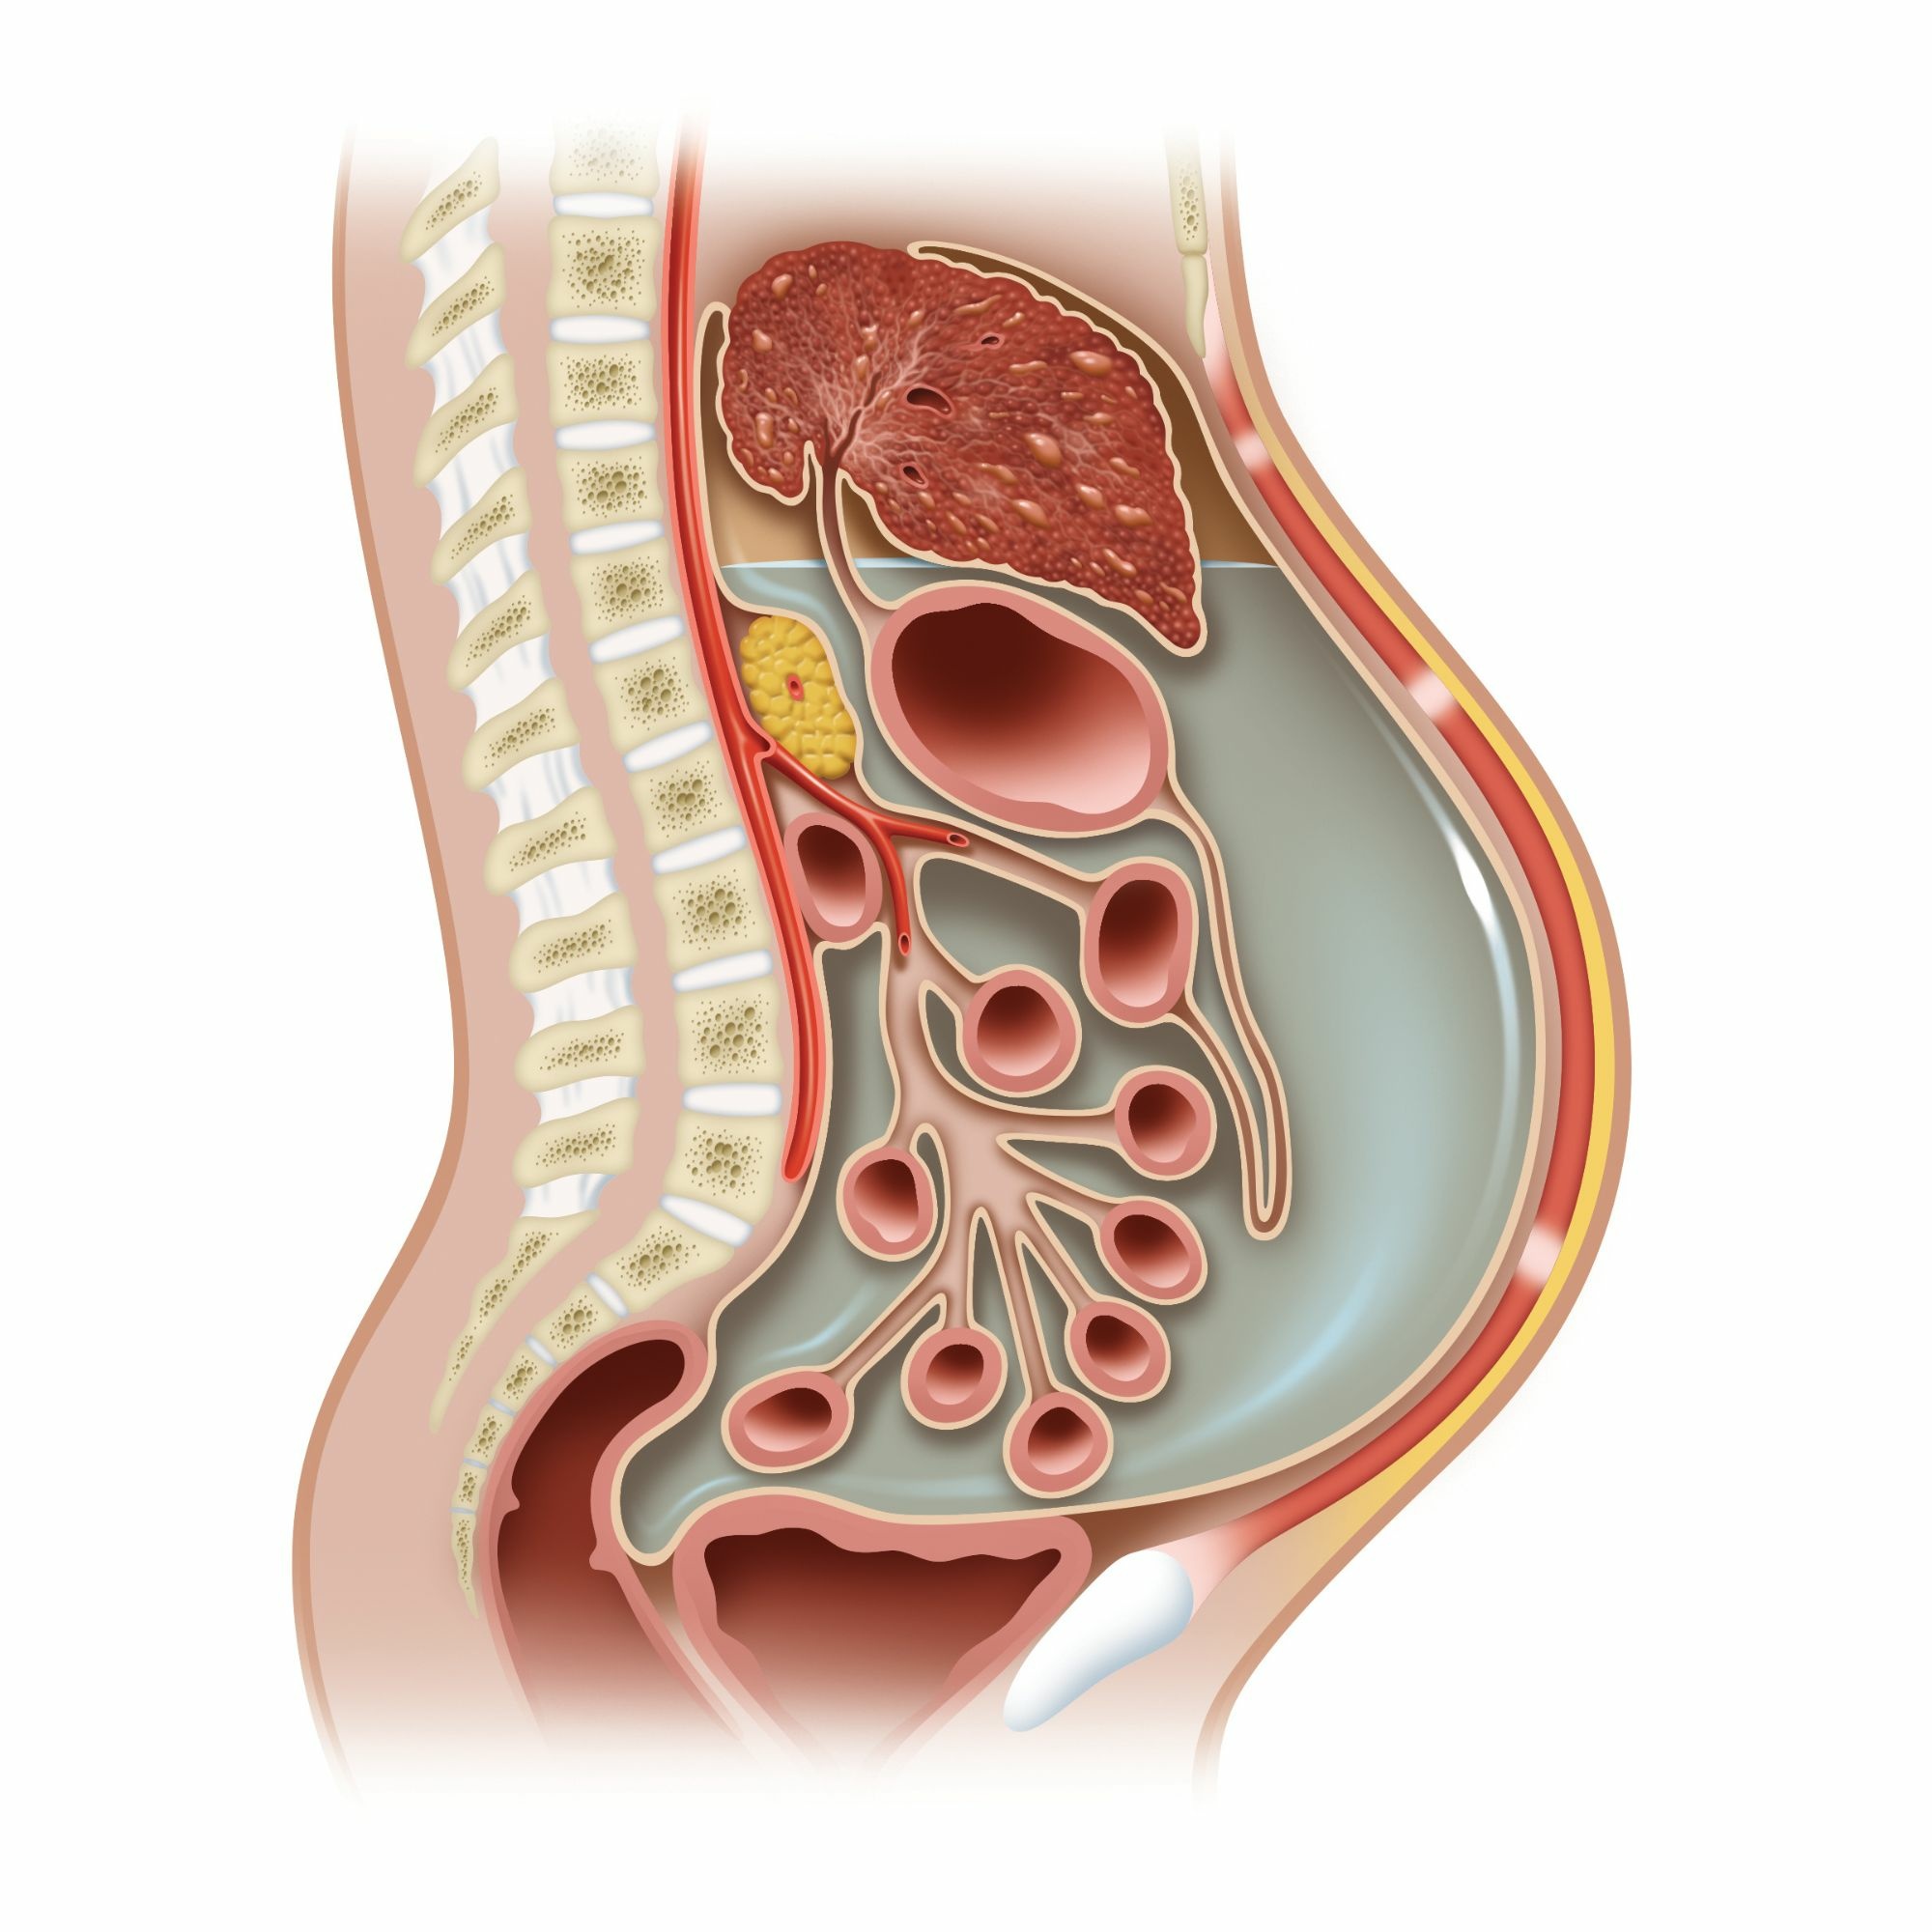
Metastatic ascites is one of those conditions where the patient looks the same on day one as they do on day three, except the abdomen is visibly larger and breathing gets shallow. I have seen this too many times across oncology wards and palliative care settings to pretend it is anything other than what it is. A serious complication of advanced malignancy, usually from ovarian, gastric, pancreatic, colorectal, or breast cancer spreading to the peritoneal lining or the liver surface itself. The fluid is not inside the liver parenchyma in most cases. It is around the liver, in the peritoneal cavity, which is an important distinction doctors sometimes gloss over when explaining it to families. The fluid buildup happens because cancer cells disrupt the normal balance of fluid production and drainage in the peritoneum. Tumor deposits on the peritoneal surface increase capillary permeability. Lymphatic drainage gets blocked. Albumin levels drop because the liver is under stress or suppressed by disease. All of this pushes protein poor fluid into the abdominal cavity. It is not a single mechanism. It is several happening at once, which is why the treatment is rarely straightforward. I remember a specific case about four years ago. A patient with known metastatic breast cancer came in with a massive tense ascites. Her albumin was 1.8. She had already been on a sodium restriction and spironolactone for two weeks with zero improvement. The ascites returned within 48 hours of a therapeutic paracentesis pulling 4.5 liters. Standard diuretics just do not work when the underlying problem is malignant obstruction of lymphatic channels. What we ended up doing was placing a tunneled peritoneal catheter. She went home with it and drained about 500 to 800 milliliters every other day. It kept her comfortable for roughly six weeks before the disease progressed further. That is the reality most people do not hear about.
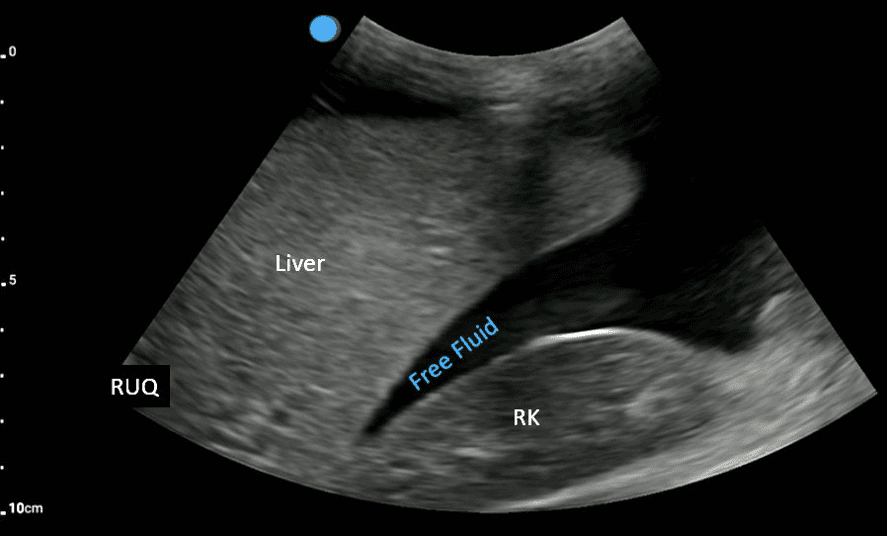
The diagnosis is usually straightforward. Imaging shows free fluid. Paracentesis confirms exudative characteristics with positive cytology in about 60 to 70 percent of cases. Sometimes you need a diagnostic laparoscopy if the fluid tap comes back negative and the imaging is unclear. CA-125, CEA, and CA 19-9 can be elevated depending on the primary tumor type, but they are not definitive on their own. The biopsy of peritoneal nodules seen on CT or MRI is what ultimately confirms the picture. Treatment options exist but each has significant limitations. Therapeutic paracentesis gives temporary relief but the fluid refills quickly. For some patients this is acceptable. For others it becomes a cycle of hospital visits that degrades quality of life fast. Intraperitoneal chemotherapy is an option in selected cases, particularly with ovarian primaries, but it is invasive and not everyone qualifies. Systemic chemotherapy depends entirely on whether the primary tumor is chemosensitive. Bevacizumab has shown some benefit in reducing ascites volume in certain trials, but it carries risks of bowel perforation and hypertension, especially in patients with liver involvement. Albumin infusions are commonly given alongside paracentesis when large volumes are removed, but the evidence that this actually prevents reaccumulation is weak. It helps with intravascular volume stability, that is about it. Indwelling pleural or peritoneal catheters are the most practical option for patients with limited life expectancy who need repeated drainage. The downside is infection risk. About 10 to 15 percent of patients develop peritonitis or cellulitis around the catheter site over time. You need clean technique and regular monitoring.
There is no cure for metastatic ascites in the traditional sense. It is a sign of advanced disease. What you can do is manage symptoms, maintain function, and have honest conversations about goals of care. The liver involvement makes things worse because it reduces the body's ability to produce albumin and process medications. Dosing of diuretics and pain medications needs adjustment. Drug clearance is slower. Small changes in dosage matter more than they would in a patient with normal liver function. If you or someone you know is dealing with this, the most useful thing is to get a clear understanding of the primary cancer type, the extent of peritoneal involvement, and what realistic outcomes look like. Second opinions matter here. Not every center has experience with tunneled catheters or intraperitoneal drug delivery. Ask about palliative care involvement early. It is not the same as hospice. Palliative care teams specialize in symptom management and can make a measurable difference in how a patient feels day to day. The truth behind metastatic ascites is not complicated but it is heavy. Fluid builds up. It causes discomfort. It signals advanced disease. Treatment focuses on drainage and comfort rather than reversal. Knowing that upfront changes how you approach the next steps.
Get the Full Details