Why Most Medical Practices Fail at Differentiation
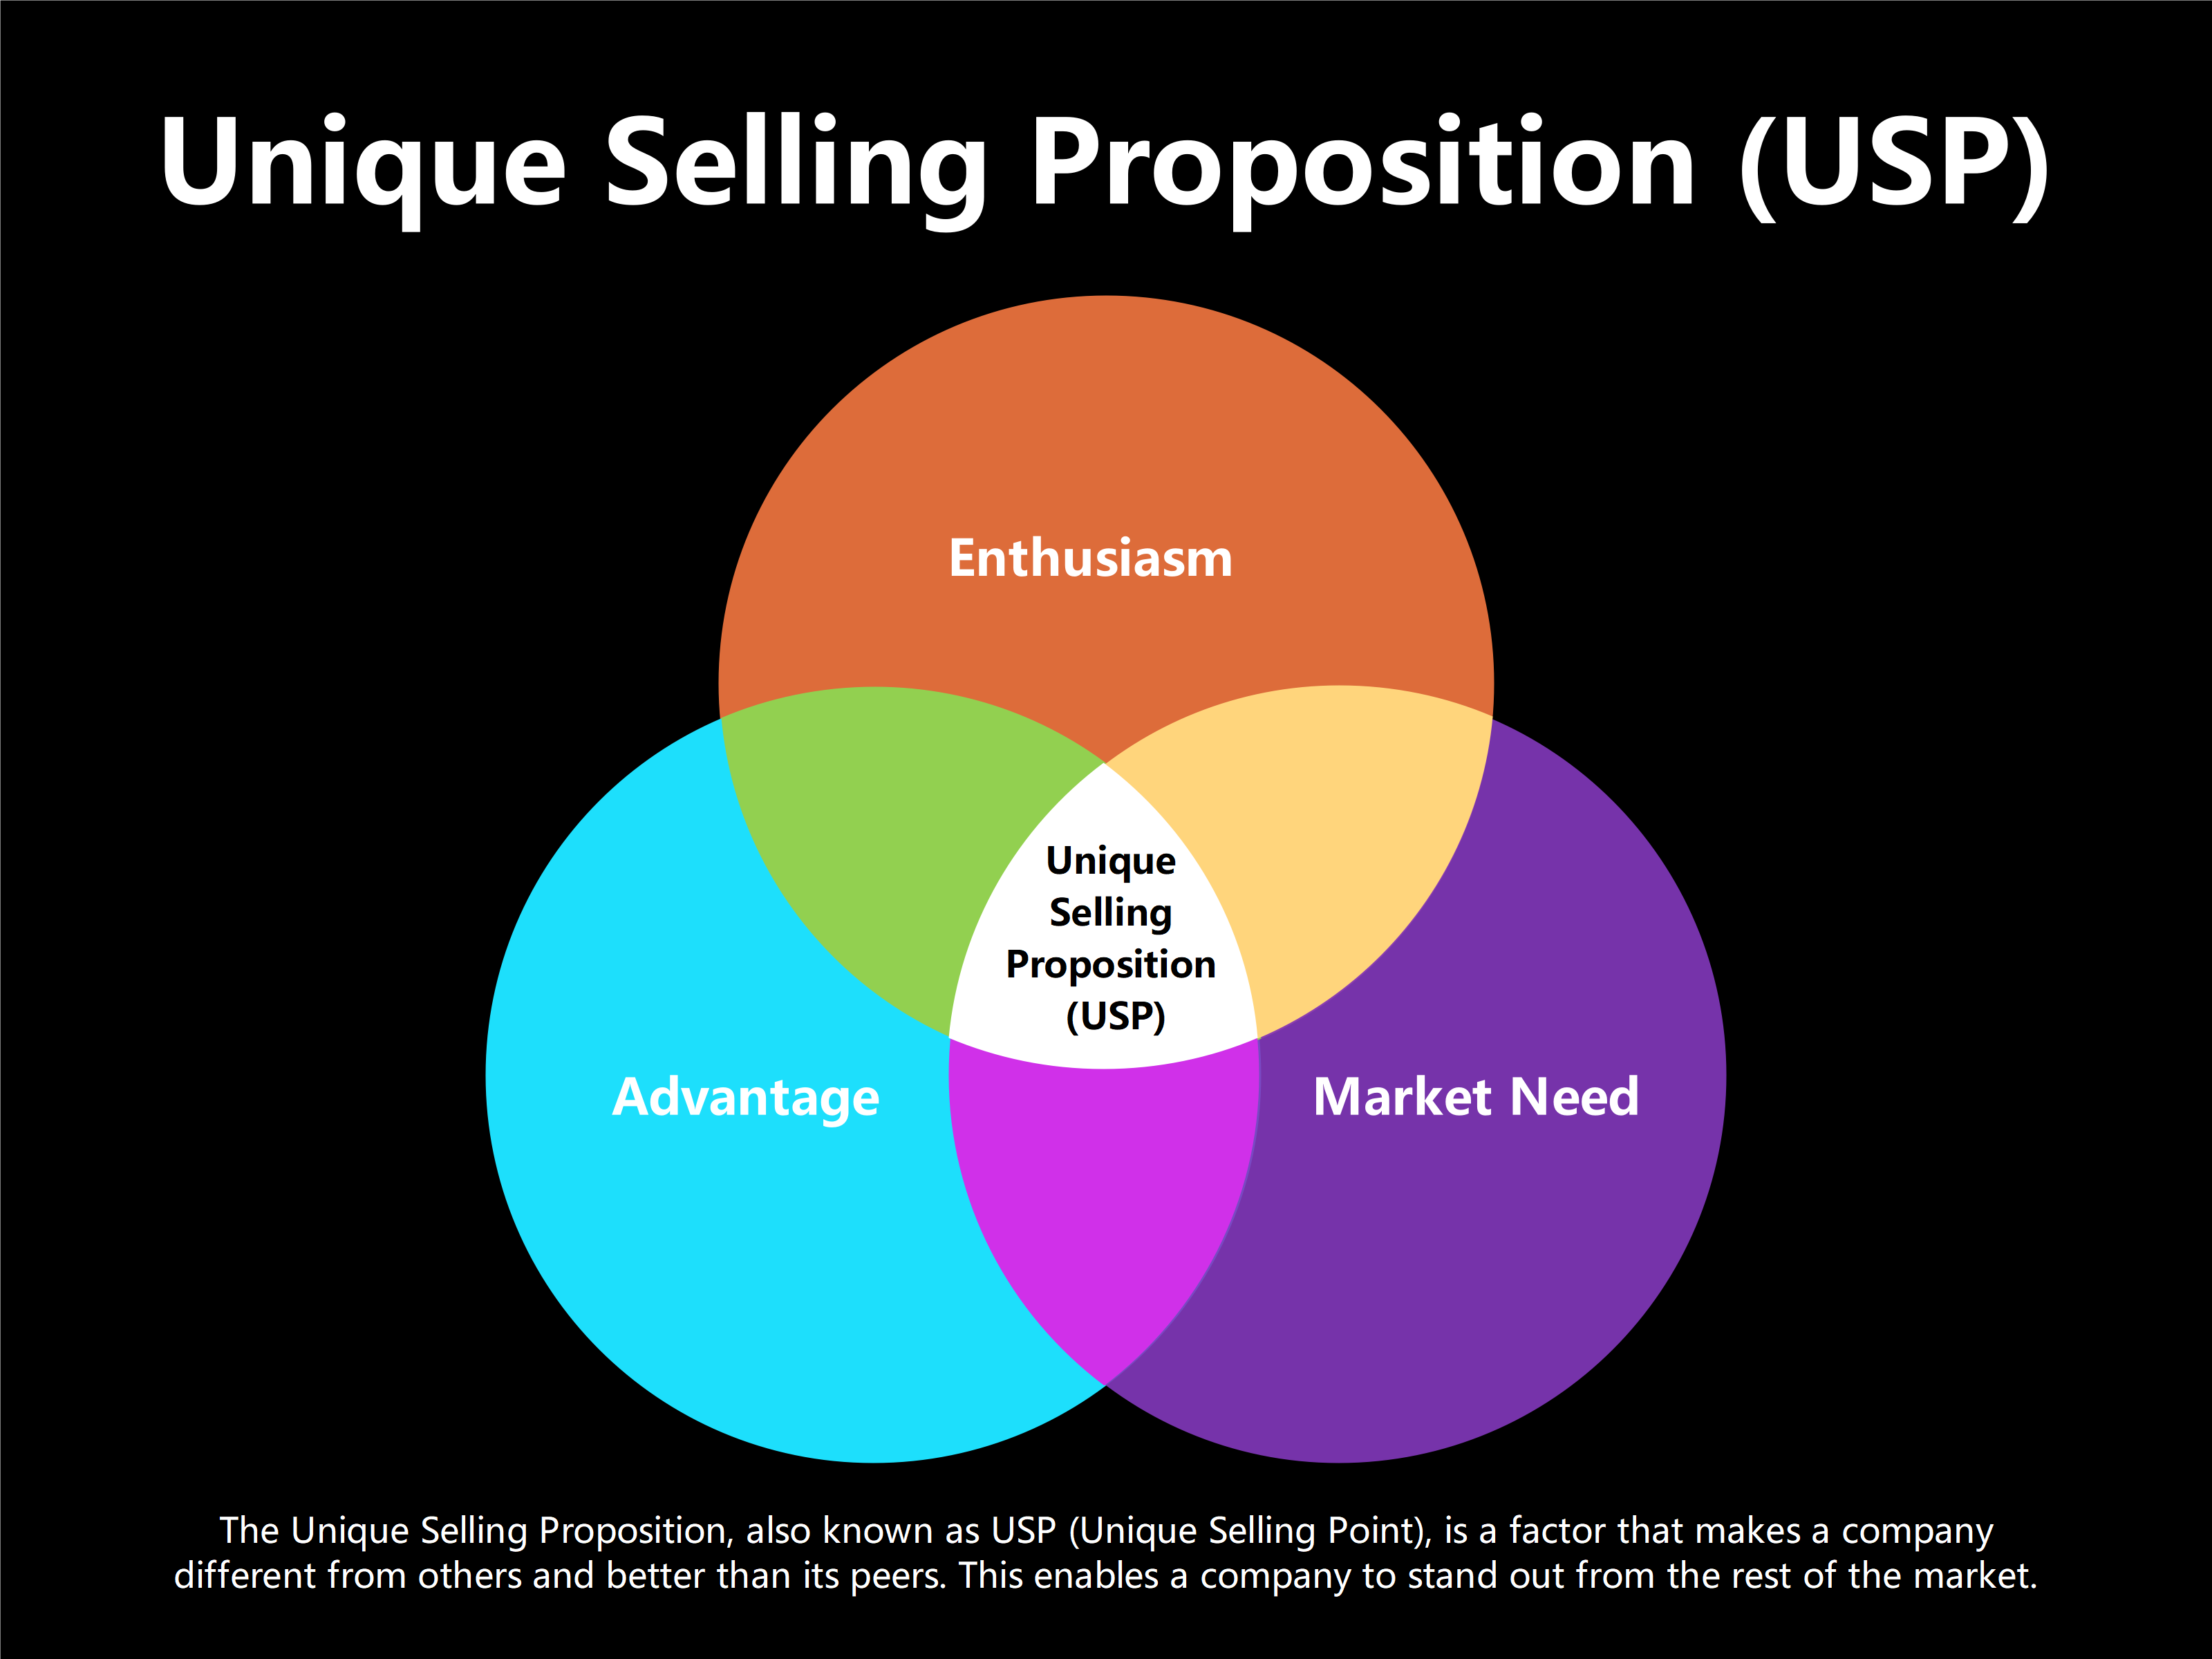
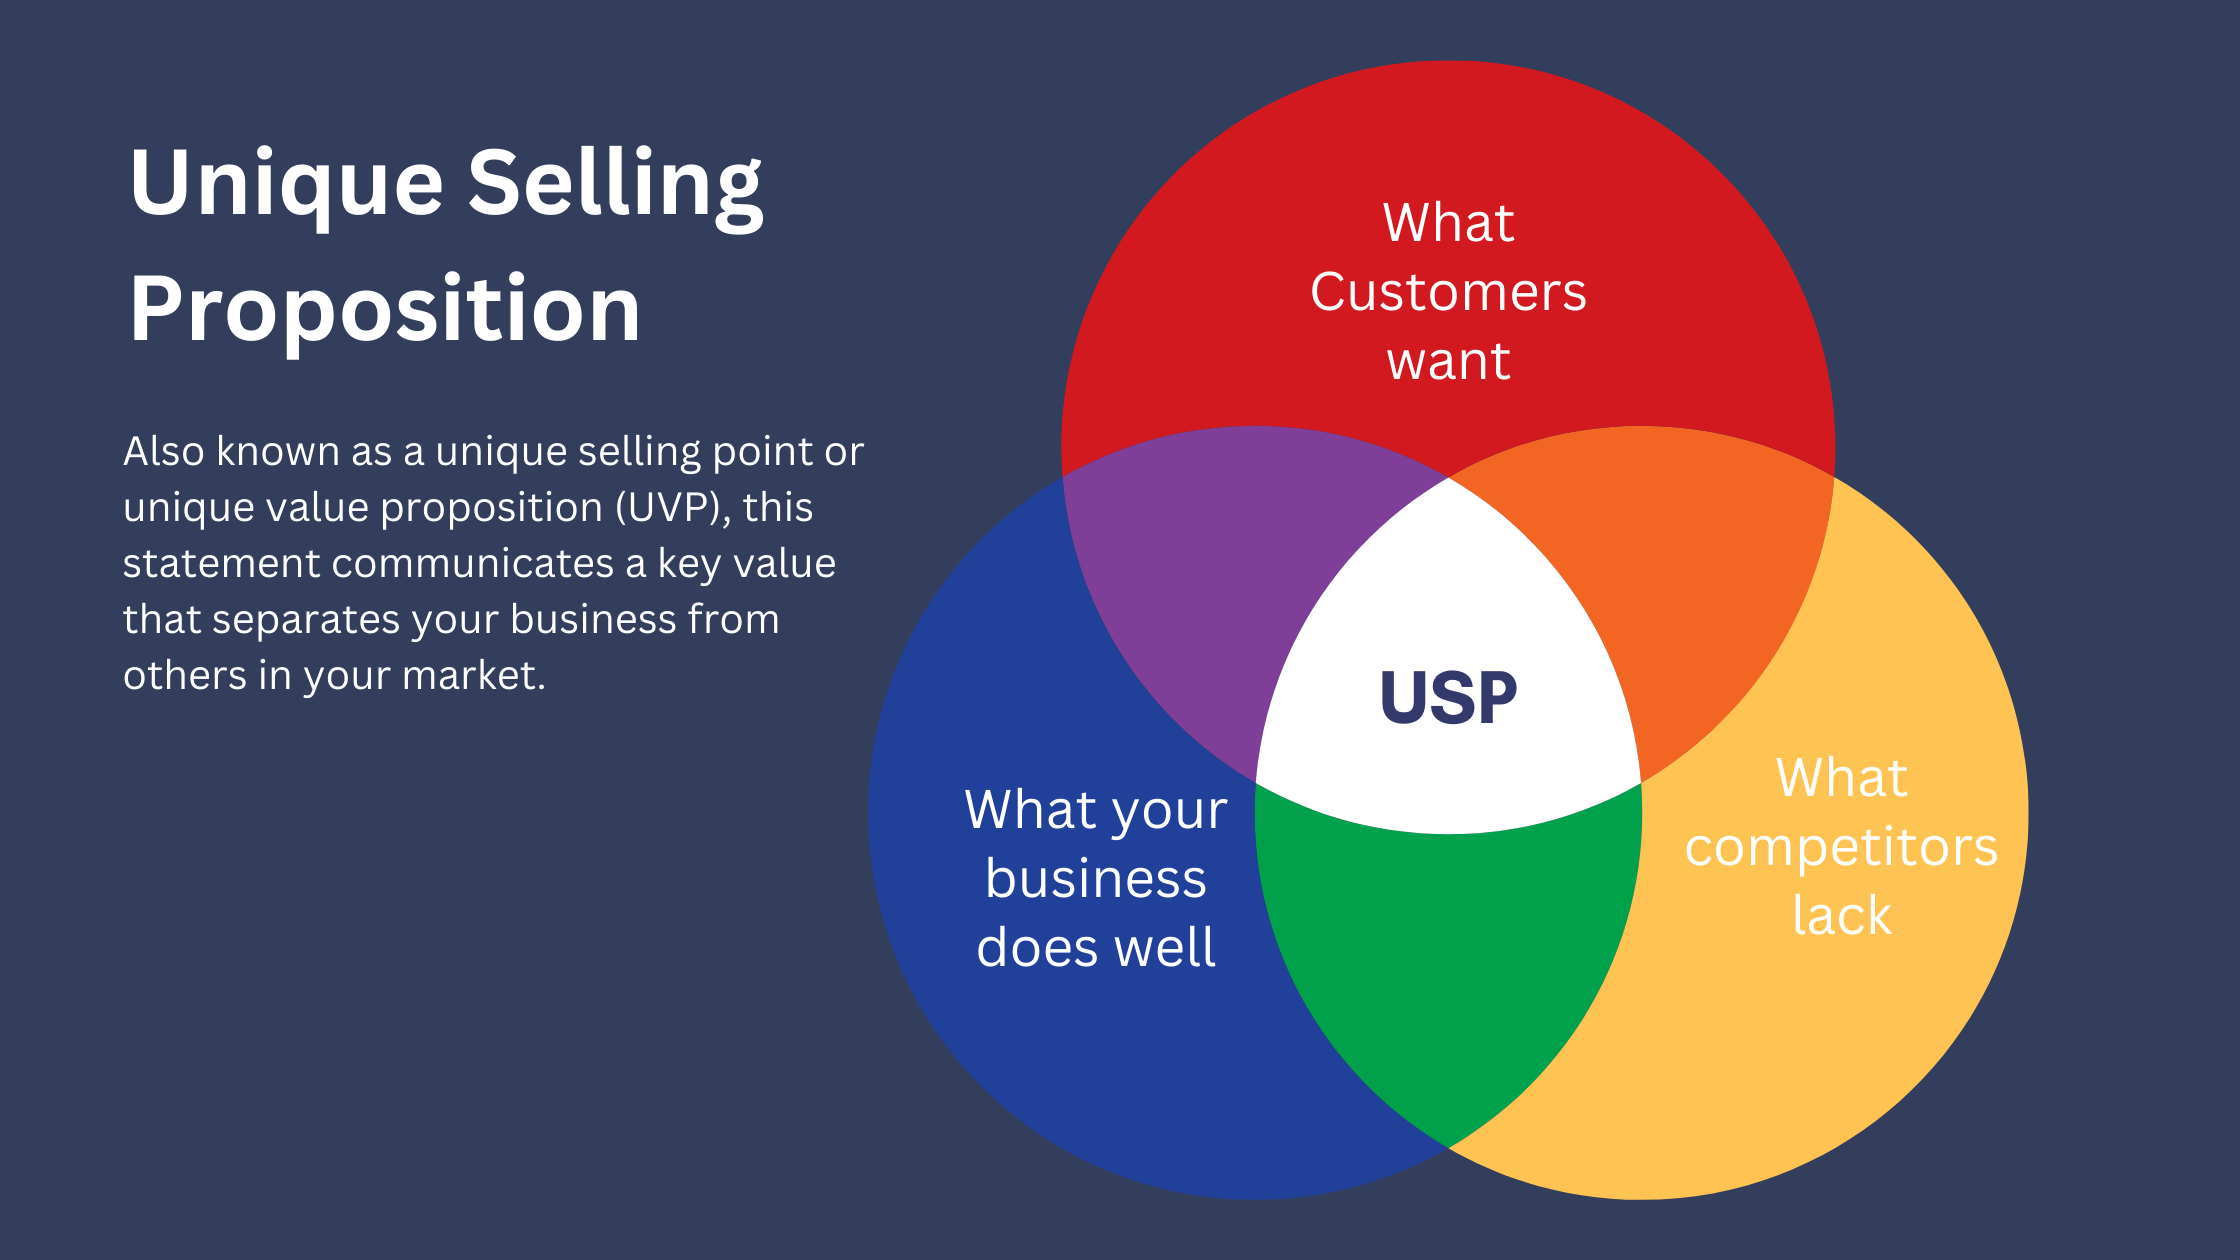
Most clinics pick a USP and hope it sticks. They write something vague on their website like "patient-centered care" or "compassionate service," then move on to whatever emergency is on fire. That approach doesn't work because every clinic says the same thing. When you strip away the marketing fluff, a real USP is a specific, provable claim that gives a patient a concrete reason to choose you over the place three miles down the road. I spent years watching practices try to compete on "quality" and "convenience" without actually delivering anything measurable. The ones that figured it out weren't the biggest or the oldest. They were the ones that picked a narrow lane and owned it completely. This is what I mean by Usp Beaumont How Unique Selling Propositions Drive Market Dominance And Patient Loyalty.
Usp Beaumont How Unique Selling Propositions Drive Market Dominance And Patient Loyalty
The concept isn't complicated but executing it cleanly in healthcare is harder than in most industries because patients don't shop for healthcare the same way they shop for restaurants. They're anxious, time-constrained, and heavily influenced by insurance networks. A USP that works for a medspa doesn't translate to a cardiology practice. You have to match the proposition to the actual decision factors your patient segment cares about. In practice, I've seen two types of USPs that actually move the needle. The first type solves a specific friction point. Examples include same-day orthopedic consultations with next-week surgery scheduling, telehealth follow-ups for chronic management that cut average wait times from four weeks to three days, or board-certified pediatricians who see appointments within twenty-four hours during illness windows. The second type anchors to a specific clinical strength. A dermatology group that publishes peer-reviewed outcomes on rosacea treatments, a pain management clinic that publishes its opioid-sparing protocol success rates, or a women's health practice that highlights perinatal outcomes data. Both approaches work. The key is picking one and not hedging. Here's the part people miss. Your USP has to be defensible. If you claim fastest wait times in the area but your front desk scheduler is understaffed and patients are waiting forty-five minutes past their appointment slot, you just made things worse. You advertised a promise you can't keep, and now you have angry patients who feel lied to. I learned this the hard way with a practice that went all-in on twenty-four-hour scheduling availability without upgrading their intake infrastructure. Patient volume spiked thirty percent in six weeks and the cancellation rate doubled because the system couldn't handle the throughput. The fix was simple but expensive: we replaced the scheduling workflow with a dedicated telehealth triage line that routed urgent cases immediately and pushed routine visits into the next open slot. Costs went up but retention numbers doubled because the promise finally matched the experience.
Another counter-intuitive detail. Your USP should ideally live somewhere a skeptic can verify it. Statistics, published outcomes, board certifications, membership in recognized networks, patient satisfaction scores that are auditable. Vague claims die fast when a patient cross-checks them. I once worked with a practice that claimed to be "the leading provider of minimally invasive spine care" but had no published outcomes, no peer citations, and no verifiable procedure volumes. Their marketing team loved it. Their patient acquisition costs were through the roof. We swapped that claim for a very specific one: "over five hundred minimally invasive spine procedures performed annually by fellowship-trained surgeons." It was less flashy and infinitely more effective. Conversion rates improved because the claim was grounded in something real. The mechanism behind patient loyalty is straightforward once you get past the buzzwords. People return to providers who reduce uncertainty. A clear USP lowers the cognitive load of choosing. When a patient already knows you specialize in something specific, the decision becomes simpler. They don't weigh ten generic clinics against each other. They pick the one that matches their problem. This is why narrow USPs outperform broad ones even though instinct pushes you toward the opposite. There are real limitations to this approach that nobody talks about enough. A USP locks you in. If you commit to being the fastest orthopedic consultation provider, you can't casually expand into general family practice without confusing the signal. You also become dependent on consistently delivering on that promise, which means operational discipline becomes as important as marketing. Small practices sometimes find that adopting a USP requires structural changes they aren't ready to make. In those cases, the alternative is focusing on relationship-based loyalty instead, which builds slower but doesn't demand the same operational rigor.
Get the Full Details

If you're building a USP for a medical practice, start with a constraint. What can you actually deliver better than anyone nearby? Not what sounds good on paper but what your current staff, schedule, and budget can sustain. Then write it as a single verifiable sentence. Test it by asking whether a skeptical patient could fact-check it in under five minutes. If the answer is no, rewrite it.