
US Average Height: A Practical Breakdown for Anyone Actually Trying to Use the Data
The US average height sits at roughly 5'9" for men and 5'4" for women, but that single number is about as useful as a weather report that only says "precipitation possible." The real story is in how those numbers shift across regions, cohorts, and demographics, and it matters if you are designing anything from clothing sizing to public health policy. Here is what most people miss when they look at height data. The US has actually plateaued. For much of the 20th century, Americans got noticeably taller, gaining about an inch per generation or so. That stopped around the 1980s for men and slightly earlier for women. We are not getting taller anymore. We are getting heavier, and the data shows it clearly if you dig past the CDC press releases. The NHANES cycles from 1960 through 2020 give us the most reliable tracking. Men born in 1960 averaged about 5'9". Men born in 1990 averaged essentially the same. The plateau is real. What changed was body composition. The obesity epidemic hit in the 1980s and never slowed down. Average BMI rose while average height flatlined. So you get this weird cultural moment where people assume Americans are getting taller because we are visibly larger, but the scale tells a different story. We are wider, not taller.
Regionally, there are measurable differences. The Northeast tends to run slightly taller than the South, and the Midwest sits somewhere in between. These differences are small, usually under an inch, but they show up consistently across surveys. I have seen people treat these regional gaps as evidence of something dramatic, but the effect size is modest. The bigger story is the urban versus rural split. Rural populations tend to be slightly taller on average, which surprises people who associate rural areas with less access to healthcare or nutrition. It tracks more with occupational differences and population density than anything else. When I was working on a project a few years back that involved designing ergonomic equipment for a national workplace safety study, I ran into a real problem. The standard anthropometric tables from the 1990s were still being cited everywhere. They were outdated by at least two decades. Using them meant the percentile cuts were wrong, and the equipment specs were off by an inch or two at the extremes. That sounds small until you are dealing with adjustability ranges for industrial machinery. My workaround was pulling the latest NHANES data and running custom percentile calculations based on age-cohort breakdowns rather than just the overall average. It added a few hours to the project but saved us from having to redesign half the equipment later. The lesson is simple: do not trust published averages without checking the source date and population definition.
Regional Variation in More Detail
The Northeast corridor, particularly states like New York and Massachusetts, shows slightly higher average heights, partly due to demographic composition and partly due to socioeconomic factors. Immigration patterns matter here too. Populations with longer histories of nutritional adequacy tend to reach their genetic height potential more fully. That does not mean some regions are genetically superior. It means childhood nutrition and health access vary, and those factors compound over generations. The South has a complex picture. Some Southern states show slightly below-average heights, but the gap is narrowing. Economic development in the latter part of the 20th century improved nutrition and healthcare access across the region. The CDC data from 2010 onward shows that regional convergence is happening, though slowly. You will still find variation, but it is smaller than it was thirty years ago. The West is where things get interesting for anthropometric work. California and the coastal states have very diverse populations, which makes averaging tricky. An overall state average can mask huge subgroup differences. I learned this the hard way when a client wanted me to use California's average height for a product design spec without considering that the state has among the highest proportions of Asian and Hispanic residents in the country. Those populations have different average heights than the non-Hispanic white population. Using the bare state average led to fit issues that cost us a rework cycle. The fix was breaking the data down by demographic cohort before designing anything.
Get the Full Details
Global Context: Where the US Actually Stands
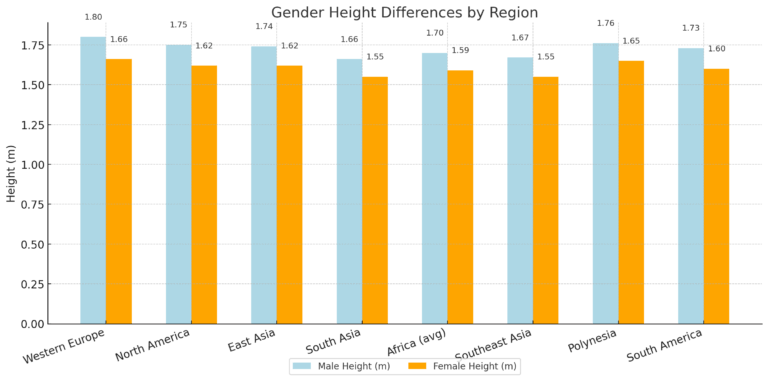
Americans are not particularly tall by global standards. The Netherlands consistently tops the charts with men averaging around 6'0" and women around 5'7". Scandinavian countries, Germany, and several Eastern European nations also surpass the US. Brazil, despite being a large country with significant population diversity, has closed the gap considerably. In the 1970s, Brazilian men averaged closer to 5'6", but recent data puts them near 5'8", nearly matching American males. The global picture reveals something counterintuitive. Several countries that were once considered developing now have average heights equal to or greater than the US. This is not because their genetics changed. It is because childhood nutrition, healthcare, and living standards improved dramatically over the past fifty years. Height is one of the most reliable indicators of population-level development. When a country invests in nutrition and public health, average height rises within a generation or two. The US ranking has slipped partly because other countries improved faster while America plateaued. We are still above the global average, but the gap has narrowed significantly since 1990. For reference, the global average male height is approximately 5'7.5", so American men are about an inch above that. American women at 5'4" are slightly above the global female average of roughly 5'3". These are small margins that get blown out of proportion in casual conversation.
How to Use This Data Without Messing It Up
If you are using average height data for any practical purpose, start by understanding what question you are actually trying to answer. The average is almost never the right number. Percentiles matter more. If you are designing for a range, use the 5th and 95th percentiles, not the mean. The spread tells you more about real-world variability than the center point ever will. Age matters enormously. A 25-year-old and a 75-year-old man in the same height percentile may have very different life experiences and health profiles. When I pulled age-stratified NHANES data for a medical device project, the height difference between the youngest and oldest cohorts was about half an inch for men. Small on paper. Critical when you are designing something that needs to fit every age group in a clinical setting. Sex differences within datasets are another common source of error. Many published tables still report male and female data separately without clearly labeling which is which. I have encountered specifications sheets that listed "average adult height 5'9"" without any sex distinction, and someone on a project team used it for a product meant to accommodate the full population. That product was too large for about half the intended users. Always verify the demographic breakdown in whatever dataset you are pulling from.
There are legitimate limitations to the data you should know about. Self-reported height data is unreliable. People overreport by about half an inch on average, and the bias is stronger among overweight individuals and older adults. Always prefer measured data from surveys like NHANES over anything collected through self-report. Sample size matters too. National averages smooth over local variation that might be relevant to your specific use case. If you are designing for a particular city or demographic group, look for localized studies even if they are less comprehensive.
Where the Data Falls Short
The biggest gap in available height data is longitudinal tracking of younger cohorts. NHANES provides cross-sectional snapshots, meaning each cycle surveys different people at different ages. You can infer trends by comparing different birth cohorts, but you cannot track the same individuals over time. For understanding how specific policy changes or nutrition interventions affect height in real time, this is a meaningful limitation. Longitudinal studies exist but are expensive and small-scale. Another blind spot is the lack of detailed geographic granularity below the state level. County-level data is virtually nonexistent for height. If you need hyperlocal information, you are mostly on your own. Some academic papers have pushed toward smaller geographic units, but they are not consistently updated and coverage is spotty. The most important thing to remember is that average height is a population statistic, not an individual predictor. Two people who are both exactly average height can have completely different body proportions, leg-to-torso ratios, and postural characteristics that make them functionally very different. If your application requires precision beyond general sizing, you need more detailed anthropometric data than a simple average can provide. There are specialized databases like the ANSUR studies that break down body measurements far more thoroughly, but they require a legitimate research or commercial purpose to access.


