Understanding Well Corticated Ossicles in Medical Imaging
Unveiling The Well Corticated Ossicle Meaning Features And More
A well corticated ossicle is a small, separate bone fragment visible on imaging that has a smooth, well-defined cortical margin. This is different from a non-corticated fragment, which tends to look irregular and frayed. When a radiologist reports "well corticated," they're describing a specific appearance that carries important clinical meaning. The key distinction lies in the margin. A corticated border means the edge of the ossicle is lined by a thin, dense layer of cortical bone. On X-ray, this shows up as a bright, sharp outline. On CT, you can measure the density and see it matches normal cortical bone. On MRI, the cortex appears dark on all sequences, just like it should. This is a feature of slow growth and chronicity, not an acute process. I've seen this term come up most often in the foot and ankle, specifically around the os trigonum and the accessory navicular. These are the two locations where I've encountered well corticated ossicles repeatedly. The os trigonum sits behind the ankle joint, and when it's well corticated, it's almost always a developmental variant rather than a fracture fragment. A fracture fragment would show irregular edges, surrounding bone marrow edema on MRI, and possibly soft tissue swelling. A well corticated ossicle shows none of that. It just sits there, looking completely benign.
Here's where beginners in radiology or orthopedics tend to make mistakes. They see a second bone fragment and immediately assume it's a fracture. The cortication status is the single most important feature to evaluate first. If it's well corticated, you're dealing with an accessory bone or an old healed fragment. If it's irregular and poorly defined, you need to think about acute injury. I once had a resident flag a well corticated os trigonum as a suspected posterior ankle fracture. We spent twenty minutes comparing pre-injury sports X-rays from two years prior, which clearly showed the same ossicle. The patient had chronic posterior ankle pain from impingement, not an acute fracture. That confusion could have been avoided by simply pausing to assess the margin first. Let me walk through the practical evaluation process. When you encounter a suspected ossicle on any imaging modality, start by examining the margin in multiple planes. On X-ray, look at both the AP and lateral views. On CT, scroll through the axial slices and check the reformatted coronal and sagittal images. On MRI, look at the T1-weighted images first since they show bone anatomy clearly. The corticated margin should appear as a thin, continuous hypointense line surrounding the ossicle. If that line is interrupted or absent, the lesion may not be a benign ossicle. The size matters too. Well corticated ossicles tend to be stable in size over time. I've followed patients with os trigonum syndrome where the ossicle measured 8mm on one study and 8mm on a repeat study three years later. If you see an ossicle that's enlarging, that should raise flags regardless of how well corticated it appears. Growth suggests an active process.
Now, the tricky part is distinguishing a well corticated ossicle from other things that can mimic it. A subchondral cyst can sometimes appear rounded and well-defined on plain X-ray. The difference is that a cyst lacks internal bony trabeculation. On CT, a cyst will have fluid density inside, while an ossicle has bone density. On MRI, a cyst follows fluid signal on T2-weighted images, while an ossicle follows bone marrow or cortical signal depending on its composition. Osteochondral fragments from old fractures can also appear well corticated if they've been present long enough. This is called a loose body when it detaches completely. The differentiation from a true accessory ossicle comes down to location and clinical history. An accessory ossicle sits in a predictable anatomical location—an os trigonum is always posterior to the talus, an accessory navicular is always medial to the navicular. A loose body can migrate anywhere within the joint space. If you find a well-defined bony fragment in an unexpected location, especially in a patient with a history of trauma or joint instability, consider a loose osteochondral fragment rather than an accessory bone. Another common pitfall involves the fabella. This is a small ossicle behind the lateral femoral condyle that's present in roughly 10-30% of the population. It's usually well corticated and asymptomatic. But I've seen several cases where a fabella was mistaken for a loose body or a lateral femoral condyle fracture fragment because the reporting clinician wasn't familiar with its typical appearance. The fabella is bilateral in many cases, articulates with the femoral condyle, and has a consistent shape. Those features distinguish it from pathological fragments.
Get the Full Details

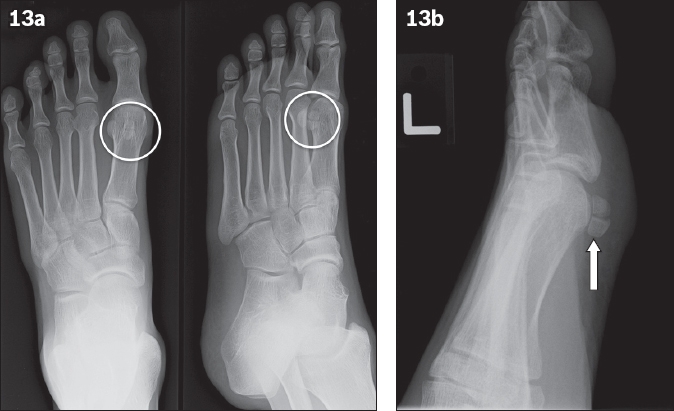
When I'm evaluating a well corticated ossicle, I also pay attention to the surrounding structures. Is there joint effusion? Is there bone marrow edema in the adjacent bone? Is there synovitis or soft tissue thickening? In a purely incidental, asymptomatic ossicle, all of these should be absent. If there's edema around the ossicle, even with a well corticated margin, you're dealing with something active. In the case of the os trigonum, bone marrow edema in both the ossicle and the adjacent talus on STIR sequences indicates os trigonum syndrome—the ossicle is being pinched during ankle plantarflexion. The cortication tells you it's not an acute fracture. The edema tells you it's currently symptomatic. The management implications are significant and directly tied to what you see on imaging. A well corticated ossicle without surrounding edema or symptoms typically requires no intervention. I've had patients who were told they needed surgery for an "ankle fracture" when it was actually just an incidental os trigonum. That's unnecessary. Conservative management, activity modification, and sometimes a single corticosteroid injection are the appropriate steps for a symptomatic but well corticated ossicle. Surgery is reserved for cases that fail conservative treatment after a reasonable trial period, generally three to six months. One limitation I want to flag clearly: plain X-ray can miss the cortication detail. On a single view or a poor-quality radiograph, both corticated and non-corticated fragments can look similar. That's why CT is the gold standard for characterizing an ossicle's margin. If the X-ray is equivocal and the clinical picture doesn't match, get a CT. I once evaluated a patient whose X-ray showed what looked like a small fracture fragment at the base of the fifth metatarsal. The CT revealed a well corticated Os Vesalianum, a rare accessory bone. The patient had been referred for possible surgical fixation of a Jones fracture that didn't exist. Proper imaging characterization prevented unnecessary surgery.
Similarly, ultrasound can be useful in specific scenarios. It can dynamically demonstrate an ossicle being impinged between bones during joint movement. This is particularly relevant for the os trigonum, where impingement only occurs in plantarflexion. A static CT scan might show a perfectly benign-appearing well corticated ossicle, but ultrasound during active plantarflexion can reveal the mechanical impingement that explains the patient's symptoms. It's an underutilized tool for this purpose.