What Actually Happens When You Have RLS Combined With Rhythmic Movement Disorder
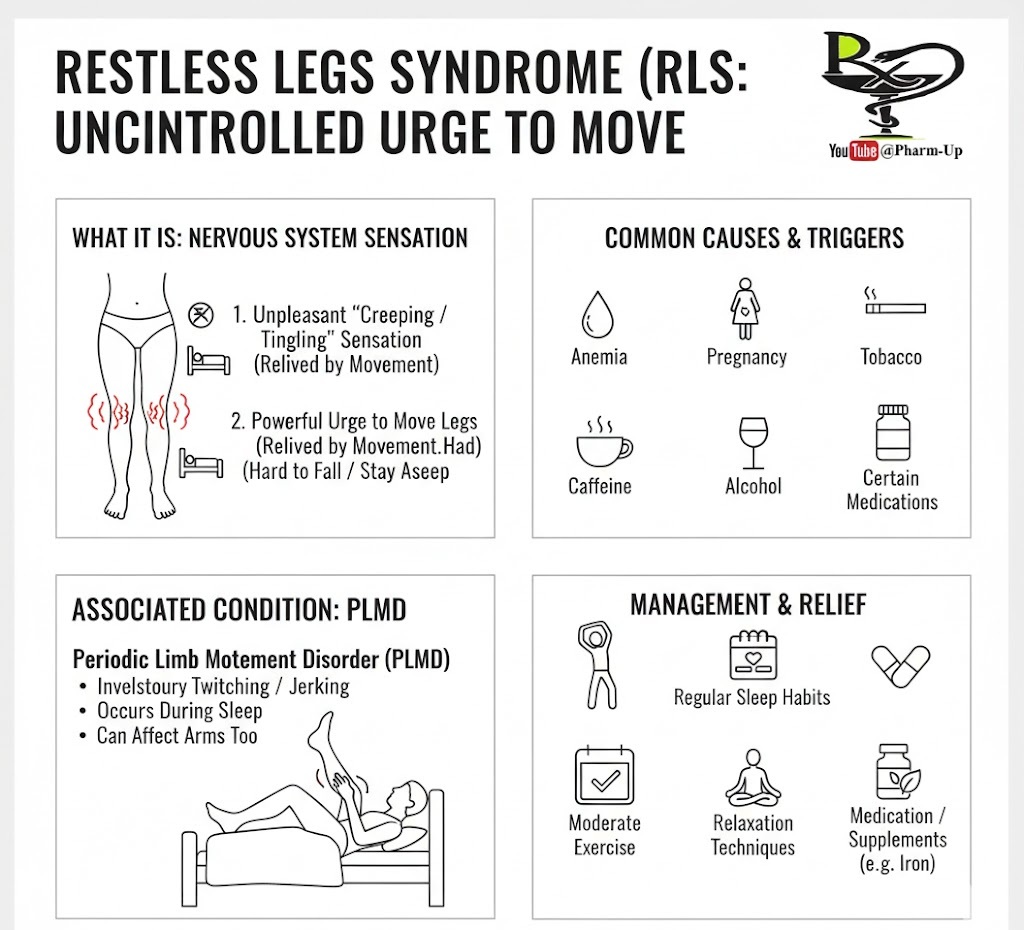
I've been dealing with both restless legs syndrome and rhythmic movement disorder for years now. What most people don't realize is that having one doesn't just come with the symptoms of the other — they interact in ways that make sleep logistics genuinely complicated. Rhythmic movement disorder involves repetitive, stereotyped movements before falling asleep or during the night. Head banging, body rocking, leg rolling — these aren't voluntary. When you add RLS into the mix, the urge to move your legs constantly conflicts with the involuntary movement patterns your brain is already producing. It sounds like it should be exhausting. It is. Most sources treat RLS and Rhythmic Movement Disorder (RMD) as separate conditions, which they technically are. But the overlap in real life matters more than the diagnostic separation. RLS creates an uncomfortable urge to move, usually in the legs, with symptoms worsening in the evening or at night. RMD produces the actual physical movements — head banging, body rocking, grinding teeth — during sleep transitions or throughout the night. When someone has both, the RLS urge can trigger or worsen the rhythmic movements, and the movements don't reliably stop once RLS medication kicks in because they're driven by different neurological pathways. The iron connection is where things get interesting. RLS is strongly linked to low ferritin in the brain, and the standard threshold for starting treatment is a serum ferritin level below 75 micrograms per liter. Most general practitioners won't even check ferritin unless you're anemic. I had mine checked because my movement symptoms weren't responding to first-line dopaminergic treatments. My ferritin was at 28. Oral iron supplements got it to about 50 over six months and did nothing for the RLS. Intravenous iron therapy pushed it above 200 and reduced the RLS severity by maybe 60 percent. The rhythmic movements stayed mostly the same. That told me something important — two different mechanisms at work.
Diagnosis usually starts with a sleep study, specifically a polysomnography with video monitoring. The RLS diagnosis itself is clinical — four criteria from the International Restless Legs Syndrome Study Group. You need an urge to move accompanied by discomfort, worsening at rest, partial or total relief with movement, and worsening in the evening. The RMD diagnosis requires the repetitive movements themselves, documented during sleep, causing either significant distress or actual physical injury. Not everyone with RMD hurts themselves. Most don't. But the disruption to sleep architecture is real regardless. Here's a practical detail most guides skip: rigid sleep positioning can actually reduce RMD severity in some cases. I use a firm pillow against the headboard and a weighted blanket that's about 15 percent of my body weight. The pressure from the blanket seems to dampen the intensity of the rhythmic movements without suppressing them entirely. That's important because completely stopping the movements would likely trigger worse RLS rebound. It's a balancing act, not a cure.
Treatment Approaches That Actually Work
Dopaminergic agents like pramipexole and ropinirole are the standard first-line treatment for RLS, but they come with a well-documented problem called augmentation. Augmentation means the medication makes your symptoms worse over time — the sensations start earlier in the day, spread to other body parts, or become more intense despite staying on the same dose. I've seen people on pramipexole for three years end up with symptoms starting at 3 PM and requiring double or triple the original dose. It's not uncommon. Alpha-2-delta ligands have largely replaced dopaminergic agents as first-line treatment in current guidelines. Gabapentin enacarbil is FDA-approved specifically for RLS. Pregabalin and gabapentin are used off-label and work well for many people. The mechanism is different — they modulate calcium channels rather than affecting dopamine — so augmentation risk is significantly lower. The tradeoff is dizziness and daytime drowsiness, which can be problematic if you need to function during the day. I take gabapentin enacarbil at 7 PM and it keeps the RLS at bay until about 3 AM, after which the coverage drops off and I sometimes need a small rescue dose. For RMD specifically, there's less evidence-based treatment because it's rarer and often underreported. Clonazepam, a benzodiazepine, is sometimes prescribed and can reduce the intensity of the movements. The downside is tolerance buildup and next-day sedation. Muscle relaxants like cyclobenzaprine have been tried with mixed results. Protecting yourself from injury is the more immediate concern — padded headboards, foam bedding near the bed, avoiding hard surfaces within reach of your movements during sleep transitions.
Get the Full Details
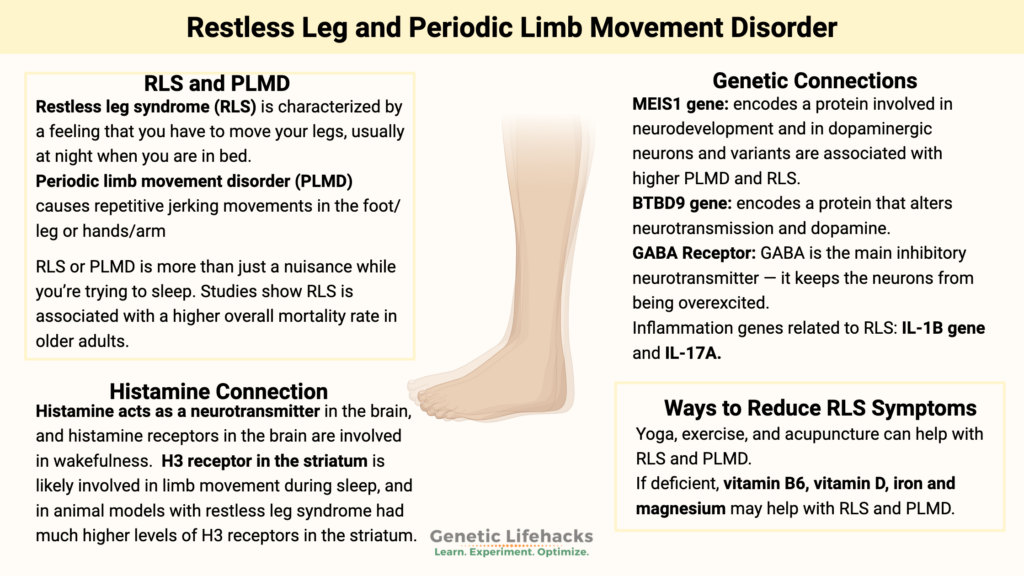
Iron supplementation deserves more attention than it gets. If your ferritin is below 75, oral iron should be your starting point. Ferric maltol or iron sucrose IV are options if oral isn't tolerated or absorbed properly. I check my ferritin every four months. The target for RLS management is at least 100, ideally 150 or above. Once you get there and stay there, the RLS symptoms tend to stabilize. This isn't a permanent fix — ferritin levels drift, especially if you're not supplementing consistently — but it's the single most effective intervention I've found for long-term management.
What Nobody Tells You About Living With Both
Daytime sleepiness is unavoidable if your sleep is fragmented by both conditions. I measure my resting heart rate variability and sleep stages using a wearable tracker. On nights when the RMD is active and RLS is uncontrolled, I typically get less than four hours of actual deep sleep. The RLS pulls you out of deep sleep with leg discomfort, and the RMD movements prevent you from settling into sustained restful sleep. CPAP machines for sleep apnea — which is comorbid in a significant number of RLS patients — can sometimes worsen RLS symptoms due to the mask and airflow irritation, creating another layer of complexity. Exercise helps RLS but can worsen RMD if done too close to bedtime. I learned this the hard way. A heavy leg day at 6 PM followed by an already compromised evening routine meant I was moving for hours after trying to fall asleep. Now I do any intense exercise before 3 PM and stick to gentle stretching or walking in the late afternoon. The difference is noticeable. Caffeine is another hidden exacerbator. Half of RLS patients report clear caffeine sensitivity. It doesn't have to be a lot — one coffee after 2 PM is enough to push my symptoms into uncomfortable territory. Alcohol has a similar effect, though the mechanism is different. It suppresses REM sleep initially but causes rebound arousal later in the night, which intersects badly with both RLS and RMD cycles.
The psychological toll is real but rarely discussed in medical literature. The chronic sleep disruption leads to irritability, difficulty concentrating, and what I'd describe as a persistent low-grade anxiety about when the next episode will hit. Cognitive behavioral therapy for insomnia (CBT-I) helped me manage the anxiety around sleep rather than eliminate the physical symptoms. It's an adjunct, not a replacement for medical treatment, but it changed my relationship with the whole situation in a practical way. If you're newly diagnosed or suspect you have both conditions, start by requesting a ferritin test from your doctor. Ask specifically for it — don't wait for them to order it as part of a standard panel. Then find a sleep specialist who takes RLS seriously rather than dismissing it as "just restless legs." The treatment landscape has shifted considerably in the last five years, and many clinicians are still operating on older protocols centered on dopamine agonists. A knowledgeable specialist will start with iron assessment and alpha-2-delta ligands, reserving dopaminergics for refractory cases.