Understanding BMI Visualizers and What They Actually Do
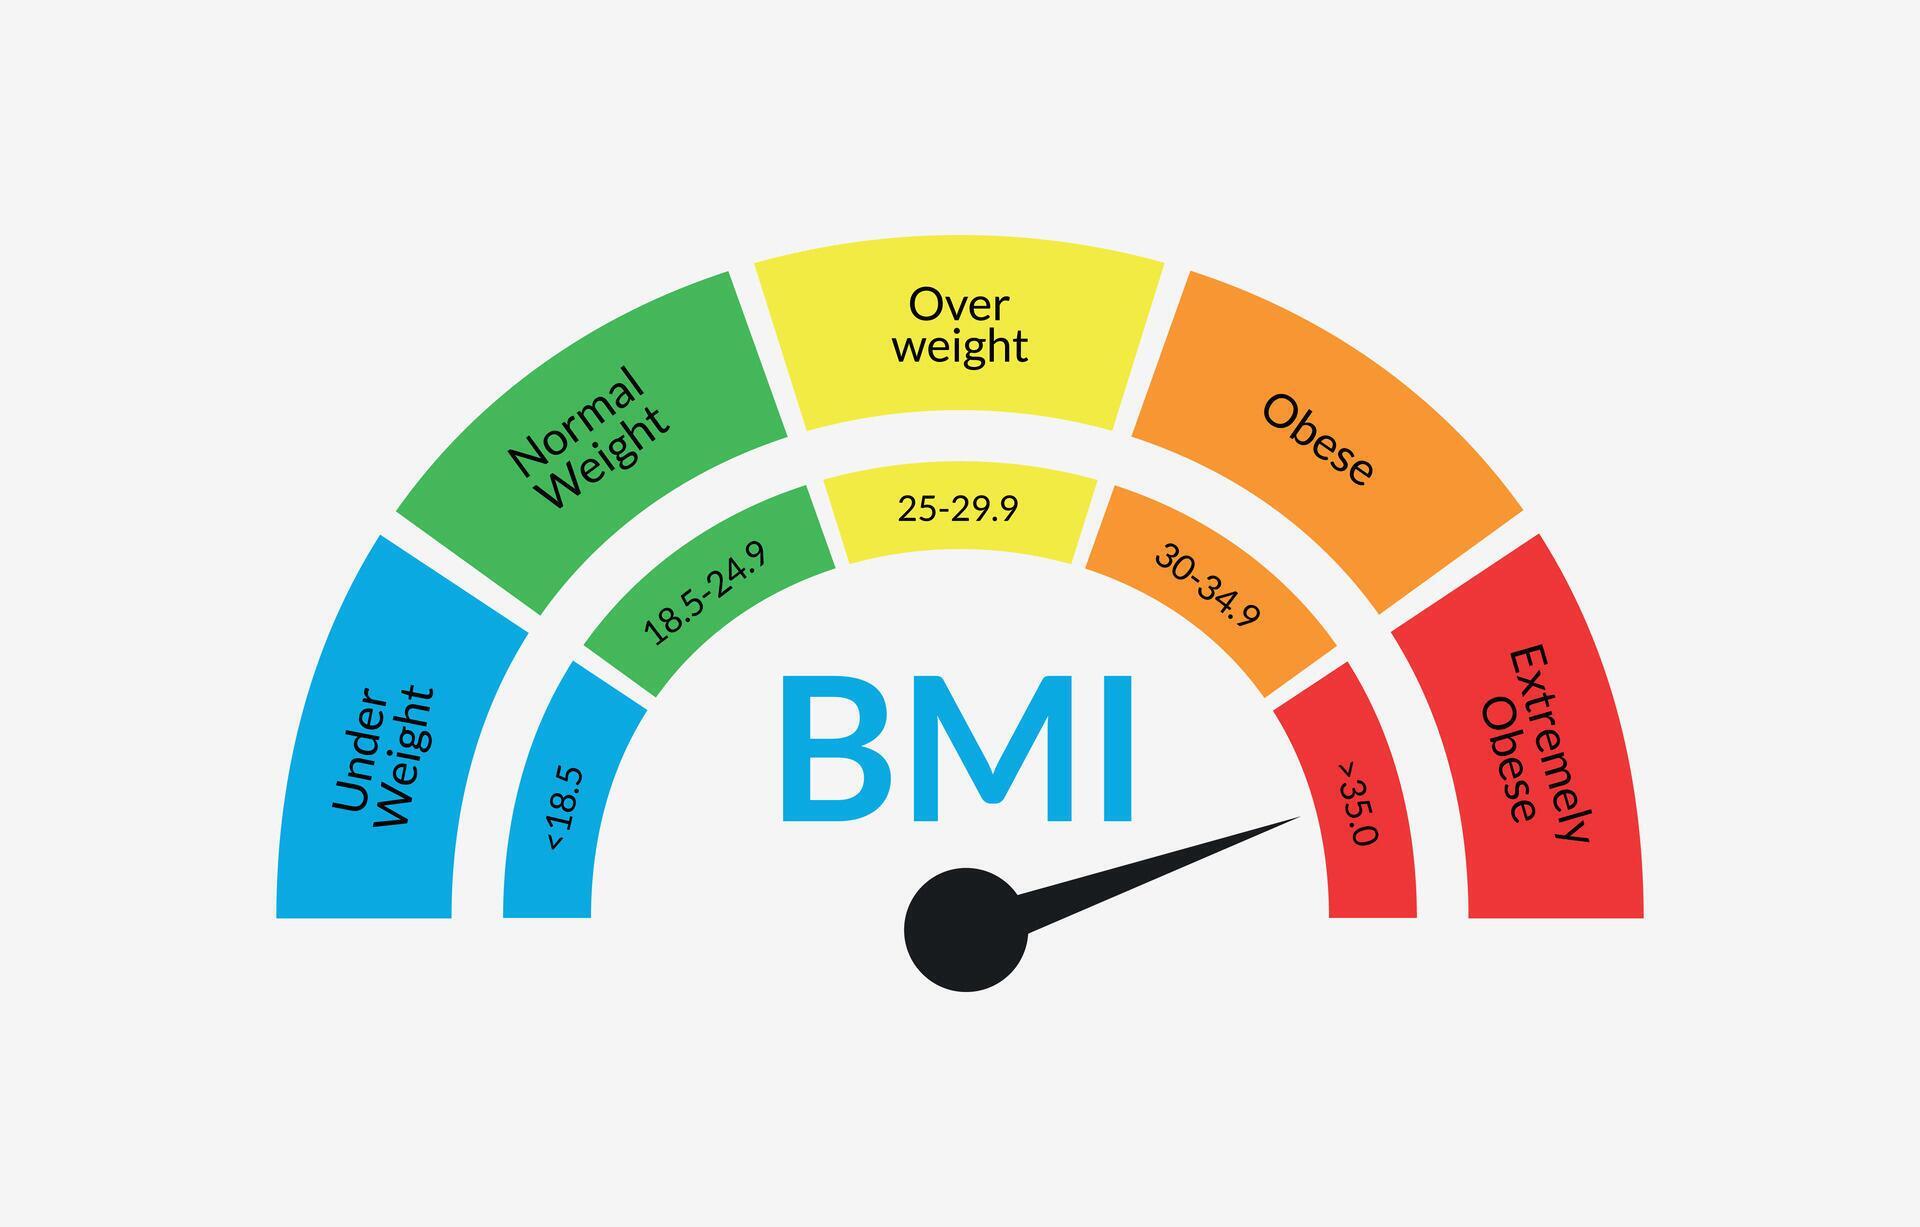
The concept is straightforward enough. You take a person's height and weight, run the math, and overlay that number onto a visual chart or gauge. But the reality of building these tools, or properly interpreting them, is messier than most marketing copy admits. I spent three years integrating BMI calculators into clinical dashboards before I learned to stop treating the output as a diagnosis. It isn't one. At their core, BMI visualizers are interface components that map a calculated value against a color-coded scale. Green for normal, yellow for overweight, red for obese. The visual part is what makes the difference between a spreadsheet cell and something a patient can actually sit with. Numbers on a screen get ignored. A red zone on a gauge gets noticed. I built my first version using a simple SVG radial gauge. Input field for kilograms, input field for centimeters, a calculate button, and an SVG element that redraws itself based on the output. The whole thing took about forty minutes to throw together. It was also dangerously incomplete. Here is what I learned the hard way.
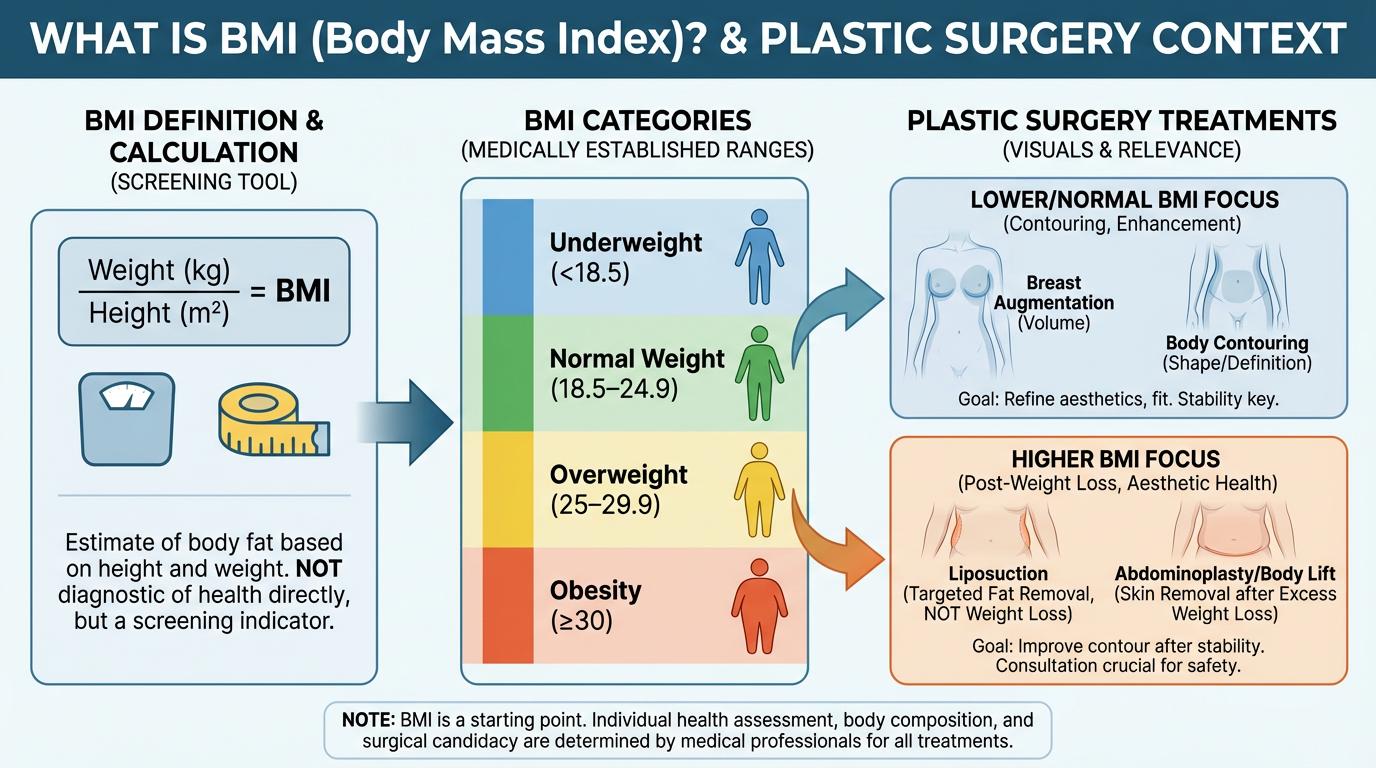
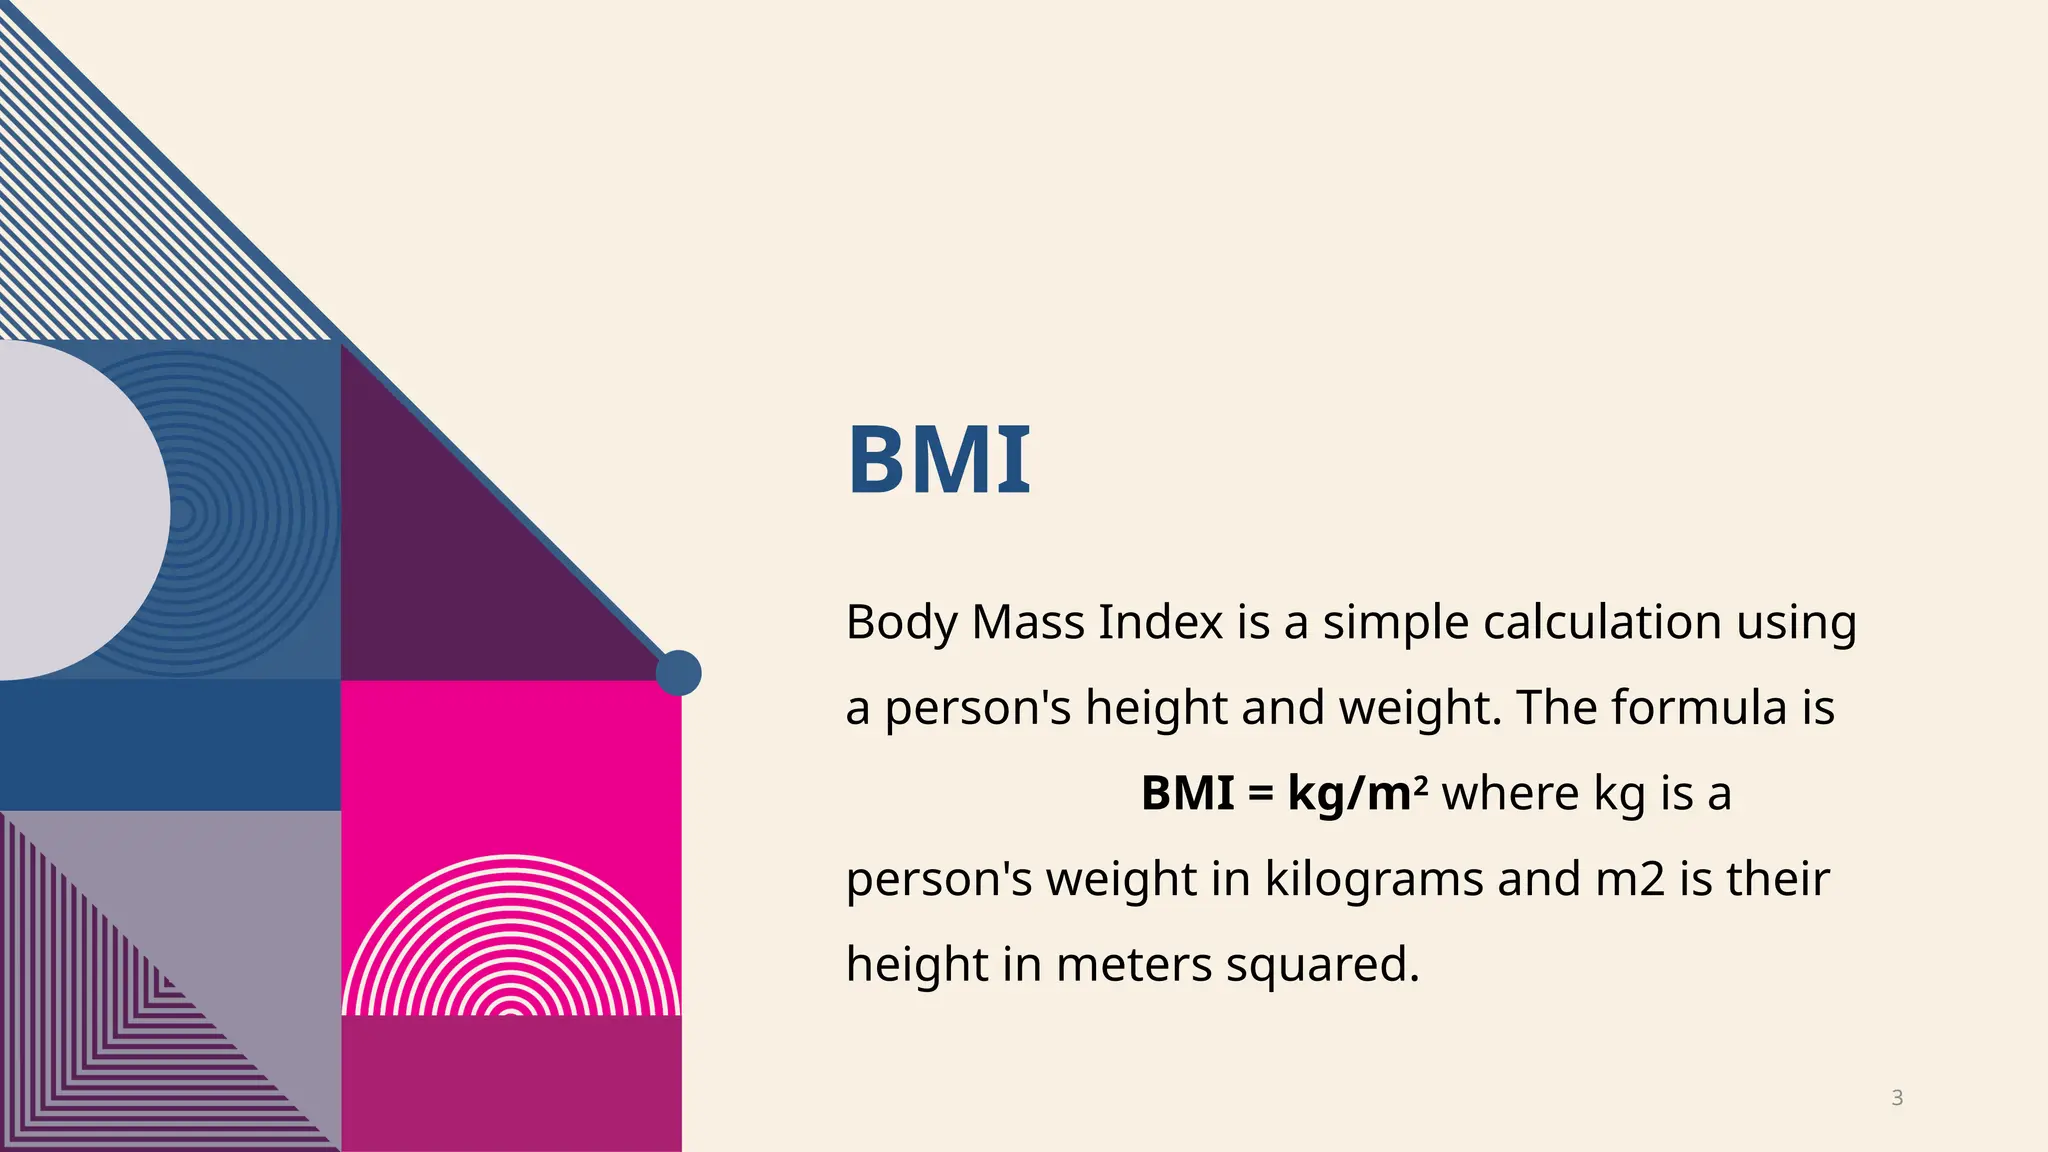
BMI is weight divided by height in meters squared. That formula has been around since the 1830s. Adolphe Quetelet developed it. It was never designed to assess individual health. It was designed to describe populations. When you hand a individual patient a number and a color, you are translating a population-level statistic into a personal judgment. That translation causes real problems. The edge case that almost broke my system involved a client who was six foot two and weighed two hundred and thirty pounds. His BMI came out to approximately 29.7. The visualizer painted him yellow-orange, right at the border of the overweight category. He was a competitive rock climber with about eight percent body fat. The number was meaningless to his actual health status, but the interface made it look like a warning sign. I had to add a disclaimer layer and a body composition input field to give clinicians a way to flag athletes separately. Without that, the tool was actively misleading.
How to Build a Functional BMI Visualizer
Start with the inputs. Height in centimeters and weight in kilograms is the standard for most of the world. If you are targeting a US audience, you will need pound and inch support with the conversion baked in. I recommend accepting both units but storing everything internally in metric. It removes a class of rounding errors. For the calculation itself, the formula is BMI = weight_kg / (height_m * height_m). Convert centimeters to meters by dividing by one hundred. Do not skip that step. I have seen too many implementations that divide by height in centimeters directly and produce numbers that are off by a factor of ten thousand. The visual component can be as simple as a horizontal bar with color zones. I prefer the radial gauge for mobile interfaces because it reads well at small sizes. A horizontal bar needs more width to communicate the same information clearly on a phone screen. Build both and let the CSS handle which one displays based on viewport width.
Get the Full Details

Here is the basic structure. An HTML form with two number inputs and a button. A JavaScript function that reads those values, converts them, calculates BMI, and then updates a canvas or SVG element. That is the entire technical stack. The complexity comes from making it handle edge cases gracefully.
Common Pitfalls That Will Break Your Implementation
The first one is not handling invalid input. If a user types negative numbers, letters, or leaves a field blank, your visualizer should not crash or display NaN on screen. Clamp values to reasonable human ranges before calculating. Anything under thirty kilograms or over three hundred fifty kilograms should trigger a warning message rather than producing a bogus result. Same for height. Anything under one meter or over two point five meters is likely a data entry error. The second pitfall is the categorization thresholds. The WHO standard categories are underweight below eighteen point five, normal eighteen point five to twenty-four point nine, overweight twenty-five to twenty-nine point nine, and obese thirty or above. These are clean numbers. But they do not apply uniformly across all populations. East Asian populations tend to experience metabolic risks at lower BMI thresholds. Some clinical guidelines recommend using twenty-three and twenty-seven as cutoff points for overweight and obese in those groups. If your tool is used in a multicultural context, hardcoding the WHO thresholds without an override option is a mistake. I encountered a third issue during testing when a clinic tried to use the visualizer for pediatric patients. BMI for children requires age and sex-specific percentiles from the CDC growth charts. The standard adult calculation is completely wrong for anyone under eighteen. My workaround was to add a demographic checkbox that switches the calculation mode. If the user selects pediatric, the tool asks for age and sex and looks up the percentile from a stored dataset rather than computing a raw BMI number. That added about two days of development time but prevented the tool from being used incorrectly on a vulnerable population.
What These Tools Actually Deliver
A properly built BMI visualizer cuts the time a clinician spends explaining a raw number to a patient from roughly ninety seconds down to maybe fifteen. The visual does the explanation work. The patient points at the gauge and says they understand. The clinician can then move on to discussing what the number actually means in context or whether further assessment is needed. The limitation is that the number itself tells you almost nothing about body composition, visceral fat distribution, muscle mass, or metabolic health. Two people with identical BMI can have completely different risk profiles. The visualizer makes the number feel more authoritative than it is. That is a design problem, not a technical one. The interface should make clear that this is a screening tool, not a diagnostic one. If you are building this for a consumer app, add a link to more comprehensive assessments. Body fat percentage calculations, waist-to-hip ratio inputs, or a referral to a healthcare provider for actual lab work. The BMI number is a starting point. Treating it as an endpoint is where the tool becomes harmful.
I have stopped recommending standalone BMI calculators for clinical use. They belong inside larger assessment workflows where body composition data and clinical history are available. The visualizer is fine as a quick screening aid in a primary care waiting room. It is not fine as a standalone health assessment product. The marketing language around these tools usually implies something they cannot deliver.