What AST Actually Tells You, And What It Doesn't
You order a liver panel. The AST comes back at 48 U/L. Most clinicians glance at it, compare it to the reference range, and move on. That's usually fine when it's 1.5 times the upper limit of normal or less. The real confusion starts when values swing much higher or when AST and ALT diverge from each other. That's where people get tripped up. AST stands for aspartate aminotransferase. It's a cytoplasmic enzyme, and there's also a mitochondrial isoform. Both leak into blood when cells are damaged. The liver contains a meaningful amount, but so do skeletal muscle, cardiac muscle, kidneys, brain, and red blood cells. When you see an elevated AST without a clear liver story, that distribution is why.
Unveiling The Mystery Of Ast Aspartate Aminotransferase Understanding Its Role In Liver Health
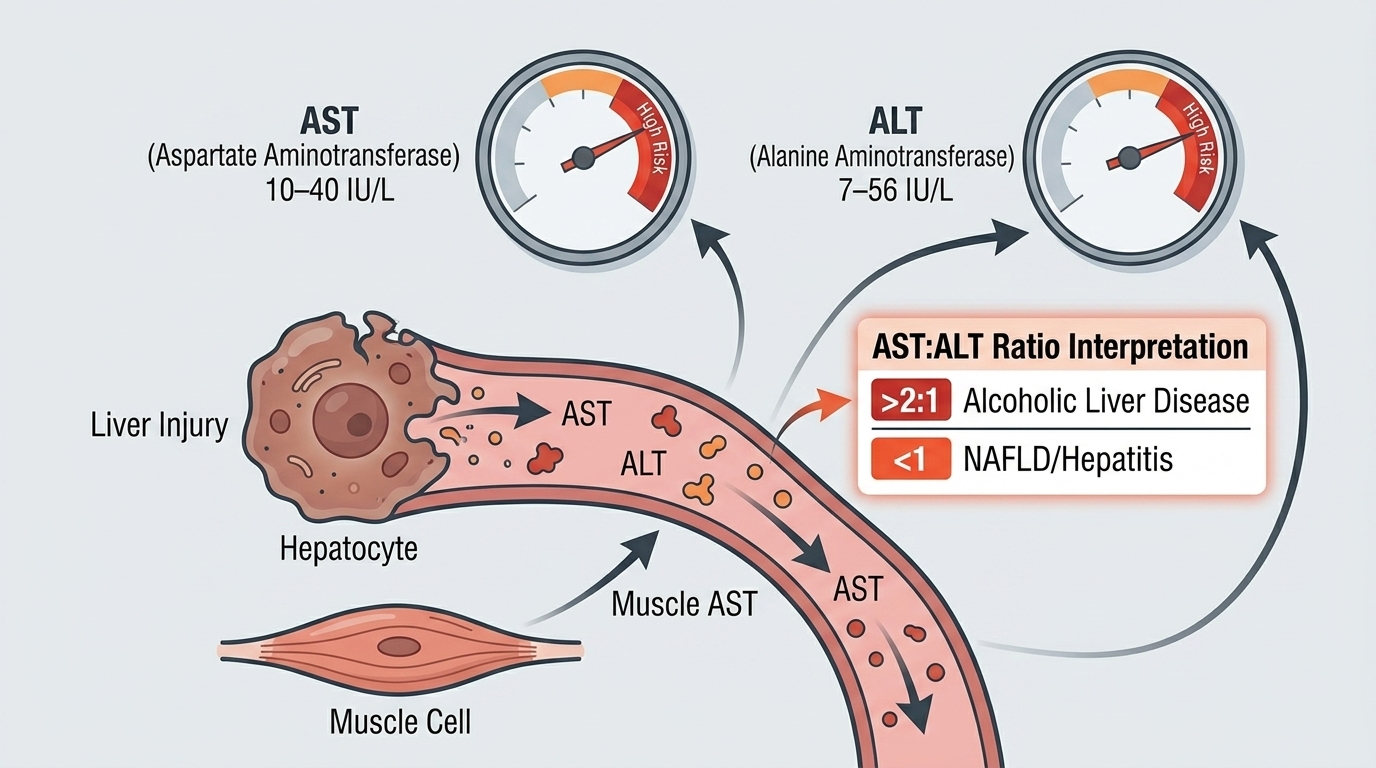
The standard test measures total AST activity using a coupled enzymatic reaction. Clinical chemistry analyzers run it alongside ALT, alkaline phosphatase, and bilirubin in what everyone calls a comprehensive metabolic panel. There's no special prep. Fasting doesn't change the result. The main pre-analytical variable is hemolysis. Red blood cells contain AST. A sample that looks slightly pink after centrifugation can push the AST value up by 10 to 20 percent or more depending on the degree of hemolysis. I've rejected panels on that basis more times than I care to count, and most lab directors won't tell you how often they do it quietly. The reference interval varies by laboratory and by sex. Many labs report roughly 10 to 40 U/L for women and 10 to 45 U/L for men, but your lab's range matters more than any textbook number. Always check the reference interval printed on your report. Using an incorrect cutoff is one of the most common sources of false alarm in primary care practice. In acute viral hepatitis, AST and ALT both climb into the hundreds or thousands. AST typically rises first and falls faster than ALT during recovery, which is why you might see a narrowing gap between the two values as the patient improves. That kinetic difference is useful for staging the injury, but it means a single late measurement can understate the original severity. I saw this with a patient who presented three weeks after the onset of jaundice with an AST of 89 and an ALT of 120. The story on history alone suggested recent injury, but the pattern and the ratio pointed to resolving hepatitis from months prior. The single snapshot was misleading. A repeat in two weeks confirmed the trend.
The AST-to-ALT ratio, sometimes called the De Ritis ratio, is the part everyone remembers from medical school and almost nobody applies correctly in daily practice. An AST/ALT ratio greater than 2 is strongly associated with alcoholic liver disease. The biology here is partly about pyridoxal 5'-phosphate. Alcohol use disorder commonly causes vitamin B6 deficiency, and B6 is a required cofactor for ALT synthesis. Less cofactor means lower ALT activity relative to AST. That ratio pattern is helpful but far from specific. About 30 percent of patients with alcoholic hepatitis never reach a ratio above 2, and nonalcoholic steatohepatitis can produce ratios in the same range, especially as fibrosis advances. I ran into a particularly annoying edge case last year. A patient with well-controlled hypothyroidism and a history of marathon training came in for routine monitoring. Her AST was 112, ALT was 52, and her alkaline phosphatase and bilirubin were normal. The primary care provider flagged it as possible hepatitis and ordered a full viral workup. I checked CK. It was 3,400. The patient had run a half-marathon the weekend before the blood draw. Skeletal muscle damage was the sole explanation. The workaround is simple but often missed: order a CK when AST is elevated out of proportion to ALT and liver-specific markers are quiet. In my experience, this saves an unnecessary hepatology referral and a couple of extra blood draws, usually cutting the follow-up timeline from four weeks down to a single visit. Another thing that surprises people is that AST is not the better marker for liver specificity. ALT is. ALT lives almost entirely in the liver, while AST is shared across multiple organs. When you need to know whether a biochemical abnormality is liver-derived, ALT is the cleaner signal. AST becomes more relevant when you're looking at certain patterns, like alcohol-related injury, medication-induced liver injury with mitochondrial toxicity, or situations where you need to estimate the speed of an acute event based on how quickly the value peaks and drops.
Get the Full Details
Medication monitoring is where AST gets used most aggressively in practice. If someone starts isoniazid, methotrexate, or valproate, periodic LFTs are standard. A common rule of thumb in the literature is to hold or reassess therapy when transaminases rise above three times the upper limit of normal, especially if bilirubin is also elevated. The rule has teeth. It prevents hepatotoxicity from becoming severe. It also generates a lot of false positives because many drug-related AST elevations are transient and resolve without intervention. I've seen patients stopped on statins unnecessarily because their AST crept to 80 and stayed there while the clinical picture was otherwise stable. Rechecking in two to four weeks usually sorts out the real signal from the noise. The limitations deserve to be stated plainly. AST does not correlate well with fibrosis stage. You can have significant cirrhosis with a normal AST, and you can have a dramatic AST spike with reversible inflammation and no permanent damage. Relying on AST alone to judge chronic liver disease severity is a mistake. FibroScan, ELF panels, and histology matter more for that question. AST is a marker of injury activity, not structural integrity. There's also the issue of macro-AST. It's a benign condition where AST binds to immunoglobulin and forms a large complex that clears slowly from blood. The result is a persistently elevated AST that looks alarming on paper but causes no disease. The diagnosis is made with polyethylene glycol precipitation or electrophoresis. It's rare, maybe one in a thousand tests, but it shows up in the patients who get worked up repeatedly for no reason. If your AST is chronically elevated at a low-to-moderate level and every other liver test is normal over years, macro-AST should be on the differential before you send someone for imaging or biopsy.
For practical purposes, here's how I read these results now. If AST is mildly elevated, below two times the upper limit of normal, and ALT is normal or only slightly elevated, I look for muscle sources, medications, and metabolic syndrome before assuming liver disease. If AST and ALT are both elevated and the ALT is higher, I think nonalcoholic fatty liver disease, viral hepatitis, or medication effect. If AST is higher than ALT with a ratio approaching or exceeding 2, I ask about alcohol and check vitamin B6 status, but I don't stop there. Advanced fibrosis flips the usual ratios because damaged hepatocytes hold less enzyme overall, so a falling AST with rising bilirubin and low platelets can signal progression rather than improvement. That paradoxical drop is the part most clinicians miss, and it's the one that costs the most if ignored. The test itself is inexpensive, widely available, and fast. The interpretation is the hard part. A normal AST does not rule out liver disease. An abnormal AST does not diagnose it. Context, pattern, and repeat testing separate noise from signal. Everything else is just paperwork.