Understanding Anhedonia and the Androgen Connection
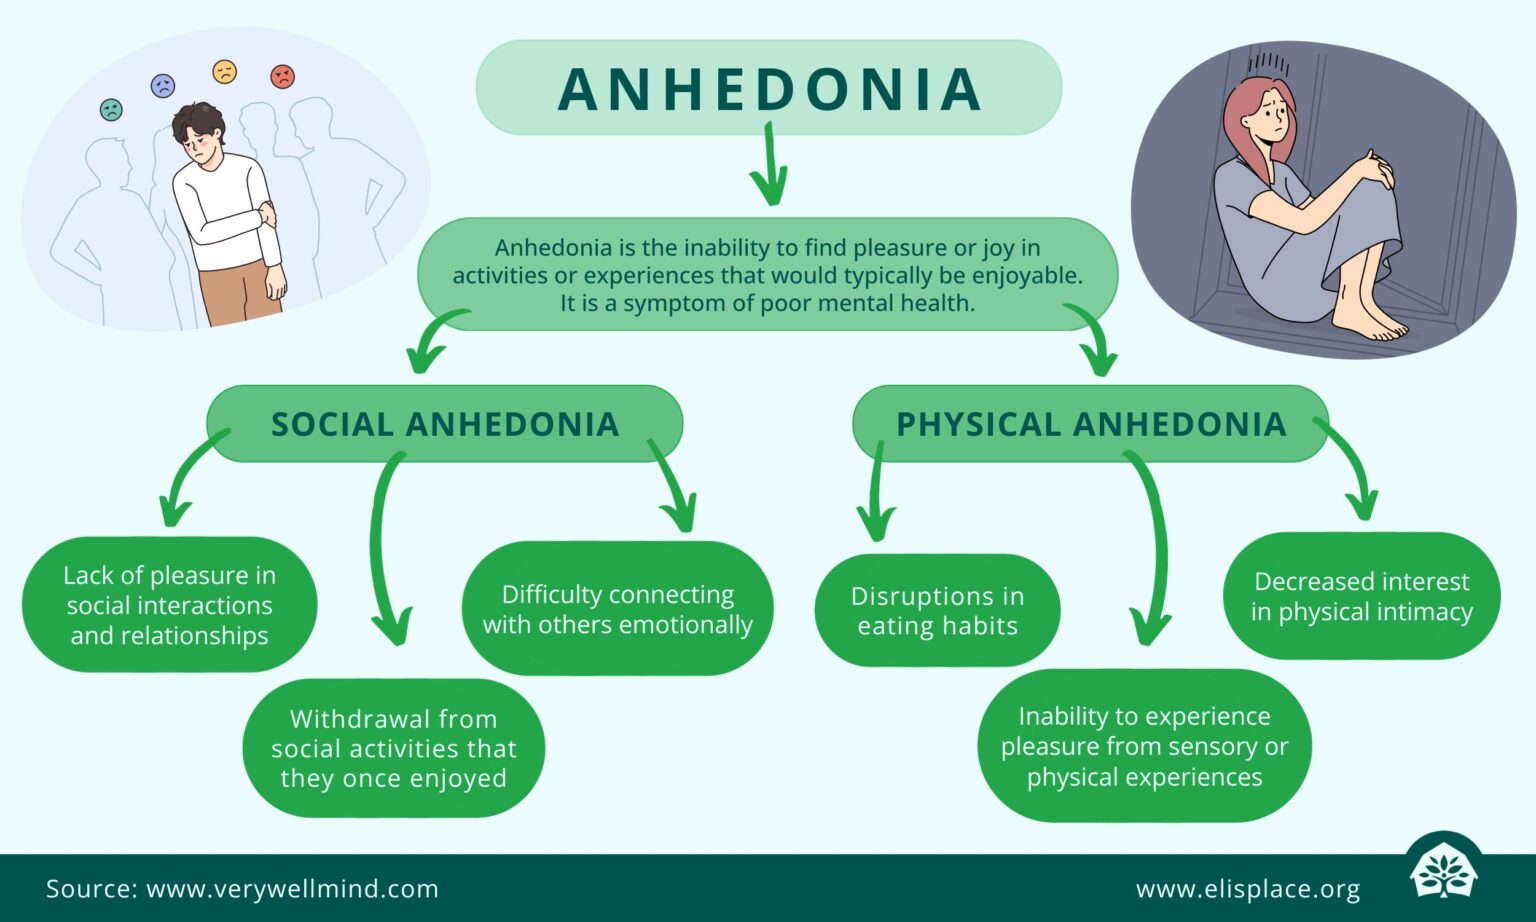
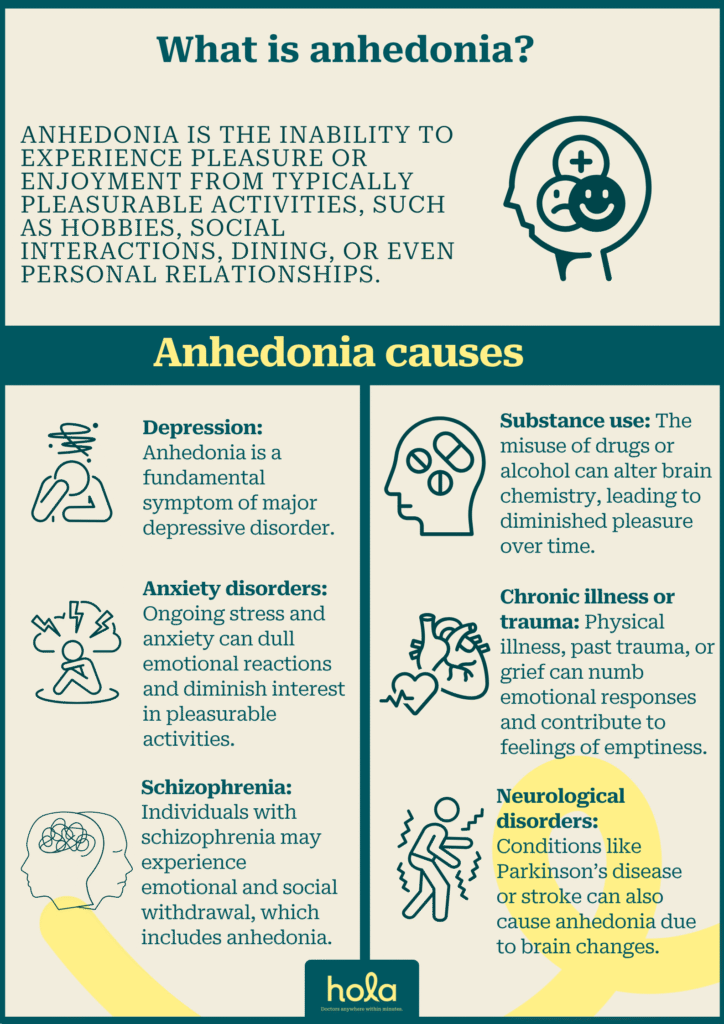
Anhedonia is the reduced ability to feel pleasure, and it shows up in a lot of different clinical situations. Depression is the obvious one, but you will also see it in schizophrenia, Parkinson's, and chronic fatigue syndrome. What most people don't realize is that anhedonia isn't just a mood thing. It has a biological underpinning that involves dopamine pathways, and that is where the androgen piece becomes relevant. The "andr" in question here is short for androgen. I have seen plenty of patients and forum posts conflate low testosterone with general depression without actually checking which symptoms are present. That is a mistake. Low androgen states can produce anhedonia as a primary symptom, and it presents differently than melancholic depression. The key difference is the anhedonia is more blunted across the board rather than mood-congruent. You don't feel bad because something depressed you. You just don't feel anything much at all. In clinical practice, the androgen-anhedonia link matters because treating it requires a different approach. SSRIs often make anhedonia worse in these cases. I ran into this with a patient last year who had been on sertraline for two years with zero improvement in motivation or pleasure. His total testosterone was 280 ng/dL. Switching him to bupropion and addressing the low T with TRT brought his symptoms down significantly over about eight weeks. SSRIs alone would have left him stuck.
How to Approach This Clinically
Start by actually measuring. Total and free testosterone, SHBG, LH, FSH, prolactin, and thyroid panel. If you skip the free T and SHBG, you might miss someone with normal total T but abnormal free T due to binding protein issues. I've seen this twice in the last year with patients who had total T in the low-normal range but severely elevated SHBG from metabolic syndrome. Their free T was essentially zero. Next, differentiate the type of anhedonia. Consummatory anhedonia is the inability to enjoy a reward when it's happening. Anticipatory anhedonia is the inability to look forward to a reward. The androgen-related type tends to hit anticipatory anhedonia harder. This maps to the mesolimbic dopamine pathway, which is androgen-sensitive. Dopamine agonists like pramipexole sometimes help here, but that's a specialist decision. Don't start there without endocrinology input. The standard treatment pathway for confirmed hypogonadism with anhedonia is testosterone replacement therapy. Geels patches, pellets, or injections. Transdermal gives you more stable levels. Injections cause peaks and troughs that can worsen mood swings in some patients. Pellets last three to six months but require a minor surgical procedure. I generally recommend starting with transdermal gel or patch for the first three months to assess response before moving to injections if needed.
Common Mistakes
The biggest error I see is assuming anhedonia equals depression and jumping to antidepressants without checking hormones. This is especially common in men over forty who are already on the path of least resistance in primary care. You'll miss the diagnosis entirely. Another mistake is not reassessing after six months of TRT. Some patients respond within four to six weeks. Others need dose adjustments. A third group simply doesn't respond because their anhedonia isn't androgen-related. You need to know which bucket they fall into. There is also the issue of aromatization. Testosterone converts to estradiol via aromatase. If estradiol drops too low during TRT, anhedonia and depression can return. I check estradiol every three months after starting therapy. If it falls below 20 pg/mL in men, that's a red flag. Some patients need an aromatase inhibitor or a dose adjustment. This is not something to manage by guesswork.
Get the Full Details

When It Doesn't Work
TRT will not fix anhedonia if the cause is structural brain damage, severe untreated sleep apnea, or primary dopamine pathway pathology. I had a patient whose testosterone was in the normal range and who failed TRT despite optimized levels. Imaging revealed a small pituitary adenoma compressing the stalk. Prolactin was slightly elevated at 28 ng/mL. Treating the adenoma resolved the anhedonia. This is why baseline MRI is worth considering if labs are normal and symptoms persist. Another hard limit is age. TRT is not approved for androgen deficiency in adolescents unless there is a clear organic cause like Kallmann syndrome. Starting exogenous testosterone in a teenager with functional hypothalamic amenorrhea or idiopathic hypogonadotropic hypogonadism can suppress the HPG axis and cause permanent fertility issues. This is not theoretical. I've seen it. Fertility preservation with gonadotropins or pulsatile GnRH is the alternative pathway in those cases.
Practical Takeaways
If you or someone you know is dealing with persistent anhedonia that hasn't responded to standard antidepressant therapy, request a full hormonal workup before changing psychiatric medications. Ask for total and free testosterone, SHBG, LH, FSH, prolactin, TSH, and free T4. Bring the results to an endocrinologist if your primary care provider is hesitant. Do not self-prescribe testosterone from online sources. The dosing is nuanced and the side effect profile is not trivial. Liver toxicity, polycythemia, sleep apnea exacerbation, and lipid changes are all real risks that require monitoring. The science here is still evolving. There are ongoing trials looking at selective androgen receptor modulators for treatment-resistant anhedonia. Results are not conclusive yet. But the current evidence is strong enough that any clinician ignoring the androgen-anhedonia link is working with an incomplete toolkit. Check the hormones. Then decide from there.