Unveiling The Mysteries Of Do I Ique Sachse A Journey Through The Depths Of Acquired Brain Injury
Samantha
2026-07-20
Understanding Acquired Brain Injury: A Practical Guide
What Acquired Brain Injury Actually Is
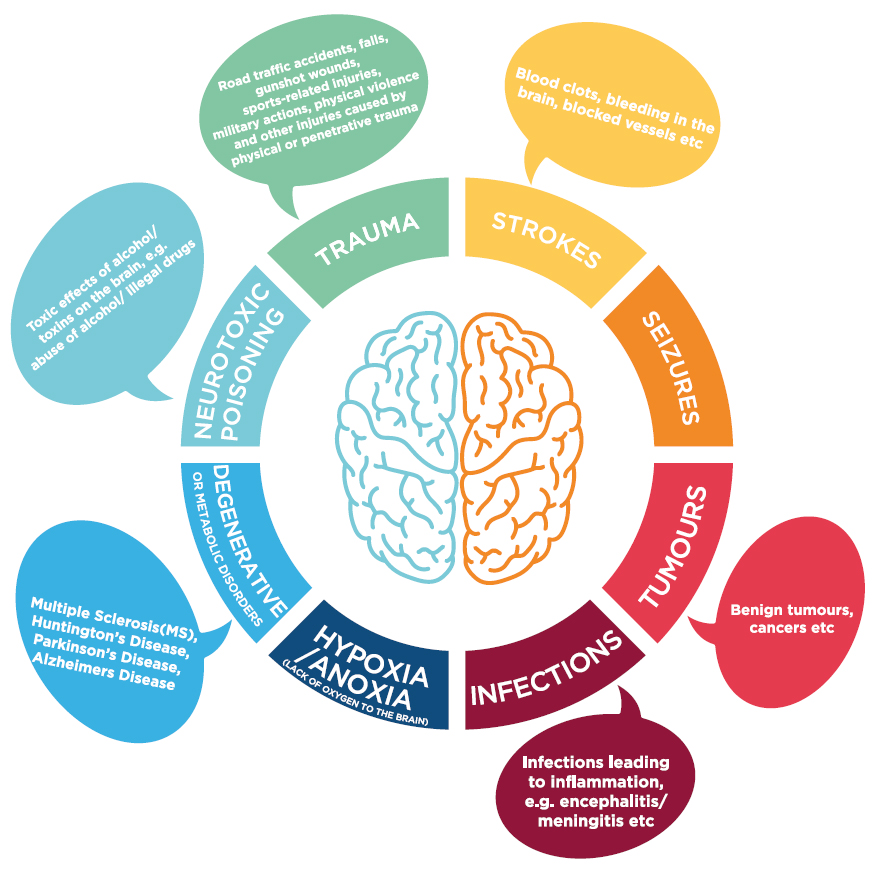
Acquired brain injury, commonly called ABI, refers to any brain damage that occurs after birth. It is not hereditary, congenital, or degenerative. The two broad categories are traumatic brain injury — caused by external force like a concussion, fall, or blast — and non-traumatic injury, which includes strokes, tumors, infections, oxygen deprivation, and toxic exposure. People often lump all brain injuries together, but the mechanisms, recovery timelines, and rehabilitation approaches differ significantly between them.
Where the confusion starts
There is a body of work and personal accounts sometimes referenced as
Unveiling The Mysteries Of Do I Ique Sachse A Journey Through The Depths Of Acquired Brain Injury
that deals with lived experience of ABI, the emotional arc of recovery, and the gaps in medical understanding that patients face. I do not have a precise citation for this specific title or author, and I want to be honest about that rather than inflate it. What I can say with confidence is that the core subject — the reality of living with and recovering from acquired brain injury — is extremely well documented in clinical literature and patient memoirs alike, and the practical takeaways are consistent across most sources.
The phases people actually go through
Right after the injury, in the acute hospital phase, the focus is stabilization. Getting the brain swelling under control, preventing secondary damage, keeping vitals stable. This phase can last hours to weeks depending on severity.
Then comes the inpatient rehab phase. This is where neurorehabilitation really begins. Physical therapy, occupational therapy, speech-language pathology, and neuropsychology all work together. The intensity is high — typically four to six hours of therapy per day. The goal is maximizing functional independence, not returning to baseline because the baseline has changed.
Outpatient and community reintegration is the longest phase and the one most people are unprepared for. You are out of the structured environment and suddenly expected to manage everything — work, relationships, finances, daily logistics — with a brain that processes things differently. This is where the real challenges surface, and where most support systems break down.
Neuroplasticity is real but misused
Everyone tells you the brain can rewire itself, and that is true. But the speed and extent depend on age, injury location, injury severity, pre-injury cognitive reserve, and the quality of rehabilitation. The common misconception is that more therapy always equals better outcomes. That is not necessarily true. Overloading a fatigued brain can actually slow progress. I have seen people push through twelve-hour therapy days and regress because their cognitive reserve was depleted. The evidence supports distributed practice — shorter, more frequent sessions with adequate rest — over marathon sessions that leave the patient burned out.
Cognitive deficits that nobody warns you about
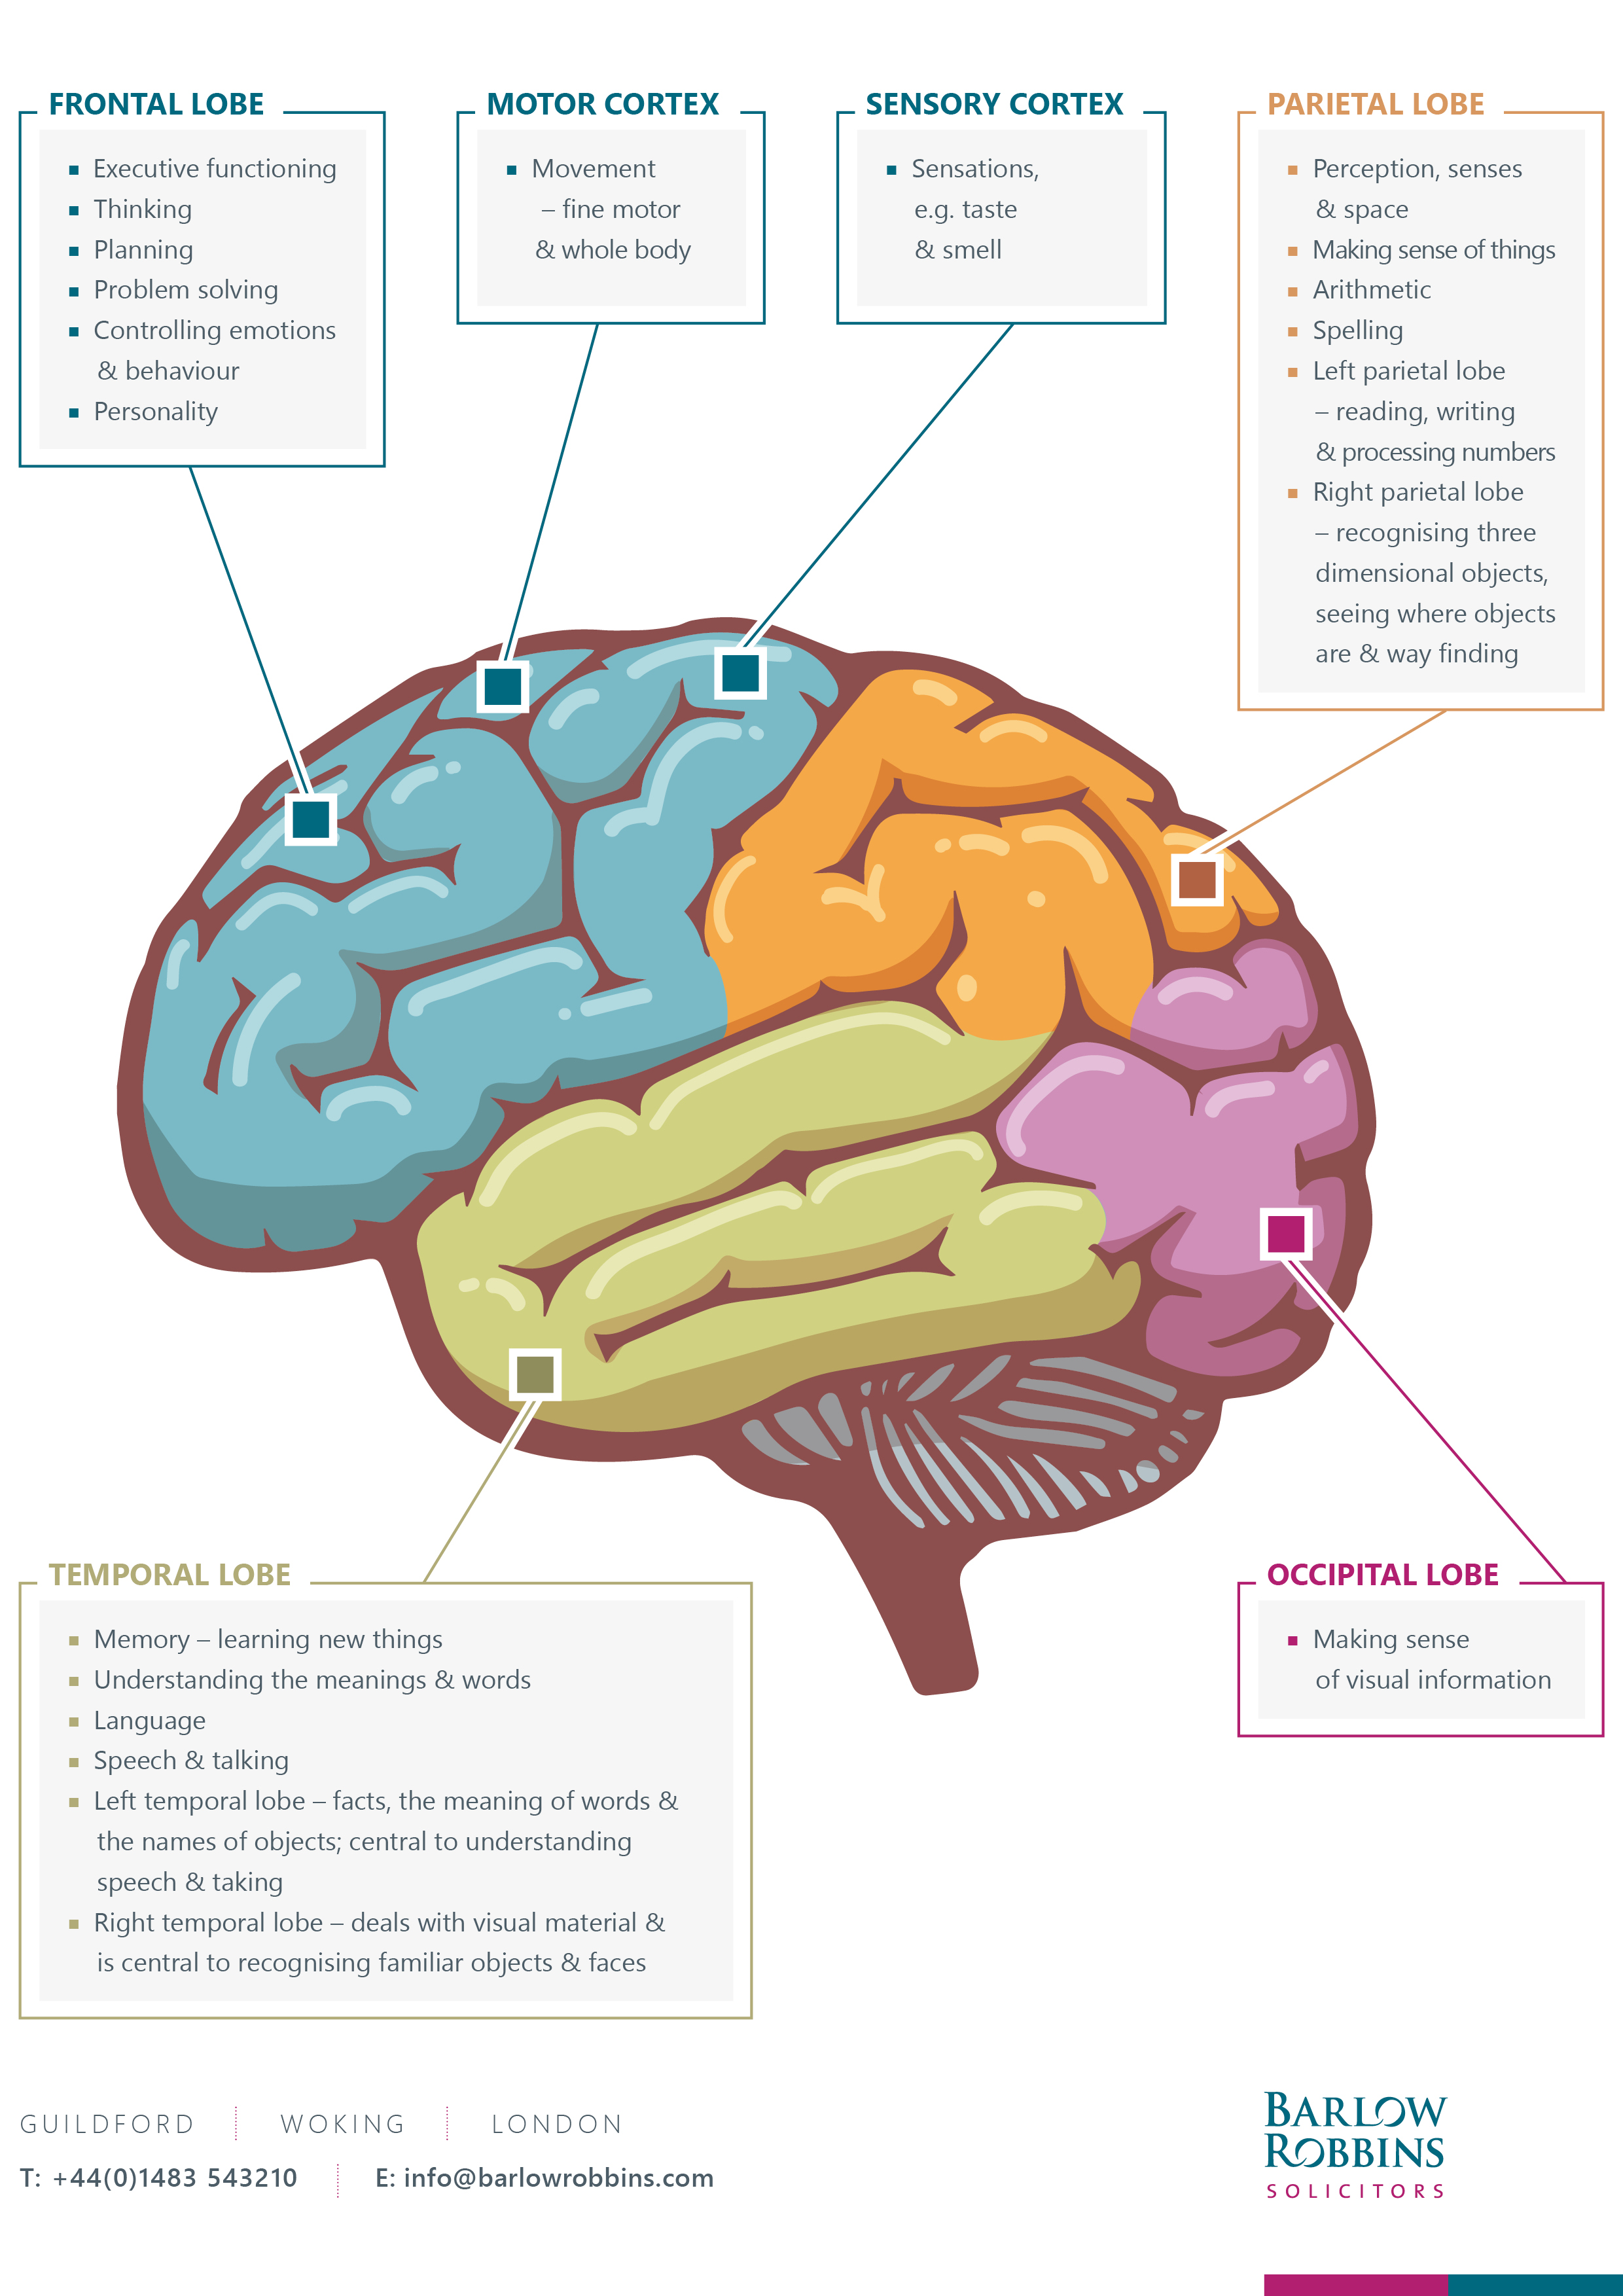
Memory problems get the most attention, but executive dysfunction is usually the bigger life-impacting issue. Planning, sequencing, multitasking, impulse control, emotional regulation — these are the things that make returning to work and maintaining relationships difficult. A person might remember your name perfectly but have no capacity to follow through on a multi-step plan like grocery shopping or managing medications.
Fatigue is another one. Brain injury fatigue is not ordinary tiredness. It is a neurological exhaustion that limits cognitive output. I once worked with someone who could function adequately for ninety minutes of focused work and then could not process a simple conversation afterward. The workaround was structuring the day around cognitive rest periods, not pushing through. Scheduling demanding tasks for late morning when alertness is higher, and leaving afternoons for low-demand activities.
Emotional changes are medical, not character flaws
Pseudobulbar affect — involuntary crying or laughing — affects roughly fifteen to twenty percent of ABI survivors. Emotional lability, irritability, depression, anxiety, apathy. These are not personality changes. They are neurological symptoms. The family often interprets them as the person becoming difficult or distant. It helps to reframe them early. Medication can help with some of these, particularly SSRIs for mood and valproate or dextromethorphan for pseudobulbar affect, but therapy and accommodations matter just as much.
Return to work — the hard part
Most people with moderate to severe ABI face some degree of vocational change. The job they had before the injury is often not recoverable, at least not immediately. Cognitive stamina, processing speed, and working memory deficits make many professional roles impossible to perform at previous levels. The practical steps are: get a neuropsychological evaluation that maps specific cognitive strengths and weaknesses, request a vocational rehabilitation assessment through your insurance or state programs, and explore modified duty or reduced-hour arrangements before attempting full return.
I have found that the most successful returns to work involve a gradual schedule — starting with two or three days per week at half capacity and building over months, not weeks. Employers who rush the process often see the employee burn out and leave. The disability is invisible, so there is no accommodation period built into the culture.
The diagnostic tools that actually matter
CT and MRI show structural damage. They do not show functional impairment. A person can have a clean scan and significant cognitive deficits, or a messy scan and surprisingly good recovery. Neuropsychological testing is the gold standard for understanding what the brain can and cannot do post-injury. It takes six to eight hours usually, spread over two days, and produces a detailed profile of cognitive strengths and weaknesses. I recommend it for anyone with moderate or severe ABI, regardless of how well they seem to be functioning.
Common mistakes families make
Assuming recovery plateaus early. The brain continues to heal and adapt for years, especially with targeted rehabilitation. Expecting the person to simply try harder. Willpower does not repair neural pathways. Comparing the person to their pre-injury self constantly. This creates pressure and grief that slows adjustment. Failing to advocate for services. Insurance companies will deny coverage aggressively. Persistent appeal and documentation usually shift decisions.
Resources that are actually useful
The Brain Injury Association of America offers state-specific directories for rehabilitation and support groups. The VA has extensive programs for traumatic brain injury, including vestibular and balance rehabilitation which many providers overlook. Neuropsychology clinics at university hospitals tend to produce the most thorough assessments. Peer support groups — especially those led by people who are years out from their injury — provide more practical guidance than most clinical appointments.
What the research says about prognosis
Recovery is individual and unpredictable, but there are some reliable patterns. People under fifty generally recover better than older adults. Those who regain consciousness within six months of a severe TBI have better long-term outcomes than those who do not. Non-traumatic injuries like strokes have different recovery curves depending on the vascular territory affected. The first six to twelve months are the window of fastest recovery, but meaningful improvement continues beyond that. The idea of a hard ceiling at two years is outdated — it is a simplification that does not match clinical reality.
Practical daily strategies that help
External cognitive aids — phone reminders, whiteboards, medication organizers, calendar alerts — reduce the load on impaired working memory. Consistent routines minimize the cognitive demand of decision-making. Breaking tasks into single steps prevents overload. Identifying and avoiding personal triggers for fatigue and irritation is essential. Sleep hygiene becomes non-negotiable — the injured brain recovers during sleep, and poor sleep directly impairs cognitive function the next day.
I also recommend keeping a symptom and trigger journal for the first few months post-discharge. Patterns emerge that you would miss otherwise — specific times of day when cognition drops, activities that cause disproportionate fatigue, environmental factors like noise or brightness that worsen symptoms. This data is useful for adjusting therapy plans and advocating for accommodations at work or school.
The gap between research and real-world application
There is a notable disconnect between what clinical trials show and what actually happens in community settings. Rehabilitation protocols are often underfunded, understaffed, and rushed. Patients receive four weeks of inpatient therapy and are discharged with a folder of papers and a phone number for outpatient services that may not accept their insurance. The transition period between inpatient rehab and independent living is the most dangerous gap in the care continuum. I have seen people relapse cognitively and emotionally during this window because there was no structured support.
If you or someone you know is navigating ABI, the most actionable step is to build a support team before discharge — a neuropsychologist, a speech-language pathologist familiar with cognitive rehabilitation, a therapist experienced in brain injury, and a peer support group. Having these connections established while the person is still in the hospital makes the transition infinitely less chaotic.
Bottom line
Acquired brain injury changes everything but does not have to end meaningful life. The recovery process is nonlinear, frustrating, and often poorly supported by the medical system. Understanding the mechanics — neuroplasticity limits, cognitive fatigue, executive dysfunction, emotional lability — helps families and patients make better decisions. The literature is clear on what works: intensive early rehabilitation, neuropsychological assessment, gradual return to activity, and strong social support. The gaps are in access and follow-through, which is something patients and families have to manage proactively rather than expect the system to handle.
Gallery Unveiling The Mysteries Of Do I Ique Sachse A Journey Through The Depths Of Acquired Brain Injury
Acquired Brain Injury | International Association of Chiefs of Police
Types Of Acquired Brain Injury – DNMIO
Overview of Acquired Brain Injury - Mind Forward
What is an acquired brain injury (ABI)? - Manton Heights ABI Unit
Acquired Brain Injury - Cherry Training


.png "Acquired Brain Injury | International Association of Chiefs of Police")