Understanding Corneal Arcus: What It Actually Is
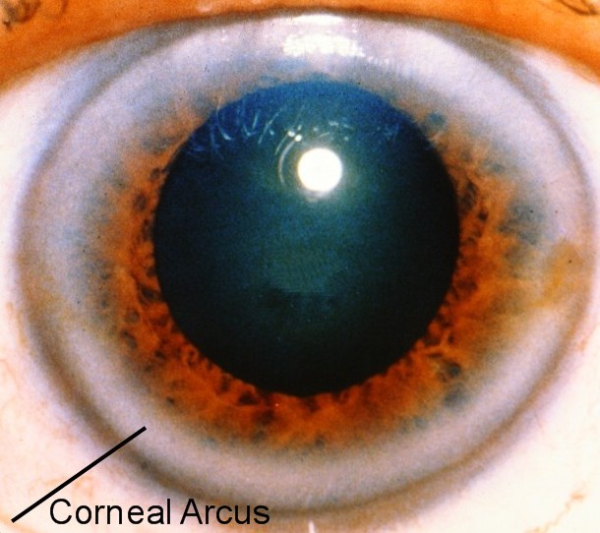
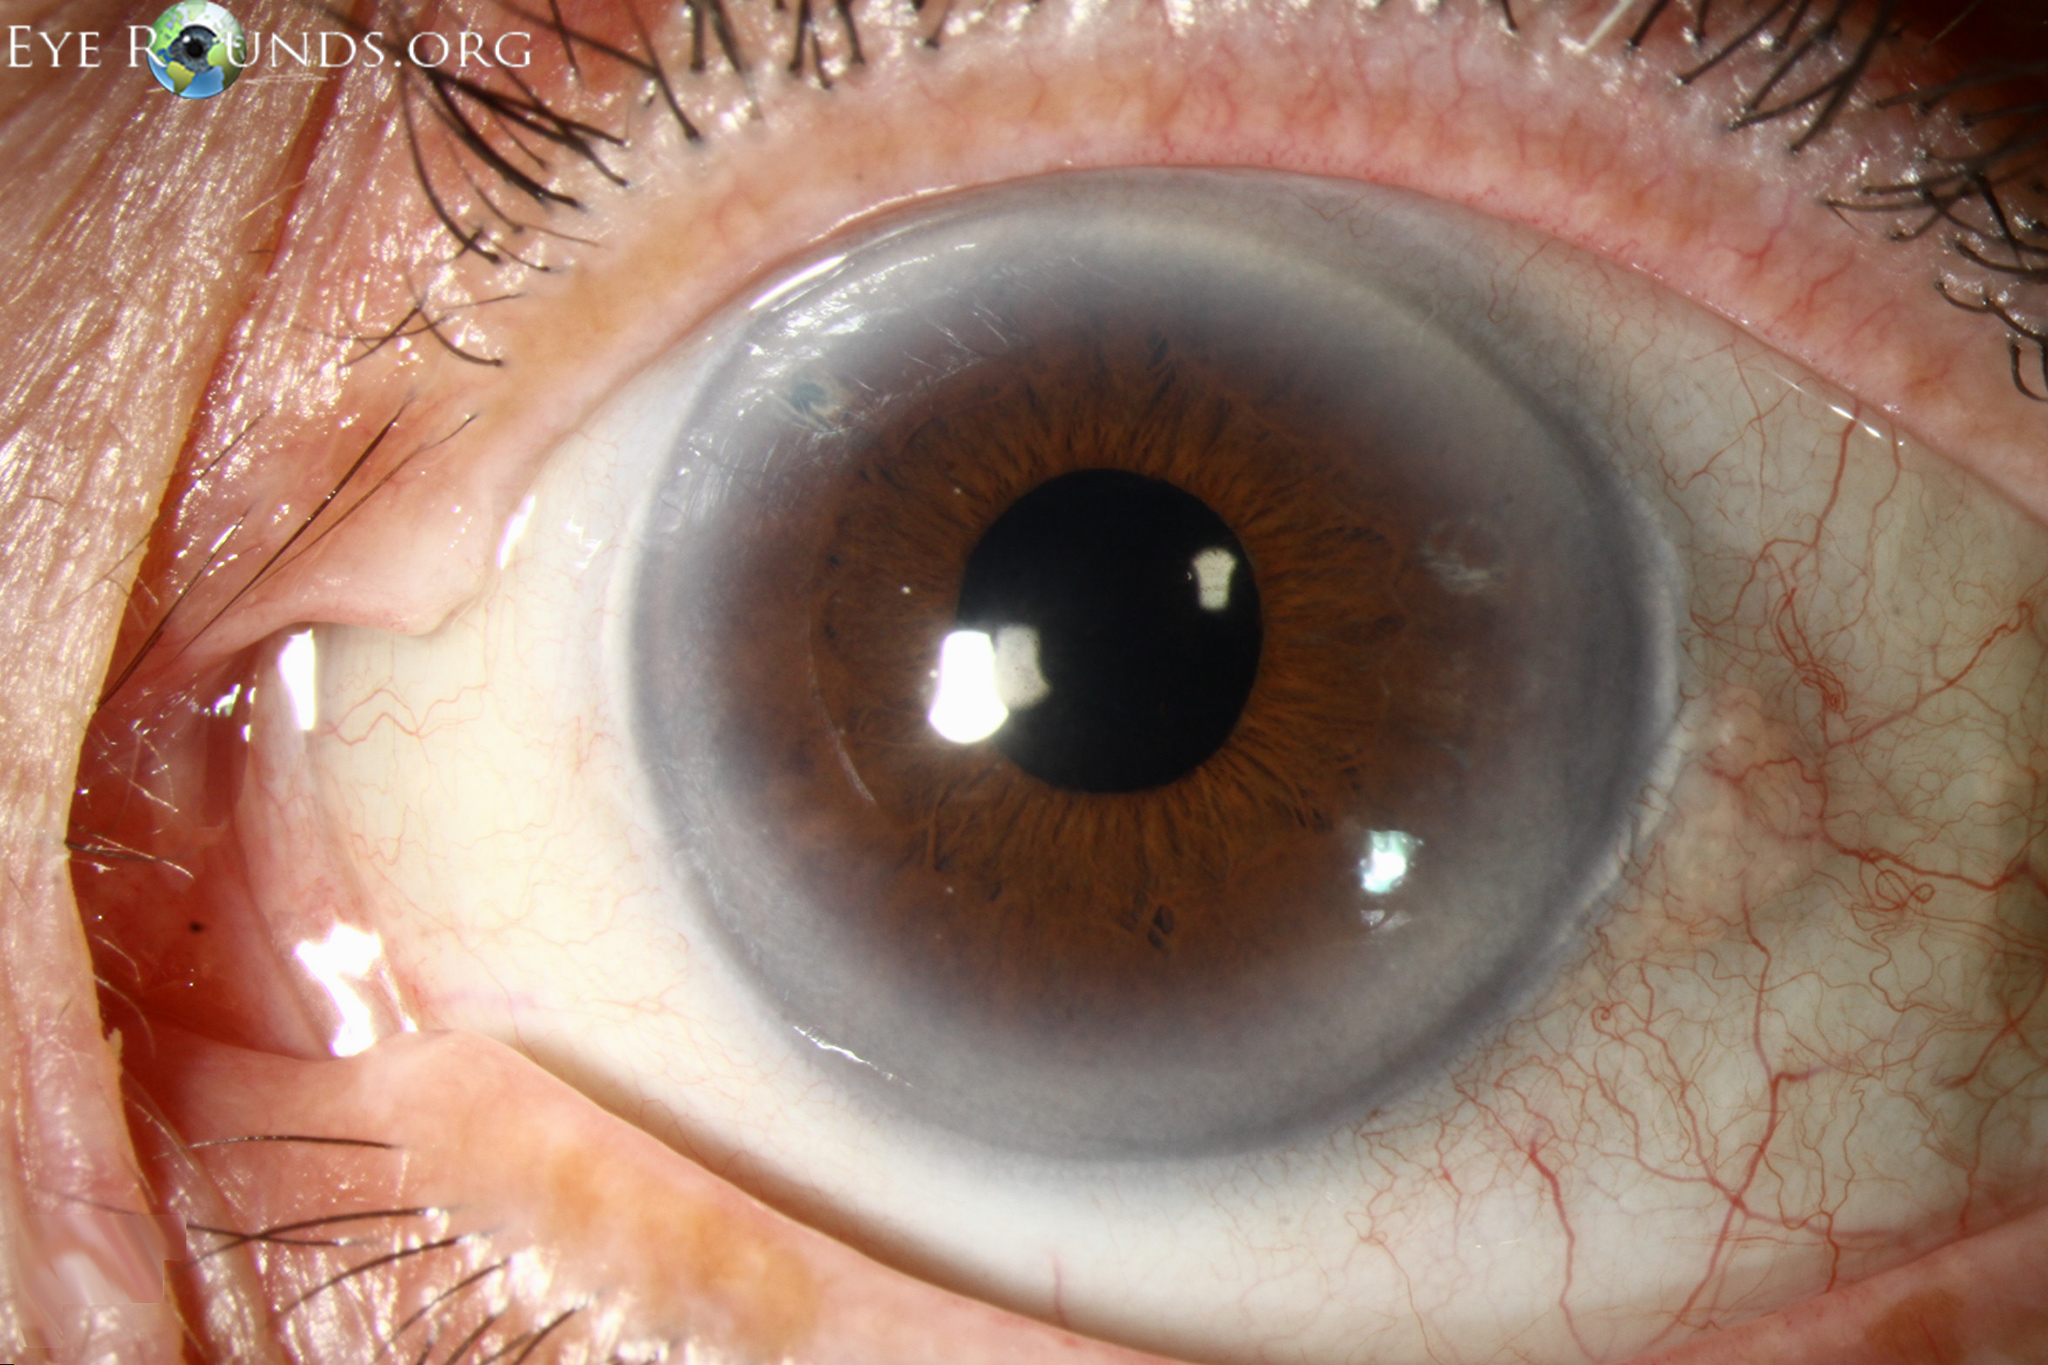
Corneal arcus, also called arcus senilis, shows up as a grayish-white ring or arc around the outer edge of the cornea. It's caused by lipid deposits — mainly cholesterol and phospholipids — accumulating in the corneal stroma. You see it most often in people over sixty, but it can appear much earlier. When it does, that's when it matters clinically. Here's what most people get wrong about it. The condition itself doesn't threaten vision. The lipid deposit sits in the peripheral cornea, well away from the visual axis. Patients won't complain of blurry vision from arcus alone. The real concern is the association with systemic lipid disorders, especially in younger patients. An arcus in someone under forty is a flag, not a diagnosis.
Unveiling The Mysteries Of Corneal Arcus A Guide To Identifying And Managing This Devastating Eye Condition
I need to correct something right out of the gate. The title language calling this "devastating" is wrong. Corneal arcus is not devastating. It's largely a cosmetic finding and a potential marker for cardiovascular risk. Calling it devastating causes unnecessary panic in patients who already worry about their eyesight. I've had patients come in visibly shaken because they read online that arcus means certain blindness. It doesn't. The cornea remains clear centrally. Vision is unaffected unless there's a separate concurrent condition. A slit lamp examination is the standard tool. You'll see a complete or partial ring of opaque, whitish-gray material at the corneal periphery, usually starting superiorly and inferiorly and progressing circumferentially. The lucid interval — a band of clear cornea between the arcus and the limbus — is a key distinguishing feature. That clear zone separates arcus from corneal degenerations like band keratopathy, which involves the central cornea and looks completely different. In routine practice, you can sometimes spot early arcus with a handheld slit lamp or even with good anterior illumination in a primary care setting. But definitive identification requires the slit lamp. You need to distinguish true stromal lipid deposition from other peripheral corneal opacities. Pseudarcus, or arcus juvenilis before the usual age range, needs the same workup — just with more urgency attached to the lipid panel.
When to Worry and When to Move On
If the patient is over fifty with a classic bilateral arcus and no other symptoms, order a fasting lipid panel and call it a preventive screen. That's it. Document it. Reassure the patient. No further ophthalmic workup is needed for the arcus itself. If the patient is under forty, the approach changes. Bilateral arcus in that age group carries a significant association with familial hypercholesterolemia and other dyslipidemias. I had a case a few years back — patient was thirty-two, came in for a routine exam, and I noted a near-complete arcus. The initial lipid panel showed LDL at 240 mg/dL and triglycerides at 310 mg/dL. Family history was positive for premature myocardial infarction. We confirmed homozygous familial hypercholesterolemia through genetic testing. The arcus was the only clinical sign that brought them in. Without that slit lamp exam, they might not have been diagnosed for another decade, by which point the cardiovascular damage would be substantial. This is why age matters so much in the assessment. Unilateral arcus is uncommon and should prompt investigation for underlying local pathology. Conditions like prior uveitis, glaucoma, or carotid artery disease can cause a unilateral presentation. In those cases, the workup goes beyond lipids and includes assessing intraocular pressure, evaluating for prior inflammation, and considering vascular imaging if the clinical picture suggests it.
Get the Full Details

Managing the Condition
There is no treatment for the arcus itself. The lipid deposits do not resolve with eye drops, dietary changes, or any topical intervention. Once the ring is established, it tends to persist. What you manage is the underlying risk factor. If dyslipidemia is present, statin therapy and lifestyle modification are the standard approach. Several studies have looked at whether lipid-lowering therapy can reduce arcus density, and the evidence is mixed at best. Some patients show slight regression with aggressive treatment, but most don't. Don't promise patients that treating their cholesterol will erase the ring. It won't, and saying it will undermines your credibility when it doesn't happen. The management focus should be on cardiovascular risk reduction, not ocular appearance. I've seen patients obsessed with the cosmetic aspect, asking about laser treatment or surgical removal. Neither is indicated. The cornea is delicate, and operating on it for a benign finding introduces real risk for zero benefit. Just say no to that conversation and redirect to the lipid panel.
Common Pitfalls
One mistake I see frequently is over-investigating classic arcus senilis in elderly patients without any other risk factors. Ordering an extensive cardiac workup for a seventy-five-year-old with bilateral arcus, normal blood pressure, no chest pain, and no known cardiac history is not good practice. A basic fasting lipid panel is sufficient. The yield drops dramatically when you're screening low-risk populations with expensive tests. Another pitfall is conflating arcus with corneal annulus or other peripheral degenerations. Corneal annulus, or lipid keratopathy, involves lipid deposition within the corneal substance but is usually associated with prior inflammation or vascularization. It looks different on slit lamp — the deposits are more granular and irregular, and there's often a history of uveitis or retinitis pigmentosa. Getting these mixed up leads to the wrong workup and unnecessary anxiety. A third issue is ignoring the arcus entirely in young patients. I've reviewed charts where a thirty-year-old with a prominent arcus was sent home with no lipid evaluation because the examining provider dismissed it as "just aging." That's a missed diagnosis of familial hypercholesterolemia, and those patients have a real and measurable risk of premature coronary artery disease. Age is the single most important factor in deciding how seriously to take this finding.
What the Research Actually Says
The Framingham Heart Study and several subsequent cohort studies established the link between arcus and cardiovascular disease in older adults. The association is moderate but consistent. Arcus in older patients correlates with increased risk of myocardial infarction and atherosclerosis, independent of traditional lipid levels. This suggests the arcus may be a marker of cumulative lipid exposure rather than a direct consequence of current serum cholesterol. That's an important distinction for counseling patients. In younger populations, the data is clearer but smaller in scope. Studies of patients with familial hypercholesterolemia show arcus prevalence rates of sixty to eighty percent, compared to less than five percent in age-matched controls without the condition. The presence of arcus before age forty should be treated as a strong clinical indicator warranting formal lipid evaluation and possibly genetic testing. There's no controversy about the benign nature of the ocular finding itself. The debate in the literature centers on how aggressively to pursue cardiovascular workup in asymptomatic older adults who present with arcus. The consensus leans toward opportunistic screening — check lipids, assess overall cardiovascular risk, and manage accordingly. Routine coronary imaging or stress testing solely because of arcus is not supported by the evidence.