Endometrial Adenocarcinoma Coding: What Actually Happens In Practice
Most people think ICD-10 coding for endometrial adenocarcinoma is straightforward. Pick a code, look it up, move on. I have spent enough years reading pathology reports and matching them to billing codes to tell you that this assumption gets people in trouble pretty quickly. The codes themselves exist. The problem is knowing which one to pick when the documentation is vague, contradictory, or just incomplete. The primary code you will run into is C54.1 — malignant neoplasm of the endometrium. That is the bread and butter code. It covers adenocarcinoma of the endometrium. You also have C54.0 for the endocervical gland, C54.8 for overlapping sites, and C54.9 when the site is unspecified. Then there are the Z codes and the follow-up codes you need to consider depending on the clinical context. But here is where it gets interesting, and where most coders make mistakes. Let me give you a real example from my own workflow. I had a case recently where the physician documented "stage II endometrial adenocarcinoma" and the pathologist confirmed endometrioid adenocarcinoma. Easy, right? Wrong. The staging documentation was incomplete. There was no mention of whether it involved the cervix or just the corpus. The operative report mentioned a total hysterectomy but did not specify the surgical staging workup beyond that. If I had just jumped to C54.1 with a stage II secondary code, I would have been guessing. I ended up requesting a addendum from the physician to clarify the exact extent of disease before assigning the final codes. It took three days. The patient was waiting on the claim. But guessing would have been a compliance risk.
The hidden danger here is not the code itself. It is the assumption that you can code from staging alone without confirming the anatomical site and histology. Endometrial adenocarcinoma is the most common type of endometrial cancer, roughly 80 percent of cases, and it is usually endometrioid histology. But when the pathology says "carcinoma not otherwise specified" or "malignant neoplasm of endometrium unspecified," you cannot default to C54.1 with confidence. You have to go back to the documentation or request clarification. This is not a suggestion. It is a requirement under ICD-10-CM coding guidelines. Another nuance that catches people off guard involves the distinction between C54.1 and C54.0. Adenocarcinoma arising from the endometrium goes to C54.1. Adenocarcinoma arising from the endocervical glands goes to C54.0. These are different anatomical origins even though they are close geographically. I have seen both used interchangeably in sloppy coding audits. The pathology report should make this clear. If it does not, you code to the more specific site available and query the physician. Do not pick the code that seems more convenient. Then there is the issue of laterality and multi-site involvement. Endometrial adenocarcinoma does not have a laterality component in the standard C54 codes, but if the cancer involves the ovary as well, you need separate codes. C54.1 for the endometrium and C56.9 for the ovary, unspecified. Or if the fallopian tube is involved, that is C57.0. This is where overlapping site codes like C54.8 become relevant — but only when the documentation explicitly states the cancer involves multiple sites within the same category and you cannot assign separate codes for each. Overlapping codes are not a catch-all. They require documented multi-site involvement.
History codes matter too. If a patient had endometrial adenocarcinoma treated in the past and is now under surveillance with no evidence of disease, you use Z85.42 — personal history of malignant neoplasm of corpus uteri. But you still need to document that the active treatment has concluded and the patient is in follow-up. If there is any suspicion of recurrence, you go back to C54.1. The line between active treatment and history status is drawn by the physician's documentation, not by how much time has passed since surgery. One more thing that is easy to miss: the sequencing. For an admission primarily for treatment of endometrial adenocarcinoma, C54.1 is the principal diagnosis. But if the reason for admission is something else entirely — say, a hip replacement — and the endometrial cancer is a history item, then Z85.42 comes after the primary condition. Sequencing errors here cause claim rejections and audits. I have seen claims get denied for exactly this reason on a routine basis. The real bottleneck in this process is documentation quality. Physicians are not coders. They document what they need to document for clinical purposes. Sometimes that means omitting details that are obvious to them but invisible to someone looking at the chart for coding. My workaround is simple: build a query template specific to gynecologic malignancies that asks for site, histology, stage, and current treatment status in one standardized request. It cuts down the back-and-forth from an average of four messages per case to one or two. It saves maybe twenty minutes per case, but when you are running a high-volume practice, those minutes add up.
Get the Full Details
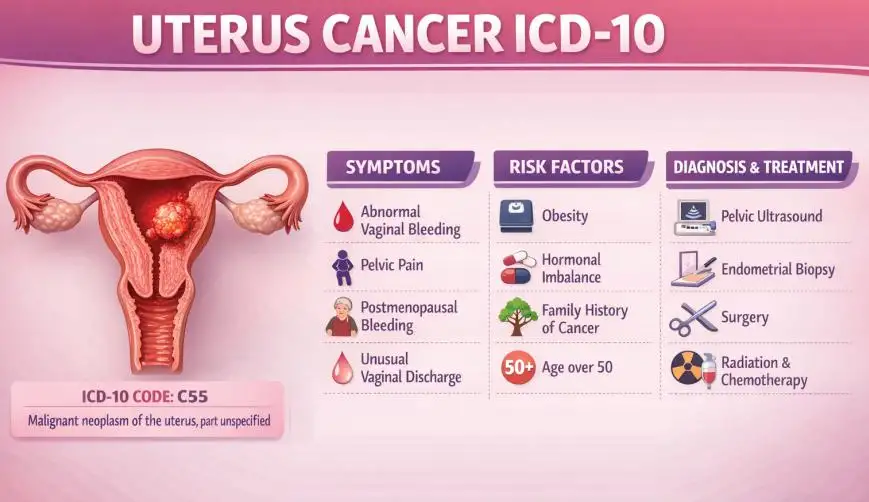
There is no perfect solution here. Coding endometrial adenocarcinoma will always depend on the quality of the underlying documentation. If the pathology report is missing, if the operative notes are fragmented, if the staging workup was never completed and documented — none of that is fixable by the coder. You code to what is available. You query when you can. You document your queries and responses. That is the process. It is not elegant. It works.