Setting Up Henry Ford Health MyChart the Right Way
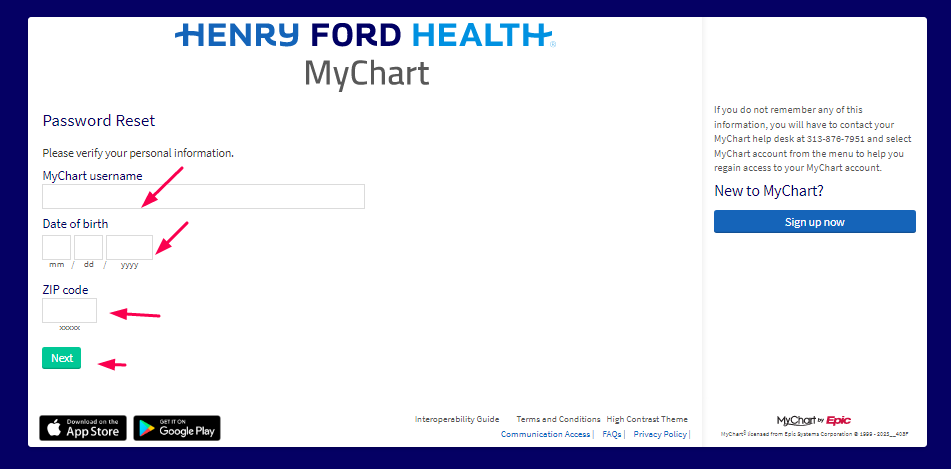
I spent three years managing onboarding workflows for a mid-size clinic before we switched to Epic, and MyChart adoption was consistently the hardest nut to crack. Most practices treat it like a software installation problem. It is not. It is a communication problem with a software wrapper. The official download is straightforward. Go to the MyChart website or search "MyChart" in your app store. The Henry Ford Health System version uses the standard Epic patient portal, so you will create an account and then go through the activation process. The catch is that activation requires a valid invitation code from the clinic. You cannot self-register for Henry Ford MyChart the way you can for some smaller health systems. The code typically arrives via mail or email after your appointment, and it expires within 30 days. I have lost count of the patients who called frustrated because they missed that window and assumed something was broken.
Unveiling The Future Of Healthcare Henry Ford Mychart Revolutionizes Patient Engagement
Here is the part nobody puts in the training materials: the real friction point is not the signup. It is the proxy access setup for parents managing care for adult children, or adult children managing care for aging parents. Epic updated their proxy policies a while back, and now you need explicit authorization. The system will not let you add someone as a proxy unless they approve it from their own account, and they will not approve it unless they understand why they are doing it. I had a case where a daughter was trying to manage her father's medications after a hospital discharge, and the entire process stalled for nine days because she did not realize the system required her father to initiate the proxy request from his own device. The workaround was simple once I knew it: call the clinic's health information management desk and request a paper proxy form instead. The digital path assumes both parties are equally tech-comfortable, which is rarely true in geriatric care scenarios. Another thing that trips people up is the medication reconciliation workflow. MyChart shows medications, but it does not always sync correctly with the pharmacy fill data. I had a patient who called saying his blood pressure medication had "disappeared" from his portal. It had not disappeared. It was listed under the brand name when his pharmacy dispensed the generic, and Epic's medication matching algorithm had not linked them. The fix was to print the medication list from the portal, bring it to the next appointment, and ask the provider to manually reconcile and re-enter it with both names attached. This took about ten minutes at the visit and resolved the confusion permanently. The messaging feature is where MyChart actually earns its keep, and also where it fails most quietly. Response time guarantees vary by practice. Henry Ford Health typically states 48 business hours for non-urgent messages, but in my experience, routine refill requests and lab follow-ups often get answers within 4 to 6 hours during weekdays. Weekend messages accumulate and get batched. If you send a message on Friday evening about something that is not an emergency, do not expect a response until Tuesday morning. The system does not differentiate urgency well on the patient side, which means patients sometimes send panic-level messages through the same queue as routine requests. I recommend adding a clear subject line that includes the word "urgent" only when it actually is urgent. The clinical staff filters by subject line first, and vague messages get deprioritized regardless of content.
Lab results are another area with a specific quirk. Epic releases labs to the patient portal automatically in most configurations, including Henry Ford's setup. However, some markers have delayed reporting windows. TSH, for example, can take three to five business days to appear even after the lab completes the run. Patients sometimes message saying their results never came back, when in reality the result is just pending in the lab information system. Knowing the typical turnaround times for different test categories prevents a lot of unnecessary support tickets. The appointment scheduling module works, but it has a frustrating limitation: you cannot schedule two appointments for the same provider on the same day through the portal. If you need a follow-up and a procedure on the same visit, you have to call the desk. This is a system constraint, not a bug, and it has not changed in years despite patient complaints. Billing and statements are integrated, which saves a step. You can view explanations of benefits, make payments, and set up payment plans directly in the portal. The one downside is that claim adjudication delays sometimes mean your portal balance shows the full charge before insurance has processed their portion. Do not panic and do not pay the full amount immediately. Wait 14 days and let the EOB update. Paying early just creates a credit balance that takes additional steps to resolve.
Get the Full Details

The mobile app adds some convenience but strips away functionality. Certain advanced features like downloading full visit summaries or accessing imaging reports are not available in the app. They require the web browser version. I always tell patients to use the app for quick checks and messages, but switch to a computer when they need to pull documentation for work or disability purposes. If you run into persistent activation issues that the online help cannot resolve, the Henry Ford Health patient relations line is the correct escalation path. The general clinic numbers will not help with portal technical problems, and transferring between departments wastes time. Going straight to patient relations gets you to someone who can check the underlying registration status in the Epic system and identify whether the issue is a demographic mismatch, a duplicate record, or an activation code error. The portal works well once you understand where the edges are. It is not intuitive by design, and the documentation assumes you already know how Epic structures data. That gap between what the system can do and what patients realize they can do is where most of the engagement happens, or fails to happen.