Postmortem CT Scanning: What Actually Happens When You Run A Cadaver Through The Machine
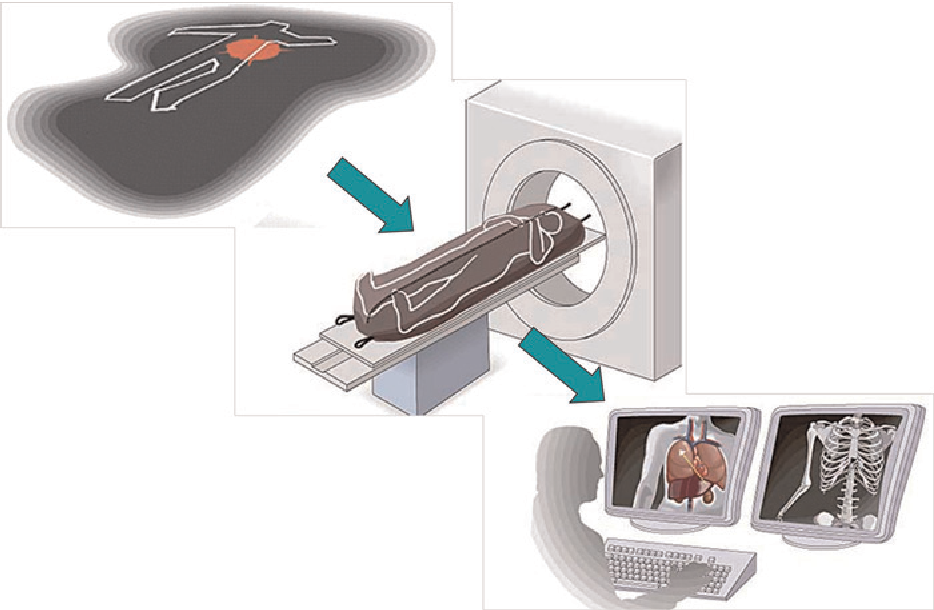
The first time I set up a postmortem CT scan, I spent forty-five minutes arguing with a radiology tech about whether we should sedate the deceased for the procedure. We did not sedate the deceased. The scan itself took about eight minutes for a full-body run on a 64-slice Siemens. The reconstructions took another twenty on the workstation. Total workflow from patient table to diagnostic report: roughly forty minutes. A conventional autopsy in our department runs two to three hours minimum, not counting histology. So let me walk through how this actually works in practice, including the stuff nobody puts in the brochures.
Unseen Data Revealed The Growing Role Of Ct Scans In Postmortem Investigations
What it is (without the marketing speak) Postmortem CT, sometimes called virtopsy when you combine it with 3D surface scanning and sometimes MRI too, is just computed tomography performed after death. The physics don't change. A CT scanner measures X-ray attenuation through tissue at multiple angles and reconstructs cross-sectional images. What changes is the context. Living patients move. They breathe. Their hearts beat. Dead patients do none of that, which sounds like a limitation but is almost always an advantage for imaging quality. The reason this field is growing has nothing to do with technology improving dramatically. CT scanners have been good for twenty years. The growth is driven by three practical pressures: families increasingly declining traditional autopsy for religious or cultural reasons, the legal system wanting more objective documentation, and coroners' offices being chronically understaffed and overworked.
The actual workflow Here's what a standard protocol looks like at our facility. The body is transported to the radiology department on a gurney. We remove any external monitoring leads, chest compression devices, endotracheal tubes if present, and anything metallic that isn't part of the body itself. Dental fillings, hip replacements, pacemakers stay. We position the body supine, secure the head with foam padding so it doesn't drift during the scan, and run a localizer scout view. That takes thirty seconds. Then we scan. Head and neck: 1mm slices, bone and soft tissue windows. Chest and abdomen: 1.25mm slices, same dual-window approach. Full body: 2.5mm slices for trauma survey. We typically get three datasets from one positioning. A standard study takes between six and twelve minutes of actual scan time depending on the protocol.
Get the Full Details
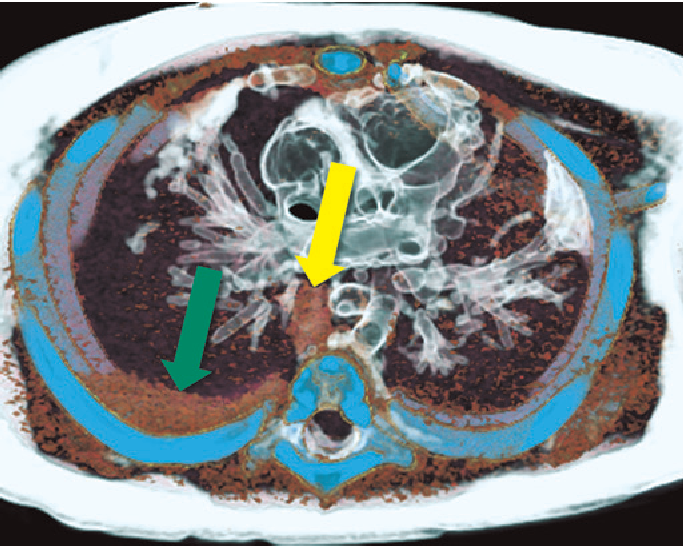
After the scan, the body goes back to the morgue. If we're doing a virtual autopsy only, that's it. If we're combining imaging with traditional autopsy, we use the CT data to plan the incisions. This is where it gets interesting. The scan might show a bullet fragment lodged near the superior mesenteric artery that we wouldn't have found by routine dissection alone. Or it might show nothing of significance and we proceed with a standard autopsy with confidence that we're not missing an obvious structural problem. Reconstruction and interpretation This is the part that eats time. Raw CT data is useless without processing. We run bone algorithm reconstructions for fracture assessment, soft tissue algorithms for organ evaluation, and volume rendering for 3D visualization. The volume rendering is what makes the evidence presentation work in court. A juror can understand a rotating 3D model of a skull fracture pattern far better than they can understand a verbal description or a flat 2D slice.
I spend about twenty to thirty minutes per case on post-processing, depending on complexity. A straightforward cardiovascular death might take ten. A multi-trauma case with thirty-seven fracture fragments and potential projectile tracking takes longer. We average about four hours from body arrival to finalized report, though complex medicolegal cases can stretch to a full day.
What CT Can And Cannot Tell You After Death
Where it excels Fractures. CT is genuinely superior to palpation and standard radiography for detecting fractures in the postmortem setting. I've seen cases where a sternal fracture was completely missed on external examination and only became obvious on the CT reconstruction. Rib fractures, especially posterior ones, are consistently underdetected by manual examination. Pelvic fractures that indicate significant blunt force trauma are immediately apparent on CT. Blood. Postmortem CT can detect intracranial hemorrhage, hemothorax, hemoperitoneum, and retroperitoneal bleeding. The blood appears hyperdense on non-contrast CT just like in living patients. This matters for establishing cause of death in trauma cases. A massive subdural hematoma visible on CT is a finding that stands up in court without relying solely on pathologist interpretation.

Foreign bodies and projectiles. Bullets, shrapnel, needles. CT localizes these with millimeter precision. We've tracked bullet trajectories that crossed multiple body compartments, identifying entrance and exit wounds that were ambiguous on external exam alone. This is particularly valuable in cases with multiple projectiles or when the body has been degraded. Air. Pneumothorax, pneumomediastinum, cerebral air embolism. Free air in the wrong places is visible on CT. Gas gangrene shows up as gas in soft tissues. Postmortem gas production in the liver and vessels is also visible, which actually helps us distinguish antemortem from postmortem gas patterns. Where it fails completely
Toxicology. A CT scan cannot tell you if someone died from fentanyl or cyanide or ethanol. This is the single biggest limitation and the one that surprises most people entering the field. You need blood, urine, and vitreous humor for toxicology. The CT tells you about structure. It tells you nothing about chemistry. Microscopic pathology. Myocardial infarction. The CT might show coronary calcification, which is a risk marker, but it cannot confirm acute plaque rupture or thrombosis. Early ischemic changes are invisible. You'll see a perfectly normal heart on CT from a patient who died of a massive anterior MI twenty minutes earlier. This is not a flaw in the scanner. It's a fundamental limitation of X-ray based imaging at the resolution we're working with. Inflammation and infection. Pneumonia is difficult to distinguish from dependent pulmonary edema on postmortem CT. Both appear as dense, gravity-dependent opacities. Without histology, you're guessing. We've had cases where pneumonia was the actual cause of death but the CT was indeterminate, and we had to go back to traditional autopsy to resolve it.
Poisoning and metabolic disturbance. Carbon monoxide poisoning doesn't show up on CT. Diabetic ketoacidosis doesn't show up on CT. Hyperkalemia doesn't show up on CT. If the cause of death is biochemical, the CT is going to be a waste of your time unless you're using it as a screening tool to rule out structural causes.

Specific Problems I've Faced And How I Worked Around Them
Decomposition gas mimicking pathology About two years ago, we received a body that had been deceased for approximately five days in warm weather. The external examination showed significant bloat. On CT, the entire venous system was filled with gas. The portal vein, the inferior vena cava, the hepatic veins — all of it looked like an air embolism. This is a known artifact of decomposition. Postmortem gas production by bacteria creates pressure that forces gas into the venous system, and it looks identical to a fatal air embolism on CT. If you report that as air embolism without considering decomposition, you've made a significant error. The workaround is straightforward but requires experience: compare the gas distribution pattern. Decompositional gas follows venous channels in a tree-like branching pattern that respects vascular anatomy. A true air embolism from trauma or procedural complication tends to be more focal and doesn't branch the same way. We also correlate with external findings — significant abdominal bloat and skin slippage point toward decomposition rather than an acute embolic event.
In that specific case, the body was from a residential care facility. The medical history suggested heart failure. The CT showed massive decompositional gas throughout the venous system but no focal traumatic injury. We concluded natural death from cardiac causes and the gas was an artifact. Had we missed that distinction, we could have opened a criminal investigation based on a misread CT finding. Dental work creating beam-hardening artifacts Another practical issue: dental amalgam and gold crowns create streak artifacts on CT that can obscure the base of the skull and the upper cervical spine. In a case involving suspected blunt force trauma to the head, the artifacts from a full-mouth dental bridge made it nearly impossible to evaluate the skull base for fractures. We couldn't rule out a basilar skull fracture because the reconstruction was compromised.
The workaround was to acquire a high-resolution cone-beam CT scan, which uses a different geometry and has less susceptibility to the same type of beam hardening. The cone-beam data cleared the skull base and showed no fracture. Without that secondary scan, we would have had to proceed to traditional dissection of the skull base, which is invasive and time-consuming. Not every facility has access to cone-beam CT. In those settings, the alternative is to use metal artifact reduction algorithms if your CT software supports them, or simply accept the limitation and document it in your report. Documentation matters. Saying "skull base evaluation limited by dental artifact" is honest and defensible. Saying nothing and missing a fracture is not.

Practical Considerations For Setting This Up
Cost and access A single postmortem CT scan at our institution costs roughly the same as a contrast-enhanced CT angiogram in the living patient, which puts it in the eight hundred to fifteen hundred dollar range depending on your payer mix. This is significantly cheaper than a full traditional autopsy when you factor in pathologist time, histology processing, and report generation. But the capital cost of the scanner is the barrier. Most medical examiners' offices do not own CT scanners. They contract with hospitals or imaging centers. The contracting model works but introduces logistical friction. The body needs to reach the scanner within a reasonable timeframe. Decomposition progresses. Imaging quality degrades as gas production advances. We try to scan within twenty-four hours of receipt whenever possible. Bodies held longer than seventy-two hours without refrigeration become progressively more difficult to interpret.
Legal admissibility Postmortem CT findings are admissible in court in most jurisdictions now. The Daubert standard has been applied to virtopsy in several appellate decisions. The key is proper chain of custody, documented protocol, and qualified interpretation. Your report needs to state what the CT can and cannot determine. Overclaiming is the fastest way to get your testimony challenged. "The CT demonstrates a fracture of the C2 vertebra" is appropriate. "The CT confirms that the C2 fracture caused death" is not — cause of death requires correlation with all available evidence. Training
The biggest bottleneck in this field is not equipment. It's trained interpreters. Radiologists who read living CT scans do not automatically know how to read postmortem CT scans. The appearance of organs changes after death. Dependent lividity mimics consolidation. Gas in the portal system is normal in decomposed bodies but looks pathological to an untrained eye. I spent roughly six months studying postmortem CT literature and reviewing reference atlases before I felt comfortable interpreting these studies independently. The learning curve is steeper than it should be because there aren't many formal fellowship programs in this subspecialty yet.

When To Order A Postmortem CT And When To Skip It
Order it when the question is structural. Trauma assessment. Unknown cause of death where structural pathology is likely. Cases where family refusal of traditional autopsy is anticipated. Child abuse investigations where skeletal trauma is the primary concern. Exhumations where traditional autopsy is limited by decomposition. Skip it, or use it only as an adjunct, when the clinical question is biochemical or microscopic. Suspected overdose without trauma. Sudden cardiac death in a patient with known coronary disease. Cases where toxicology is the primary diagnostic question. The CT will be normal in all of these and won't help you reach a diagnosis. The strongest applications combine CT with targeted traditional autopsy. Use the imaging to identify what needs dissection and what doesn't. This focused approach can reduce autopsy time by forty to sixty percent in trauma cases while actually improving diagnostic yield because you're directing your dissection toward findings that the CT flagged as significant.
We ran a pilot program comparing full traditional autopsy against CT-first then targeted autopsy for a series of homicidal trauma cases. The CT-first pathway identified all fractures and foreign bodies that the traditional autopsy identified. It found two additional rib fractures that were missed on gross examination. It failed to diagnose a pulmonary embolism in one case where the clot was soft and Ischemic heart disease in two cases where there were no gross coronary changes. Total time savings averaged three hours per case. The families reported higher satisfaction because the imaging provided visual evidence they could understand, even when the final cause of death required traditional tissue sampling to confirm. The field is moving forward but slowly. Every paper I read claims that virtopsy will replace traditional autopsy within a decade. That hasn't happened and won't happen in the next decade either. The biochemical limitations are fundamental, not technical. But for the right cases, postmortem CT is already indispensable. It's not a replacement for pathology. It's a different tool in the same toolkit, and it's one that more coroners and medical examiners should be using sooner rather than later.
