Understanding Anxiety, OCD, and Related Disorders: A Practical Guide
Most people who come across these conditions initially misunderstand them. They think of anxiety as just feeling worried. They think of OCD as being overly tidy. Both are wrong, and those misunderstandings make treatment harder, not easier. I want to walk through what actually happens in these disorders, how you can start making sense of them, and where most people get stuck. This is not a substitute for professional care. It is something I wish I had when I first started trying to understand my own patterns.
Unraveling The Strands Of Anxiety Obsessive Compulsive And Related Disorders Understanding Atis
The acronym ATIS comes up in some clinical circles, though you will not find it standardized in every textbook. It generally refers to a framework for looking at Anxiety, Trauma, Insomnia, and Somatic symptoms as interconnected rather than separate problems. The insight there is practical: treating one strand in isolation often leaves the others intact. I saw this play out repeatedly with a client who had been treated for what looked like pure OCD. Exposure and response prevention helped somewhat, but the sleep disruptions kept getting worse, and the anxiety rebounded between sessions. Once we started mapping the insomnia and the trauma history onto the same timeline as the compulsions, the picture changed. The compulsion was not just about contamination. It was about exhausting the nervous system so thoroughly that sleep became possible. That changes the treatment approach significantly. Here is the counter-intuitive part that most beginner therapists miss. In OCD and related disorders, reducing anxiety through avoidance or compulsion does not actually reduce the disorder. It reinforces the neural pathway that says the feared outcome is real and only prevented by the ritual. The uncomfortable truth is that the very thing that provides temporary relief is what keeps the cycle running. You have to be willing to sit in the discomfort without performing the ritual, and that is genuinely difficult to do without guidance.
How These Disorders Actually Present
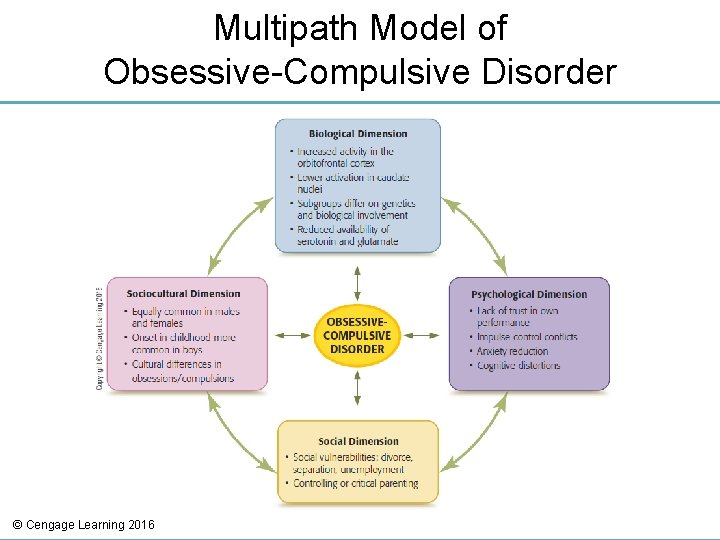
Anxiety disorders exist on a spectrum, but the key distinction most people miss is between state anxiety and trait anxiety. State anxiety is a reaction to a specific situation. Trait anxiety is your baseline. OCD and related disorders are not simply high trait anxiety. They involve specific cognitive patterns: thought-action fusion, inflated responsibility, and intolerance of uncertainty. These are measurable constructs with validated scales behind them. Obsessive-Compulsive and Related Disorders include body dysmorphic disorder, hoarding disorder, trichotillomania, excoriation, and obsessive-compulsive personality disorder. The last one is frequently confused with OCD itself. OCPD is about perfectionism and control as a personality structure. OCD is about intrusive thoughts and compulsions that feel ego-dystonic, meaning they conflict with the person's actual values. Mixing these two up leads to completely wrong treatment strategies. Related disorders like trichotillomania and excoriation share mechanisms with OCD but present differently. The urge is often premonitory, a building tension that releases when the behavior occurs. This is closer to a habit loop than a fear-based compulsion. Treatments that work for classic OCD do not always transfer cleanly here.
Get the Full Details

Practical Assessment: Where to Start
If you are trying to understand your own patterns or someone else's, start with a structured inventory. The Yale-Brown Obsessive Compulsive Scale is the standard for OCD severity. The GAD-7 covers generalized anxiety. For related disorders, the Barratt Impulsivity Scale and specific scales for hair-pulling and skin-picking can help differentiate. One specific problem I ran into involved a patient who scored low on standard OCD measures but had severe ritualistic behaviors around checking and counting. The issue was that their obsessions were not purely cognitive. They were sensory. The urge was not about preventing harm but about achieving a specific tactile sensation. Standard ERP protocols assume cognitive obsessions. When the obsession is sensorimotor, the protocol needs adjustment. I worked around this by introducing sensory-based exposure tasks rather than purely cognitive ones. It took longer to find the right framework, but the standard tools were just not mapping correctly to what was actually happening.
Treatment Approaches That Actually Have Evidence
Exposure and Response Prevention remains the gold standard for OCD. The mechanism is straightforward but not simple to execute. You expose the person to the feared stimulus and prevent the compulsive response. Over time, the anxiety decreases through habituation and, more importantly, through predictive coding updates in the brain. The brain learns that the feared outcome does not occur, even without the compulsion. For anxiety disorders, cognitive restructuring and exposure are the two active ingredients. Mindfulness-based approaches show moderate evidence but are not standalone treatments for clinical anxiety. Medication, particularly SSRIs, can reduce symptom severity enough to make therapy more effective. The combination usually outperforms either alone for moderate to severe cases. For hoarding disorder, standard OCD treatments perform poorly. The active components are different: decision-making training, skill-building around organization, and extended exposure to discarding. Treating hoarding like OCD is one of the most common mistakes I see, and it wastes months of a person's time.
Common Pitfalls
The biggest mistake people make is expecting linear progress. These disorders improve in waves. You will have three good weeks followed by a week that feels worse than when you started. This is normal. It does not mean the treatment is failing. What it usually means is that you have moved to a harder exposure level, and the nervous system is recalibrating. Another pitfall is confusing symptom reduction with recovery. If you are performing fewer rituals but only because you are too exhausted to do them, the underlying disorder is still active. True recovery means the rituals lose their psychological grip, not just that you lack the energy to maintain them. medication management is also frequently mishandled. SSRIs used for OCD typically require higher doses than those used for depression, and they take longer to work. Six to eight weeks at a therapeutic dose is the minimum before judging effectiveness. Many people discontinue too early and conclude the medication does not work, when the actual issue was insufficient dosage or duration.

When Standard Approaches Fail
Some cases resist first-line treatment. This is not rare. Approximately twenty to thirty percent of OCD patients do not respond adequately to standard ERP. In those cases, options include switching to clomipramine, adding low-dose antipsychotic augmentation, or trying intensive residential programs. Deep brain stimulation and transcranial magnetic stimulation have evidence for treatment-resistant cases but are not first-line interventions. The hardest truth about these disorders is that they tend to be chronic. Remission is absolutely possible, but relapse risk never drops to zero. The goal is management and quality of life, not necessarily permanent eradication of all symptoms. Anyone promising a complete cure is not being honest with you. The most useful thing you can do is build a detailed understanding of your own specific presentation. The categories help, but the individual variation is enormous. Two people with the same diagnosis can have fundamentally different mechanisms driving their symptoms. Mapping yours accurately is the single most important step toward effective treatment.


