Getting Actual Numbers Out Of Your Breathing
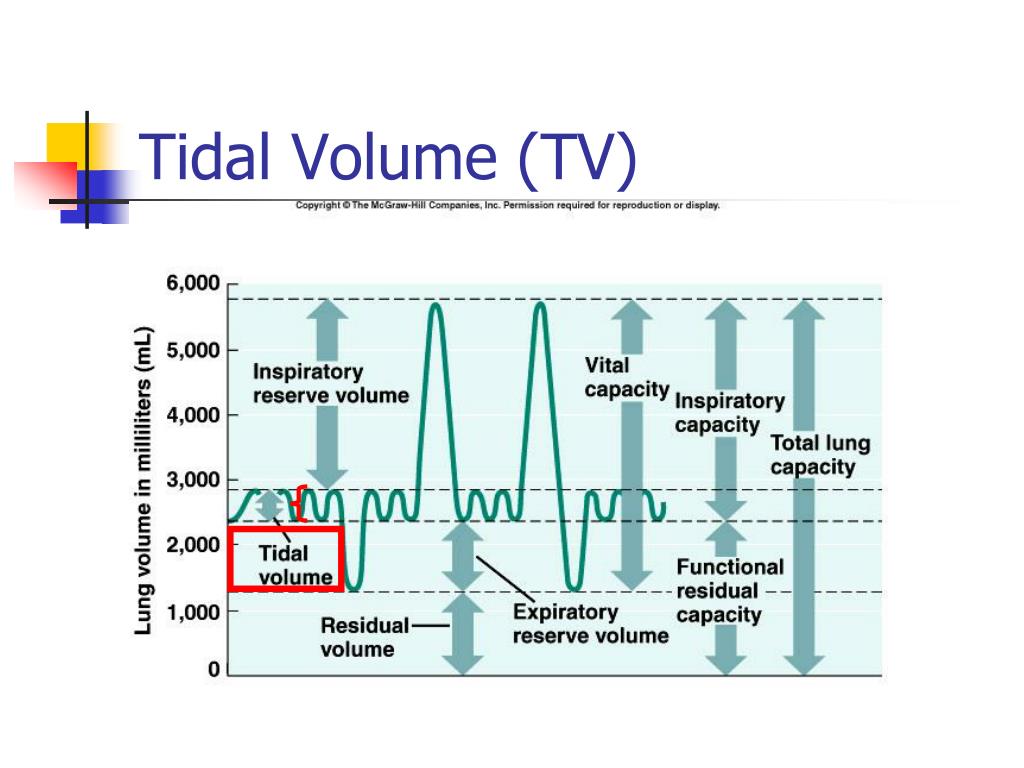
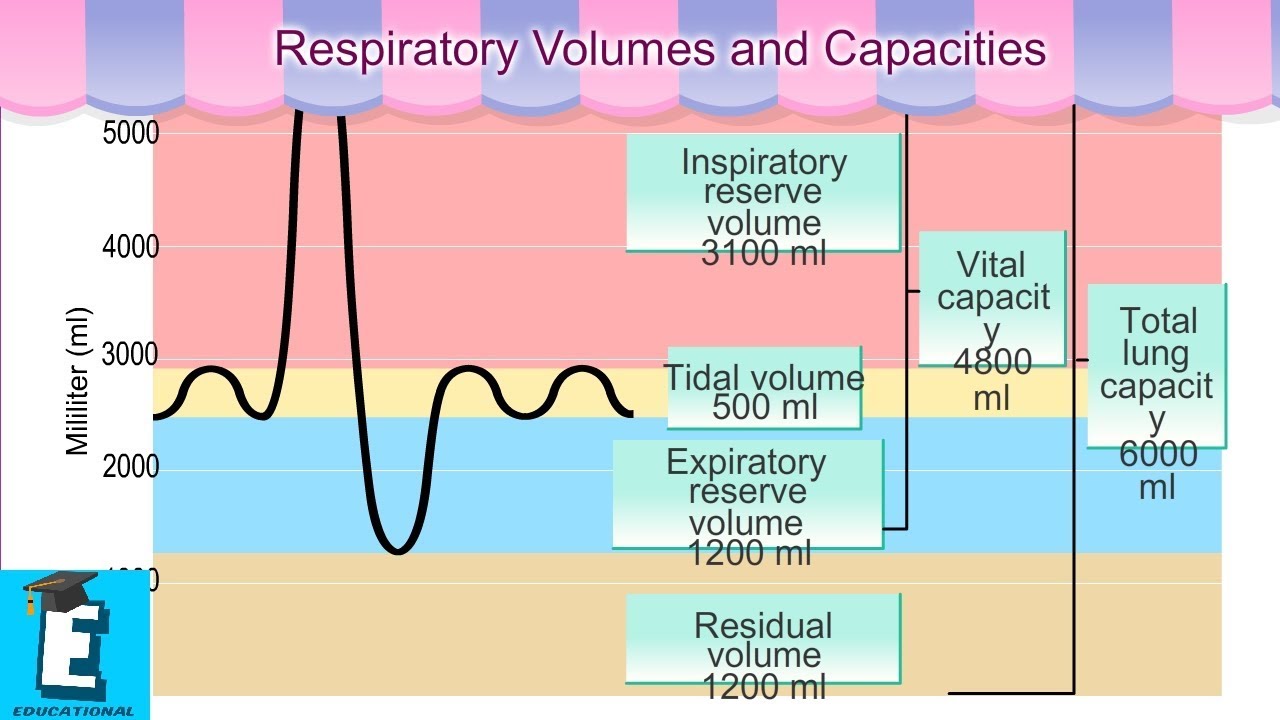
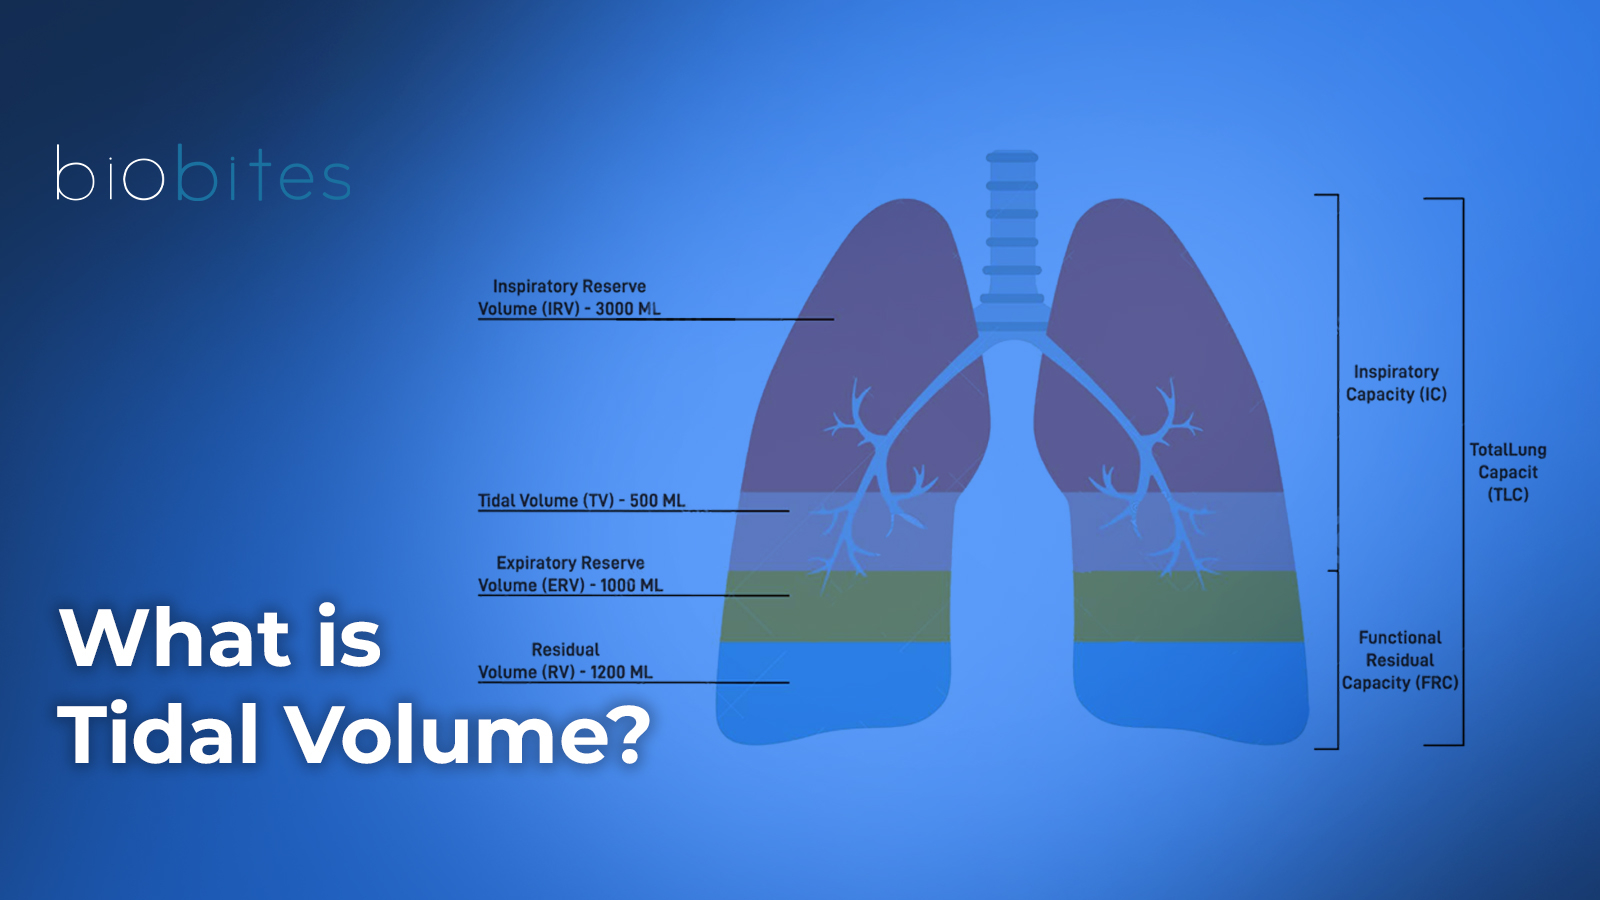
Tidal volume is the amount of air you move in and out during a normal breath at rest. Most people estimate it without realizing it, somewhere around 500 milliliters for an average adult. That number shifts depending on body size, fitness level, and whether you are actually relaxed or just pretending to be. Getting a real reading requires either a spirometer or a budget-friendly flow sensor, and the process is not as straightforward as breathing into a plastic tube. I used to work in a pulmonary lab where we calibrated devices weekly because the sensors drifted fast in humid climates. One particular issue I ran into involved a patient whose tidal volume readings looked normal on paper but were actually garbage. The problem was that the sensor had a built-in leakage tolerance of about 5%, and the mask seal was slightly compromised. Small leaks upstream of the sensor get interpreted as lower volumes, and the machine compensates by inflating the numbers. I solved it by placing a second low-resistance pressure transducer near the mask interface and cross-referencing both datasets. If the difference exceeded 8%, I flagged the trial as unreliable rather than trying to fix it in post-processing.
Unraveling The Mystery Of Tidal Volume A Comprehensive Guide To Measuring Respiratory Health
Start by acquiring a reliable measurement tool. Disposable pneumotachographs give decent readings for one-time use and cost roughly $15 to $30 each. Reusable ultrasonic flow meters run $200 to $600 but last for years if you maintain them properly. The tradeoff is calibration drift on cheap units, which accumulates over time and skews results without any obvious warning. Fit the sensor assembly according to the manufacturer's instructions. For mouthpiece setups, use a nose clip to prevent nasal bypass. For mask-based systems, ensure the seal covers both nose and mouth without excessive tightness. A seal that is too tight compresses facial tissue and alters natural breathing patterns, which invalidates the resting state you are trying to measure. Have the subject sit upright and breathe normally for two minutes before starting data collection. The first thirty seconds are always noisy because people adjust their posture and breathing rate when they realize they are being monitored. Discard that warm-up period. Record at least three minutes of stable, resting breathing. Sample at 100 Hz or higher if your device supports it. Lower sampling rates miss the peak inspiratory and expiratory flow points, which throws off volume integration.
Export the raw flow data and integrate it over time to get volume per breath. Most software packages handle this automatically, but verify the baseline. A drifting baseline means the sensor or the analog-to-digital converter is unstable. If the zero-line wanders more than 50 mL over the recording window, recalibrate and repeat. From the integrated trace, extract tidal volume for each breath cycle. Average across at least ten complete cycles. Report the mean and standard deviation. A standard deviation above 75 mL suggests inconsistent breathing, which usually means the subject is anxious, counting their breaths, or the equipment is introducing artifacts. Normal tidal volume for a healthy adult at rest falls between 400 mL and 600 mL. Athletes and larger individuals can comfortably sit at 700 mL to 900 mL without effort. Values below 300 mL at rest often indicate restrictive lung disease or shallow breathing patterns from pain or anxiety. Values consistently above 1 L at rest in a non-athlete usually signal compensatory hyperventilation or metabolic acidosis, though it can also just mean the person is nervous during testing.
Get the Full Details
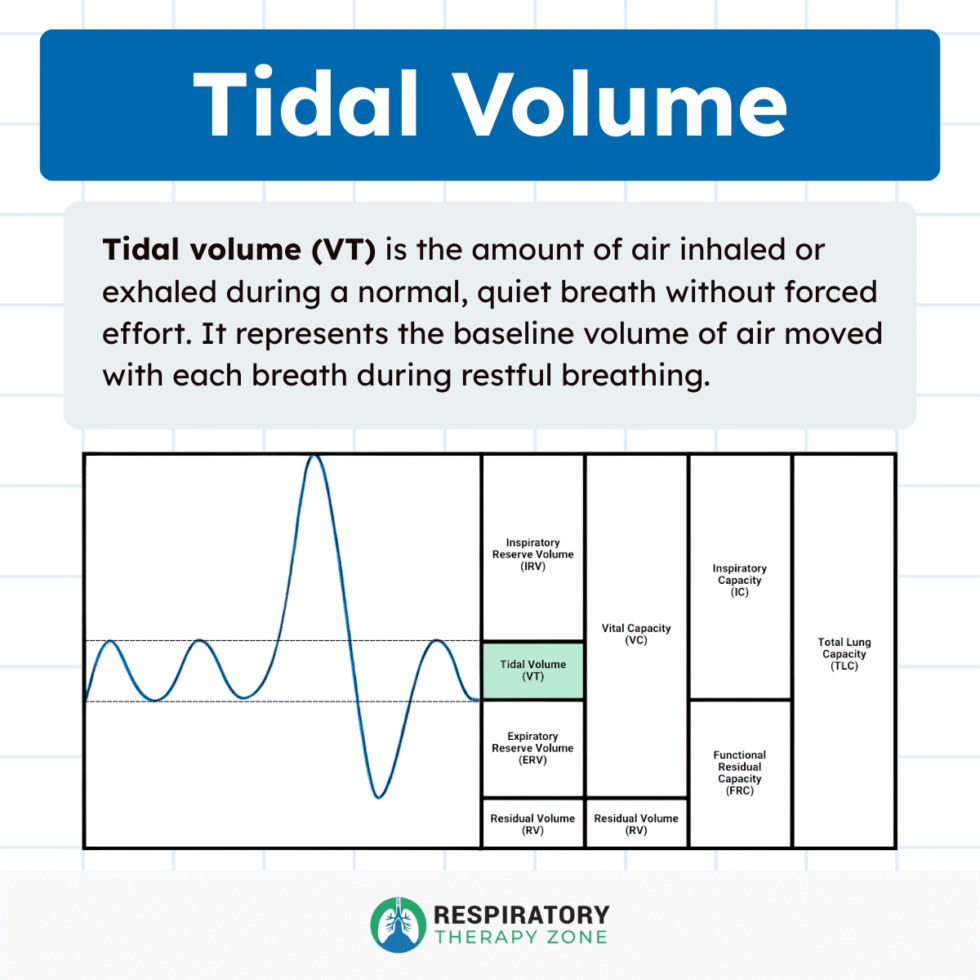
One thing most guides skip over: tidal volume changes dramatically with speaking, walking, and even emotional state. A resting measurement tells you very little about functional respiratory capacity. If you want meaningful data, record tidal volume during light activity as well. Walking at a normal pace typically increases tidal volume to 1 L to 1.5 L in healthy adults. If it stays below 800 mL during light exercise, that is worth investigating further. The biggest limitation of consumer-grade respiratory monitoring is accuracy. Smartphone apps that claim to measure tidal volume through the microphone are essentially useless. They detect sound amplitude, not airflow volume, and the correlation is weak at best. For anything beyond casual curiosity, invest in a proper flow sensor and follow a validated protocol. If you need continuous monitoring over days rather than single snapshots, consider a piezoelectric belt-based tracker. These measure chest wall expansion rather than direct airflow. They are less precise than pneumotachographs but practical for long-term trend tracking. Expect about 10% to 15% error compared to gold-standard spirometry, which is acceptable for monitoring trends in known conditions but not for diagnosing new ones.
Download links and specific product recommendations depend on your region and budget. The key is matching the tool to the question. A one-time clinical assessment needs a calibrated spirometer. Daily tracking for sleep apnea management might justify a piezo belt. Never buy the cheapest option and expect clinical-grade results. Sensors degrade. Calibration matters. Readings without context are just numbers.