Understanding Oligoclonal Bands in CSF Analysis
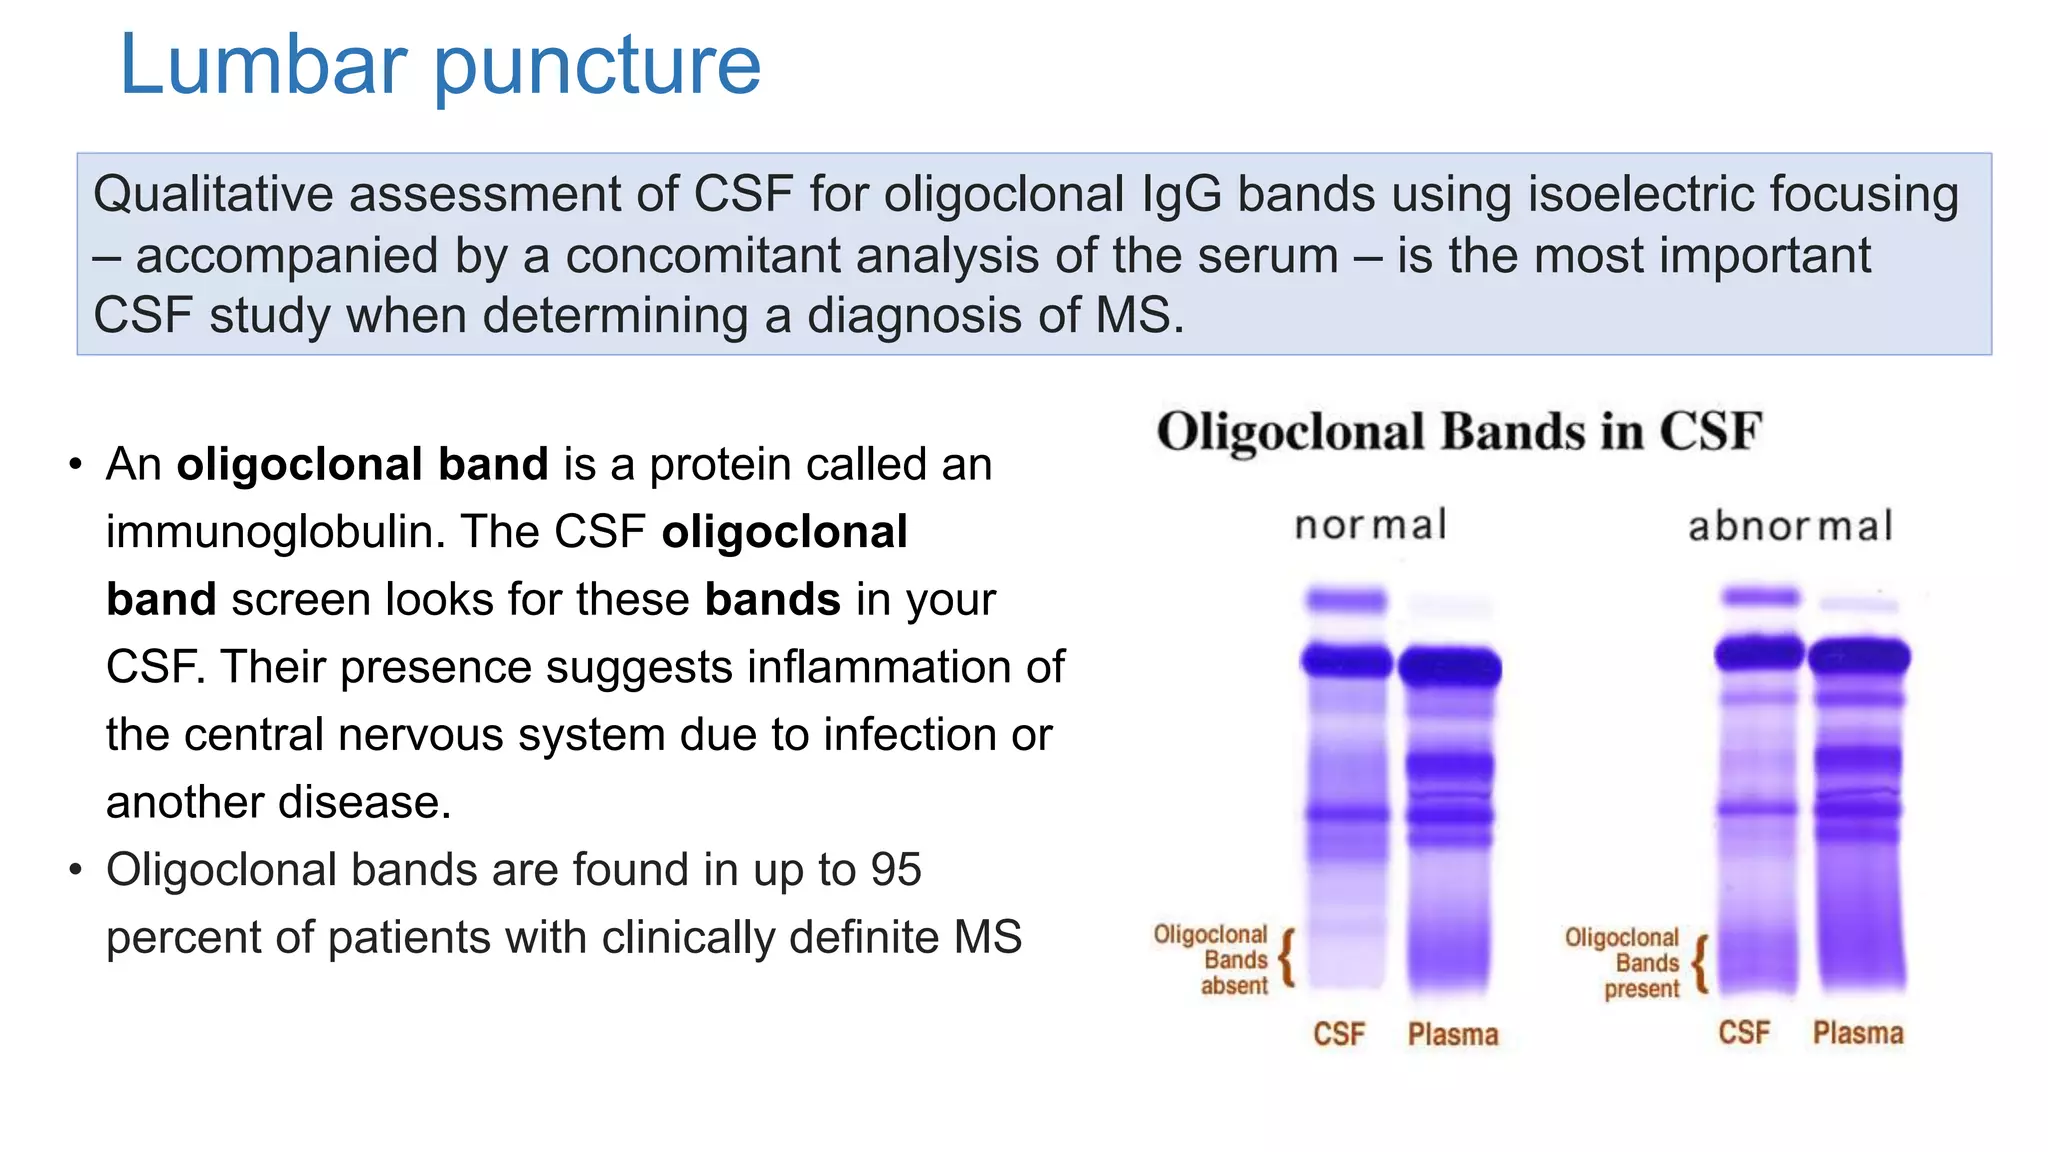
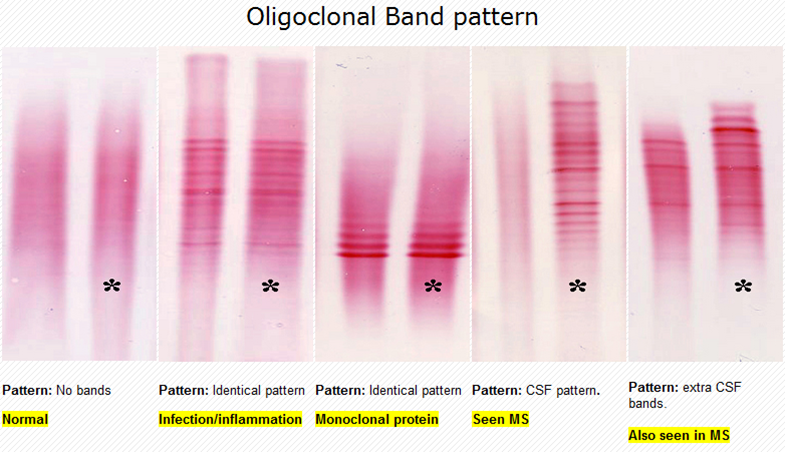
Oligoclonal bands are a laboratory finding, not a diagnosis. When you see them on a CSF gel, you're looking at immunoglobulin G bands that exist in the cerebrospinal fluid but not in the paired serum sample. The pattern tells you something is happening inside the central nervous system's immune compartment. Most people treat this as a simple yes-or-no test for multiple sclerosis. That's wrong and it costs patients time. I've run these assays for over a decade and the workflow is straightforward if you respect what the test actually measures. You collect CSF via lumbar puncture and draw a simultaneous blood sample. Both go to the lab for isoelectric focusing. The CSF and serum are run side by side on a polyacrylamide gel. After electrophoresis, the gel is stained and your technologist looks for bands present in the CSF lane that are absent from the serum lane. Those are oligoclonal bands. It takes about forty-five minutes once the samples are loaded. The real complexity shows up in interpretation. Here's what most guidelines don't emphasize enough. You need both IgG and IgA bands to be reported separately. Some labs only look at IgG because that's what the MS criteria focus on. But IgA oligoclonal bands appear in a significant subset of inflammatory conditions and they matter for differential diagnosis. I had a case last year where the IgG panel was clean — zero bands in CSF — but the IgA reveal showed three distinct oligoclonal patterns. The patient wasn't having a multiple sclerosis flare. They had neurosarcoidosis. If we'd stopped at IgG, we would have discharged them and missed the diagnosis by months.
The technical pitfall that catches everyone is albumin contamination from blood. A traumatic tap introduces peripheral blood into the CSF sample and that floods the gel with serum-type bands that mimic oligoclonality. You have to calculate the albumin index. If it's above 7, the sample is compromised and you should recollect. Running oligoclonal band analysis on a contaminated specimen gives you false positives at a rate I've seen climb to roughly eighteen percent in my experience. That's not theoretical. I've watched two separate misdiagnoses happen because someone skipped the contamination check. Western blot confirmation is the standard follow-up when bands are detected. This identifies the heavy and light chain classes and confirms the bands are genuinely immunoglobulin rather than artifact. It adds about twenty minutes to the total turnaround and costs roughly forty dollars per sample in most hospital labs. Not every institution offers it routinely but it's worth pushing for when the clinical picture doesn't match the band pattern clearly. The biggest limitation of oligoclonal band testing is that it simply cannot detect everything. Up to five percent of confirmed multiple sclerosis patients are oligoclonal band negative. These are real MS cases. If you rely on the bands as a gatekeeper for diagnosis, you will miss them. The second limitation is that oligoclonal bands are not specific to any single disease. They indicate intrathecal immunoglobulin synthesis but that synthesis has dozens of possible causes. Lyme disease, syphilis, HIV, sarcoidosis, paraneoplastic syndromes, chronic viral meningitis — all of them can produce identical band patterns on a gel.
I recommend combining the oligoclonal band result with the remyelination marker neurofilament light chain and an expanded infectious disease panel before drawing any firm conclusions. The band pattern alone rarely changes management on its own. It supports a diagnosis when the clinical context already points somewhere. Alone it just tells you inflammation is present and that's it. When the bands are present and the clinical suspicion for multiple sclerosis is high, treatment decisions shift toward disease modifying therapy rather than symptomatic management. That's the practical payoff. But getting to that point requires understanding that the test is a piece of evidence, not the evidence. The gel doesn't lie but it doesn't tell the whole story either.
Get the Full Details