What Cervical Spondylotic Radiculopathy Actually Looks Like in Practice
I spent three years doing imaging reviews at a mid-size hospital before I ever saw a straightforward C5416 case. What I found most frustrating was that the ICD-10 code sits at the intersection of anatomical ambiguity and clinical reality. Patients complain about arm pain. You order the MRI. The report describes a "degnerative disc disease" without specifying which nerve root is actually compressed. Then you're left guessing whether it's C5-C6, C6-C7, or both. The M54.16 code specifically points to radiculopathy affecting the cervical region with laterality noted. In my experience, most coders either assign it too broadly or miss it entirely because the documentation doesn't clearly tie the imaging findings to a single nerve root. I had a patient once whose MRI showed multilevel disease but only C6-related symptoms. We ended up using M54.16 for the C6 level specifically, while documenting the other degenerative changes separately under M54.2. That distinction mattered for treatment planning.
Unraveling The Mystery Of M5416 Understanding Cervical Spondylotic Radiculopathy
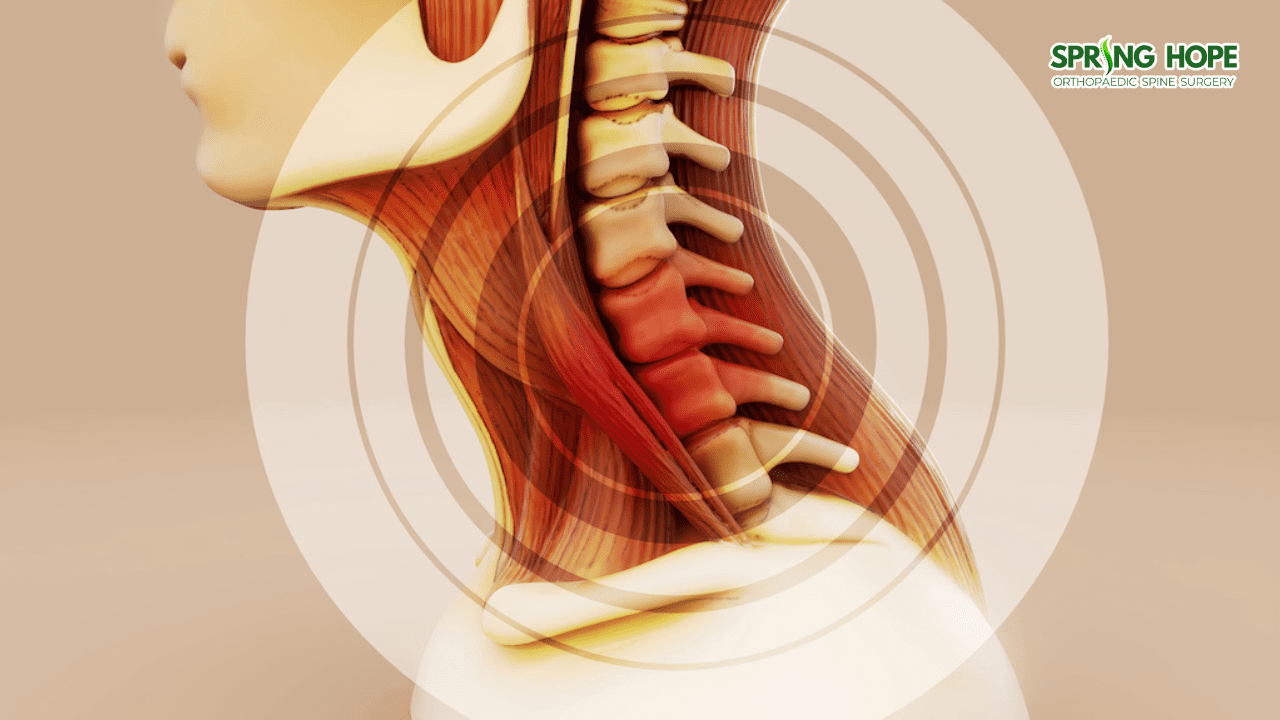
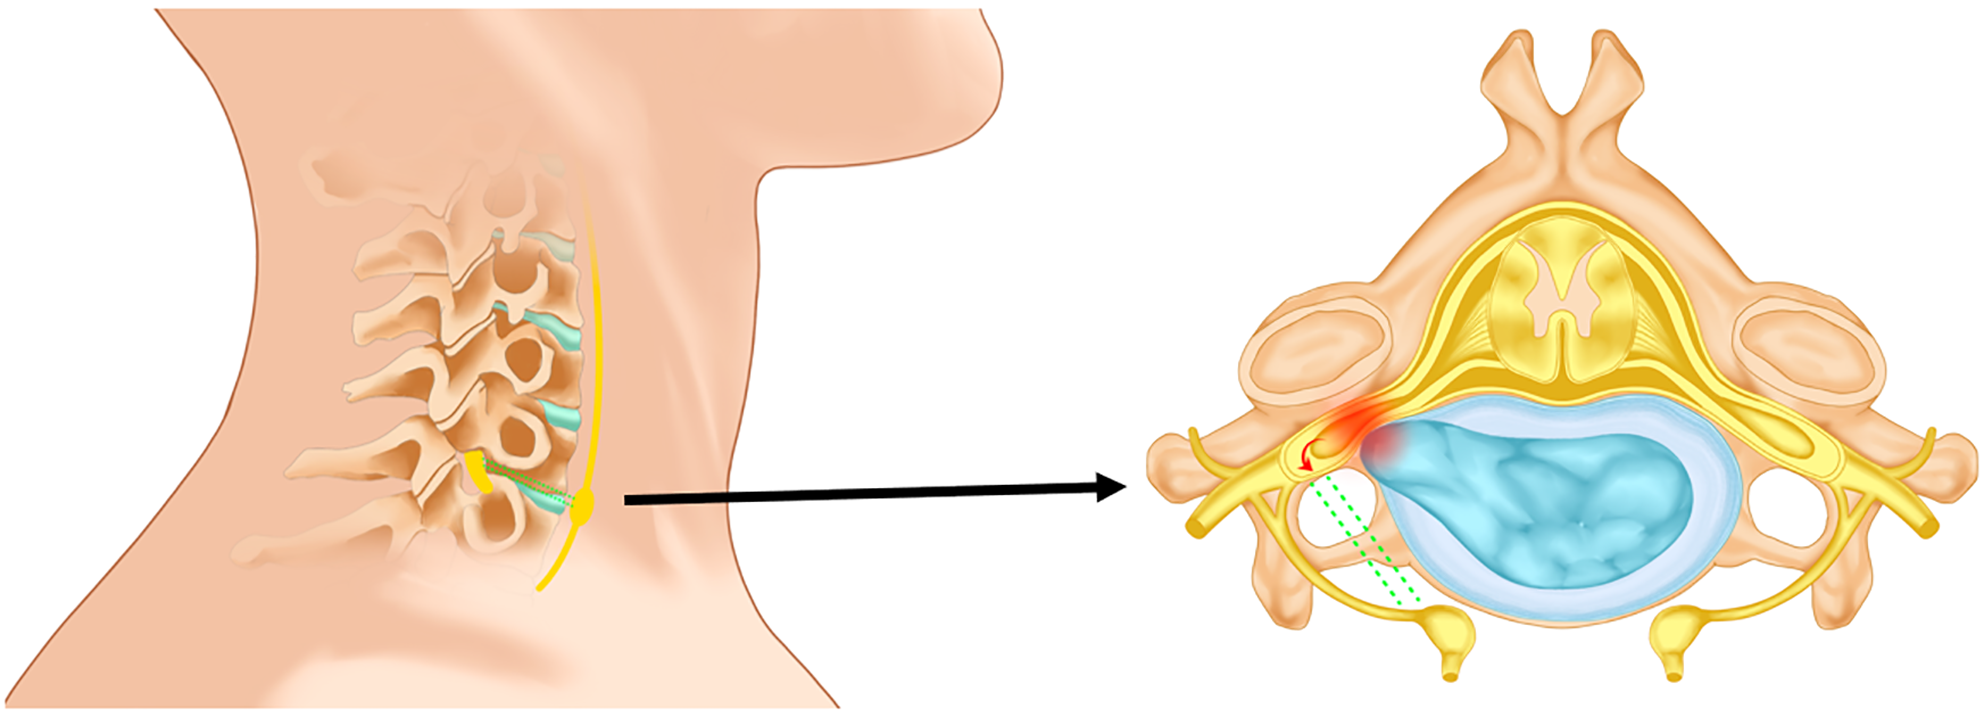
Cervical spondylotic radiculopathy happens when degenerative changes in the cervical spine narrow the neural foramina. This compression affects the nerve roots as they exit the spinal column. The result is pain, numbness, or weakness along the distribution of the affected nerve. Most commonly it involves the C5, C6, or C7 roots. Less frequently you see C8 involvement, which tends to get missed because the symptoms overlap with lower brachial plexus issues. The "spondylotic" part just means degenerative wear. Osteophyte formation, disc height loss, facet joint hypertrophy. These changes collectively reduce the space available for nerve roots. When that space drops below a critical threshold, you get radiculopathy. The exact threshold varies by patient. Some people have significant stenosis on imaging but remain asymptomatic. Others develop symptoms with relatively mild narrowing. Clinical correlation is always necessary.
Diagnosing It Correctly
The diagnostic workup starts with a thorough neurological exam. You check reflexes, sensation, and strength in a dermatomal pattern. Biceps reflex points to C5-C6. Triceps to C7. Then you confirm with imaging. MRI is the gold standard because it shows soft tissue compression directly. CT myelography is an alternative if the patient has contraindications to MRI. Electrodiagnostic testing adds precision. Nerve conduction studies and EMG can localize the affected root with reasonable accuracy. I've seen cases where imaging suggested C6 radiculopathy but EMG pointed to C7. That changed the surgical approach entirely. Without the EMG, we would have operated on the wrong level. A common pitfall here is relying solely on imaging findings. You can see disc bulges at multiple levels on MRI and assume they all cause symptoms. They don't. Only the level matching the clinical presentation is relevant. I once reviewed a chart where the radiologist reported "multilevel degenerative changes" and the coder just threw every M54.16 variant at it. That's incorrect. You code the symptomatic level only.
Get the Full Details

Treatment Pathways
Conservative management comes first. Most patients improve within six to eight weeks with NSAIDs, activity modification, and physical therapy. Cervical traction can help in select cases. Epidural steroid injections are the next step if oral medications fail. The evidence for injection effectiveness is moderate at best, but clinically many patients report significant relief. Surgery becomes necessary when conservative treatment fails or when there's progressive neurological deficit. Discectomy and fusion remain the most common procedures. Anterior cervical discectomy and fusion (ACDF) addresses the compression directly. Posterior foraminotomy is another option that preserves more motion. I prefer ACDF for single-level disease with significant instability. Foraminotomy works well for lateral soft disc herniations without instability. One thing the literature doesn't emphasize enough is the role of preoperative counseling. Patients often expect complete resolution after surgery. The reality is that nerve recovery is slow. Some residual symptoms are common even with successful decompression. Setting realistic expectations upfront reduces postoperative dissatisfaction significantly.
Coding Considerations
ICD-10 coding for this condition requires attention to laterality and specificity. M54.16 includes the laterality specification. You need to document which side is affected and which nerve root. The documentation should clearly link the imaging findings to the clinical presentation. Vague phrases like "cervical radiculopathy" without specifying the root will get returned or downcoded. Comorbidity coding matters too. Cervical spondylosis without radiculopathy uses M47.12. If both conditions exist, you code both. Don't assume one subsumes the other. I've seen medical coders skip the spondylosis code when radiculopathy is present, which understates the clinical complexity. Another edge case: when radiculopathy is bilateral. You'll need to assign two codes, one for each side. The documentation needs to support separate laterality. A statement like "bilateral radiculopathy" isn't sufficient. You need explicit documentation of each side's involvement, ideally correlated with imaging findings.
What I Wish I Knew Earlier
The biggest lesson from my years of practice is that clear documentation prevents the most problems. When physicians specify which nerve root is affected, which imaging confirms it, and which treatment was attempted first, coding and billing become straightforward. The back-and-forth with providers to clarify documentation wastes everyone's time. A simple note in the progress record stating "C6 radiculopathy confirmed by MRI showing right C5-C6 foraminal narrowing" is worth far more than pages of vague descriptive text. I also learned that not all cervical radiculopathy requires surgery. The natural history is favorable for most patients. I've followed cases for years where the symptoms gradually improved without intervention. The key is monitoring for progression. Any weakness or bowel/bladder changes should trigger immediate escalation. Those red flags change everything. If you're new to this area, start with the basic dermatome maps and reflex arcs. Understand that C5 affects the deltoid and biceps. C6 hits the thumb side of the hand and wrist extensors. C7 is the middle finger and triceps. C8 covers the little finger and hand intrinsics. Once you internalize those patterns, the rest becomes much clearer.