Endometriosis Is Not Just Painful Periods
Most people who get a delayed diagnosis spend years being told their symptoms are normal. The average time from first symptom to confirmed diagnosis is about seven to nine years. That gap exists because endometriosis doesn't announce itself clearly on standard imaging, and the medical system still treats it as a gynecological inconvenience rather than a systemic inflammatory condition. I've seen patients cry in exam rooms after being dismissed for three years of debilitating pain, only to have a surgeon find stage 4 disease at laparoscopy. It happens constantly. Here's what actually distinguishes endometriosis from regular menstrual cramps. Standard period pain, or dysmenorrhea, typically causes cramping in the lower abdomen for one to three days per cycle and responds reasonably well to NSAIDs like ibuprofen or naproxen. Endometriosis pain is different. It often radiates to the lower back and thighs. It can persist throughout the entire cycle, not just during bleeding. The pain frequently worsens with bowel movements, urination, or sexual intercourse, depending on where the lesions are located. Some people experience what's called "cyclical" pain that builds several days before their period and lingers after it ends. Others have constant baseline pain with flares. Both patterns are valid. The disease works by having tissue similar to the uterine lining grow outside the uterus. This ectopic tissue responds to hormonal changes just like the lining inside the uterus does. It thickens, breaks down, and bleeds during each cycle. But unlike internal menstrual bleeding, this external bleeding has no exit route. It gets trapped, causing inflammation, scar tissue formation, and adhesion development between organs. Over time, this chronic inflammatory state can affect surrounding structures beyond the pelvic region.
There are different types of endometriosis, and knowing which type you're dealing with matters significantly for treatment decisions. Superficial peritoneal implants sit on the surface of pelvic organs and are the most common type. These can be subtle and easy to miss during surgery if the surgeon isn't looking carefully, especially when they appear as clear or powder-burn spots rather than obvious raised lesions. Deep infiltrating endometriosis, or DIE, penetrates more than five millimeters beneath the peritoneal surface. This is the type most likely to cause bowel symptoms, urinary issues, and severe pain because it invades deeper structures. Endometriomas are ovarian cysts filled with old blood, sometimes called chocolate cysts. They're relatively easy to detect on ultrasound but can recur after surgical removal. A rare but serious presentation is extrapelvic endometriosis, where tissue implants appear in the lungs, diaphragm, or surgical scars. Thoracic endometriosis can cause catamenial pneumothorax, which is a collapsed lung that happens in sync with your menstrual cycle. Diagnosis remains the biggest bottleneck in managing this condition. The gold standard is still surgical visualization through laparoscopy with histological confirmation. You need to actually see the lesions and have them biopsied. Transvaginal ultrasound is useful but has significant limitations. It can detect endometriomas and sometimes identify deep infiltrating nodules, particularly when performed by a specialized sonographer familiar with endometriosis mapping. However, superficial peritoneal endometriosis is frequently invisible on ultrasound. MRI is more sensitive than ultrasound for deep disease but still misses superficial implants. The reality is that a negative ultrasound or MRI does not rule out endometriosis. I had a patient who had multiple clear ultrasounds over two years, normal MRI results, and was told nothing was wrong. She went in for exploratory laparoscopy and had widespread superficial endometriosis covering her uterus, ovaries, and bowel surface. The lesions were all smaller than a centimeter and pale, making them nearly invisible without careful inspection under magnification. This leads to the uncomfortable truth about surgical diagnosis. The skill and experience of the surgeon matters enormously. Studies show that non-specialist surgeons miss between 40 to 70 percent of endometriosis lesions during laparoscopy. This isn't because the lesions are inherently invisible. It's because superficial and atypical presentations don't look like the textbook descriptions. You need someone who knows what to look for, who understands that endometriosis isn't always the classic blue-black powder burn lesion. Some implants are clear, white, red, pink, or even brown. Some appear as flat patches. Others form nodules that distort normal anatomy. A thorough surgical evaluation takes time. If a surgeon spends ten minutes looking and says they found nothing, that conclusion is unreliable.
Management strategies fall into several categories, and no single approach works for everyone. The first line for many people is hormonal suppression. Combined oral contraceptives, progestins like norethindrone or dienogest, and levonorgestrel-releasing intrauterine devices all work by suppressing ovulation and thinning the endometrial lining. This reduces the cyclic bleeding and inflammation that drive pain. For some, this is sufficient. For others, the side effects are intolerable or the pain breakthroughs remain severe. I worked with a patient who tried four different hormonal treatments over three years. Each one reduced her symptoms somewhat but caused significant side effects like depression, weight gain, or loss of libido. She ultimately chose surgery over continuing to cycle through medications that barely helped. Surgical excision is the preferred approach when intervention is needed, and there's an important distinction between excision and ablation. Ablation burns or cauterizes the surface of lesions. Excision cuts them out entirely with negative margins. Multiple studies show that excision has significantly lower recurrence rates compared to ablation. The key trial published in the journal Fertility and Sterility found that recurrence after excision was roughly half that of ablation over a two-year follow-up period. This matters because repeat surgeries carry progressively higher risks of complications, including organ damage and adhesions. The ideal outcome is complete removal of all visible disease in a single procedure, though achieving that depends heavily on disease extent and surgical expertise. I encountered a particularly stubborn case involving a patient with recurrent left-sided pelvic pain who had undergone two prior laparoscopies. Both were reported as showing only "mild endometriosis" and treated with ablation. She returned with worsening pain that now included painful bowel movements during her period. When I reviewed her operative reports from the earlier surgeries, the descriptions were vague. There were no detailed drawings or anatomical maps of where lesions were found. This is a common problem. Many surgeons document endometriosis poorly in operative notes, making it nearly impossible for subsequent providers to understand what was actually treated and what was missed. In this patient's case, a detailed pre-surgical MRI with endometriosis protocol revealed a deep nodule infiltrating the left uterosacral ligament and approaching the rectosigmoid colon. During surgery, we found extensive disease that had been completely missed on both previous operations, including a deeply infiltrating lesion on the anterior bladder surface that was adherent to the bladder wall. Complete excision of all four sites resolved her symptoms almost entirely.
Get the Full Details

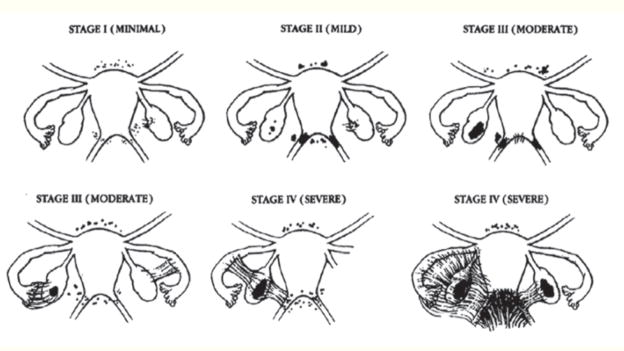
Pain management extends beyond hormones and surgery. Physical therapy focused on the pelvic floor is essential for many patients. Chronic pelvic pain causes pelvic floor muscles to go into sustained spasm, which creates its own layer of pain that compounds the underlying disease. Pelvic floor physical therapy can reduce this secondary muscle tension and improve function. I've seen patients whose pain dropped significantly after six to eight sessions of pelvic floor PT alone, even while their endometriosis was still present. Nerve-related pain is another consideration. The obturator nerve, ilioinguinal nerve, and pudendal nerve can all be compressed or irritated by endometriosis lesions or scar tissue. Nerve blocks can be both diagnostic and therapeutic. A block that eliminates pain temporarily confirms the nerve involvement and can guide targeted treatment. Dietary and lifestyle interventions don't cure endometriosis, but they can meaningfully affect symptom severity for some people. The inflammatory component of endometriosis means that anti-inflammatory approaches may help reduce pain flares. Some patients report improvement with an anti-inflammatory diet, regular gentle exercise, and stress reduction techniques. The evidence base for these approaches is weaker than for medical or surgical treatment, but they're low-risk adjuncts that don't hurt. I generally advise patients to track their symptoms alongside any dietary changes for at least three months before drawing conclusions. What works for one person may do nothing for another. Fertility is a major concern for many endometriosis patients, and the relationship between the disease and infertility is complex. Endometriosis can impair fertility through multiple mechanisms. Anatomical distortion from adhesions can prevent the ovary from releasing an egg into the fallopian tube. The chronic inflammatory environment can affect egg quality, sperm function, and embryo implantation. Endometriomas can damage ovarian reserve, and surgery to remove them carries its own risk to ovarian tissue. The American Society for Reproductive Medicine stages endometriosis from I to IV based on the extent and location of disease, but stage doesn't reliably predict fertility outcomes. Someone with stage 1 can have significant difficulty conceiving, while someone with stage 4 might conceive spontaneously. When fertility is the goal, the approach depends on age, ovarian reserve, and disease extent. Laparoscopic excision can improve natural conception rates in mild to moderate cases. For more advanced disease or when other fertility factors are present, assisted reproductive technologies like IVF are often recommended.
There's a critical limitation I need to be honest about. Even with expert surgical excision, recurrence rates range from 20 to 40 percent within five years. This isn't because the surgery failed. It's because microscopic disease can remain behind, or new lesions can develop from existing implants that were too small to visualize. Hormonal suppression after surgery can reduce recurrence risk, but it's not a guarantee. Some patients require multiple surgeries over their lifetime. This is an unfortunate reality of the disease, and it's important that anyone considering treatment understands this upfront rather than discovering it later. Hysterectomy is sometimes discussed as a definitive treatment, but it's important to be clear about what it does and doesn't do. Removing the uterus eliminates menstrual bleeding and can reduce pain related to uterine contractions, but it does not remove endometriosis lesions that are located on other organs like the bowel, bladder, or pelvic sidewall. If endometriosis implants remain elsewhere in the pelvis, pain can persist after hysterectomy. The procedure is most appropriate for people who have completed childbearing, have failed conservative treatments, and have uterine-dominant symptoms. Ovarian hormone suppression after hysterectomy is also typically recommended to prevent any remaining implants from being stimulated. If you're navigating this diagnosis, the practical steps that matter most are finding a surgeon who specializes in excision rather than ablation, getting a detailed pre-surgical mapping with an endometriosis-savvy radiologist, and assembling a multidisciplinary care team that addresses pain, fertility, and quality of life simultaneously. The system makes this harder than it should be, but the information is out there if you know where to look and what questions to ask.